How to actually get through dosage calc without second-guessing every decimal
Most nursing programs make you take a Med Math Dosage Calculations test before you touch a patient. It's usually a two-hour sit-down exam with about 25 to 30 problems on it. The problems themselves aren't hard, but the format is designed to catch people who skip steps or don't write their work down. I watched a student fail twice because she was doing everything in her head. She got the right answer on the third attempt after she forced herself to write out every conversion. The core mechanic is dimensional analysis, sometimes called the factor-label method. You line up fractions so the units cancel out and you're left with only the unit you need. It sounds academic until you realize it's the same thing hospitals use when they set up IV drip rates or weight-based pediatric doses. The reason people mess it up isn't because they can't do fractions. It's because they set up the problem wrong at the start and then spend ten minutes trying to fix it instead of catching the error immediately.
Med Math Dosage Calculations
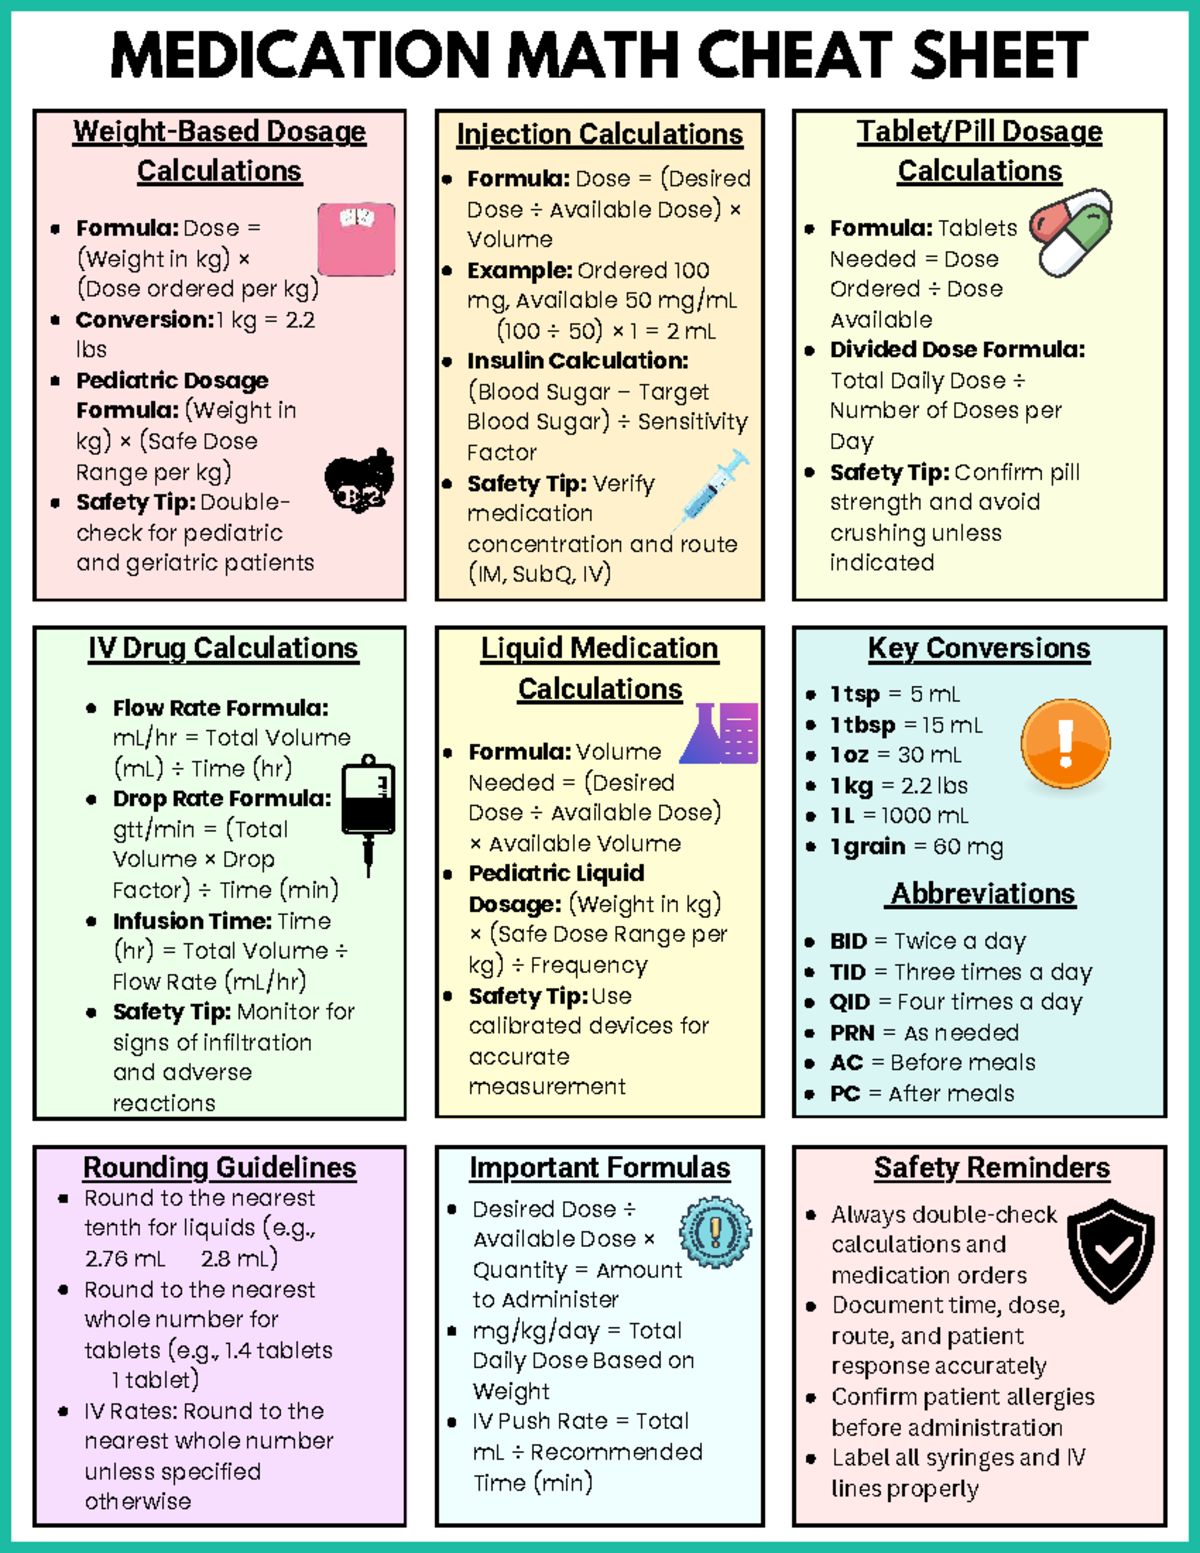
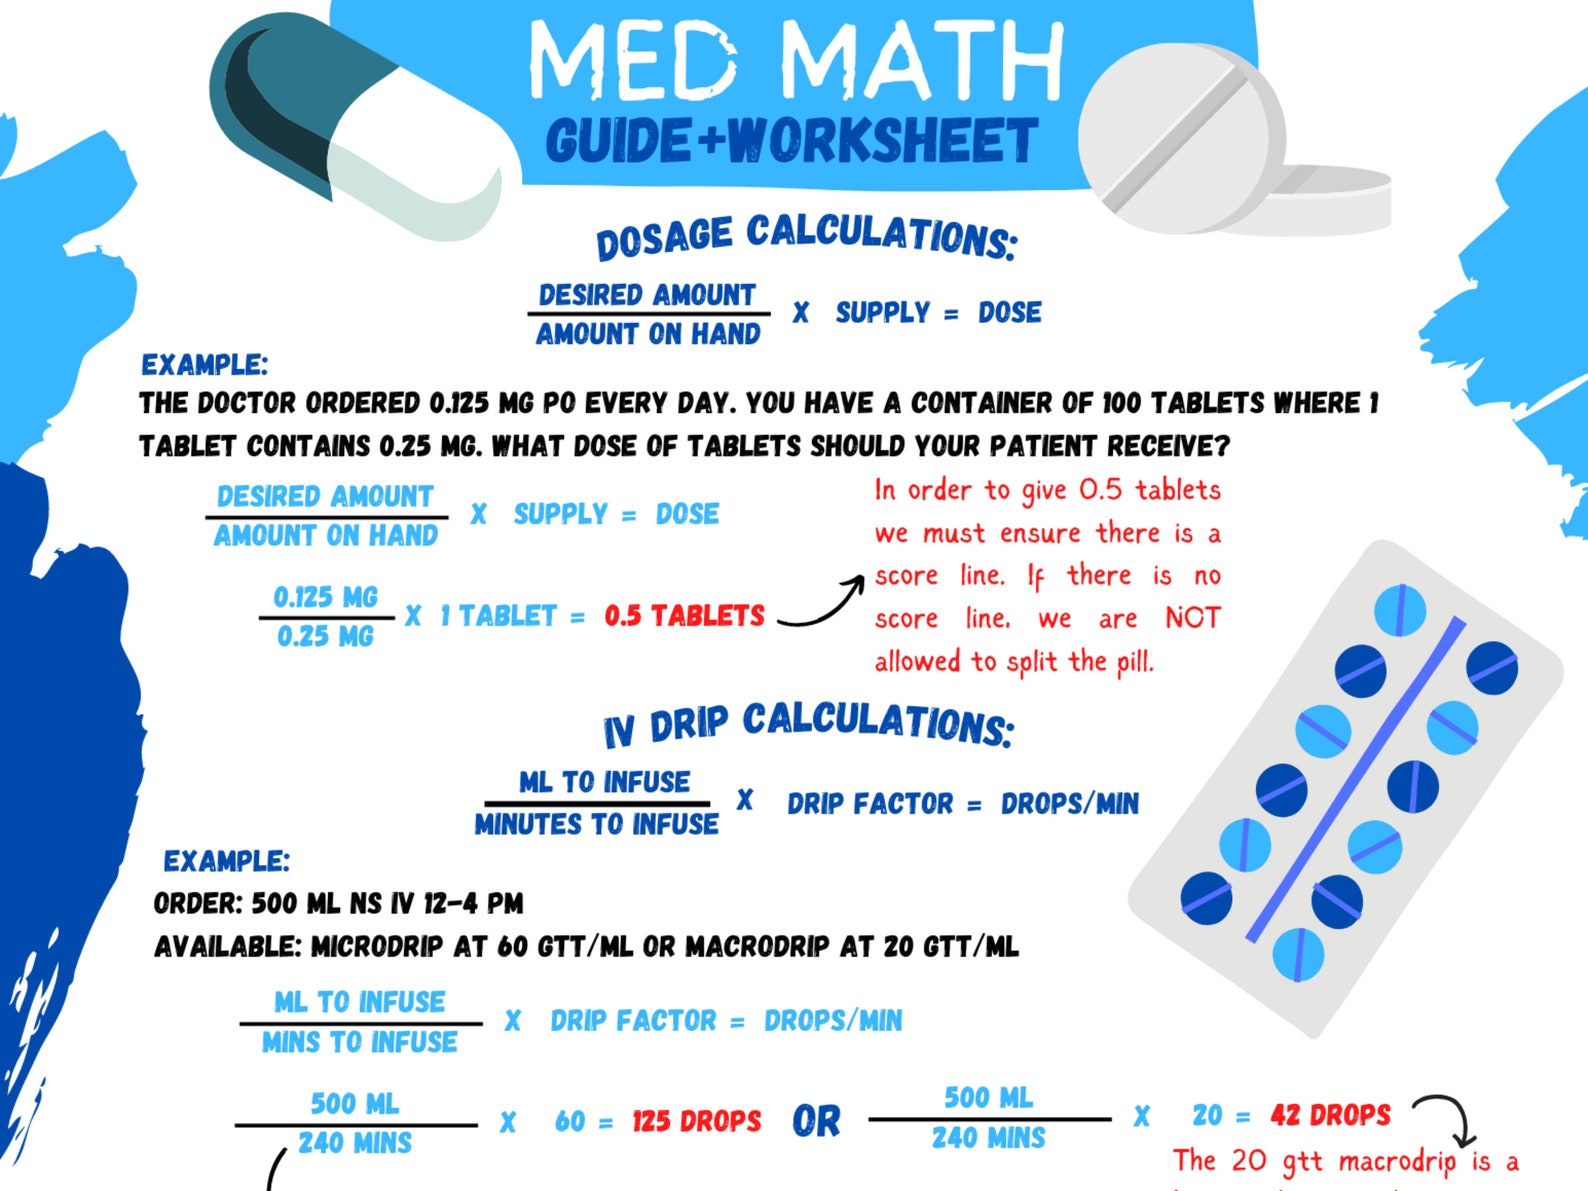
Start every problem by writing what you have and what you need. That's it. Don't jump into any formula. Put the given information on one side and the target unit on the other, then fill in the conversion factors between them. I keep a small notebook where I write out my setup for each problem before I do any arithmetic. This takes about 30 seconds per problem and prevents maybe 80 percent of the mistakes I see in practice. Most people skip this and just start multiplying numbers they're not sure about. The two main problem types you'll see are the basic dose calculation and the IV flow rate calculation. The basic dose one gives you an ordered dose and a supplied dose and asks how many tablets or milliliters to administer. The IV flow rate one gives you a volume, a time, and a drop factor and asks for drops per minute. There are more complex variants involving weight-based dosing and continuous infusions, but they just layer on extra conversion factors. Here's a basic dose example. The order is for amoxicillin 500 mg. The supply is 250 mg per tablet. You set it up as 500 mg times 1 tablet over 250 mg. The milligram units cancel. You're left with 500 over 250, which is 2 tablets. That's the straightforward case. Things get messy when the order is in grams and the supply is in milligrams, or when you have to convert kilograms to pounds first for a pediatric dose.
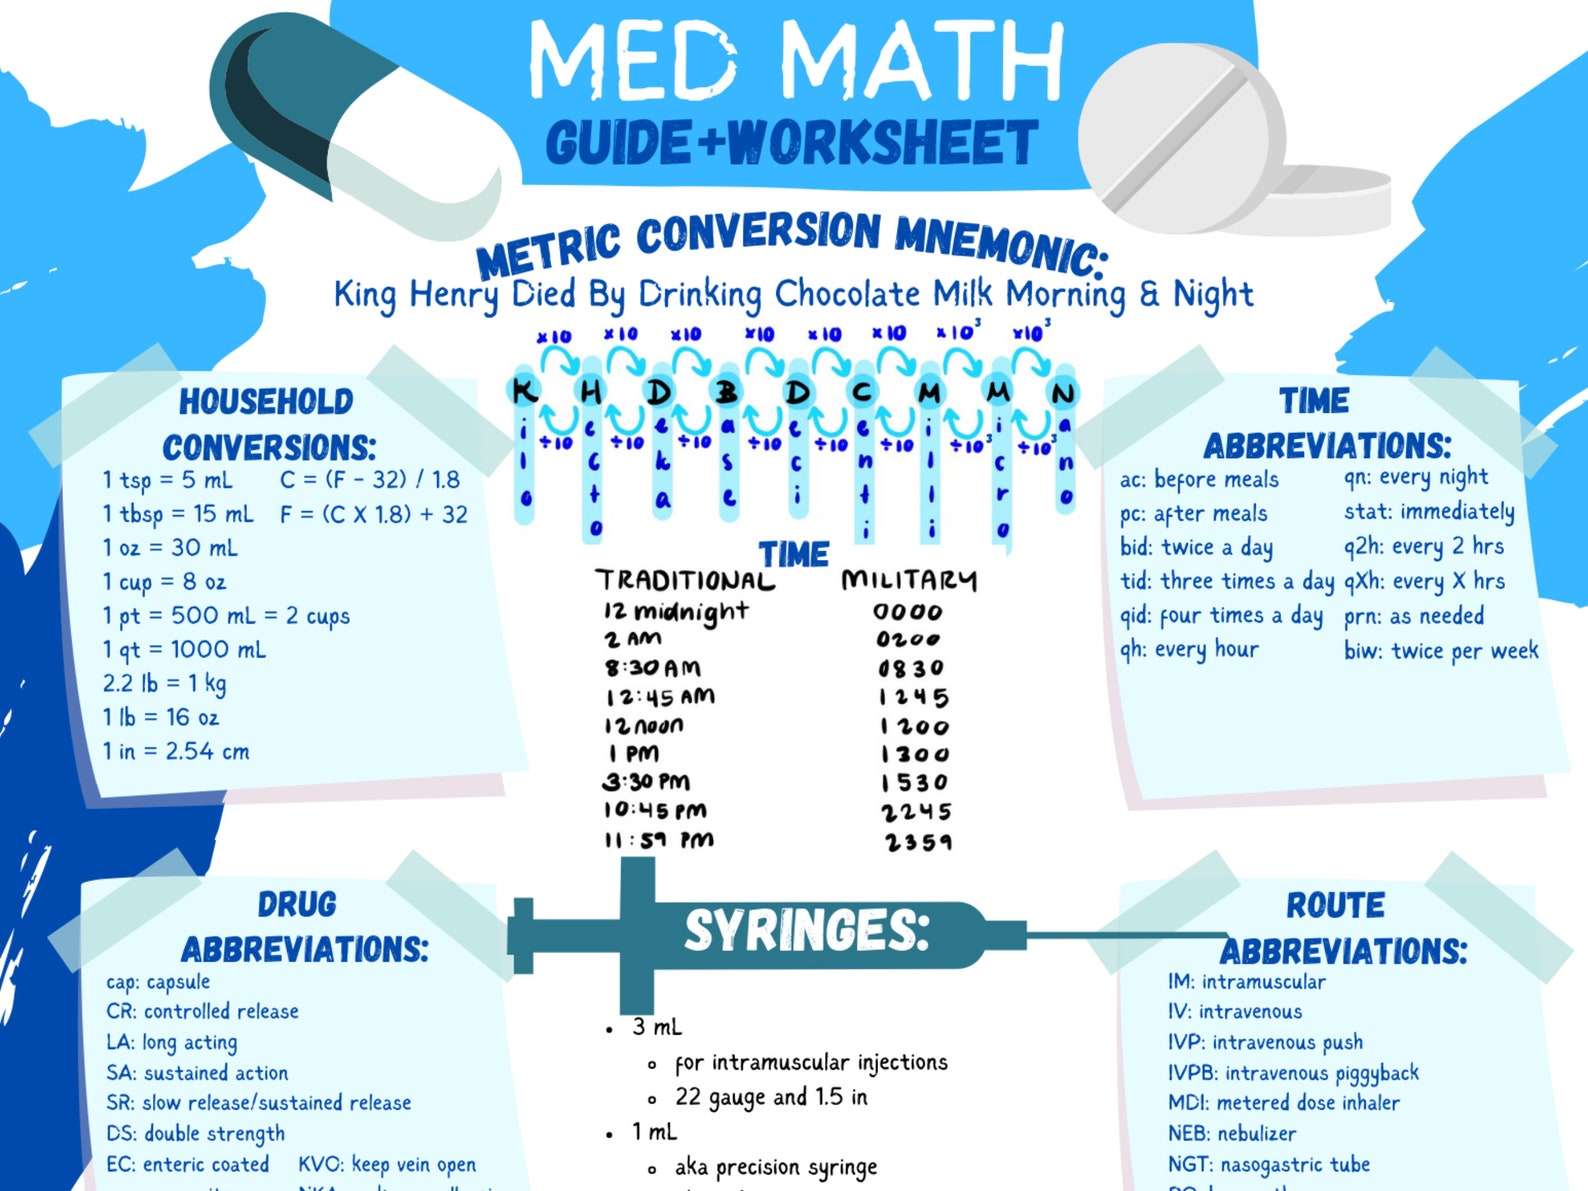
The conversion tables you need to know cold are the ones for kilograms to pounds, grams to milligrams, milliliters to teaspoons, and hours to minutes. You should be able to move between these without thinking. If you're pausing to look up how many milligrams are in a gram during the test, you've already lost time. I memorized these by writing them on a single index card and keeping it visible at my desk for two weeks. It took maybe 20 minutes total of real study time. One thing nobody warns you about is the microgram versus milligram trap. Orders for levothyroxine or certain cardiac drugs are often in micrograms, and the supply may be listed in milligrams. If you miss that prefix difference, your answer will be off by a factor of 1,000. I've seen that happen on practice tests repeatedly. The fix is to always write out the full unit before you start cancelling anything. Never write just "mg" if there's a chance it could mean microgram in the problem. Write mcg or g to distinguish it. For IV drip calculations, the formula is drops per minute equals volume in milliliters times the drop factor divided by time in minutes. The drop factor is printed on the IV tubing packaging. It's usually 10, 15, or 60 drops per milliliter for macrodrip sets, and 60 for microdrip. If the order says 1,000 mL of normal saline over 8 hours with a 15 gtt/mL set, you convert 8 hours to 480 minutes first, then multiply 1,000 by 15 and divide by 480. That gives you about 31 drops per minute.
Get the Full Details

Weight-based dosing is where most people stall out. The typical setup is something like a child weighing 44 pounds needs a medication dosed at 10 mg per kilogram per day. You convert 44 pounds to kilograms by dividing by 2.2, which gives you 20 kg. Then you multiply 20 by 10 to get the daily dose of 200 mg. If the order is divided into three equal doses, you divide 200 by 3 to get about 66.7 mg per dose. The math is simple. The issue is usually the unit conversion at the beginning or forgetting to divide the total daily dose into individual administrations. I ran into a specific problem once on a clinical rotation that highlighted a gap in how these are taught. A patient was ordered vancomycin at 15 mg per kilogram every 12 hours. The pharmacy dispensed it as a powder that needed to be reconstituted to a concentration of 40 mg per milliliter. The patient weighed 72 kilograms. The dose calculation itself was fine, but the reconstitution step meant the actual volume to draw up depended on both the weight-based dose and the concentration. I calculated the total dose as 1,080 mg, then divided by 40 to get 27 mL per dose. What tripped me up initially was that I'd mentally separated the two steps and nearly double-calculated the weight conversion. Once I wrote both steps on the same line with a single setup, the error disappeared. Continuous infusion calculations follow the same dimensional analysis principle but add another layer. You might be asked to find the milligrams per minute delivery rate when the bag contains 2 grams in 500 mL and the pump is set at 30 mL per hour. You convert grams to milligrams, then use the concentration to find how many milligrams are in each milliliter, then multiply by the hourly rate and divide by 60 to get minutes. The setup looks like this: 2 grams becomes 2,000 mg. 2,000 mg over 500 mL gives you 4 mg per mL. At 30 mL per hour, that's 120 mg per hour, or 2 mg per minute. Four steps, but each one is a single conversion factor.
There's a common shortcut that people pick up called the formula method, which uses ratios like desired over havens times quantity. It works fine for simple problems but breaks down when you have multiple unit conversions or when the supply concentration needs to be derived from a reconstitution step. Dimensional analysis handles those cases without switching methods. I recommend committing to dimensional analysis from the start even if your textbook presents both. It reduces the chance of using the wrong formula for a problem type you haven't seen before. The biggest time sink in these exams is setting up the problem correctly under pressure. I timed myself during practice and found that writing out the full dimensional analysis setup for a standard problem took about 45 seconds. Doing the arithmetic took another 30 to 60 seconds depending on whether the numbers divide evenly. Problems with triple conversions can take two to three minutes for the setup alone. If you're spending more than five minutes on any single problem, you're probably overthinking or you set it up wrong and are trying to back into the answer. Practice problems from standard sources like the nursing drug handbook or online calculators are useful, but they don't replicate the fatigue factor of a timed exam. I recommend doing a full 30-problem set under actual test conditions at least once before the real thing. Set a timer for two hours, sit at a table with only a calculator and scratch paper, and don't pause. The fatigue changes how you read the problems. Late in a session, a question asking for micrograms per minute can look identical to one asking for milligrams per hour if you're not reading carefully.
A counter-intuitive thing about these tests is that writing more work actually makes you faster. People who try to do mental math to save time often end up going back to check their work, which costs more time overall. The students who finish first are usually the ones who write out every conversion factor and every intermediate result. It's not elegance. It's a verification system built into the process. Another thing that catches people is rounding. Some programs want you to round to the nearest whole number for tablet counts and to one decimal place for liquid doses. Others want two decimal places for everything. If you round too early in a multi-step problem, your final answer can drift enough to be marked wrong even though your method was correct. Keep all decimals through the calculation and round only at the very end. For the IV pump problems, make sure you know whether the question asks for milliliters per hour or drops per minute. These are different things. A pump delivers mL/hr automatically. Drops per minute only matters for gravity drips where you count manually. I've seen students calculate the drop rate for a pump order and then write that as their final answer when the question wanted mL/hr. The numbers were right. The unit was wrong.
If you want practice materials, most community college nursing pages and sites like the Purdue OWL nursing math section have free worksheets. The Texas Technical University health science department also publishes a set of dosage calculation practice problems with answer keys. I used those during my prep and found the answer explanations to be more useful than most commercial test prep books. They show the setup, not just the final number. The method has clear limitations. Dimensional analysis doesn't help you catch a misread order. If the physician writes 0.5 mg and you read 5 mg, no amount of correct setup will protect you. That's why the habit of reading the order twice, especially for high-alert medications like insulin, heparin, and opioids, matters more than any calculation technique. The calculation is the easy part. The reading part is where most real-world errors happen. Also, these methods assume clean numbers. In clinical practice, you'll encounter concentrations that don't divide evenly and weights that require extended decimal conversion. The test environment hides this by using round numbers. Don't let that create false confidence. When you're actually drawing up medication, the numbers won't be forgiving.
For the actual test, bring a basic scientific calculator if allowed. Some programs permit it and some don't. Check the syllabus. A calculator speeds up the division and multiplication but it won't help with setup errors. If you're doing the problems by hand, a simple four-function calculator is sufficient. The math rarely goes beyond multiplication, division, and decimal conversion. One last thing that isn't talked about enough is the anxiety component. People who freeze during these exams often know the material. They just can't access it under time pressure. The workaround is repetition under realistic conditions. Do enough problems that the setups become automatic, and the anxiety drops because your brain isn't reconstructing the method from scratch each time. After about 50 practice problems, the patterns start to look familiar and the process feels less like solving and more like following a recipe.