Understanding the noise before you look for the signal
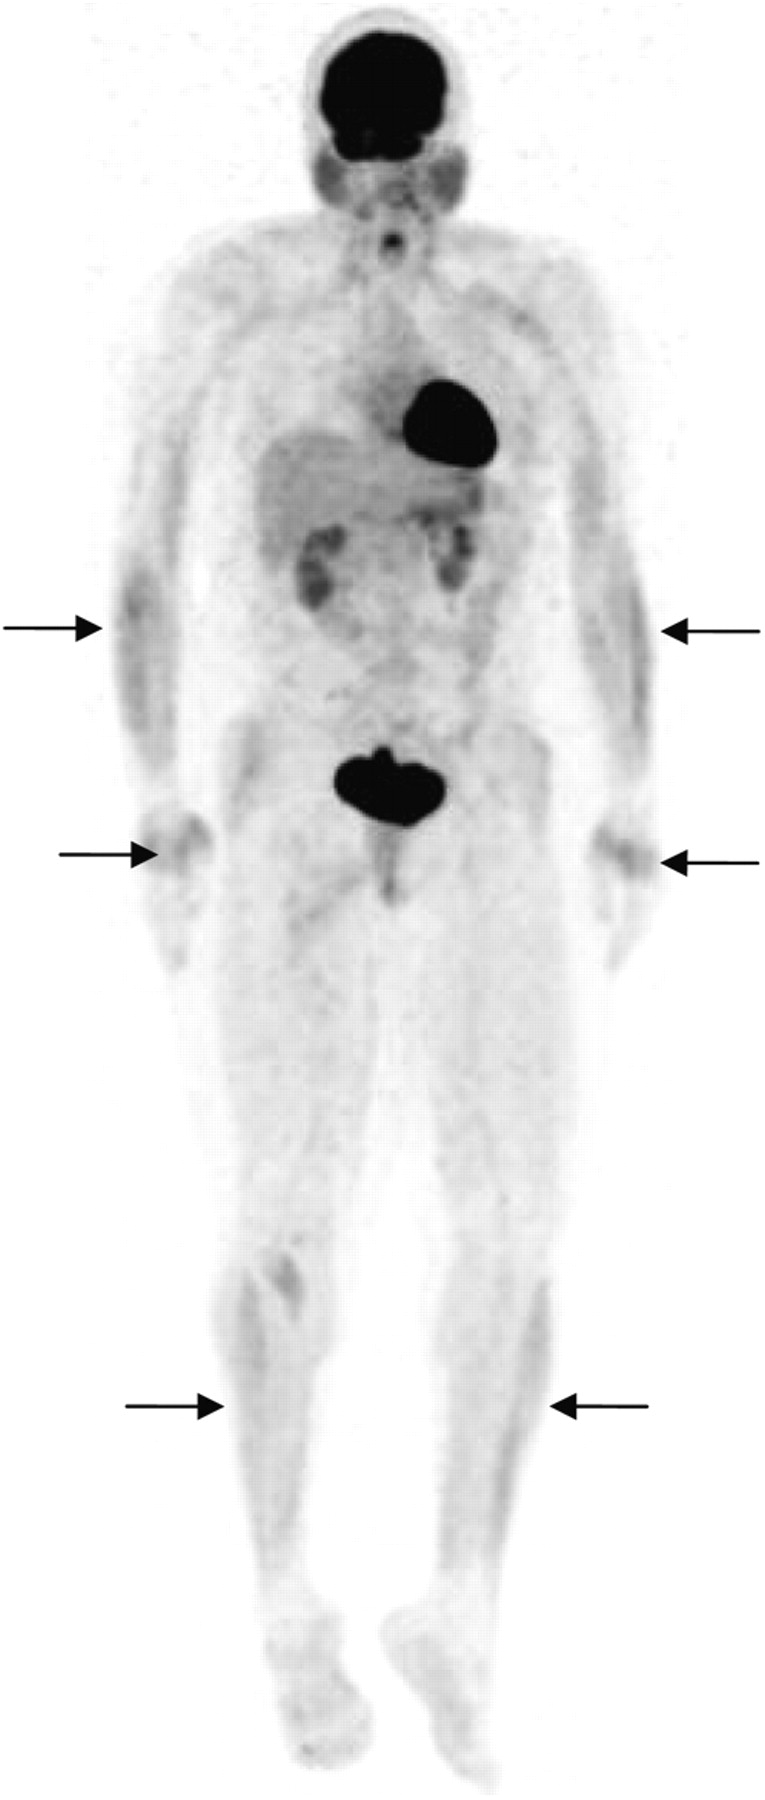
PET scans aren't magic. They're measurements of radiotracer concentration at a specific moment in time, and that tracer goes where the body tells it to go whether you want it to or not. Physiologic uptake is just the background music of normal biology playing at full volume. If you don't know what normal looks like, you'll mistake a yawn for a scream every single time. I've been reading oncologic PET/CTs since before hybrid scanners were common, and the hardest skill isn't spotting disease. It's ignoring the stuff that isn't disease. The brain eats glucose like nobody's business. The kidneys dump it. The bladder becomes a glowing furnace. These are not findings. They are features of the exam.
What Is Physiologic Uptake On Pet Scan
Physiologic uptake refers to the normal, expected distribution of a radiotracer through the body's organs and tissues. With FDG—the fluorodeoxyglucose tracer used in the vast majority of oncology scans—this means any tissue that normally metabolizes glucose at a measurable rate. Intensity varies. Brain and myocardium are typically high. Liver is moderate. Renal excretion creates the highest concentrations because the tracer is cleared through the urinary system. The nuance most people miss is that "normal" is not a fixed template. It's a range that shifts dramatically based on patient preparation, blood glucose, body temperature, recent physical activity, and even the season. A scan done at 7 AM on a patient who slept poorly and walked briskly to the clinic looks fundamentally different from one done at 2 PM on a fasted, rested patient. Both can be entirely normal.
Why this matters in actual practice
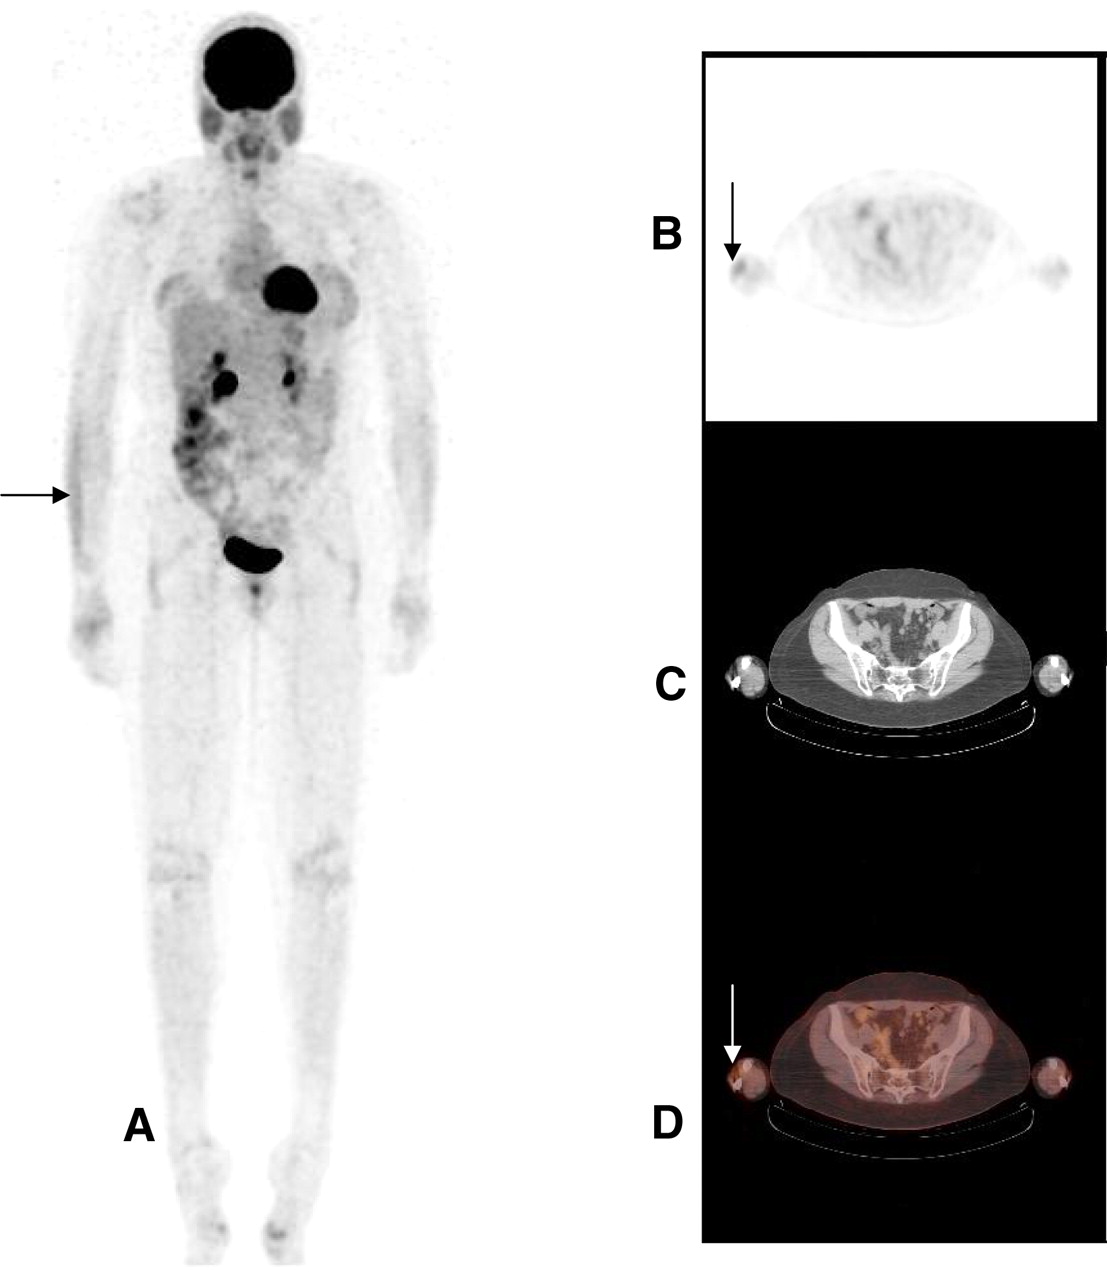
Here's the thing that gets people in trouble: physiologic uptake mimics pathology far more often than pathology mimics physiologic uptake. The distribution patterns overlap enough that a careless reader will flag normal bowel activity as peritoneal disease or bilateral parotid uptake as lymphoma. The fix is simple but requires discipline—always cross-reference the CT component. If the PET hot spot corresponds to normal anatomy on CT with no mass effect, nodal architecture distortion, or abnormal soft tissue, it's almost certainly physiologic. Brown fat activation is a persistent headache. It shows up as symmetric linear or nodular uptake in the supraclavicular, paratracheal, and paraspinal regions. On a hurried read it looks like lymphadenopathy. On CT it's fat attenuation. I have a protocol now where I specifically check the soft tissue windows at the neck before signing out any study, and I've learned to suspect brown fat whenever the uptake is bilateral and follows the expected anatomic distribution of adipose tissue. Myocardial uptake is another trap. Without proper prep—typically a high-fat, low-carbohydrate load followed by fasting—the heart toggles between fatty acid and glucose metabolism unpredictably. The result is patchy, variable uptake that can look like infarction, myocarditis, or even pericardial disease. Some centers routine preps their cardiac oncology patients to suppress this. Many don't. When you see it and the patient wasn't prepped, the right call is usually to note it and move on rather than chase it.
Get the Full Details

I once spent two weeks chasing what I thought was a suspicious focal uptake in the right parotid gland. It turned out the patient had been chewing gum during the uptake phase. Unilateral masticatory muscle uptake can localize surprisingly well and create a focal-appearing hotspot that mimics a parotid lesion. The CT showed normal parotid parenchyma. Striated muscle enhancement on the delayed phase confirmed it. That case changed how I think about every superficial head and neck finding.
Common pitfalls and where the method breaks down
Physiologic uptake interpretation has real limitations. It is inherently subjective. Two qualified readers will disagree on borderline findings more often than anyone admitted in training. The symmetric uptake pattern rule works most of the time but has well-documented exceptions—unilateral renal compensation, asymmetric brown fat activation, and focal muscle uptake from injection site contamination all exist. Attenuation correction artifacts create false-positive uptake. The most common is at the diaphragm-liver interface where respiratory mismatch between the CT and PET slices creates artificial hot or cold spots. Dental work produces streak artifacts that can obscure or fake uptake in the mandible and surrounding soft tissues. These artifacts don't follow biologic logic, which is usually how you catch them, but catching them requires knowing they're possible in the first place. The biggest practical limitation is that physiologic uptake cannot reliably distinguish benign from malignant when the patterns overlap. Inflammation from recent surgery, infection, or granulomatous disease takes up FDG with exactly the same mechanism as tumor. A post-surgical bed at six weeks is essentially impossible to interpret on FDG PET alone. You need clinical context, comparison to prior imaging, or alternative tracers. There is no PET-based shortcut around that.
When physiologic patterns become truly unreliable—diffuse inflammatory states, high blood glucose above 200 mg/dL which competitively inhibits FDG uptake, or when the clinical question hinges on distinguishing scar from recurrence—the scan itself may be non-diagnostic. In those cases, recommending MRI with contrast or a different radiotracer like FLT or choline-based agents is often more useful than pushing for another FDG study six weeks later.

A practical workflow
Start with the CT. Establish what normal anatomy looks like for that patient before you touch the PET. Note organ size, symmetry, and any structural abnormalities. Then bring up the PET and ask where the tracer is going. Map each area of uptake to its anatomic correlate. If it matches expected physiology, file it as such. If it doesn't match, if it's asymmetric in a way that breaks the pattern, if it sits in a location without a normal excretory or metabolic pathway, that's when you dig deeper. Document your reasoning. Not for anyone else. For yourself, six months from now when you're looking at a follow-up scan and wondering whether that questionable spot was real or just normal variant #47. Writing it down forces clarity and creates a reference point that's worth more than any memorized uptake chart.