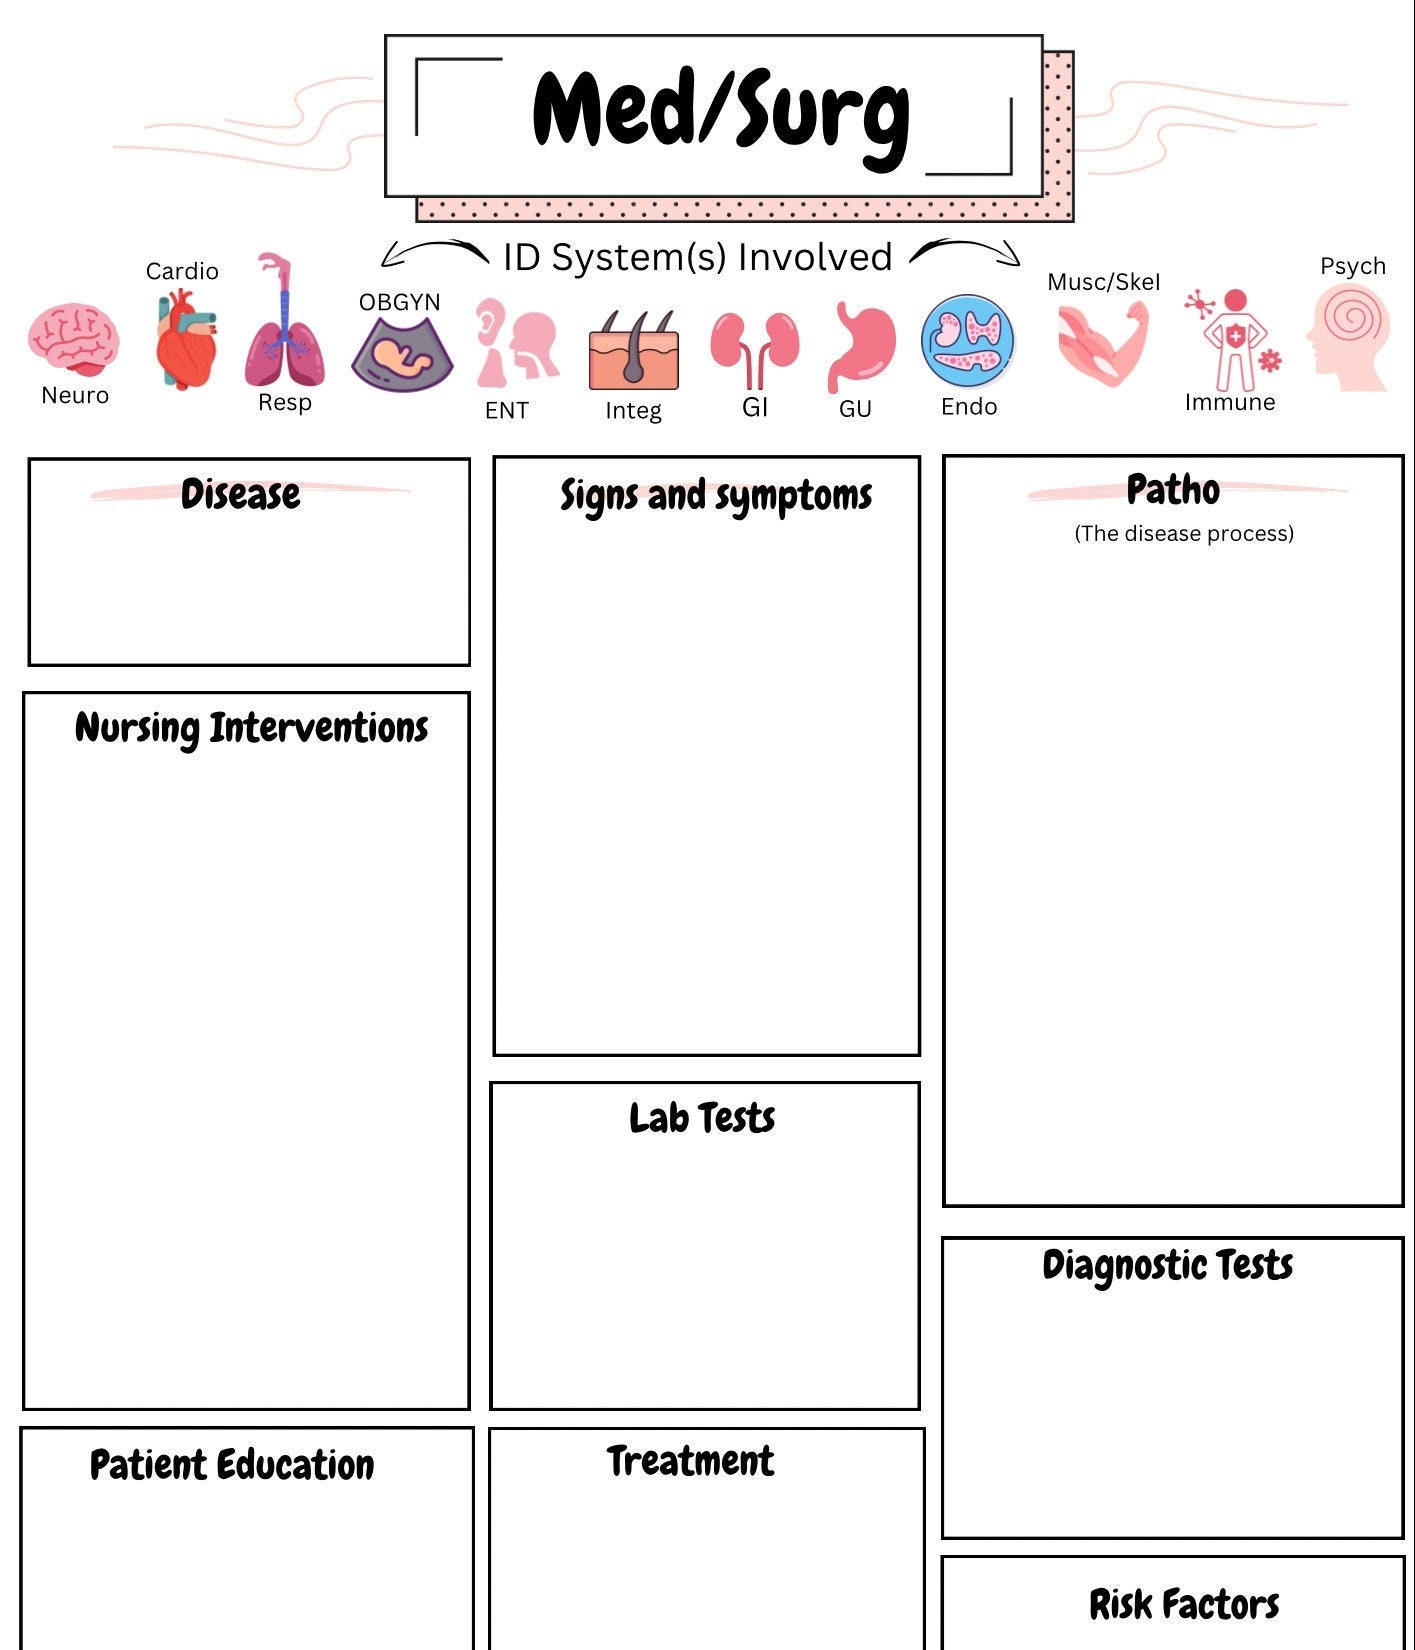
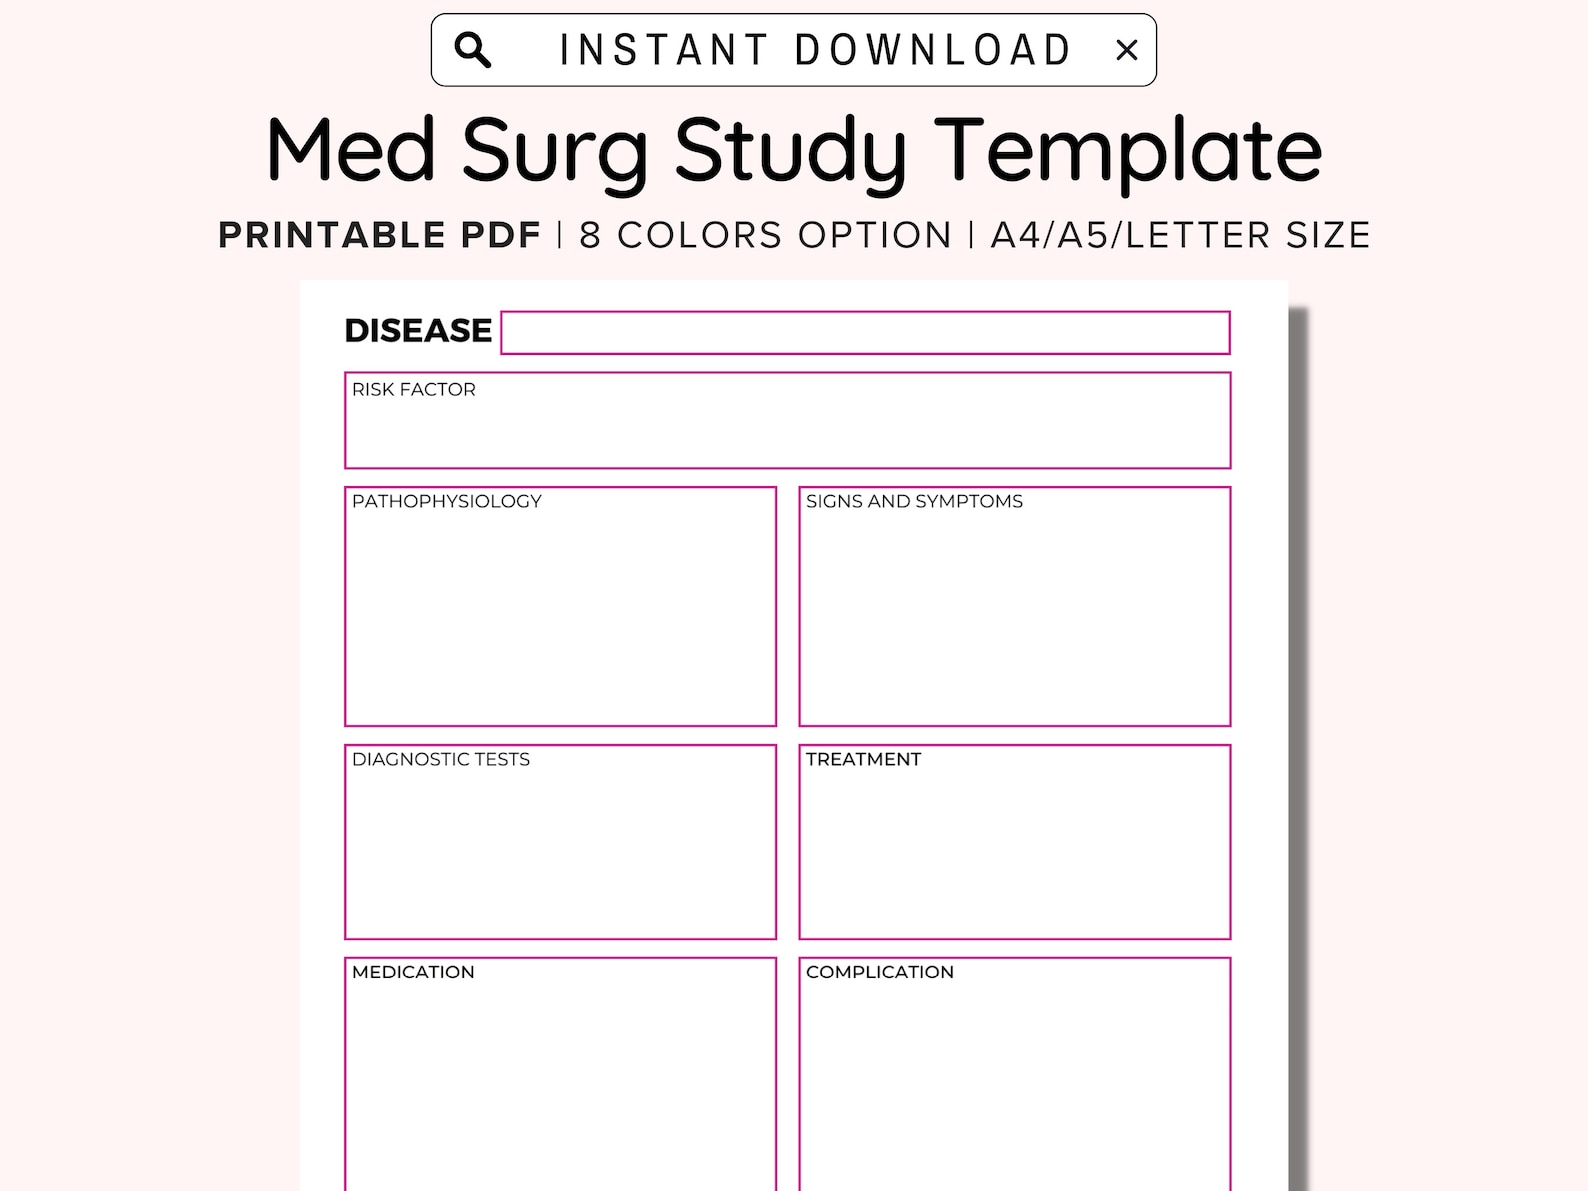
Med Surg Study Template Free: Why Most Templates Suck and How to Fix Yours
I spent three years in acute care med-surg before moving into nursing education, and I see the same broken templates get passed around every semester. Students download them, fill in the blanks, and still fail their case studies because the template forces them to think linearly when patients don't present that way. A Med Surg Study Template Free is useful if you understand what it's actually good for and what it's terrible at. Here's how to make one that doesn't waste your time.
Getting Started with a Med Surg Study Template Free
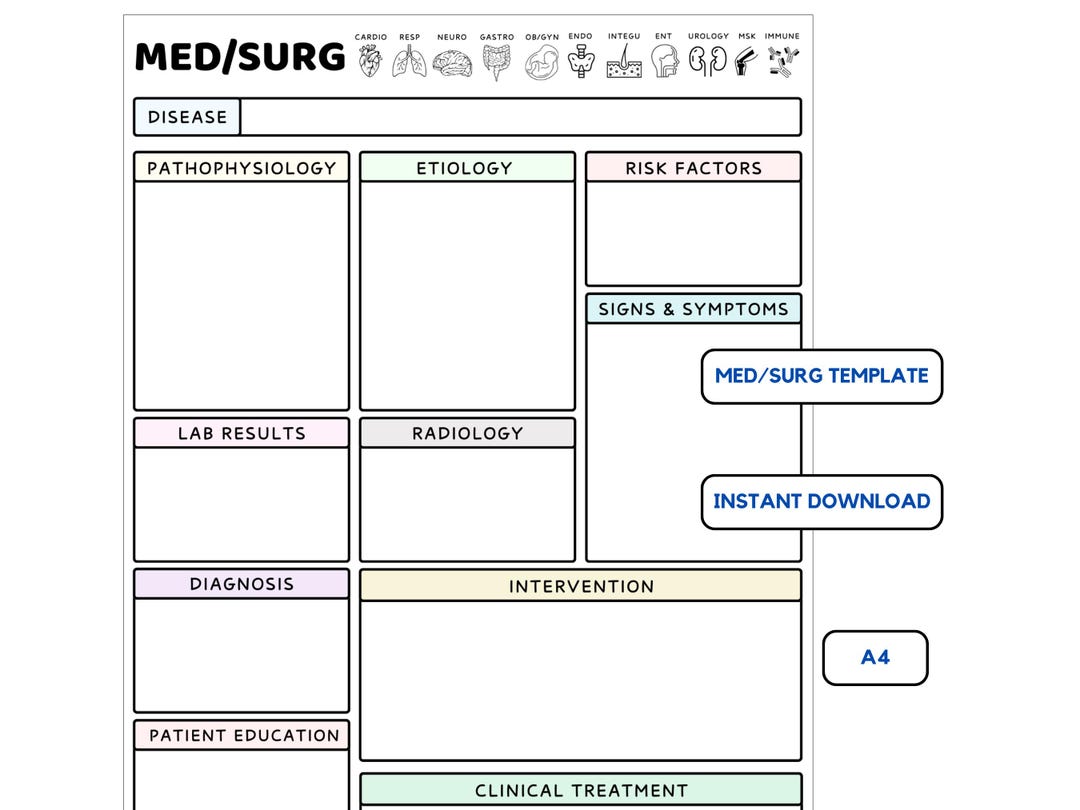
The structure most free templates use is basic disease-process assessment interventions. That covers maybe sixty percent of what you actually need. The missing forty percent is usually what separates a passing grade from a mediocre one. Start with the patient scenario. Don't start with the textbook disease. I always tell my students to write out the patient's chief complaint, age, comorbidities, and medications in one paragraph first. Everything else flows from that. If you skip this step, your template becomes a generic nursing paper that could apply to any patient with any condition. Here's what a functional template section looks like in practice:
Admission Data: Age, primary diagnosis, secondary diagnoses, current medication list with doses, allergies, code status, recent labs within 24 hours, fluid balance from last shift. Assessment Focus: Not just "do a head-to-toe." Pick three systems you actually need to prioritize based on the primary diagnosis and write why. If the patient has pneumonia and diabetes, lungs and blood glucose matter more than bowel sounds, even though bowel sounds are part of every assessment. Clinical Reasoning Bridge: This is the section most free templates omit entirely. Connect your assessment findings to your diagnosis. Show the pathophysiology link. Why does this patient have elevated WBC? Why is the glucose unstable? Write two sentences that prove you understand the mechanism, not just the symptom.
Get the Full Details

Nursing Interventions: Split into independent and collaborative. Independent means things you do without an order. Collaborative means you need a provider involved. Students conflate these constantly, and it shows up as point deductions.
The Pathophysiology Section Nobody Gets Right
Here's a counter-intuitive thing: most students write pathophysiology like they're summarizing a textbook chapter. They don't. In med-surg, the instructor wants to see you connect the pathophysiology to the specific lab values and symptoms in front of you. Instead of writing "Diabetes mellitus is characterized by hyperglycemia due to insulin deficiency," write something like: "The patient's Type 2 diabetes with poor control (HbA1c 9.2%) contributes to impaired wound healing and increased infection risk, which is relevant given the post-operative status and elevated WBC of 14.2." That's the difference. One gets you a C. The other gets you an A- minimum. The template should have a dedicated box for this bridge section, not just a generic pathophysiology paragraph that could be copy-pasted from any source.
Medication Management: The Hidden Trap
Medication sections in most free templates are just drug tables. Name, dose, route, frequency, indication. That's not wrong but it's insufficient. You need to include monitoring parameters specific to that drug in that patient's context. For example, if the patient is on vancomycin, the template should prompt you to document trough levels, renal function trends, and infusion site monitoring. Generic drug info is everywhere. Context-specific monitoring is what makes a study template actually useful for clinical decision-making. I also add a column for "What would make me call the provider?" Each medication should have one or two specific triggers. For IV insulin drips, that might be a blood glucose drop below 70 despite dextrose intervention. For heparin infusions, it's an aPTT consistently above therapeutic range after the first dose adjustment. These aren't in the textbook. They're clinical judgment markers.
My Specific Problem with Standard Templates and the Workaround
Last year I was grading case study submissions and noticed a pattern. Students were using free Med Surg Study Template Free resources that had separate sections for "Lab Values" and "Assessment Findings" but never cross-referenced them. A student would list potassium at 3.1 in the lab section and then write "cardiac assessment unremarkable" in the assessment section. Two disconnected boxes, zero clinical synthesis. My workaround was simple. I modified the template to add a color-coded reference system. Lab abnormalities get flagged in red, and every assessment finding that relates to a lab value must be linked with a bracketed reference like [K+ 3.1]. Now when I read through the paper, I can instantly see if the student is connecting data points or just filling boxes. It takes about ten extra minutes to set up initially but cuts my grading time by roughly half because the reasoning is visible on the page. Another issue: most templates don't account for shift handoff dynamics. In real med-surg, your assessment and priorities change dramatically between day shift and night shift. I added a small optional section for "Shift Change Considerations" that prompts students to note what would be different in their assessment if they were taking over care at 7 PM versus 7 AM. Vital sign frequency, IV drip priorities, wound check timing — these shift-based considerations are rarely in any free template I've seen, and they're clinically significant.
What This Approach Misses
No template replaces actual clinical hours. A beautifully structured study template cannot compensate for someone who hasn't physically assessed a patient with a specific condition. I've seen students ace case study grades using templates while struggling to place a peripheral IV or recognize early sepsis signs at the bedside. The template is a learning scaffold, not a substitute for clinical competence. Additionally, these templates work well for straightforward med-surg cases but break down with complex multi-morbidity patients. When a patient has COPD, CHF, and Stage 3 CKD simultaneously, no single template format captures the competing priorities effectively. In those situations, I recommend switching to a problem-list-driven approach instead, where each active issue gets its own assessment-intervention-monitoring cycle rather than forcing everything into one linear template. If you want something to start with today, search for a basic nursing case study template and strip out everything except the assessment focus section and the clinical reasoning bridge. Build from there. The rest is filler that slows you down more than it helps you.