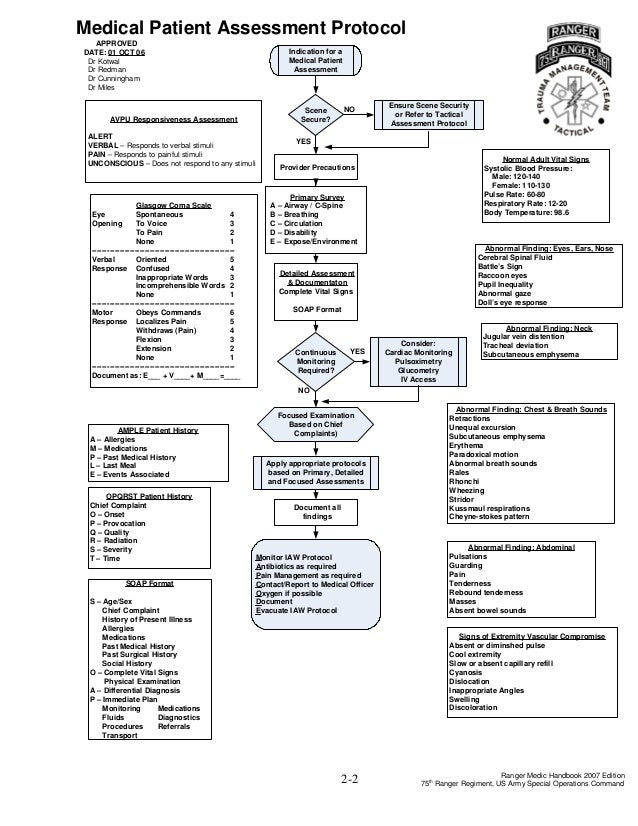
Why Most EMT Cheat Sheets Are Useless in the Field
I spent years trying to force textbook-style assessments into chaotic scenes where nothing matched the algorithm. The Medical Assessment Emt Cheat Sheet most people use starts with SAMPLE history and runs straight into a head-to-toe physical. That works fine when patients are stable and cooperative. It falls apart immediately when you walk into a house and find a patient actively seizing or struggling to maintain an airway. The cheat sheets that actually helped me stopped being checklists and became decision trees instead. You assess what's killing them right now, not what the textbook says should come first.
Building a Medical Assessment Emt Cheat Sheet That Survives Real Calls
Start with your primary assessment and embed decision points inside it rather than treating it as a linear sequence. ABCs are the framework, but you should be checking pulse and breathing simultaneously, not sequentially. One thing that tripped me up early on was patients in shock who have adequate respiratory rates but shallow tidal volumes. Their breath sounds look fine from across the room. The cheat sheet needs to flag that distinction clearly because auscultation alone will mislead you. Here is the structure that actually works during live calls.
Primary Assessment with Embedded Decision Points
Begin with scene safety and mechanism of injury. If the mechanism raises suspicion for spinal involvement, manual inline stabilization happens before anything else, not after your initial impression. This is where most students lose time because they follow the steps in order instead of running parallel tasks with the partner. Level of consciousness should be assessed with AVPU or GCS immediately upon contact. A declining GCS takes priority over every other assessment step. I once missed an intracranial bleed in its early compensatory phase because I was too focused on documenting a perfect neuro check instead of noticing the patient became less responsive between the first and second minute of my assessment. Airway assessment needs to include an evaluation for obstruction sources. Look for foreign bodies, secretions, blood, and anatomical compromise. Snoring respirations indicate partial airway obstruction, not a patient who is simply relaxed. A snoring sound means the tongue or soft tissue is falling back. Insert an oropharyngeal airway and reassess immediately.
Get the Full Details

Breathing evaluation requires three actions at once: inspect rate and effort, listen to bilateral lung sounds, and palpate for subcutaneous emphysema and symmetric chest rise. Unilateral breath sounds with tracheal deviation point toward tension pneumothorax. Needle decompression comes before you finish writing down respiratory rates. Circulation assessment should determine perfusion status using skin condition, pulse quality, and capillary refill. Capillary refill is unreliable in elderly patients and those with peripheral vascular disease. I learned this after wasting valuable minutes checking fingers on a sixty-eight-year-old diabetic with poor perfusion that made capillary refill readings essentially meaningless. Disability follows with a neurological screen. Check pupil size and reactivity, assess motor function on both sides, and document the patient's verbal response. Asymmetrical pupils demand immediate transportation consideration. Unequal pupils in a trauma patient signal possible brain herniation.
Exposure involves removing clothing to identify hidden injuries while preventing hypothermia. Cover the patient immediately after examination. Hypothermia worsens coagulopathy and increases mortality in trauma patients.
Secondary Assessment That Actually Matters
The head-to-toe physical after the primary assessment is where most cheat sheets become bloated. Focus on areas that change management, not areas that generate paperwork. A complete head-to-toe takes four to seven minutes in ideal conditions. In the field, you often have three minutes before transport decisions need to be made. Use the AMPLE history as your anchor, not as an afterthought. Allergies determine medication choices and contraindications. Medications reveal conditions the patient may not volunteer. Past medical history frames your differential diagnosis. Last oral intake matters for surgical risk and aspiration management. Events leading to the present illness provide mechanism clues. Vital signs should be interpreted against the patient's baseline when available. A blood pressure of 150 over 90 means something completely different for a sixty-year-old with known hypertension than it does for a thirty-five-year-old with no recorded history. An elderly hypertensive patient may be in shock at that same blood pressure reading. Their baseline could be 200 over 110, and their body is failing to compensate. This is the single most missed interpretation by EMT students and new grads.

Physical examination should target areas based on the chief complaint and mechanism. For a medical chest pain call, you do not need a thorough posterior lung exam if the patient is diaphoretic, tachycardic, and reporting crushing substernal pain. Your findings will not change the treatment pathway. Treat the presentation, then document thoroughly later. For trauma patients, a detailed log-roll and spinal assessment are non-negotiable. Missed spinal fractures in trauma happen because providers skipped the log-roll due to time pressure. The lateral decubitus position reveals injuries the supine exam misses entirely.
Reassessment and Documentation
Reassessment intervals depend on patient stability. Unstable patients require vital sign reassessment every five minutes or sooner if condition changes. Stable patients can be reassessed every fifteen minutes on basic life support. Critical care transport situations shift these intervals based on protocol and physician direction. Documentation should reflect clinical reasoning, not just checkbox completion. Writing "neck supple" without noting that you actually palpated every cervical vertebra tells someone reading your chart that you may not have performed the examination. Specificity in documentation protects you clinically and demonstrates competence to receiving providers. The patient's response to your interventions matters more than the interventions themselves. If you administered oxygen and the patient's mentation improved, document that improvement. If you positioned the patient and pain decreased, record it. Trends over time are what receiving nurses and physicians look for first.
Limitations and When the Cheat Sheet Fails
No cheat sheet replaces clinical judgment. Here are the scenarios where rigid adherence causes problems. Geriatric patients present with atypical symptoms. A urinary tract infection may manifest as confusion without fever or localized pain. Cardiac ischemia in elderly women frequently presents as fatigue and nausea rather than chest pain. Following a standard cardiac assessment algorithm without broadening your differential delays appropriate diagnosis and treatment. I had a patient we initially treated for dehydration who turned out to be septic from a UTI. The normal blood pressure masked the severity because her baseline systolic was consistently low. Pediatric assessments require modified expectations. Children maintain blood pressure until late in decompensation. By the time hypotension appears, the child is in extremis. Use pediatric vital sign norms and focus on work of breathing and perfusion markers like liver edge palpation and pulse volume rather than waiting for blood pressure to drop.

Burn patients and those with significant soft tissue injury may not fit standard assessment categories. The priority shifts to burn surface area estimation and fluid resuscitation calculations. A full-body skin assessment becomes secondary to airway management and inhalation injury evaluation. Opioid overdose recognition should be automatic when you encounter respiratory depression with pinpoint pupils. Naloxone administration may be the only assessment-driven intervention needed. Do not waste time on an extensive secondary assessment before reversing the respiratory depression. The cheat sheet approach breaks down in mass casualty incidents where you must triage using START or JumpSTART protocols instead of individualized comprehensive assessment. Your Medical Assessment Emt Cheat Sheet should include a separate triage algorithm page that you reference when scene circumstances change.
What to Include on a Physical Reference Card
If you are building a small card for your pocket, limit it to information you cannot reliably recall under stress. Drug interactions, normal pediatric vital ranges by age, dosage calculations for common medications, ECG rhythm recognition patterns, and GCS scoring criteria belong on the card. Assessment steps and treatment algorithms should be internalized so thoroughly that you do not need to look them up during a call. Waterproof the card or store it in a sealed sleeve. Blood, bodily fluids, and rain will destroy paper quickly. Laminated cards are easier to clean but become impossible to write on after repeated exposure to disinfectants. Keep a backup. Review and update the card after every course or protocol change. Outdated medication dosages on a reference card cause more harm than having no card at all. I once carried an old cheat sheet with a dosing error for a pediatric medication for approximately six months before catching it during a recertification review. The error would have been catastrophic.
Practical Workflow for Using Assessment Materials in the Field
Keep the cheat sheet in the ambulance, not on your person. Reference it during patient care only when needed for calculations or uncommon protocols. Carry mental shortcuts instead. A laminated sheet in the back of the rig is useful for doubling drug doses or confirming Pediatric Advance Life Support guidelines during a call. Pulling it out during primary assessment slows you down and signals hesitation to both your partner and the patient. Practice scenario-based review rather than memorizing static content. Run through assessment sequences mentally during quiet periods between calls. The information consolidates through repetition in variable contexts, not through passive reading. I found that running through patient assessments during my drive to work sharpened my recognition patterns faster than any review session. Debrief after difficult calls and identify where your assessment process lagged. Was there a step you skipped? Did you miss a finding that later proved significant? Adjust your mental checklist accordingly. The cheat sheet is a living document that should evolve with your experience.