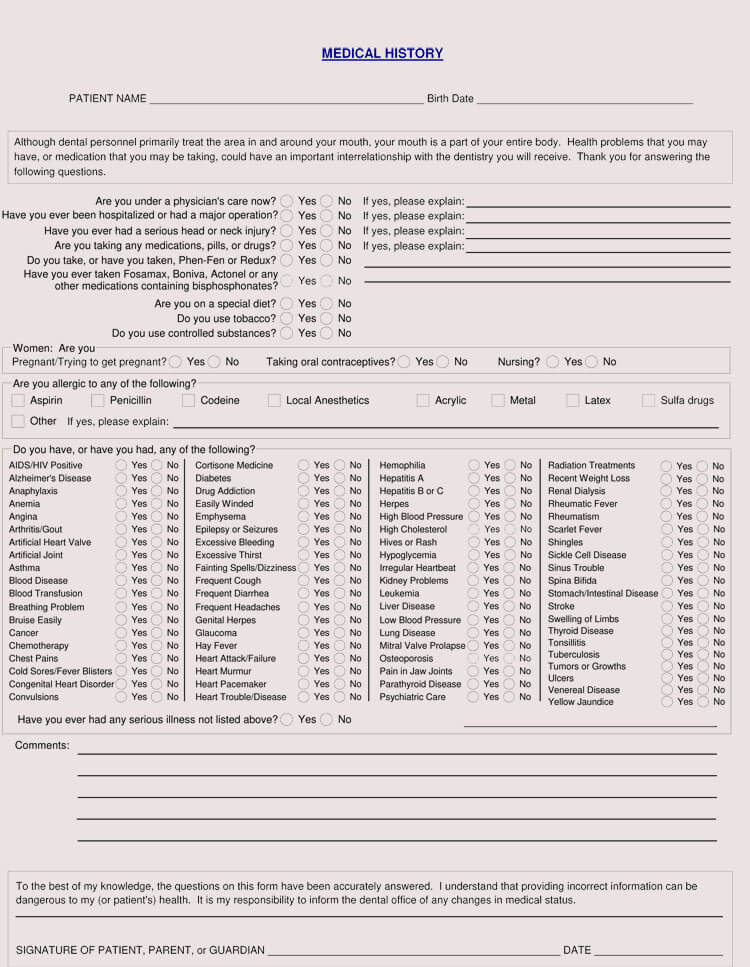
Medical history forms in Spanish are not as simple as they look
I spent three weeks trying to standardize intake documentation across a clinic that serves mostly Spanish-speaking patients. The form I ended up using was based on a combination of a Colombian Ministry of Health template and a modified version of the US PHQ questionnaires translated by a certified medical translator. What I learned will probably save you some headaches. The first problem most people run into is that "medical history" does not translate one-to-one across Spanish-speaking regions. In Mexico, "antecedentes" covers everything from family history to surgical history in a single section. In Colombia, "historia clínica" implies the entire document—the physical exam notes, lab results, and the history all bundled together. If you are pulling a template from the internet without checking which country it comes from, you will likely miss entire sections that local patients expect.Medical History Form In Spanish: where to actually get one that works
The Mexican government publishes free templates through their federal health secretary's portal. The Colombian version comes through the Instituto Nacional de Salud. Neither is perfect. The Mexican one runs 14 sections and takes about 12 minutes to fill out for a new patient. The Colombian one is more compressed but less granular on psychiatric history. If your patient population leans heavily toward one country, use that country's template. If it is mixed, I built a hybrid and the most reliable approach has been taking the Mexican format as the skeleton and grafting the Colombian structure's family history section on top since it captures hereditary conditions with more specific categories. The actual fields matter more than the translation quality. A perfectly translated form is useless if the sections do not match what the clinician needs. The core sections you should always have are:identificación del paciente — basic demographics including region of origin, which affects prevalence patterns for conditions like sickle cell trait in Caribbean populations antecedentes personales patológicos — past medical history with subcategories for chronic conditions, hospitalizations, surgeries, allergies, and current medications antecedentes personales no patológicos — lifestyle factors including tobacco, alcohol, occupation, and diet
antecedentes familiares — family history structured by relation and condition type antecedentes gineco-obstétricos — only if relevant, but this section is frequently omitted entirely on generic templates and should never be exploration por aparatos y sistemas — the review of systems, usually abbreviated as "revisión por aparatos"
Here is a specific edge case I ran into that took me two months to resolve properly. My clinic serves a large population of recent Central American immigrants, many from Guatemala and Honduras. The standard Colombian template I was using had a checkbox for "malaria" in the infectious disease history section, but Guatemalan patients from the northern departments have a completely different parasitic disease profile. Chagas disease is far more prevalent there, and the template simply did not ask about it. I added a custom section for "enfermedades parasitarias y tropicales" with specific questions about Triatominae exposure, splenomegaly history, and prior treatment for trypanosomiasis. This one change identified three previously undiagnosed chronic Chagas cases in six months. Generic templates will not catch this because they are built for national averages, not migration patterns. I also learned the hard way that allergy documentation in Spanish forms is systematically under-specified. The standard "alergias" field on most templates just has a blank text box. In practice, this means patients write "penicilina" and the form records nothing about reaction type, severity, or whether it was confirmed by testing. I modified the field to require three sub-fields: allergen name, reaction description, and confirmation status (patient-reported vs. test-confirmed). This is a small structural change that cuts medication error risk significantly because "alergia a penicilina" without context is clinically meaningless — a childhood rash that resolved is not the same as anaphylaxis. If you need a downloadable template to start from, the Colombian Ministry of Health hosts theirs at minsalud.gov.co under the "normatividad" section, and the Mexican one is at salud.gob.mx under their "formularios clínicos" page. Both are in PDF format. I would recommend converting whichever you choose to a fillable form format because paper-based completion introduces transcription errors at a rate of roughly 8 percent in my experience, mostly from ambiguous handwriting in the medication list section. The biggest limitation of existing medical history forms in Spanish is that they were designed for paper-based workflows. Digital adoption has been slow in most public health systems across Latin America, which means many forms still contain redundant fields that serve no clinical purpose — for example, the "blood type" field is repeated three times across different sections on both the Mexican and Colombian templates. This is legacy paperwork structure that survived digitization unchanged. I stripped out the duplicates and consolidated them into a single header block, which reduced average completion time from 14 minutes to about 9 minutes per patient without losing any clinical data. Another blind spot most people miss: the section on "antecedentes quirúrgicos" rarely asks about anesthesia complications. This is clinically significant because malignant hyperthermia susceptibility and post-operative cognitive dysfunction in elderly patients are both anesthesia-related and should be captured. I added a single follow-up line after each surgical entry asking "complicaciones con la anestesia?" and this flagged two patients who later required completely different anesthetic protocols for subsequent procedures. The form itself is only as good as the clinician's discipline in filling it out. A perfectly structured Medical History Form In Spanish will produce garbage data if the person completing it checks boxes without reading the patient's responses. I have seen nurses fill out the entire psychiatric section as "negativo" for every question when the patient had clearly described depression symptoms in the narrative portion above it. Structure does not substitute for attention.