Revenue cycle documentation is mostly garbage
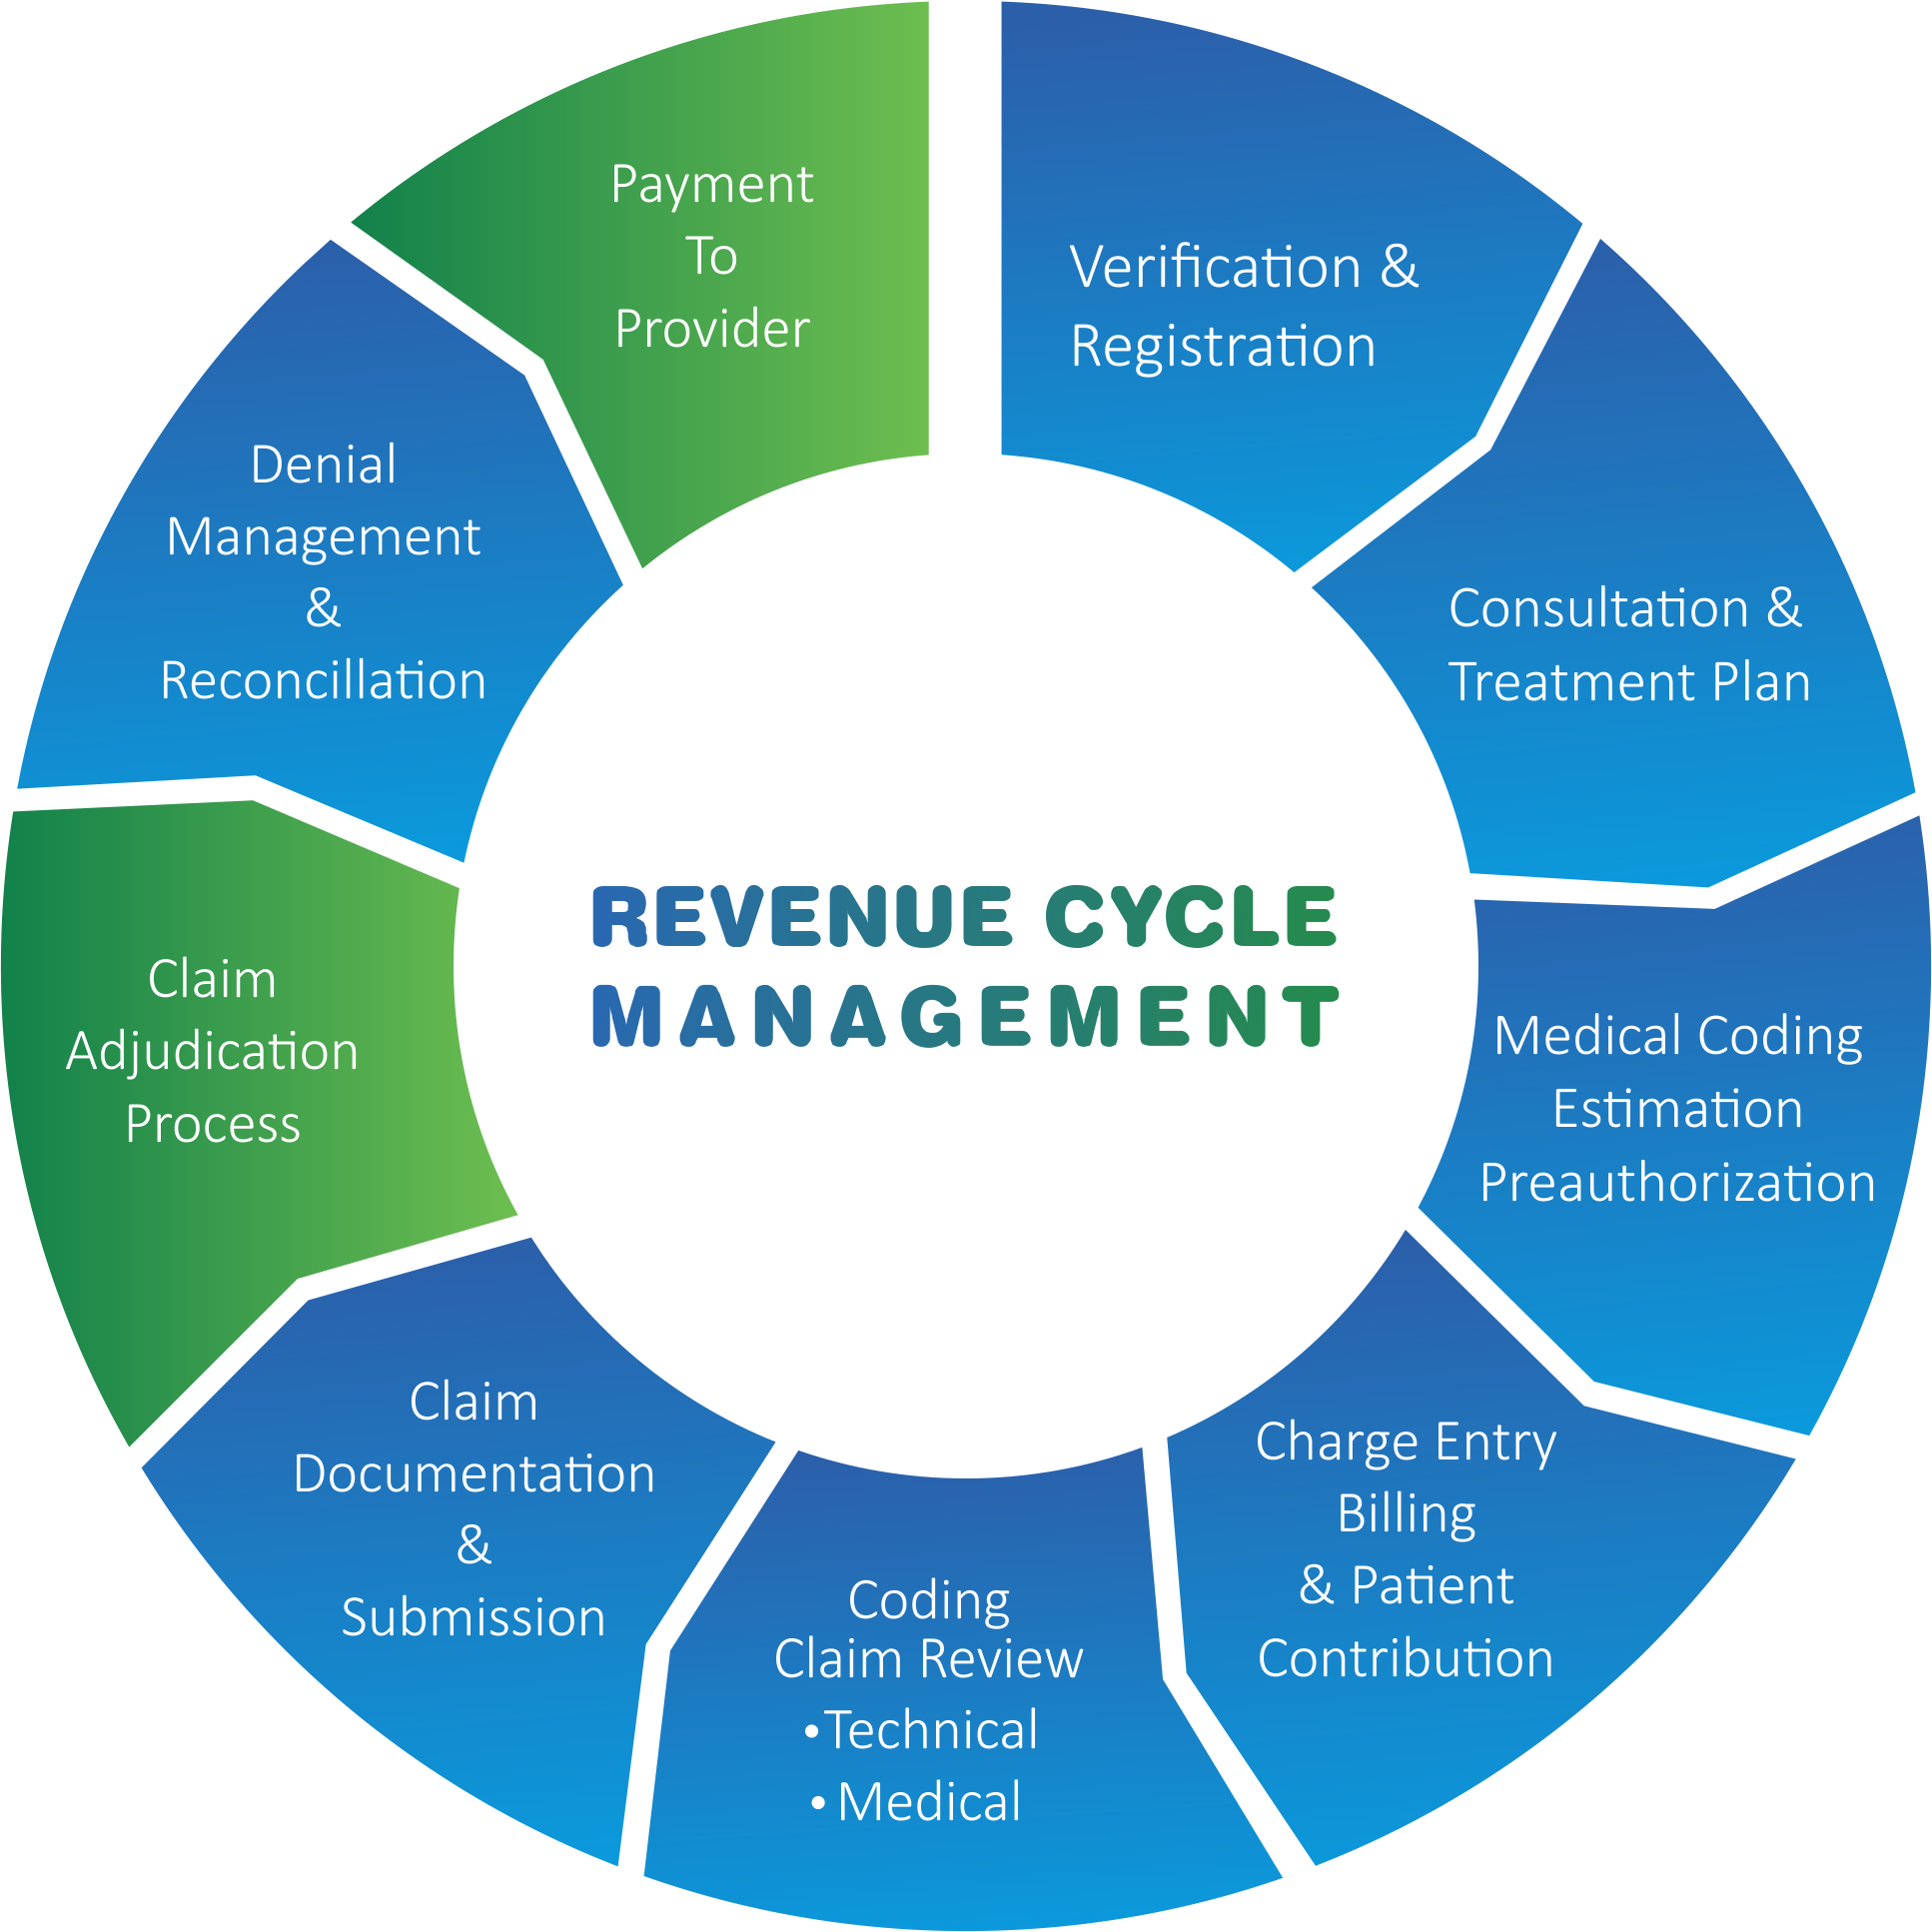
I have spent the better part of a decade dealing with medical insurance billing workflows, and the first thing you need to understand is that most PDF guides floating around on this topic are either written by people who have never touched a revenue cycle system or they are copy-pasted from compliance paperwork with the actual operational details stripped out. There is a reason for that. The real process varies so drastically between payer contracts, practice management software setups, and clearinghouse configurations that a universal guide is almost impossible to write accurately. That said, the core workflow is consistent enough that you can map it out without hiring a consultant for eight thousand dollars. Let me walk you through what actually happens from patient registration through final payment posting, and where things tend to break.
Medical Insurance A Revenue Cycle Process Approach Pdf
The document you are probably searching for is usually a compilation of standard operating procedures meant to help smaller practices structure their billing departments. I have downloaded several versions of these, and the useful ones share a handful of common sections. They cover patient demographic verification, insurance eligibility checks at the time of scheduling, charge capture workflows, claim submission and tracking, denial management, payment posting, and accounts receivable follow-up. The ones that are actually worth anything include templates for denial appeals, sample scrubbing rules, and days in A/R benchmarks broken down by payer type. Most of them are badly organized and outdated within a year of publication because CMS guidelines and payer policies change constantly. I keep a folder of the few versions that hold up, and I update the ones I use myself with current CPT and ICD-10 edits, the latest no-signature-needed policy changes, and the payer-specific quirks I have run into.
What the workflow actually looks like in a working practice
Start with scheduling. This is where I see the most preventable damage. A patient calls to book an appointment for a follow-up visit and the front desk checks insurance but does not verify the specific plan tier, prior authorization requirements, or whether the provider is in-network for that exact plan version. You might have a PPO plan that shows as active on a basic eligibility check, but the member has dropped down to a limited service tier that does not cover specialist visits without a referral. That detail does not appear on a standard real-time eligibility query through most clearinghouses. You have to pull the plan document or call the payer directly, and nobody does that because it takes eight minutes on hold. I ran into this exact problem last November with a mid-size orthopedic group using a legacy practice management system. We had a consistent stream of denials for one particular payer, about twelve percent of all claims, for the reason code CO-16. Prior authorization required. We checked our authorization module, everything looked clean. The denials kept coming. It turned out the payer had quietly changed their policy to require a different authorization number format for surgical consultations that was not being captured in our scheduling workflow. The authorization existed, but it was coded under a different reference type that the payer's new electronic editing software was rejecting. Fixing it took three days of calling the payer's provider services line, getting a supervisor involved, and updating our charge description master to tag those encounters with the correct authorization reference type before submission. After scheduling comes registration and demographic collection. This is not just entering a name and address. You need to capture the correct sequencing of insurance policies, especially for patients with Medicare and a secondary employer plan, or dependents covered under a spouse's plan versus their own. I have seen claims denied and stuck in limbo for sixty days because the primary and secondary payers were entered in the wrong order and the coordination of benefits field was not populated correctly. The fix is a standardized intake script that asks the right questions in the right order, and a mandatory fields configuration in your registration module that prevents the encounter from being created without complete insurance data.
Get the Full Details

Charge capture is the next bottleneck. When charges are documented but not entered into the system promptly, or when they are entered under the wrong code, everything downstream is wrong. Claim scrubbing catches some of this, but not all of it. A scrub tells you if a code is invalid or if there is a medical necessity flag, but it does not tell you that the charge belongs to a different CPT code that your payer covers at a higher allowable. That requires someone who understands the clinical work being done and the fee schedule for each contracted payer. I recommend having at least one person on staff who reviews the charge description master quarterly and updates it based on actual payer remittance advice data, not just the contract rate sheet. Claim submission and tracking is where the rubber meets the road. Electronic claims through a clearinghouse should process within forty-eight hours with an acceptance or rejection response. If you are still submitting paper claims for any reason, you are operating at a significant disadvantage. The rejection rates on clean claims from well-configured practices sit somewhere around two to four percent. That means six to eight percent of your submission volume is getting bounced and needs to be caught, corrected, and resubmitted within the same batch cycle. Most of these are simple data errors, but a meaningful percentage comes from payer-specific formatting requirements that are not documented anywhere obvious. Patient access and payer denial management are usually the same team in small practices, which is a mistake. Payer denials require a different skill set than patient collections. A denial needs to be categorized immediately upon receipt, tracked in a dedicated queue with aging buckets, and assigned to someone who knows how to write an appeal that references the correct clinical documentation and contract language. I have seen good claims get denied a second time because the initial appeal was too vague and the payer processed it as a duplicate submission rather than a reconsideration. Specificity matters. Reference the claim number, the date of service, the specific policy section that supports the payment, and attach the relevant clinical note excerpts.
Counter-intuitive things nobody teaches you
First, days in accounts receivable above forty-five is not always a bad thing. If you have a payer that routinely pays sixty to seventy-five days after claim acceptance, your overall A/R days will reflect that blend. Chasing payment at thirty days on a claim that is not expected to pay for another forty days just creates noise and waste. Map your A/R aging buckets to each payer's historical payment timeline and set your follow-up triggers accordingly. Second, the claim denial rate is a lagging indicator. By the time you see a spike in denials, the problem started at least thirty to forty-five days earlier because denials take time to process and post. If your clean claim rate drops below ninety-four percent, start investigating the front-end workflows, not the billing department. The denial usually traces back to a registration, authorization, or charge capture issue that happened weeks ago. Third, remittance advice processing is where most practices leave money on the table. Electronic remittances contain line-level payment detail, adjusted amount reasoning codes, and secondary claim routing instructions. If your staff is posting payments as lump sums rather than mapping each line to the corresponding claim and adjusting reason, you are not catching underpayments. I have walked into practices where the underpayment recovery rate was effectively zero because nobody was comparing the allowed amount per the contract to the actual paid amount on each line item. Running an underpayment audit against your top ten payers by volume typically recovers between one and three percent of total revenue within the first quarter of implementing one.
What this approach does not do well
A revenue cycle process PDF is a static document. It cannot adapt when your practice changes EHR vendors, renegotiates payer contracts, adds a new service line, or hires a new billing manager with a different workflow habit. The moment you adopt one of these templates, you need to customize it to your actual operations, and most practices skip that step because customization takes time and conflict with people who have been doing things a certain way for years. It also does not address the staffing reality. A well-documented revenue cycle process assumes you have enough people to execute each step. If you are a two-person billing team handling five hundred encounters a day, the process you write on paper will look nothing like the process you actually follow, which will look like triaging the most urgent denials and hoping the rest sort themselves out. Payer-specific edge cases are the biggest gap. No single document can cover the quirks of every commercial payer, Medicare Advantage plan, Medicaid managed care organization, and workers compensation carrier you might encounter. The document gives you a framework. The actual details live in your payer contract database, your remittance analysis, and your denial trend reports. If you are relying entirely on a generic PDF guide without building your own payer-specific playbook alongside it, you are going to keep hitting the same walls.

The version I actually use combines a baseline process framework with a living document for payer exceptions, updated quarterly based on the data from the previous three months of claim submissions and remittances. It is less polished than the downloadable templates, but it reflects what actually happens when the work goes through the door.