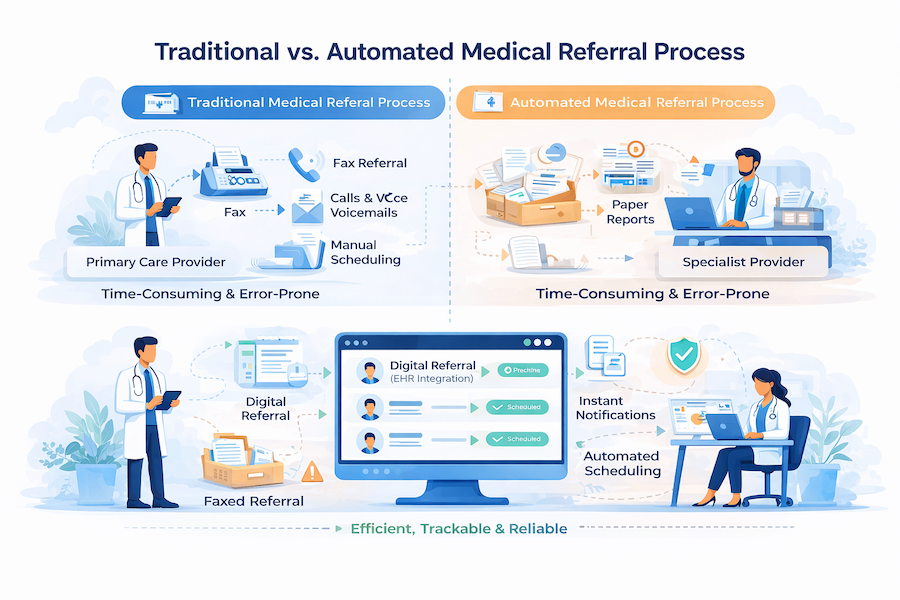
Learning to navigate the referral system without losing your mind
I spent three years handling specialist referrals at a mid-sized practice before I realized most of the problems weren't about medicine. They were about paperwork, timing, and understanding what each insurer actually requires versus what they claim to require on their website. The gap between those two things is where referrals go to die. It sounds straightforward — you learn to take a patient's chart, identify the right specialist, submit the request, and track it until someone shows up. But Medical Referral Specialist Training covers way more than that process. You need to understand prior authorization workflows, insurance tier structures, network status verification, and how to handle the 14 different rejection reasons a single insurer might throw at you in a week. The training programs that actually work teach you the rejection taxonomy first. Most beginners focus on the submission side and get burned when their perfectly formatted referral gets rejected because the referring provider's NPI doesn't match what's on file with the plan. I learned this the hard way when a cardiology referral sat in limbo for six weeks because the computerized system had the doctor's old NPI from a merger three years prior. We traced it to a manual override in the billing system that nobody had updated since 2019. Took me two phone calls and a fax to the credentialing department to fix.
You also need to understand the difference between a referral and a pre-authorization. They're not the same thing, and confusing them will waste everyone's time. A referral is the referring provider saying this patient needs to see someone else. A pre-authorization is the insurance company saying we'll pay for it if certain criteria are met. Some plans require both. Some require neither for in-network specialists. Some require pre-authorization before the referral even exists. The rules change by plan, by product line, and sometimes by individual employer group.
The Actual Workflow Most Programs Skip
Get the patient's current insurance information and verify it in real-time. Not the card they showed you at check-in. I mean run it through the insurer's verification portal or call the member services number on the back of the card. Coverage changes monthly. Copays change. Networks change. I've seen referrals submitted to specialists whose providers left the network the week before the appointment was scheduled. The patient showed up, got turned away, and now we're dealing with a complaint and a reschedule. Check the specialist's network status. This sounds obvious but most people skip it. The referring doctor might be in-network but the cardiologist they're recommending could be out-of-network for that specific plan. Run the specialist's NPI through the insurer's provider directory. Cross-reference it with the patient's benefit summary. If the directory says in-network but the claims portal says out-of-network, call the insurer and get it in writing. I keep a folder of these contradictions because they happen constantly. Submit with complete documentation. The specialist's office will reject your referral if the clinical information is incomplete. I'm not talking about the full SOAP note. I'm talking about the specific diagnostic codes, the treatments already tried, the duration of symptoms, and any red flags that need to be addressed. A referral for lower back pain without documenting what conservative treatments were attempted will get bounced back within 48 hours. Same thing for dermatology referrals without photographs or biopsy results if the lesion has been present for more than six weeks.
Get the Full Details

Track the referral until it's accepted. Submission is day one. The acceptance is usually day three to day ten depending on the specialist's scheduling complexity. Cardiology and oncology tend to be slower. Dermatology and orthopedics are faster but have different documentation requirements. Set up a follow-up reminder in your system for five business days after submission. If you haven't received confirmation by then, call the specialist's office. If they say they never received it, check whether it went to the right department. I've had referrals sent to the general intake line instead of the specific clinic because the referring office used an outdated fax number from the practice's old location.
Edge Cases That Break Beginners
Capitation and bundled payments complicate everything. Some specialty groups operate under global payment arrangements where they receive a monthly stipend per patient regardless of how many visits occur. These groups are sometimes reluctant to accept referrals because they're taking on patients they didn't choose and might not have capacity for. I encountered this with a gastroenterology practice that had a capitation deal with a major insurer. They accepted referrals but scheduled them six to eight weeks out because their panel was capped. The referring providers didn't understand why their urgent GI complaints were getting deferred. I had to explain the contract structure to three different doctors before they stopped calling me frustrated. Out-of-network referrals require a different workflow entirely. Some plans cover out-of-network care at reduced rates. Some require a written exception. Some don't cover it at all except in emergencies. I once spent four hours on hold with a PPO plan trying to determine whether a specific neurologist was considered out-of-network for a particular product line. The provider directory listed him as in-network for PPO but his practice had contracted with a different vendor for that specific plan year. The insurer's representative couldn't resolve it because she was looking at the wrong matrix. We eventually got a written determination through the provider relations department, but it took five business days and a formal appeal template. Emergency referrals bypass normal authorization but create documentation nightmares. When a patient goes to the ER and gets admitted, the admitting physician will order consultations without prior authorization. The specialist sees the patient because it's medically necessary. Then comes the fight with the insurance company about retroactive authorization. I've seen claims denied 30 days after the fact because the hospital didn't submit the emergency documentation within the required timeframe. The workaround is to have the hospital's case management team submit everything within 24 hours and keep a copy of the transmission confirmation. I always ask the covering specialist to note the emergency nature in their operative report because that sometimes triggers automatic approval.
Common Mistakes That Cost Hours
Using the wrong CDT or CPT code for the referral type. A general medical referral uses different billing codes than a surgical consultation or a therapy authorization. The insurer's system will reject the claim if the codes don't match the service type. I learned this when a physical therapy referral got denied because the submitting office used a consultation code instead of a therapy authorization code. The patient had already completed eight sessions before we caught the error. Retraining the front desk staff on code selection reduced similar rejections by about 80 percent within three months. Assuming the referral is active when you haven't received confirmation. Many systems show "submitted" as green but that doesn't mean accepted. The specialist's office might have rejected it without updating the status, or the insurer might have pending additional information requests. I check the specialist's scheduling system directly rather than relying on the portal status. If the appointment hasn't been scheduled within seven business days, I call the specialist's intake line and ask whether the referral exists in their system. This catches problems early instead of discovering them when the patient shows up and gets turned away. Not documenting the medical necessity with sufficient detail. Insurance companies have criteria for each type of referral. Rheumatology referrals usually require positive ANA or ESR results. Oncology referrals need imaging or pathology confirmation. Neurology referrals often require EEG or MRI results. I keep a quick reference guide for the top 20 referral types we handle and the specific documentation each payer requires. This cuts down rejection rates significantly because the referral goes in complete instead of getting bounced for additional information.

When the System Completely Fails
Some insurers have automated systems that reject referrals based on rigid algorithms without human review. I've encountered situations where a referral was rejected because the patient had seen the same specialist twice in six months, even though the second visit was for a completely different complaint. The system flagged it as "possible fraud" and held it for manual review that took 14 business days. In these cases, calling the insurer's provider hotline during off-peak hours (usually 7 to 8 AM or lunchtime) gets you a live person who can sometimes override the automated rejection. I also recommend having the referring provider call the specialist directly to confirm acceptance because sometimes the electronic system has errors that a human conversation can resolve immediately. Small specialty groups without dedicated referral coordinators are difficult to track. I've lost count of how many referrals I've submitted to practices where the receptionist answered the phone, said they'd follow up, and never did. For these situations, I use a combination of email confirmation requests and direct phone follow-ups every three business days until I get a verbal acknowledgment. I also ask the referring provider's office to confirm the referral with the patient because the patient sometimes receives a call from the specialist's office before the electronic confirmation arrives. Specialty drugs and procedures require separate authorization workflows that most general referral training doesn't cover. Biologics, infusion therapies, and surgical implants often need step-edit approvals, quantity limits verification, and formulary checks in addition to the standard referral. I keep a separate authorization tracker for these cases because the timelines are different and the documentation requirements are more complex. A standard referral might take five business days to process. A biologic authorization can take 15 to 30 business days depending on the plan's clinical review requirements.
Practical Tips From Actual Experience
Build a checklist for each major payer. I have different checklists for Blue Cross, United, Aetna, Cigna, and the local Medicaid plan. Each one lists the specific documentation requirements, the typical rejection reasons, and the verification phone numbers. This reduces submission errors because I'm not relying on memory or general knowledge. The checklist approach also helps train new staff because they can follow a consistent process instead of guessing what each payer requires. Use a referral tracking spreadsheet with color coding. Green means accepted, yellow means pending, red means rejected or needs follow-up. I update this daily and review it every morning before starting patient care. This visual system helps me prioritize which referrals need attention and which ones are progressing normally. The spreadsheet also serves as a backup record in case the electronic system goes down or loses data. Establish relationships with specialist scheduling coordinators. I've found that calling the same person at each specialty practice repeatedly builds rapport and improves communication. When I know who answers the phone at cardiology, oncology, and orthopedics, I can get faster responses and better information about their documentation requirements. This relationship-based approach has reduced my average referral processing time from about 10 business days to roughly 5 business days for most specialties.
Keep copies of all transmissions and confirmations. I save fax confirmations, email receipts, and portal submission screenshots in a patient-specific folder. If a referral gets rejected weeks later, having documentation that it was submitted on time with complete information protects the practice from billing disputes. I also keep a log of all phone calls including the representative's name, the time of call, and the outcome. This paper trail is invaluable when dealing with insurance appeals or patient complaints about delayed care. When Electronic Medical Referral Specialist Training isn't enough, consider hands-on mentoring. Most training programs cover the theory but not the practical realities of dealing with stubborn insurance systems or unresponsive specialist offices. I learned more from shadowing an experienced referral coordinator for two weeks than from any online course. The shortcuts, the phone numbers, the timing strategies — none of that comes from a textbook. It comes from watching someone handle real situations and asking questions when things don't make sense. The referral process will frustrate you occasionally. Systems fail, information gets lost, and insurance companies create unnecessary barriers. But having a systematic approach and documenting everything makes the job manageable instead of chaotic. Most rejections and delays come from avoidable errors like incomplete documentation or incorrect coding. Fixing those issues at the submission stage saves hours of follow-up work and prevents patient care delays that could have been avoided with proper initial preparation.