What actually happens when a patient visit turns into revenue
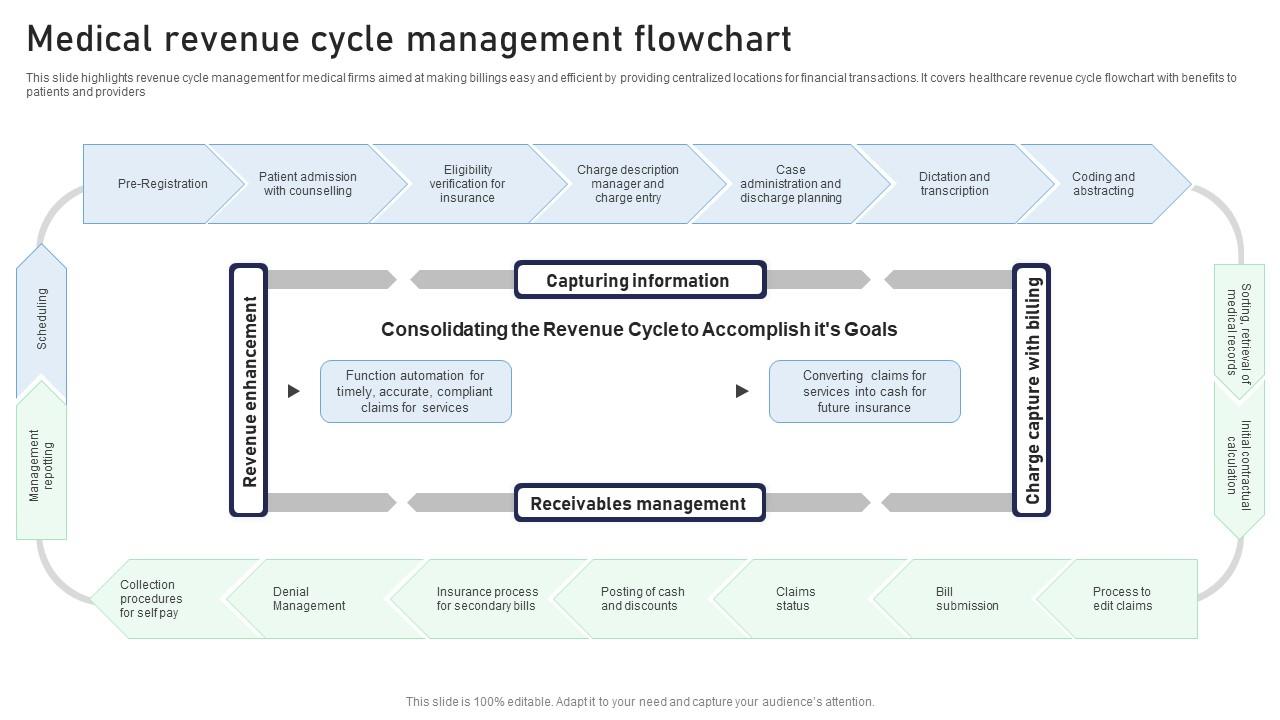
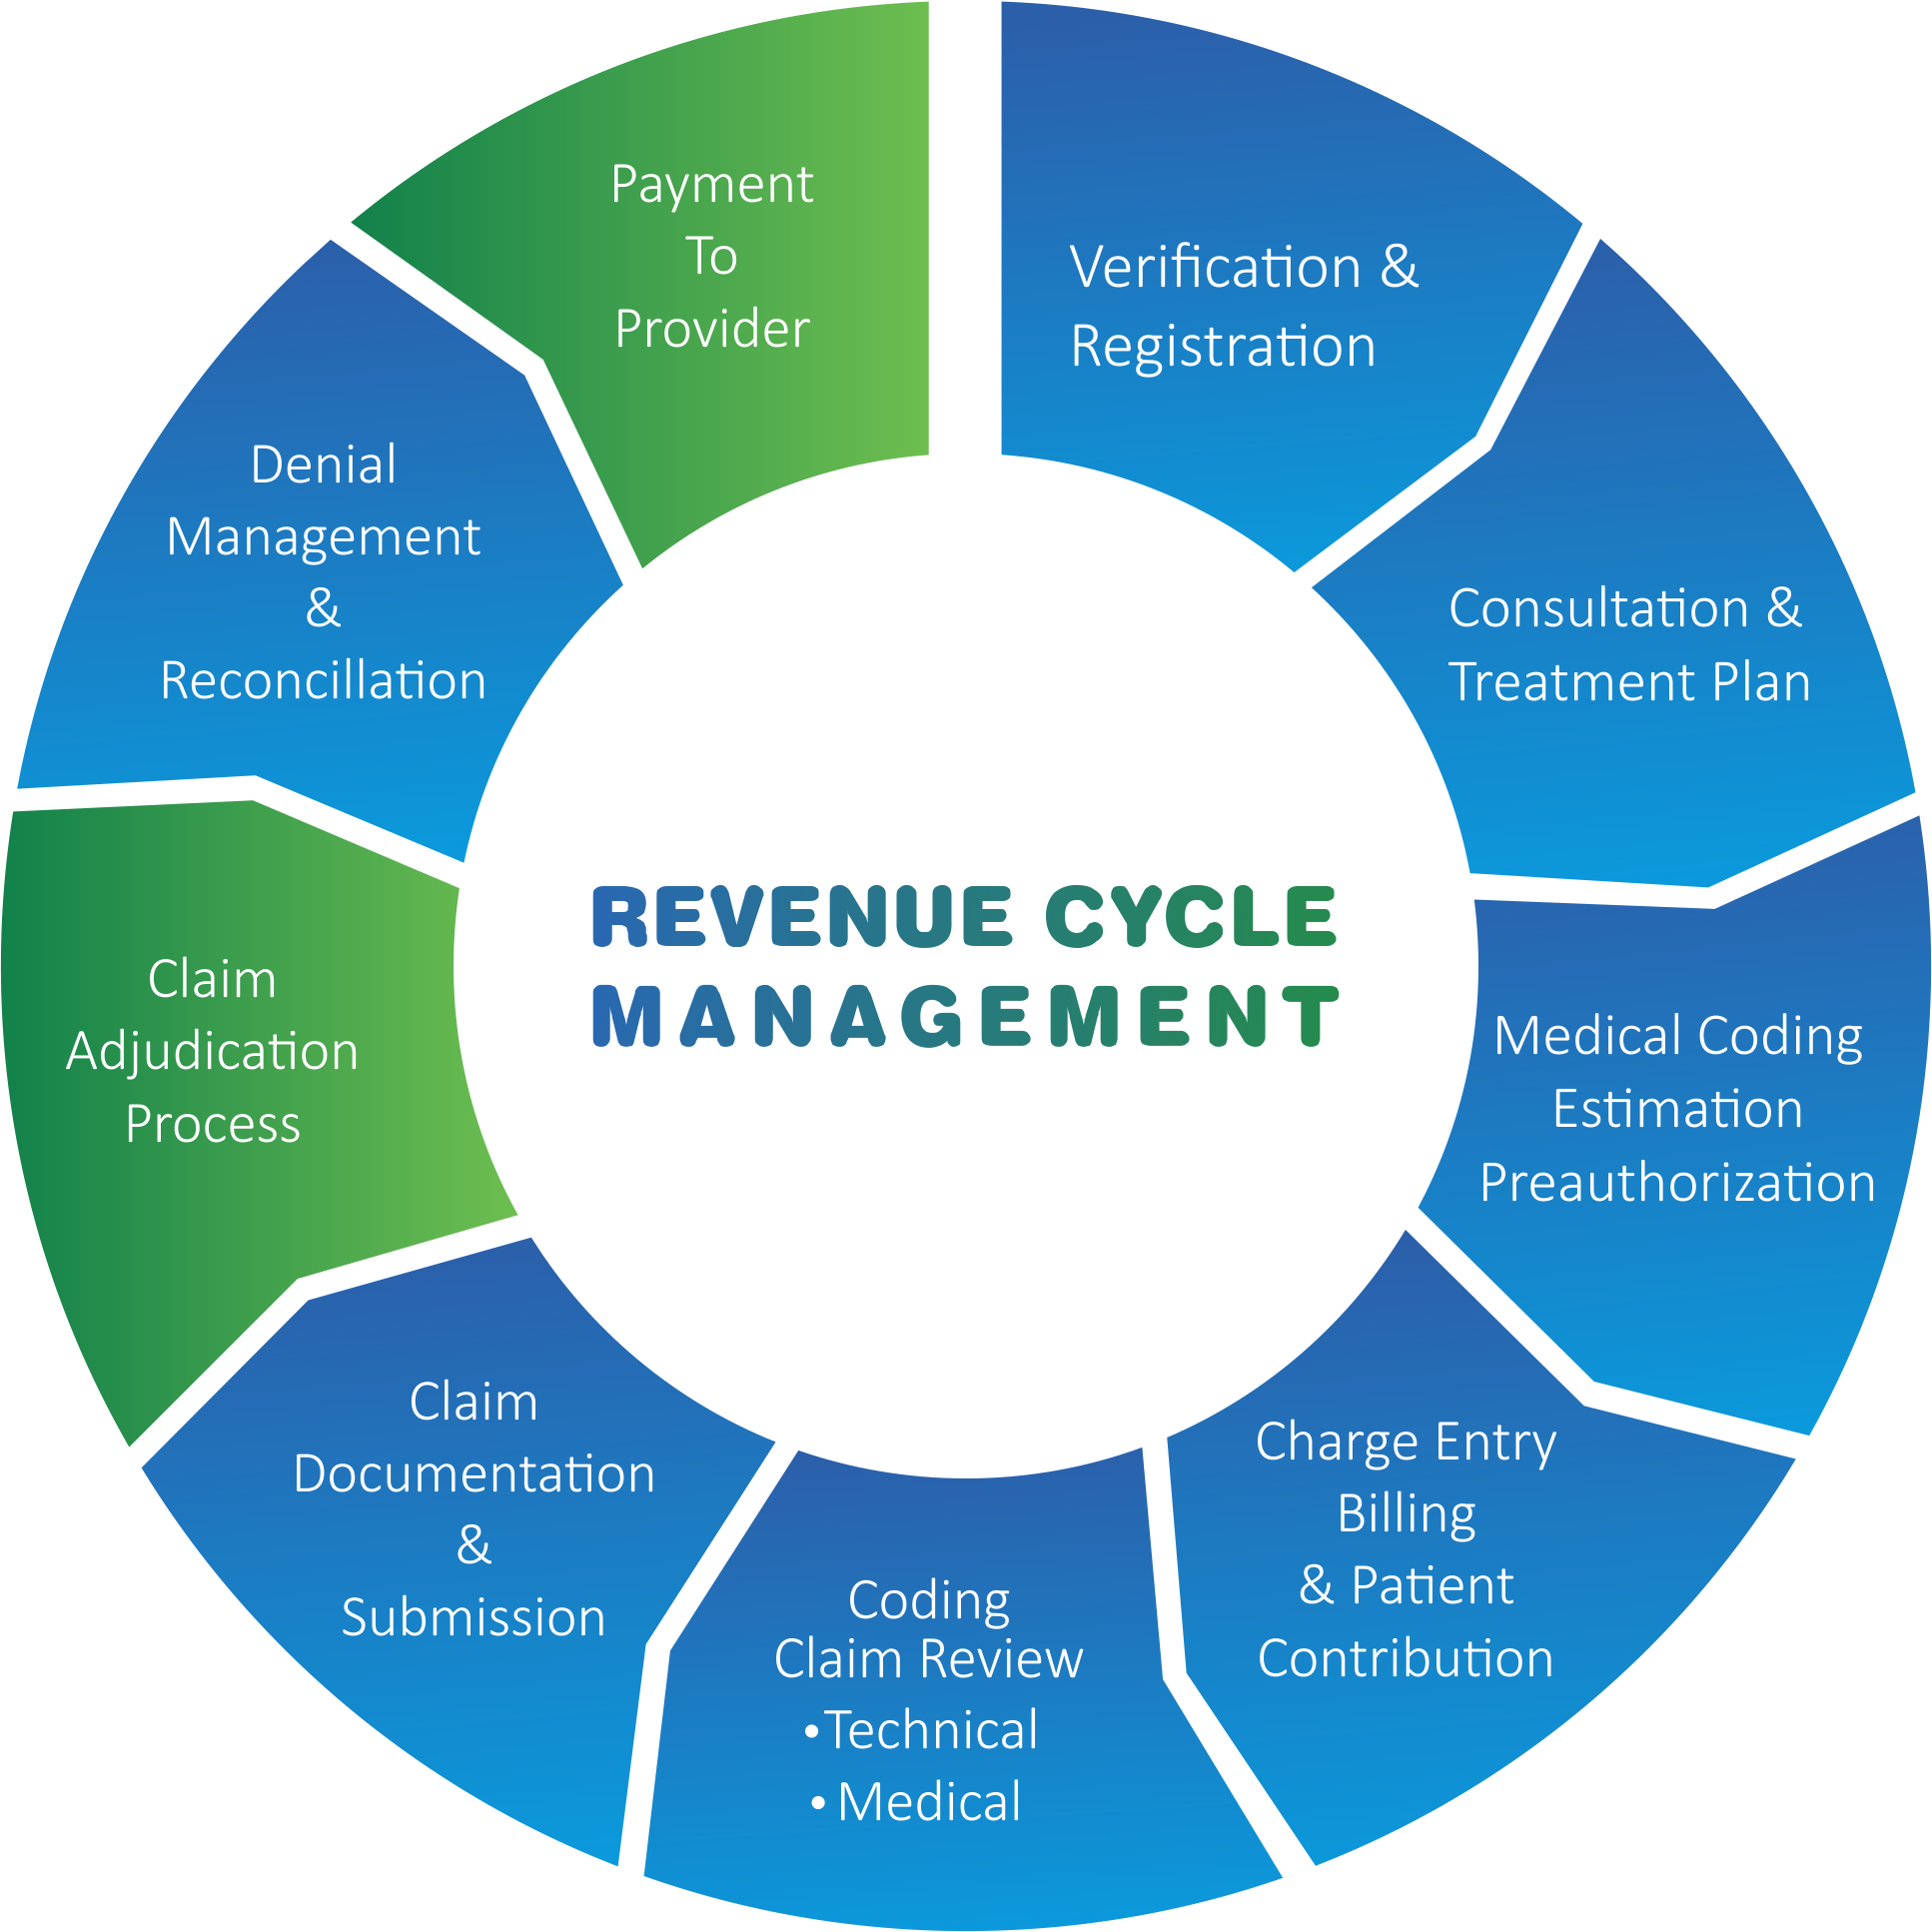
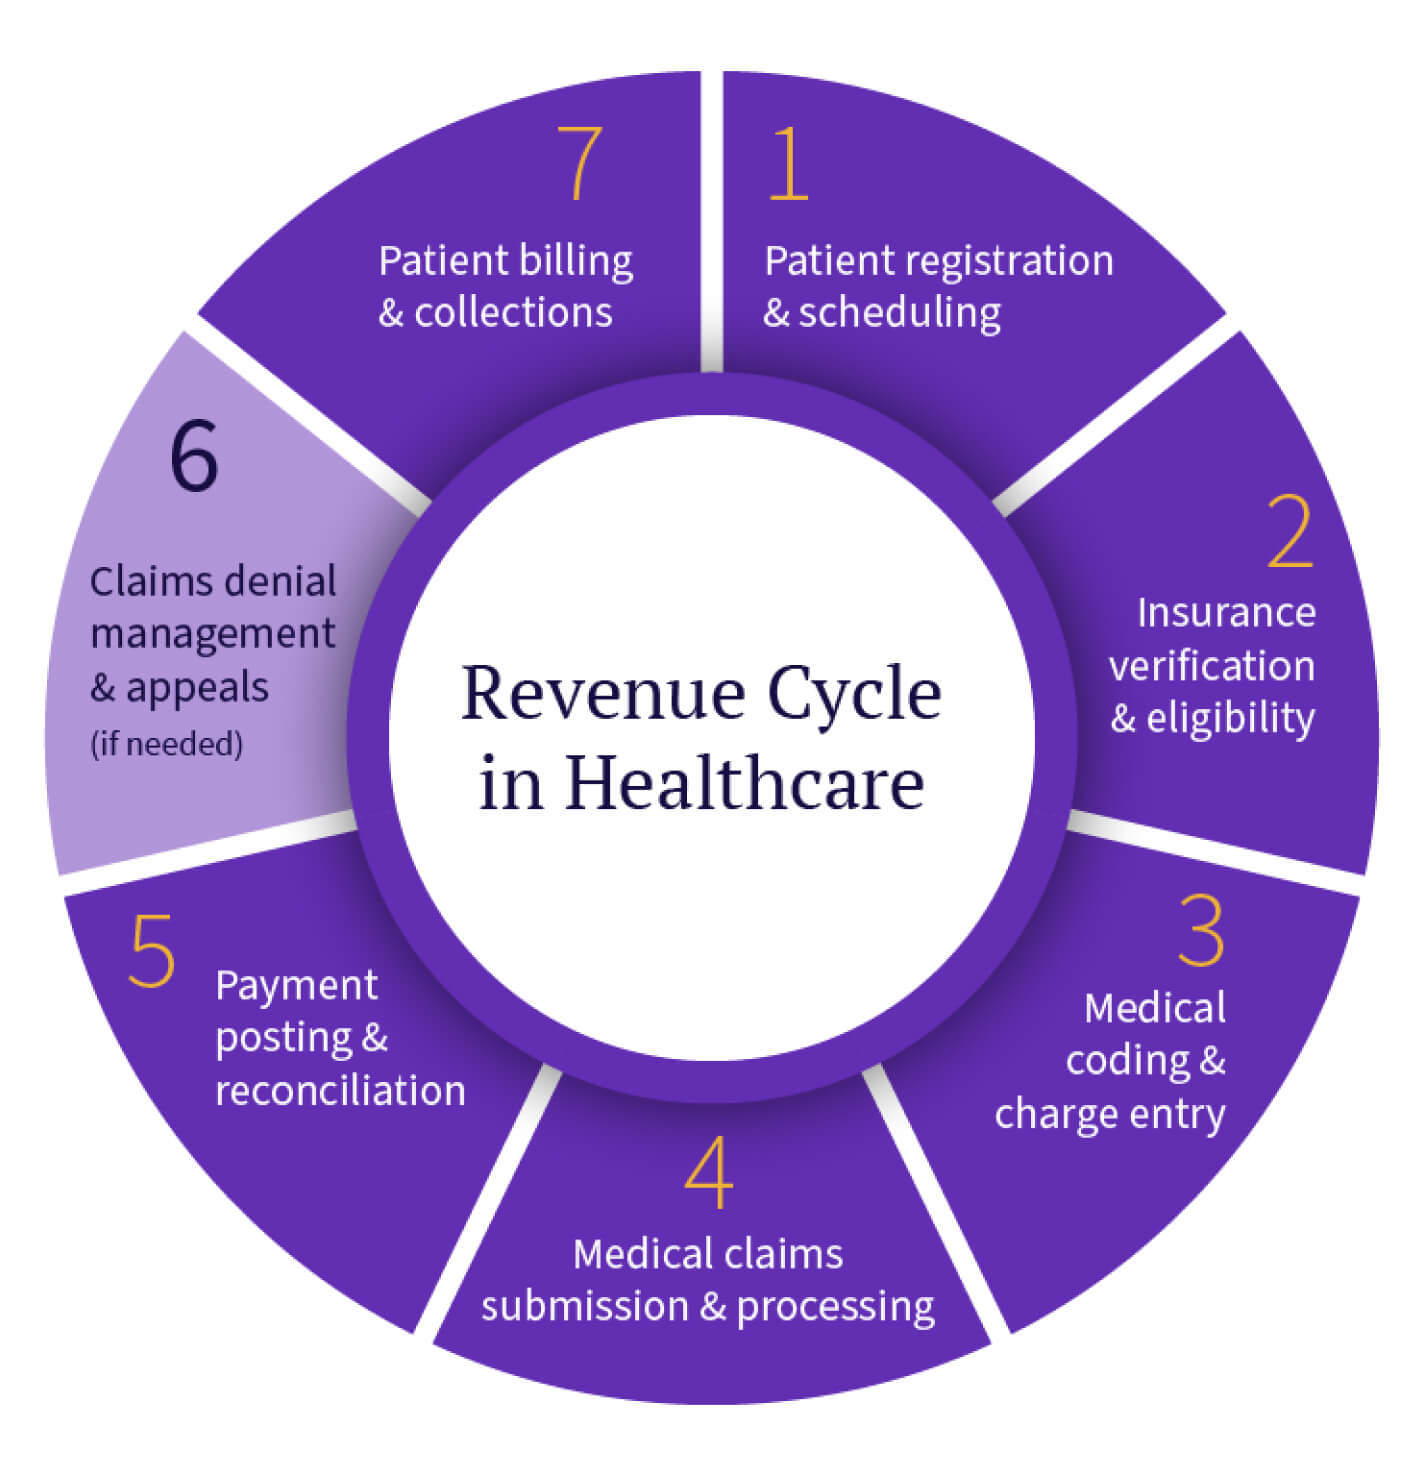
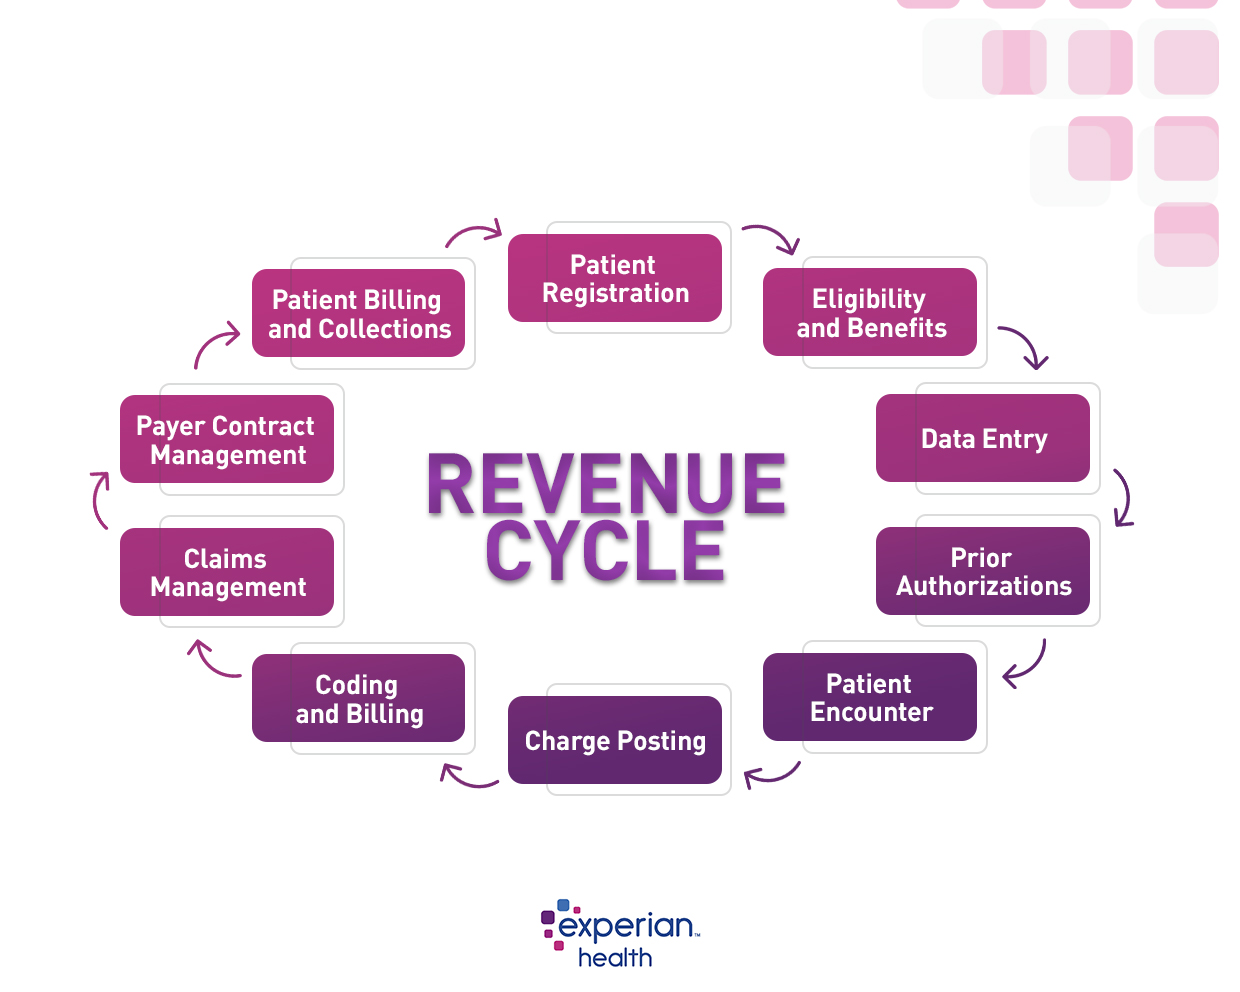
Medical Revenue Cycle Management covers everything from the moment a patient schedules an appointment until the last dollar is collected from a claim. It sounds straightforward until you realize it involves dozens of discrete steps, each with its own failure points. I have seen well-meaning practices blow a budget on fancy billing software while their eligibility verification process was still being done by hand, which is a common pattern I see more often than I would like. Start with scheduling. If you do not capture insurance information at the point of booking, nothing after that works. I spent three months tracking down why one clinic had a 38 percent initial denial rate. Turned out they were pulling insurance details from the old record instead of re-verifying every visit. Switched to real-time eligibility checks through the practice management system before every appointment, and that number dropped to under 7 percent within two billing cycles. After the visit, the coding step is where most places lose money without noticing it. Clinical documentation needs to support the level of service billed. Not just slightly, fully. I watched a provider get hit with an audit for upcoding because their notes said "minor procedure" in the narrative but the coder chose a level 4 E/M code. The discrepancy was small enough that auditors flagged it automatically. Training coders to query documentation gaps before finalizing a claim is cheaper than hiring a compliance consultant later.
Claim submission comes next, and clearinghouses exist for a reason. Do not skip them. Direct payer submission without clearinghouse validation means you are running your claims through a filter that has already caught thousands of common errors. A single rejected claim costs an average of $25 to $50 in rework depending on your staffing model. Validating edits before the payer sees the claim cuts rejection rates significantly. Payment posting is the step people rush through because it feels mechanical. That is exactly why mistakes accumulate. I recommend matching remittances line-by-line against patient statements, not just matching totals. When you match totals only, underpayments slip through. One provider was losing approximately $4,000 per month to unexplained variance because their system was auto-accepting payments without flagging contractual adjustments that did not match the payer's fee schedule. Finding that took about six hours of manual reconciliation, but it meant we could plug a hole that had been open for nearly two years.
Where the process breaks down most often
Arbitation is one of those topics nobody likes discussing until it becomes necessary. When a claim gets underpaid relative to your contracted rate, the difference is arbitrage opportunity if you fight it. Some groups ignore underpayments entirely, treating the cost of appealing as greater than the recovery. I disagree for any underpayment above $50 per claim where the contractual terms clearly support the correct amount. The math usually favors the fight. Prior authorization is another area with no shortcut that does not involve actually doing the work upfront. Some payers now require electronic prior auth through specific platforms. If your staff is still faxing forms and calling numbers, you are creating delays that become denials downstream. Setting up automated prior auth checks that trigger at scheduling can prevent a patient from showing up for a procedure only to learn mid-visit that authorization was denied. Credentialing matters more than most practice managers realize. A provider whose credentialing has lapsed even by a few days creates claims that get rejected or rendered unpayable. Track expiration dates with a calendar system, not a spreadsheet buried in an email inbox. I saw a group miss a provider recertification deadline by 11 days and lose roughly $18,000 in billable services during that window because claims submitted after the expiration date bounced back with no fallback path.
Get the Full Details

Tools that actually help versus tools that look good
Practice management systems vary wildly in quality. The expensive ones are not always the right ones. Look specifically for automation features around eligibility verification, claim status tracking, and denial management. Raw reporting dashboards that show you what already happened are useful for meetings but do not prevent problems. What you need is proactive alerting that tells you something is wrong before the billing cycle closes. Denial management software has improved a lot over the past several years. The ones worth considering use predictive analytics to flag claims likely to be denied before submission based on historical patterns and payer behavior. I recommend testing any tool against your top five denial reasons first. If it does not catch those, it is not worth the subscription cost. For smaller practices that cannot justify a full RCM platform, there are lightweight alternatives. Some clearinghouses offer bundled eligibility and claims management tools at reasonable prices. The interface is usually worse, but the functional outcome is often comparable. You trade convenience for savings, which is a fair exchange if the team does not mind the extra clicks.
When Medical Revenue Cycle Management needs outside help
Some practices benefit from outsourcing portions of the cycle, particularly denial management and accounts receivable follow-up. This is not a failure on your part. It is a recognition that specialized firms handle these problems daily and can recover dollars faster than an internal team wearing too many hats. The tradeoff is cost. Outsourcing typically takes 4 to 8 percent of collected revenue, but the recovery rate usually exceeds what most in-house teams achieve for aged receivables over 90 days. If you do outsource, require monthly reporting that includes denial root causes, payer trends, and days in accounts receivable. Vague summaries are useless. You should be able to look at the report and understand exactly where money is stuck and why. Any vendor who cannot produce that level of detail should not be your vendor.
A realistic timeline for improvement
Expect three to six months to see meaningful changes after implementing a revised Medical Revenue Cycle Management process. The first month is usually frustrating because you expose problems that were hidden by your old workflow. Denials you ignored before suddenly appear in your reports. That is progress, not regression. By month three, most practices see a measurable drop in days in accounts receivable and an improvement in clean claim rates. By month six, the improvements stabilize if the changes are maintained consistently. The biggest mistake is stopping too early. The metric that matters most is not denial rate alone. It is net collection rate, calculated as total collected divided by total allowed. A practice can have a low denial rate and still leave money on the table through contractual underpayments and delayed follow-up on aging claims. Tracking both metrics together gives you the actual picture.