Antibiotics for Beginners
Most med students hit this wall during pharmacology. You are drowning in drug names, spectra, and mechanisms. I remember sitting in the library trying to memorize every beta-lactam ever discovered. It did not go well. The breakthrough came when I stopped treating antibiotics as isolated facts and started mapping them by what they actually do in the body. Here is the approach that actually works. First, organize everything by bacterial spectrum. Gram-positive covers one column. Gram-negative covers another. Atypicals get their own section. Then within each category, note the mechanism, the key side effect, and one clinical pearl you can use on rounds. This structure mirrors how you will encounter patients anyway. I spent about three hours building this into something manageable. The result cut my review time from four days down to roughly two evenings before the exam. That is not a huge difference in absolute terms, but in med school it is everything.
The Mechanism Problem Nobody Talks About
Students obsess over memorizing drug names without connecting them to mechanism. They memorize that vancomycin inhibits cell wall synthesis, then immediately forget it because there is no hook holding the information in place. The real insight is that mechanism tells you everything else about the drug. If it targets the cell wall, it is bactericidal against actively growing organisms. If it targets protein synthesis, it is usually bacteriostatic. Cell wall agents fail against organisms without cell walls, which is why vancomycin does nothing against enterococcus at standard doses. Consider the penicillins. Amoxicillin covers streptococci and some gram-negatives. Ampicillin adds enterococci to that list. Piperacillin adds pseudomonas. The pattern is not random. Each extension adds a specific gap-filling capability. Once you see the ladder, you stop memorizing individually and start understanding the progression.
Common Pitfalls in Practice
The biggest mistake I see students make is treating antibiotics as interchangeable within categories. They think all penicillins are the same. They are not. Nafcillin covers MRSA. No, wait, that is wrong. Nafcillin does not cover MRSA. I almost made that mistake on my first clinical rotation when a attending asked about anti-staphylococcal coverage. I froze. The attending did not say anything, which somehow made it worse. Another issue is side effect memorization without clinical context. Students learn that linezolid causes thrombocytopenia, then never use that knowledge until someone asks them to monitor platelets on day five of treatment. Link the adverse effect to the monitoring requirement. The memory sticks better that way.
Get the Full Details
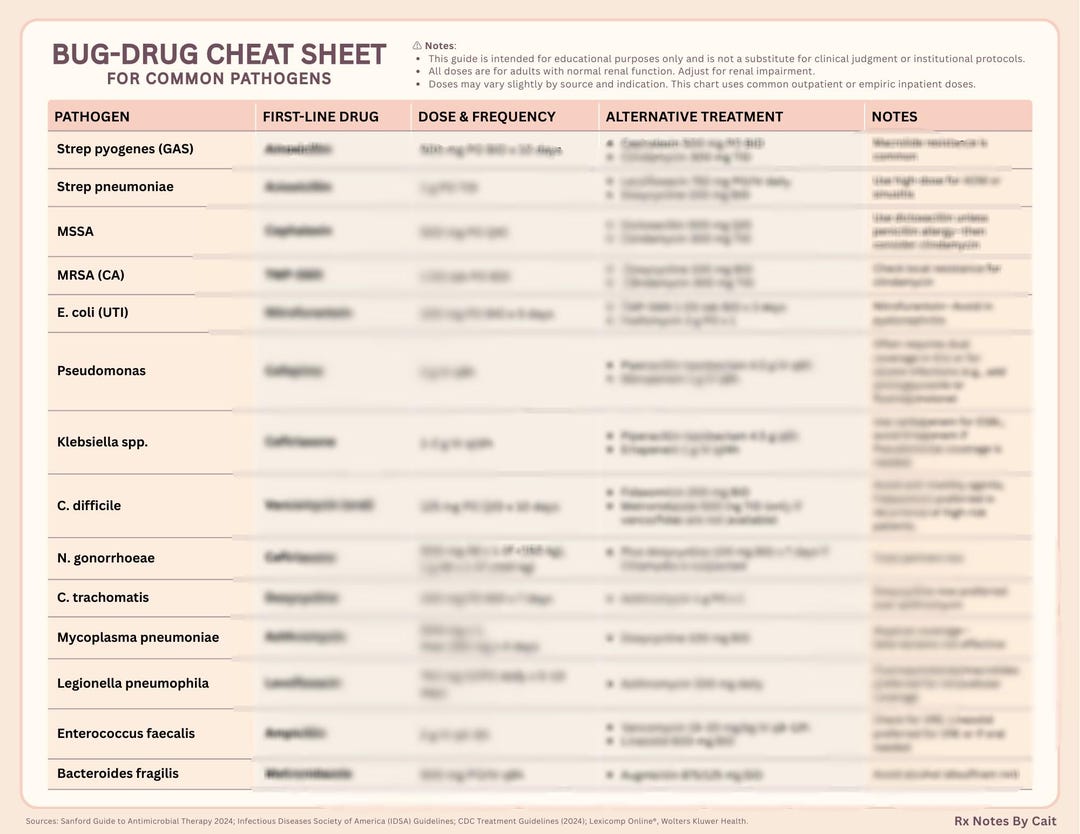
What This Cheat Sheet Actually Covers
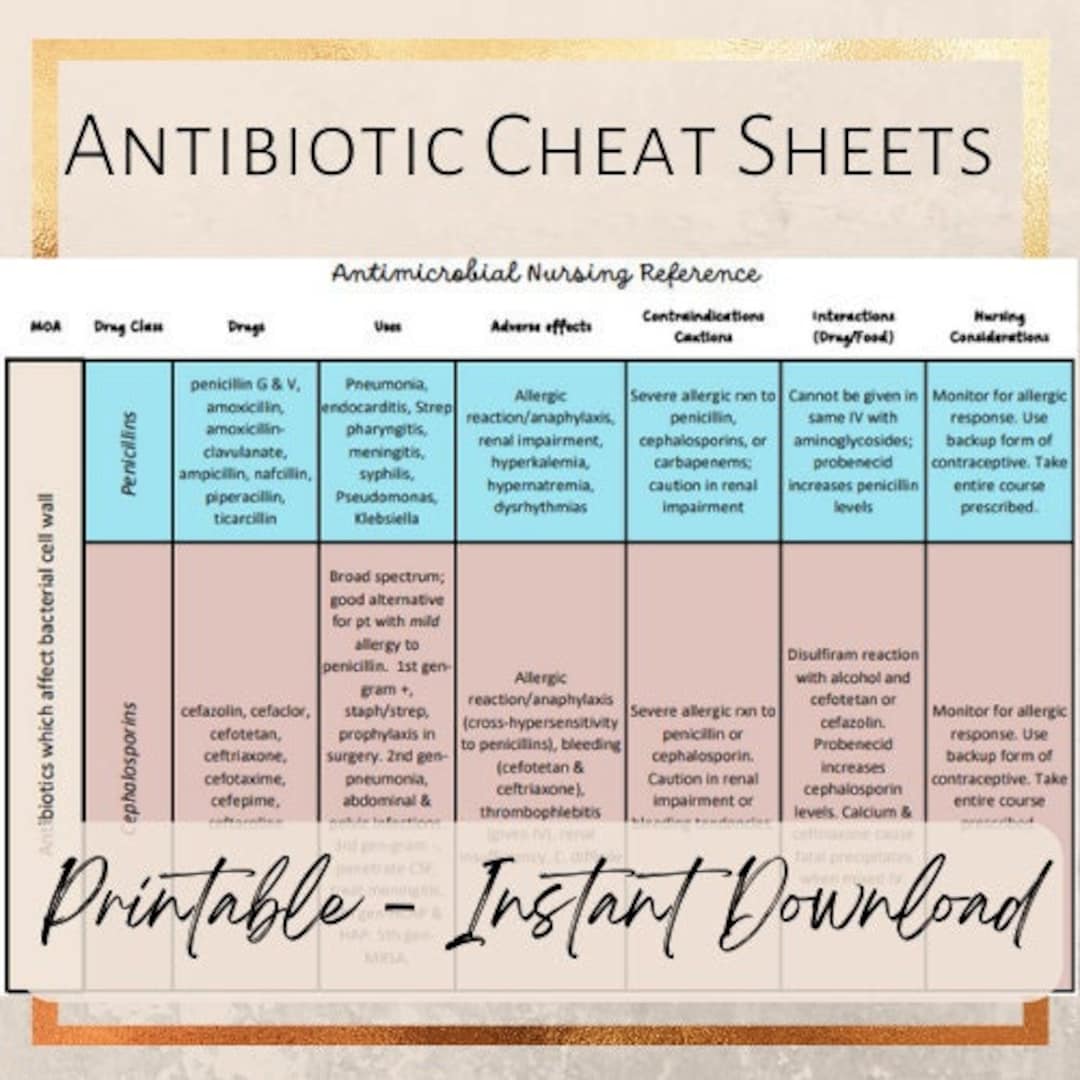
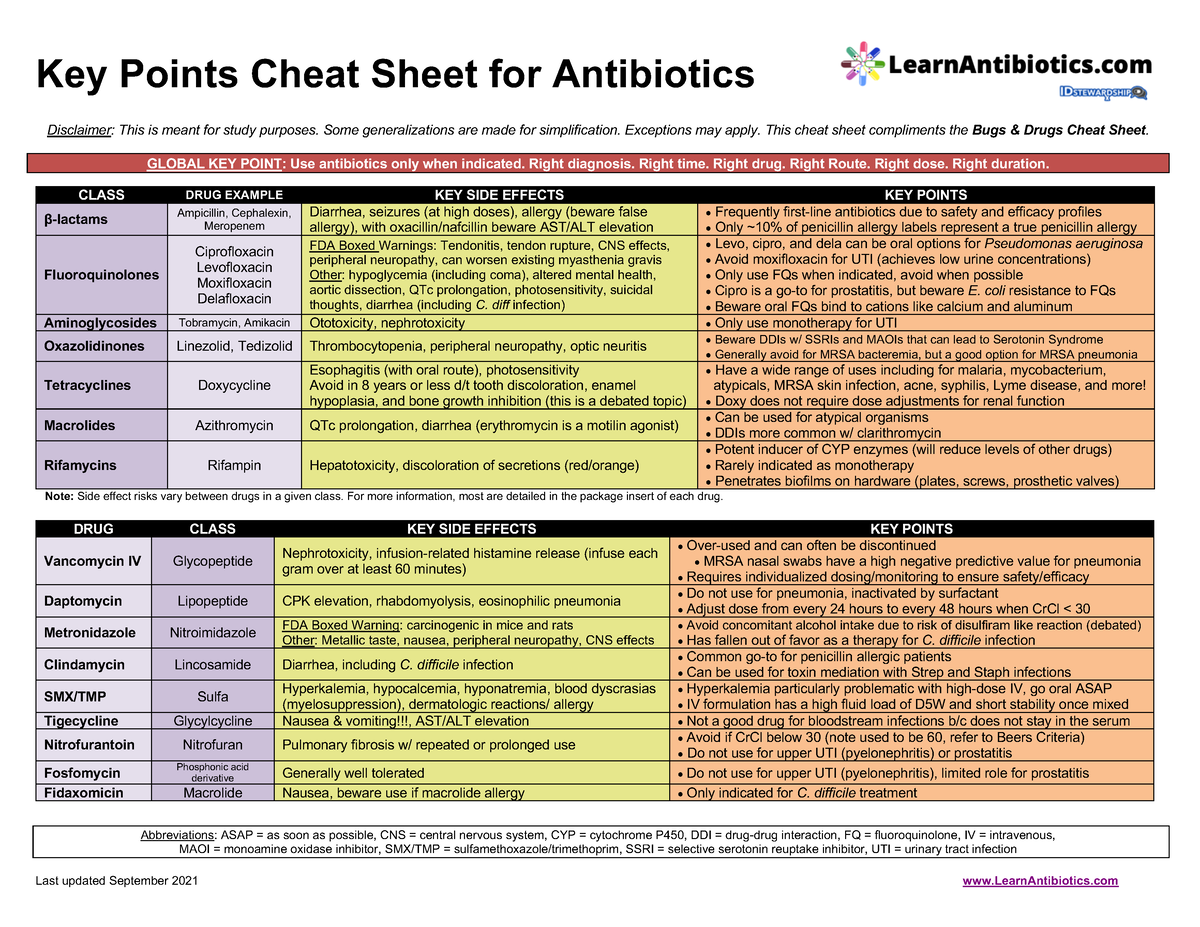
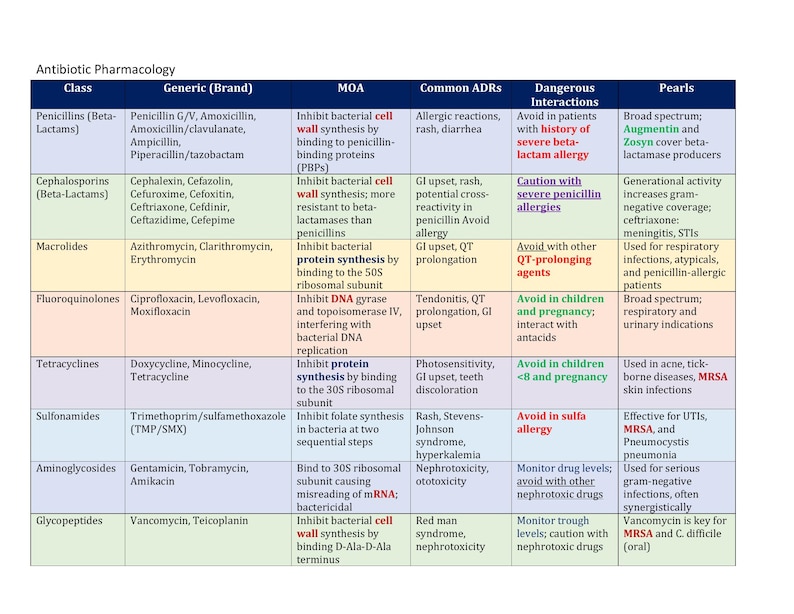
A good antibiotic cheat sheet for medical students should include drug class, mechanism, spectrum, dosing adjustments, and major toxicities. The most useful versions also flag renal versus hepatic clearance, since dose adjustment mistakes cause real patient harm. I include a quick reference for QT-prolonging antibiotics because that comes up constantly on rotation. I also track which antibiotics cover anaerobes. Metronidazole and clindamycin are the obvious ones, but piperacillin-tazobactam and meropenem have substantial anaerobic activity too. This distinction matters when you are choosing coverage for intra-abdominal infections or aspiration pneumonia.
The Limitations I Wish I Had Known Earlier
No cheat sheet replaces clinical reasoning. I built mine to help with exam preparation, but it has blind spots. It cannot teach you antibiotic stewardship principles or the nuances of duration therapy. It will not prepare you for the situations where guidelines conflict or where institutional resistance patterns override textbook recommendations. The cheat sheet is strongest for initial memorization and weakest for applied decision-making. Use it as a starting point, not an endpoint. After you have the framework down, supplement it with case-based learning and institutional antibiograms.
Building Your Own Version
Start with a blank table. Create columns for drug class, key members, mechanism, spectrum, adverse effects, and special considerations. Fill in one class at a time. Do not move on until you can explain the mechanism to someone without looking at your notes. If you cannot teach it, you do not know it yet. I recommend organizing by spectrum rather than by drug class. In clinical practice, you think in terms of coverage first, then select the agent. That mental model transfers directly to exam performance. The only time this breaks down is when the question specifically asks about mechanism or resistance patterns.

Resources That Actually Help
Beyond the cheat sheet itself, the Sanford Guide and UpToDate remain reliable references. For visual learners, the antibiotic flowchart apps available on most medical school networks provide interactive coverage maps. I also found the FDA prescribing information documents useful for detailed dosing tables, though they are dry reading. The Microbe Online portal offers good mechanism diagrams if you need visual reinforcement. Not everything clicks from text alone, and that is normal.
When the Cheat Sheet Falls Short
There are scenarios where even a well-built reference fails you. Complex resistance mechanisms like AmpC beta-lactamase or inducible clindamycin resistance do not fit neatly into one-row summaries. These edge cases require deeper study and clinical correlation. Do not trust a single-page overview to cover Vancomycin-intermediate Staphylococcus aureus management. Look up specific guidelines instead. Similarly, pediatric dosing and renal adjustment calculations are beyond the scope of most quick-reference sheets. Keep a calculator app handy and verify doses through proper protocols rather than estimating from adult standards.
Final Thoughts Without Wrapping Up
The antibiotic landscape changes constantly. New resistance patterns emerge, guidelines shift, and institutional formularies vary. A static reference document becomes outdated faster than you might expect. The value is in the method of organization, not the specific content you write down. Build the framework, learn how to populate it, and maintain it throughout training. I still use a condensed version of my original cheat sheet today on rotation. It is not perfect, but it is faster than opening a textbook when someone asks me what covers pseudomonas at 3 AM.