The Actual Process of Doing an HRA for Medicare Advantage
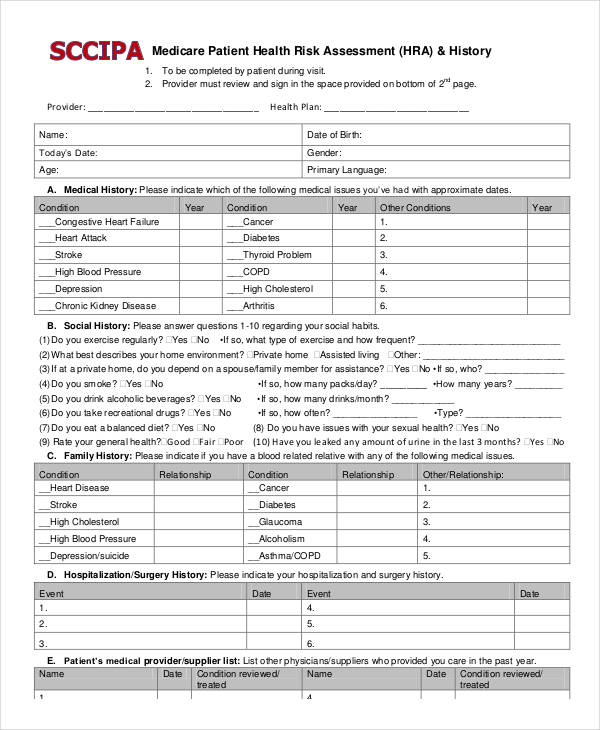
Most people treat the Health Risk Assessment like it is a checkbox exercise. It is not. CMS uses the HRA data to calculate the risk adjustment factor that determines how much a plan gets paid each month. That means getting the assessment right is directly tied to plan revenue, which is why contractors pay close attention to whether you are doing it properly.The HRA must be completed during the annual enrollment period or at special enrollment times. You use a CMS-approved instrument like the Medicare Health Risk Assessment Survey tool. The respondent can be the beneficiary or someone acting on their behalf if capacity is limited. You collect data on functional status, cognitive ability, chronic conditions, disability level, and ADLs. This feeds into the Hierarchical Condition Category model that drives capitation rates. Let me walk through what actually happens when you try to complete one of these assessments in a real-world setting. You schedule a visit or phone call with the member. You go through the instrument item by item. Some questions are straightforward. Others require clinical judgment to interpret correctly, and that is where most errors creep in. Here is a specific problem I ran into recently that almost nobody talks about. A beneficiary was completing the HRA and when asked about their ability to bathe independently, they said yes. They were still able to get into the shower with assistance and manage their hygiene with adaptive equipment. The default scoring would have placed them as independent. But the documentation in their chart showed a home health aide visiting three times a week specifically for bathing assistance. When we flagged this discrepancy, the plan had to go back and amend the assessment. CMS allows amendments within 180 days of the original submission, but you need a clear audit trail showing why the change was made. If you do not have contemporaneous documentation to support the amendment, the contractor will reject it and the risk adjustment payment for that member goes to zero for that year. That is a real financial hit.
The workaround I use now is to ask the member to describe their typical day rather than answer each question in isolation. If they mention needing help getting dressed or bathing, I circle back to the specific ADL questions and make sure the responses reflect their actual situation. It takes maybe five extra minutes per assessment but it prevents these kinds of mismatches between the HRA response and the clinical record. Another thing that catches people off guard is the difference between what counts as a valid HRA and what gets rejected during the contractor audit. The instrument has to be administered in English or Spanish unless a qualified interpreter is used. You cannot have the respondent self-complete it unless the plan has verified that they have the cognitive capacity to do so. If a member has a diagnosis of dementia and you allow them to fill out the HRA on their own without documenting capacity assessment, that entire submission is at risk of being recaptured. Here is a counter-intuitive point that most plans overlook. The HRA can actually lower your risk score in some cases. If a member is currently managing a chronic condition well through treatment and they report that their symptoms are controlled, the ADL and IADL scores may come back lower than they should based on their diagnosis alone. Plans that only look at diagnostic codes and ignore the functional component consistently overestimate their risk adjustment. The HRA is supposed to capture the severity of illness, not just the presence of a condition. When you skip the functional questions or rush through them, you are leaving money on the table or creating audit exposure.
There is also the issue of proxy respondents. When a family member completes the HRA on behalf of the beneficiary, you need to document the relationship and the basis for their knowledge. I once saw a plan accept an HRA where the daughter said her mother could not prepare meals because she lived alone and ordered takeout. The mother was actually living with her husband who prepared meals but the daughter did not know that. The HRA scored the member as needing extensive assistance with instrumental activities of daily living when they did not. The contractor flagged it during peer review because the plan's clinical records showed no diagnosis of cognitive impairment and no history of nutritional deficiencies. The assessment had to be revised and the member's risk score was reduced, which affected the plan's quality rating for that year. The technical requirements from CMS are specific. You need to collect the member's name, date of birth, Medicare number, and contact information. The assessment must be dated and signed by the person who administered it. You must document the method of administration whether it was in person, by phone, or through a telehealth encounter. For telehealth, you need to confirm that the member can see and hear you adequately and that the environment is private. Each of these details matters during an audit. One more practical detail. The HRA should be re-administered annually during the Enrollment Period. Some plans try to use data from a previous year's assessment to save time. That does not work. CMS requires a current assessment for each enrollment cycle. If you attempt to submit a risk adjustment claim based on an outdated HRA, the contractor will reject it. The timing is also important. The assessment must be completed between October 15 and December 7 for the Annual Enrollment Period, or within the applicable window for a Special Enrollment Period. Submissions outside those windows will not be accepted for risk adjustment purposes.
Get the Full Details

Let me be straightforward about the limitations here. The HRA process is not perfect. It relies heavily on self-reported data, which means member accuracy varies. Some members will underreport symptoms because they do not want to be seen as dependent. Others will overreport because they believe it will lead to better services. There is no easy fix for this. What you can do is cross-reference the HRA responses against clinical documentation and care plan records before submission. If there are significant discrepancies, you have an obligation to clarify with the member before finalizing the assessment. The biggest bottleneck most plans face is staff turnover. HRA administration requires trained personnel who understand the instrument, the scoring rules, and the documentation requirements. When you lose an experienced staff member, the new hire needs several months to reach competency. During that transition period, error rates typically go up. I recommend having at least two people on staff who are fully trained on HRA completion so you are not dependent on any single individual. Pair up new hires with experienced staff for the first sixty days and review their completed assessments before submission. Another limitation is that the HRA does not capture everything about a member's health status. It is a snapshot in time. A member who is stable during the assessment period may deteriorate shortly after. The risk adjustment model accounts for this to some extent through the chronic condition hierarchies, but it is not a substitute for ongoing clinical monitoring. Plans that treat the HRA as a once-a-year event and ignore the rest of the year are missing opportunities to update assessments when significant changes in health status occur.
If you are looking for the actual CMS instrument, you can find it on the CMS website under the Risk Adjustment Data Validation section. The current version is the Medicare Health Risk Assessment Survey Tool, and CMS updates it periodically. Make sure you are using the latest version because submitting with an outdated instrument is an easy way to get your entire submission rejected. The takeaway is that the Medicare Advantage Health Risk Assessment Requirements exist to ensure that risk adjustment payments reflect the true health status of enrolled members. Getting it right takes effort. It requires trained staff, careful administration, cross-referencing with clinical records, and a willingness to correct mistakes before submission. The cost of doing it poorly is measurable in recaptured payments and audit findings. The cost of doing it well is higher capitation rates that support the services your members actually need.