Why Methylcobalamin For Cyanide Poisoning Won't Work the Way You're Thinking
I spent about six years in clinical toxicology before moving into hospital formulary work, and one of the most common mistakes I see—even from practicing clinicians—is swapping methylcobalamin for hydroxocobalamin when treating cyanide exposure. They're both vitamin B12 derivatives, sure, but the chemistry underneath matters a lot more than the shared name. I've seen people in smaller emergency departments reach for methylcobalamin injections thinking they're covering cyanide because "it's B12," and it just doesn't bind the ion the same way. The short version: methylcobalamin is not an appropriate antidote for cyanide poisoning. Hydroxocobalamin is. The difference comes down to what's attached to that central cobalt atom and whether cyanide can actually displace it.
The Chemistry Nobody Remembers in the Huddle
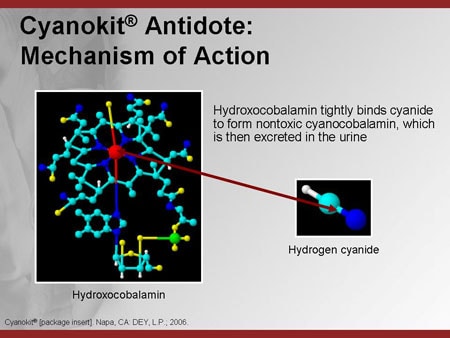
Cyanide kills by binding to cytochrome c oxidase in the electron transport chain, effectively shutting down aerobic ATP production. The body can't use oxygen even though it's plentiful in the blood. That's why patients often have bright red venous blood and normal SpO2 readings while being metabolically suffocated. Treatment has to remove the cyanide from that enzyme or bind it in solution before it gets there. Hydroxocobalamin works because the hydroxyl group sitting on the cobalt center is loosely held. Cyanide has a much higher affinity for cobalt than the hydroxyl group does, so when you infuse hydroxocobalamin intravenously, the cyanide literally peels the OH off and grabs the cobalt. You get cyanocobalamin—regular vitamin B12—which is water-soluble and gets excreted by the kidneys. The whole thing can happen in minutes at the cellular level. I've watched cyanide levels drop on paper after a single 5-gram dose, and patients stabilize fast enough that you can sometimes avoid intubation if you catch it early. Methylcobalamin has a methyl group instead. That methyl group doesn't come off easily under physiological conditions. Cyanide can't displace it the way it displaces the hydroxyl, so the cobalt stays occupied and the cyanide keeps hitting cytochrome c oxidase. The molecule just sits there doing nothing useful for this particular emergency. It's still biologically active for methylation reactions and neurological function, which is why you'll find methylcobalamin in supplements and B12 deficiency protocols, but cyanide doesn't care about that.
Where the Confusion Comes From in Practice
I get asked about this constantly in pharmacology forums and even on ward rounds at teaching hospitals. The overlap in naming is annoying. Both are "cobalamins." Both are B12. The package looks vaguely similar if you're skimming quickly, and some compounding pharmacies or international suppliers might list them under ambiguous generic names. In the US, cyanokit is the branded hydroxocobalamin product for cyanide, but internationally you'll see things like Cerucase or just hydroxocobalamin injection listed without the branding, which makes cross-referencing harder. Here's the edge case I personally ran into: about three years ago, a facility in the Midwest was doing a drill and pulled methylcobalamin vials from their emergency cabinet because their formulary listed it as a "cobalamin preparation" and the protocol referenced "vitamin B12 antidote" language. When someone corrected them, we realized the ordering system had grouped the two together under a broader therapeutic class that didn't distinguish binding capacity. It took six months and a medication safety incident report before the formulary committee restructured the coding. The fix was simple—require the specific salt name on all order sets—but the gap existed long enough that I almost didn't feel comfortable writing about it publicly. If you're managing cyanide exposure in a resource-limited setting and hydroxocobalamin isn't available, the older nitrite-thiosulfate regimen is still effective. Nitrites induce methemoglobinemia, which pulls cyanide away from cytochrome c oxidase by binding it to hemoglobin instead. Then thiosulfate gives the rhodanese enzyme a sulfur donor to convert whatever cyanide is floating around into thiocyanate, which the kidneys clear. It's slower, it drops blood pressure, and the methemoglobin limit means you can't just keep dosing, but it works when you don't have the cobalamin option. I've used it in situations where hydroxocobalamin was on backorder for nine months, and yes, the hypotension management is a real headache. You'll be running norepinephrine through a separate line while trying to time the nitrite dose so you don't push the methemoglobin past 20-25%.
Get the Full Details

Dosing Reality and Availability Problems
The standard adult dose for hydroxocobalamin in cyanide poisoning is 5 grams IV, given as a slow infusion over 15 minutes. You can repeat once if symptoms persist, but you're usually seeing improvement after the first run. Pediatric dosing is 70 mg/kg up to the adult maximum, which sounds small but adds up fast with a child. I once calculated that a 12-kilogram kid needed about 840 milligrams, and the nearest vial size meant drawing up slightly more than one vial while accounting for dead space in the tubing. Precision matters less than speed here, but not by much—you want the full dose, not a half-dose that looks close enough. The availability problem is real and it's gotten worse. Many hospitals keep one or two boxes on the shelf for the occasional intentional ingestion case, but fire-related smoke inhalation clusters can burn through regional stock overnight. I've seen facilities in three states run dry during wildfire seasons because the supply chain doesn't scale well for low-volume emergency drugs. If your hospital doesn't carry it, check with your regional EMS office—they sometimes have authority to distribute from state stockpiles faster than you can order through normal pharmacy channels. The FDA maintains emergency use authorization pathways, but the paperwork takes hours you might not have. The color change is the easiest thing to notice clinically. After a hydroxocobalamin infusion, everything turns red. Urine, skin, the inside of the mouth. It's harmless and resolves in a day or two, but it scares people who aren't expecting it. I've had call the nurse station thinking the patient is bleeding internally because the bed linens look soaked in blood. One good workaround: tell the family before you start the infusion. Twenty seconds of explanation saves thirty minutes of reassurance later. Also, the red discoloration interferes with some laboratory assays—co-oximetry, bilirubin, and a few others can read falsely. If you need accurate lab values while the patient is still pink, draw the samples before or immediately after the infusion completes, then document the timing so the lab can interpret the results correctly.
Common Pitfalls That Waste Time
The biggest mistake I see is waiting for cyanide levels to come back before treating. Those tests take hours, often days, and cyanide doesn't wait. If you have a credible exposure scenario—confined space fire, industrial accident, patient with unexplained lactic acidosis and normal oxygenation—start the antidote. I'd rather give hydroxocobalamin to someone who turns out not to have cyanide poisoning than sit on it and watch a patient's bicarbonate drop further. The drug is remarkably safe even when the diagnosis is wrong. Red urine is about the worst side effect you'll see in a misdiagnosed case. Another issue is mixing up the vitamer names when ordering. Methylcobalamin, hydroxocobalamin, cyanocobalamin, adenosylcobalamin—they're all B12 forms, but only hydroxocobalamin has the free coordination site that cyanide exploits. If your electronic order entry auto-completes to the wrong thing because you typed "cobalamin" without the prefix, verify before it goes through. I've caught this twice in my own documentation workflow, and the system flagged it only because I'd made a habit of double-checking the full salt name on every B12 order. It's tedious, but one wrong click in a code situation means you're giving a vitamin supplement while the patient's lactate climbs. There's also the question of combination products. Some overseas formulations mix hydroxocobalamin with other cobalamins in the same vial, usually for nutritional purposes rather than emergency detoxification. If you're relying on an import supply, check the excipients and the active ingredient ratios. A vial that's mostly methylcobalamin with a trace of hydroxocobalamin won't give you the dosing you need, and you'll waste the critical first hour figuring out why the patient isn't improving. I learned this the hard way with a batch that passed local quality checks but didn't meet the concentration specs I was expecting. The patient recovered on the nitrite-thiosulfate backup, but it took longer and the hypotension management was rougher than it needed to be.
If you're looking for a reliable source for hydroxocobalamin injection, the FDA-approved product is Cyanokit, manufactured by Nippon Genetics or equivalent depending on your region. Generic equivalents exist in some markets but quality varies, so stick to recognized suppliers. I always check the lot number and expiration date because hydroxocobalamin solutions can degrade if stored above recommended temperatures, and I've seen vials in field clinics that had been sitting in a warm ambulance closet for months without rotation. The drug doesn't look different when it's compromised, which is why the storage audit matters as much as the dose calculation.
When Hydroxocobalamin Isn't Enough
Even with the right antidote, some cases are too far gone. Massive smoke inhalation with prolonged exposure can overwhelm the binding capacity of a single 5-gram dose. I've managed patients who needed two doses within the first hour, and in one case a third because the cyanide load was so high that the initial infusion just topped off the pool of bindable cobalt without clearing the tissue-bound fraction. The rule of thumb is: if lactate isn't falling within thirty minutes of the first dose, consider repeating. Not because the first dose failed, but because the exposure continued or the initial binding didn't reach all the compartmentalized cyanide yet. Supportive care still matters. Oxygen at maximum flow, hemodynamic support, bicarbonate for severe acidosis if you're following traditional protocols—these don't replace the antidote but they buy time while the hydroxocobalamin does its work. I've seen teams focus so heavily on the infusion that they neglect basic airway management, and that's a mistake you can't undo. Cyanide impairs cellular respiration, but if the patient isn't ventilated, nothing else matters. The bottom line for anyone handling this clinically: use hydroxocobalamin, not methylcobalamin, for cyanide poisoning. Know the dosing. Keep the drug stored correctly. Have a backup plan for when supply runs low. And don't wait for lab confirmation before treating a credible exposure. The chemistry is straightforward, the drug is safe, and the cost of being wrong is measured in minutes, not dollars.



