Why Spongy Bone Looks Nothing Like What Your Textbooks Show You
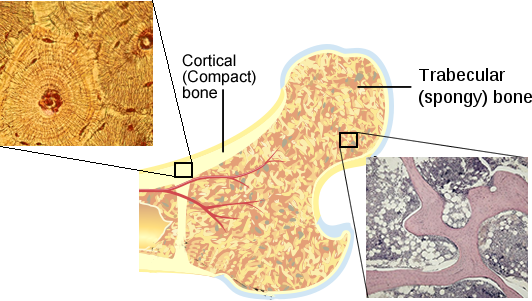
When you first look at a ground bone section under the microscope, the trabeculae seem straightforward enough—thin, interconnected plates and rods of bone tissue arranged in a lattice. But if you spend any actual time looking at them, especially at different angles or in different patients, you quickly realize that "spongy" is one of the most misleading names in histology. The architecture changes depending on where you are in the skeleton, how old the person is, and what mechanical loads that bone has been under for years. I used to think I could just point to the marrow spaces and call it a day. That stopped working about three years ago when I started cross-referencing histology slides with CT reconstructions, and the mismatch was frustrating. Spongy bone, also called cancellous or trabecular bone, sits between layers of compact bone in the interior of flat bones like the skull, the ends of long bones like the femur, and within vertebral bodies. Under the microscope, its defining features are the trabeculae themselves—those branching plates of lamellar bone interspersed with bone marrow spaces. The trabeculae run along lines of mechanical stress, which means their orientation isn't random but follows the principal stress vectors through that region of bone. What most sources leave out is that the thickness of individual trabeculae varies dramatically even within a single slide. Near a joint surface in the femoral head, you might see trabeculae that are 150 to 300 micrometers thick. Move toward the metaphyseal region and they can thin down to 50 micrometers or less. This variation matters because thinner trabeculae resorb faster during conditions like osteoporosis, and their loss follows a predictable spatial pattern—vertical trabeculae in the vertebral body go first, which is why vertebral compression fractures happen before hip fractures in many postmenopausal women. The vertical ones carry the main compressive load, but they're also thinner and more metabolically active, so they turn over more aggressively when hormonal signals shift.
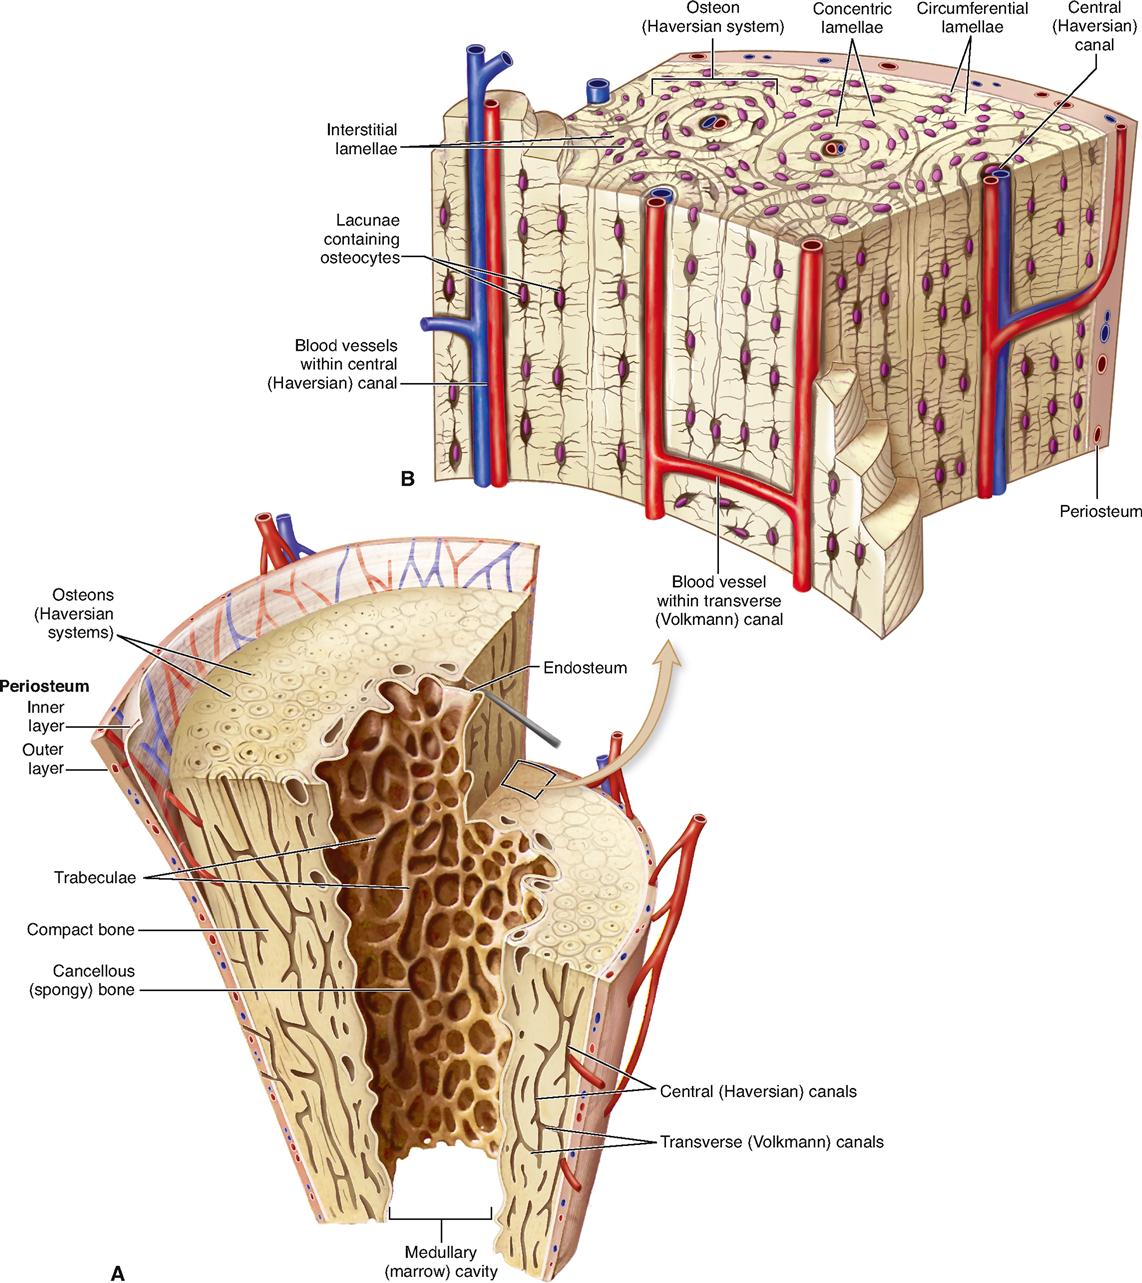
The bone tissue within each trabeculum is almost always lamellar in adults. You can see concentric or parallel lamellae just like in compact bone, though the spacing between lamellae tends to be slightly wider. The osteocytes sit in lacunae between these lamellae, and their canaliculi radiate outward to connect with neighboring osteocytes, forming the network that allows nutrient exchange since trabeculae are thin enough that diffusion from the marrow cavity reaches every cell. On the surface of each trabecula, you'll find a layer of flattened osteoblasts and occasionally some irregular osteoclasts doing their resorptive work. In active remodeling sites, you get what's called a reversal line—a darkly stained curving band that marks the boundary between old and new bone surfaces where remodeling has recently occurred. Marrow fills the spaces between trabeculae. In adult long bones, that's mostly hematopoietic and yellow marrow in varying proportions. The marrow doesn't just sit there empty-handed though. It sends vascular channels through the trabeculae via Volkmann's canals that run perpendicular to the long axis of the bone, connecting with Haversian systems in the adjacent compact bone. If you're sectioning a bone and the vasculature looks weirdly sparse in the spongy region, it could mean you've missed the plane of section or you're looking at a region of relatively avascular trabecular bone, which does occur in certain pathologic states. I ran into a real headache a couple years ago when I was trying to correlate micro-CT data with traditional histology sections of vertebral spongy bone. The micro-CT showed what looked like a well-connected trabecular network with decent bone volume fraction. But the ground sections from the same specimen revealed that large portions of those "trabeculae" were actually just articular surfaces viewed en face—essentially, the imaging was fooling me into seeing connectivity that wasn't really there in three dimensions. The workaround was to use serial sectioning at 20-micrometer intervals and reconstruct the volume manually, which took about four hours per specimen but saved me from publishing incorrect architectural measurements. If you're doing this kind of work, don't trust a single thin section. Get into the habit of looking at at least three sequential sections before drawing conclusions about trabecular connectivity.
Another thing that trips people up is the distinction between spongy and compact bone at the transition zone. There isn't really a hard boundary. The trabeculae near the cortex gradually merge with the outer circumferential lamellae, and you can often find Haversian systems that appear to grow directly out of trabecular surfaces. In osteoporotic bone, this region gets particularly messy because the cortical shell thins and the outermost trabeculae lose their connection to the compact bone entirely, becoming isolated islands that the body eventually resorbs. If you're grading bone quality from a slide, paying attention to whether trabeculae remain connected at their periphery to the cortex tells you more about structural integrity than the bone volume fraction alone. The cells you see in and on the trabeculae give you additional information beyond just structure. Osteoblasts lining active formation surfaces are cuboidal to columnar, while resting osteoblasts flatten out to become lining cells. Osteocytes appear as dark spots in lacunae, and their processes run through canaliculi that you can barely resolve without good staining. In tetracycline-labeled bone, which is the gold standard for studying dynamic parameters, you get fluorescent bands marking sites of mineralization. The distance between two labels given at known intervals lets you calculate mineral apposition rate. Without that labeling, you're stuck making assumptions about turnover rates based on static morphology, which is significantly less reliable. One counter-intuitive point: having more spongy bone isn't always better. Increased trabecular number sounds like good bone health on paper, but if those extra trabeculae are thin and disconnected, they contribute almost nothing to structural strength. The key parameters that actually predict mechanical competence are trabecular thickness, trabecular separation, and the degree of connectivity. A bone with fewer but thicker, well-connected trabeculae will outperform a bone with abundant but fragile-looking trabecular networks. This is why dual-energy x-ray absorptiometry, which only gives you areal bone mineral density, misses a huge chunk of what determines fracture risk. The microarchitecture matters independently of density.
Get the Full Details

If you're working with decalcified sections stained with H&E, the contrast between bone matrix and marrow spaces is decent but not great. For better visualization of trabecular boundaries and cellular details, toluidine blue or Masson's trichrome works significantly better. Toluidine blue especially makes the osteocyte lacunae and canaliculi pop out clearly, which helps when you're trying to assess viability in what looks like dead bone. If you need to specifically highlight osteoid—the unmineralized organic matrix—you'll want von Kossa for mineralized tissue and Goldner's trichrome, which stains osteoid bright green against the red bone matrix. Those two stains together will tell you immediately whether you're looking at normal remodeling, high-turnover disease, or an accumulation of unmineralized osteoid like in osteomalacia.
The Practical Side Nobody Talks About
Decalcification is where most people lose resolution in their spongy bone sections. Strong acids like hydrochloric acid work fast but destroy antigenicity and can blur cellular detail to the point where distinguishing an osteocyte lacuna from an artifact becomes guesswork. EDTA is slower—days to weeks depending on specimen size—but preserves morphology far better and keeps immunohistochemistry feasible if you need it. If you're in a hurry and use HCl, expect to lose the ability to do any staining beyond basic hematoxylin and eosin. That decision alone determines what else you can do with that section afterward. Section thickness for ground bone is another practical consideration. Decalcified sections cut at 5 to 7 micrometers show fine cellular detail but distort the trabecular architecture because thin sections miss the depth information. Ground bone sections at 50 to 100 micrometers preserve the 3D relationships better but make individual cell identification harder. The trade-off depends on what question you're asking. If you need to count osteocytes per unit volume, go thin. If you're assessing trabecular topology and connectivity, go thicker and accept the cellular blur. There's also the issue of sectioning artifacts that mimic pathology. When you cut through a trabecula at an oblique angle, you can create the illusion of a widened marrow space or a thinning trabecula that isn't actually there. A vertically oriented trabeculum seen edge-on looks like a thin line. The same trabeculum cut tangentially looks like a broad plate. Without knowing the orientation, you might misinterpret normal anatomical variation as trabecular thinning. Rotating the section slightly or looking at adjacent serial sections usually resolves the ambiguity, but only if you took those serial sections in the first place.
For anyone studying this material, I'd recommend starting with basic ground bone sections before moving into decalcified preparations. The structural relationships are clearer, the artifacts from decalcification are absent, and you get a better sense of what normal trabecular architecture actually looks like across different skeletal sites. Once you know what normal is, abnormal becomes obvious much faster. The reverse is also true—people who only ever look at H&E sections of decalcified bone tend to overcall pathology because they don't have a solid reference for how variable normal spongy bone actually is between individuals and anatomical regions.