What the MMSE Actually Measures (and What It Doesn't)
The Mini Mental Status Exam is a 30-point screening tool for cognitive impairment. That's about all you need to know before you start digging into the worksheet. It covers orientation, registration, attention and calculation, recall, language, and visuospatial skills. A score below 24 generally suggests some form of cognitive deficit, but the numbers themselves are where most people trip up. I've administered this instrument probably two hundred times across different clinic settings. The process itself takes about five to ten minutes if the patient is cooperative. But the worksheet portion - the actual scoring, the adjustments for education and language - that's where the real work happens. You can't just add up the points and move on.
Mini Mental Status Exam Worksheet
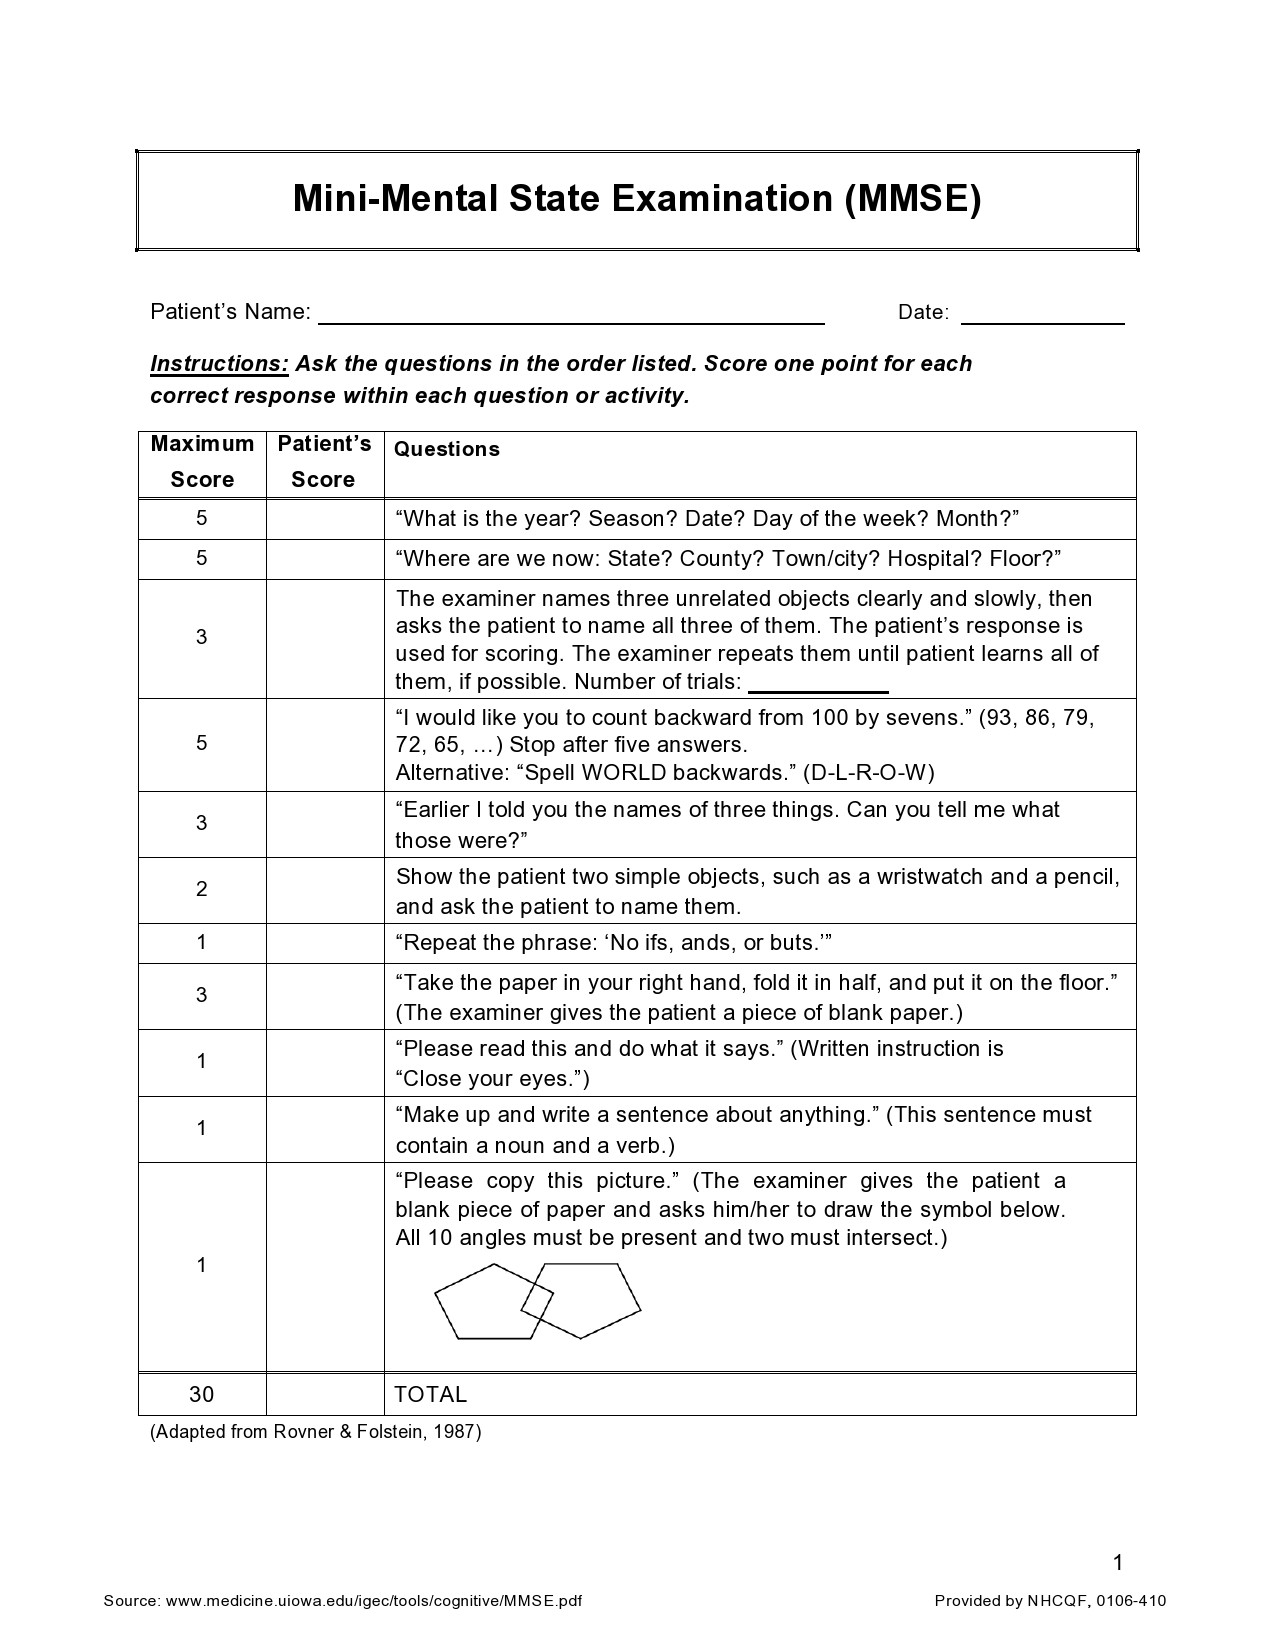
Here's how the scoring actually works in practice. The standard form has twelve sections. Orientation to time gets five points - year, season, month, date, day of week. Place gets five more - state, county, city, hospital, floor. Registration is three words repeated back immediately. Attention and calculation is either spelling "WORLD" backwards five points or counting backwards from 100 by sevens. Recall pulls those three words from registration after a three-minute delay. Language covers naming a pocket watch and a pencil, following a three-stage command, repeating a phrase, reading and complying, writing a sentence, and copying aintersecting pentagon. The trouble starts with the demographics section. You need to adjust for someone's education level and primary language. A person with less than a high school education typically loses about one to two points from their raw score. That's not in the original Folstein paper but it's standard practice in most clinical settings now. If you're working with a non-English speaker, the Spanish-validated version holds up reasonably well, but certain items like the serial sevens task become culturally loaded in ways that deflate scores without meaning real impairment. I ran into a case last year with a 72-year-old Spanish-speaking woman who scored 22 on the MMSE. She had no formal schooling past third grade and had spent her entire life in a rural town with almost no exposure to doctors or hospitals. The raw score looked concerning. But when I ran through the adjustments and then had her daughter describe her day-to-day functioning independently, the picture changed completely. She was managing her finances, cooking, taking medications without help. That 22 was a false flag. I documented the education adjustment and sent her for a more comprehensive neuropsychological battery instead of the memory clinic referral I'd initially considered. The full workup came back within normal limits.
One thing people consistently miss is that the MMSE heavily weights language and visuospatial functions at the expense of executive function. Someone with early frontal lobe pathology - dementia pugilistica, normal pressure hydrocephalus, vascular cognitive impairment - can score in the 25 to 28 range while having significant functional decline. The MoCA was designed partly to fix this gap. If you're doing a basic screen in a primary care office, the MMSE worksheet is fine. If you're tracking progression or ruling out something subtle, you're working with blinders on. Another pitfall: the recall component. Three words after a three-minute delay. But patients remember you're testing them. They'll employ strategies - repetition, association, whatever works - and inflate their score. I've seen patients who clearly struggle with short-term memory recall these words perfectly because they rehearsed them during the orientation section while waiting for me to ask the next question. It's not necessarily bad faith on their part. It's just how working memory functions under mild anxiety. Some clinicians now use visually complex nonsense shapes instead of words for the recall item to cut through that noise. The original MMSE doesn't include that variant, which means you need a modified worksheet to implement it. For the actual worksheet, you can grab a free copy from the National Institute on Aging website or use the version on the University of California San Francisco Older Epidemiology Center page. Both are public domain. I prefer the NIA one because it has cleaner fields for the education and language adjustments built in. The UCSF version is fine but it's the bare-bones Folstein format with no demographic columns, which means you're doing the math in your head instead of on the page.
Get the Full Details
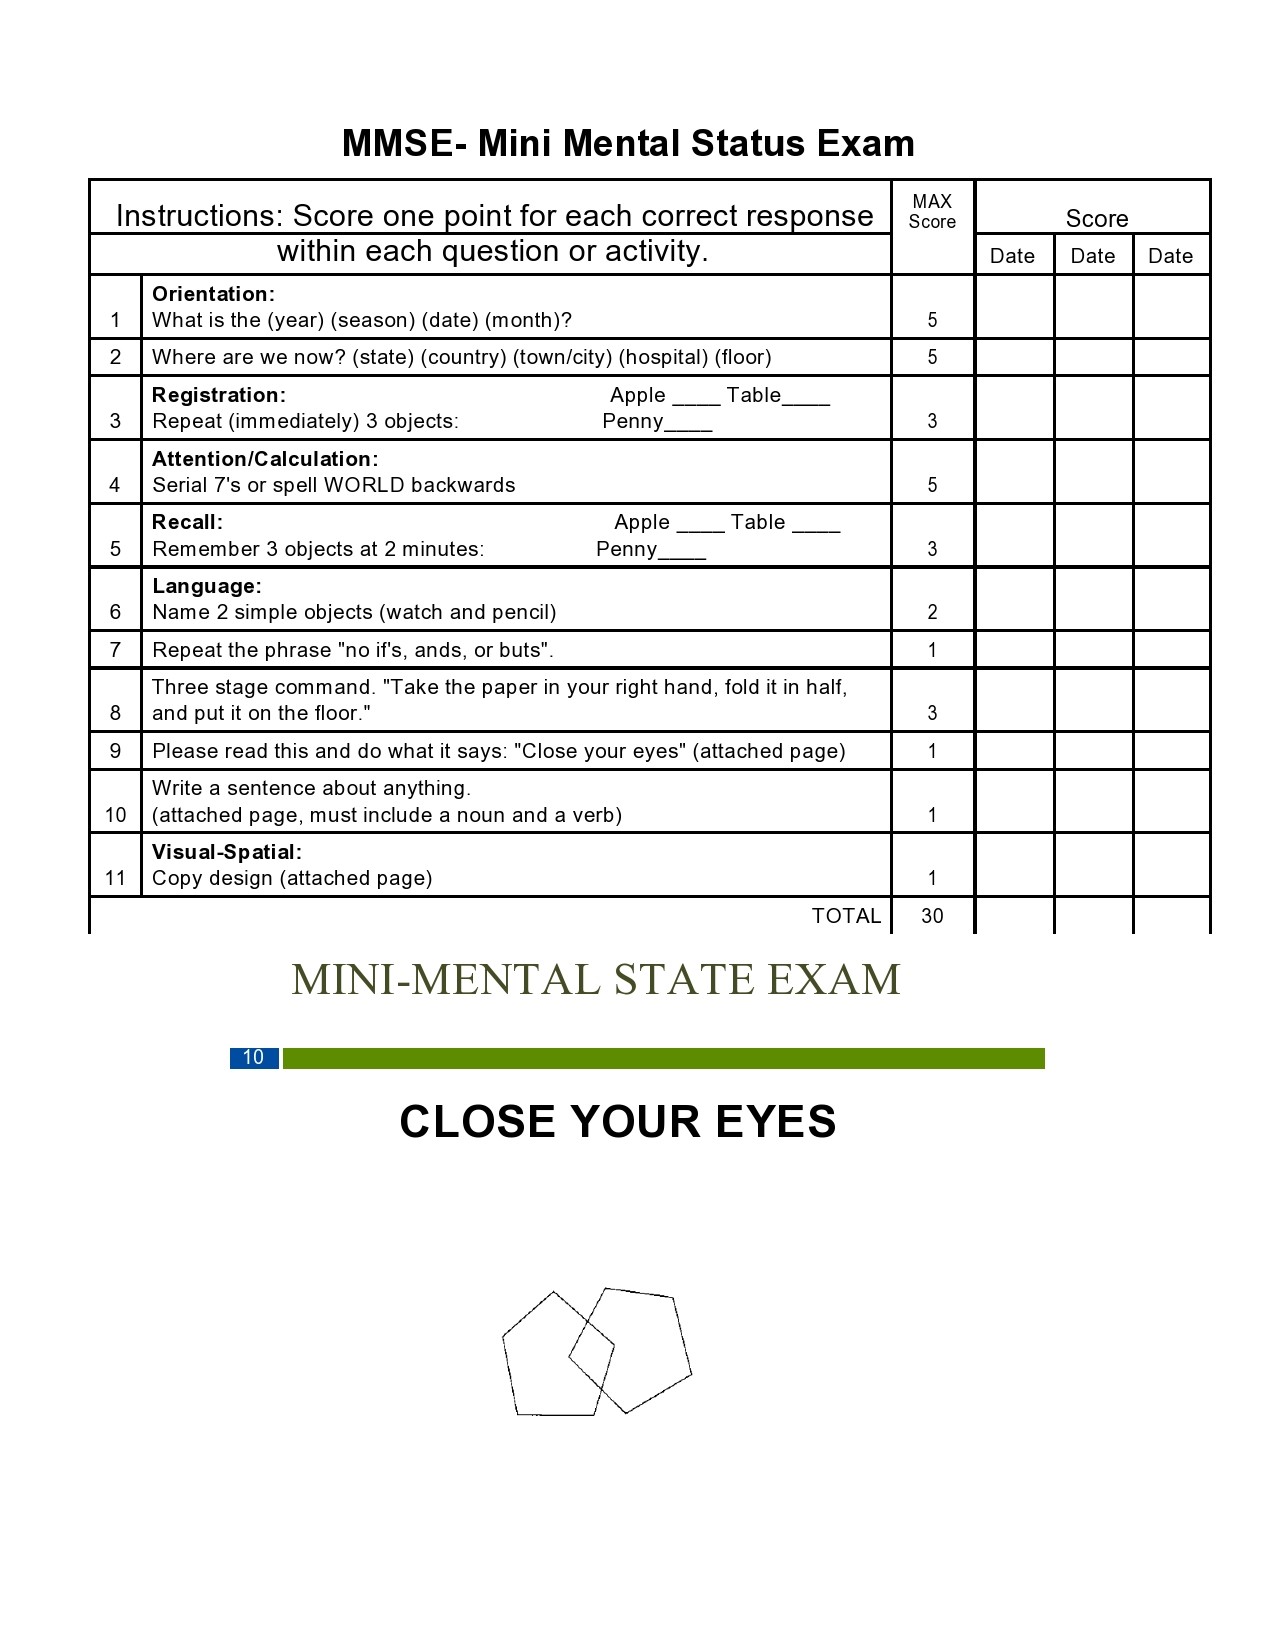
If you want a printable PDF that actually matches what I use in my sessions, here's the direct link to the NIA version: https://www.nia.nih.gov/health/mmoa-mini-mental-status-exam. It prints on a single page and leaves enough margin for notes, which matters more than you'd think when you're documenting a borderline score. The worksheet doesn't require certification to use, but that doesn't mean you should hand it to anyone. Interpreting the results properly requires clinical training. A score of 23 in an 80-year-old with diabetes and hypertension means something different than the same score in a 55-year-old with a history of depression and poor sleep. The instrument tells you there's likely something going on cognitively. It doesn't tell you what. That's the part that actually takes experience.