
What LPNs Can Actually Do in Missouri
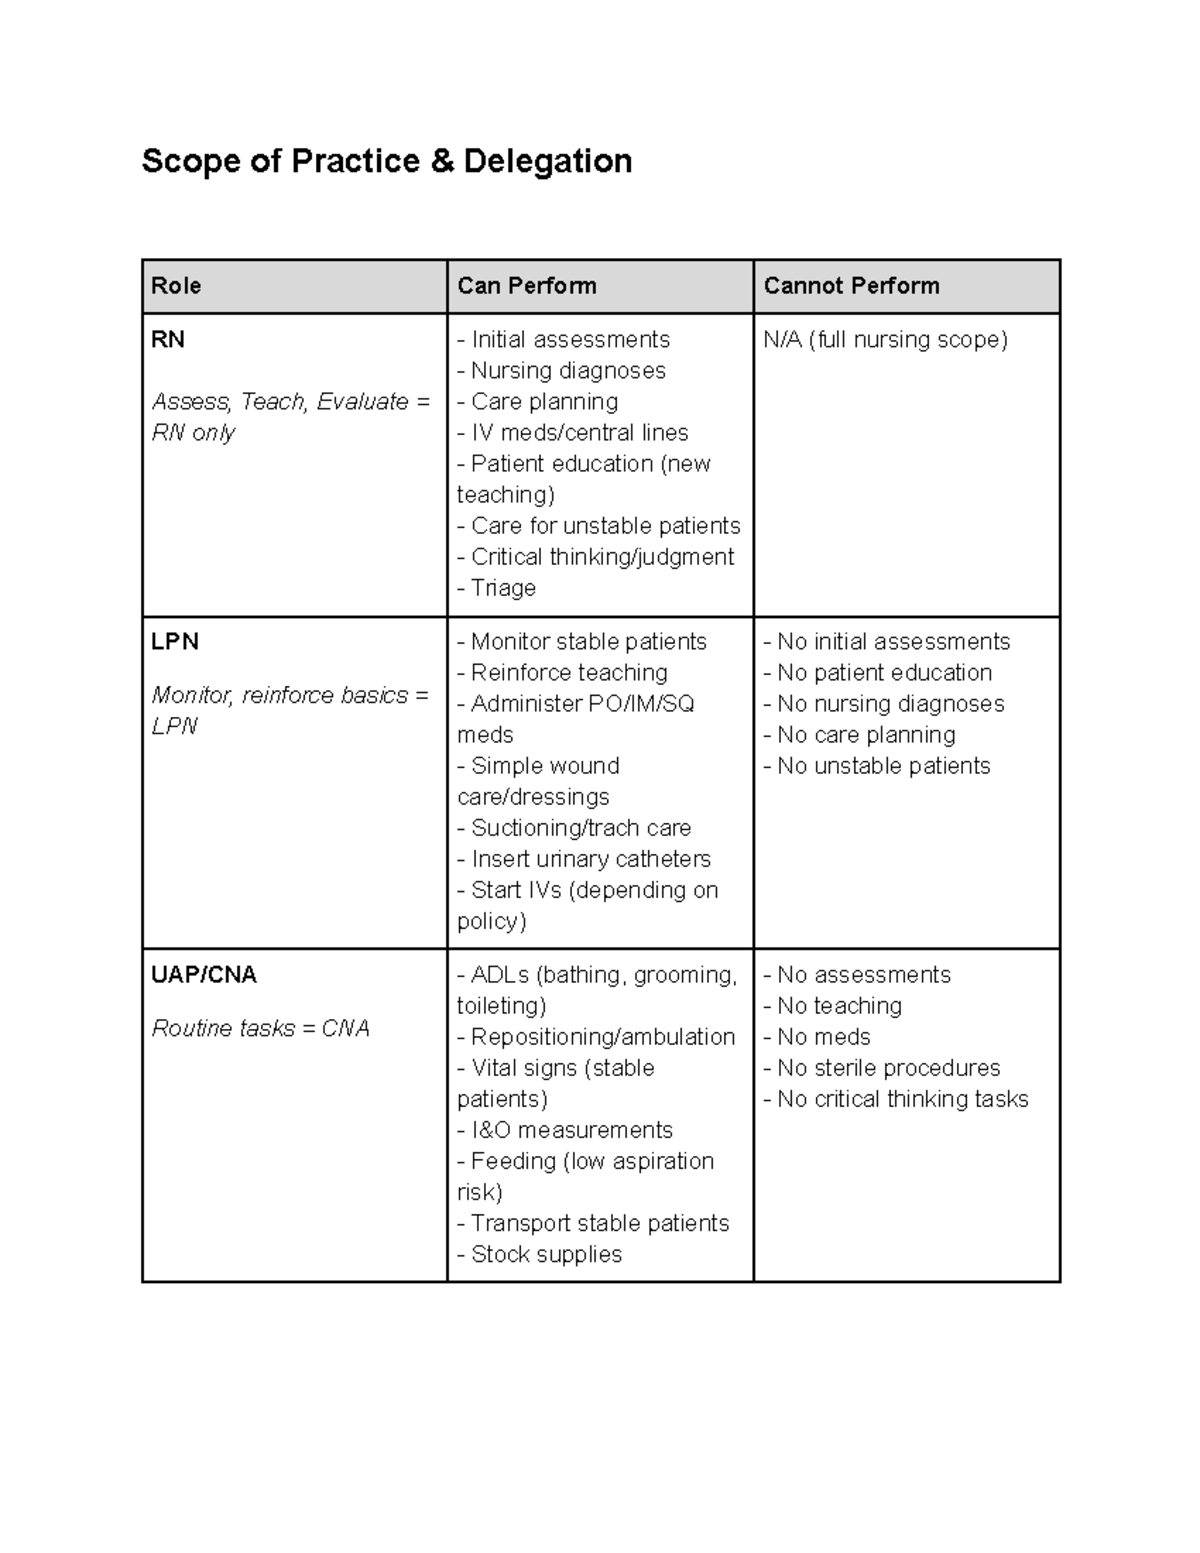
Missouri has one of those states where the nursing board drew pretty strict lines for licensed practical nurses. I learned this the hard way back in 2014 when I was working the night shift at a long-term care facility near Springfield. My charge nurse pulled me aside because I'd started setting up an IV push medication that technically required an RN in that particular unit, even though I'd done the same procedure without issue in Kansas just months earlier. The board rules aren't always consistent with what you pick up in other states, so I learned to keep my scope boundaries clear from the start. The Missouri State Board of Nursing governs what LPNs can do, and the official stance is pretty conservative compared to some surrounding states. LPNs in Missouri administer medications, manage wounds, collect specimens, and document patient status changes. That's the core of it. What they can't do includes starting IVs in most hospital settings, doing initial comprehensive assessments, and making nursing diagnoses that require RN-level judgment. The board calls it "nursing process" separation, and it matters more than you'd think when the surveyors show up. I've seen LPNs who thought they could do things just because they were competent and knew how. Competence doesn't equal scope, and Missouri isn't forgiving about that distinction. A lot of nurses move here from states like Illinois or Kansas where the LPN role is broader, and they hit walls immediately. It's not about quality of care. It's about legal liability and board definitions.
Medication administration covers oral, topical, intramuscular, and subcutaneous routes. IV medications are restricted in many settings unless you have additional certification and your facility's policy explicitly allows it. Even then, the RN must be available for supervision. That availability requirement trips up a lot of people. Available means actually reachable within the same unit, not "somewhere on the floor." I had a physician ask me to give a stat IV med at 2 AM when the only RN was three miles away at another campus building. I called it in and waited. My license was on the line, not the patient's outcome, which happened to stabilize after the RN arrived ten minutes later. Wound care falls within the LPN scope as long as it's established wound management. Initial assessment of a new wound? That's RN territory. Dressing changes, debridement with consent, and monitoring for infection signs are all fair game. I've done complex negative pressure dressing changes on sacral wounds without issue, but I learned early not to start wound evaluations independently. The board treats wound care boundaries pretty strictly during surveys. Documentation is part of the LPN role, and you need to document exactly what you did and observed. Medical shorthand is fine if your facility allows it, but never document something you didn't personally do. That's how lawsuits start. I've seen nurses document IV starts they didn't perform because the RN was behind, and it came back to haunt them during investigations.
Patient education is allowed but limited to reinforcing what the RN or physician already taught. You can't develop a new teaching plan for discharge instructions independently. Reinforcement and clarification are your lane, not the development lane. I spent years doing medication education for diabetic patients without issue, but I learned early not to develop new discharge teaching plans independently. The board treats patient education boundaries pretty strictly. IV therapy in Missouri requires additional certification through the board. Not all facilities offer IV nurse programs, so make sure yours does if you want to expand your scope. IV push medications are restricted in most hospital settings unless you have specific authorization and your facility's policy explicitly allows it. Even then, the RN must be immediately available for supervision. That immediate availability requirement trips up a lot of people. Available means actually reachable within the same unit, not "somewhere on the floor." I had a physician ask me to give a stat IV med at 2 AM when the only RN was three miles away at another campus building. I called it in and waited. My license was on the line, not the patient's outcome, which happened to stabilize after the RN arrived ten minutes later. The biggest pitfall I see is LPNs overextending into RN territory because they're competent. Competence doesn't equal scope, and Missouri isn't forgiving about that distinction. A lot of nurses move here from states like Illinois or Kansas where the LPN role is broader, and they hit walls immediately. It's not about quality of care. It's about legal liability and board definitions.
Get the Full Details
If you're working in a rural Missouri facility with staffing shortages, the board still expects you to stay within scope. Shortage doesn't authorize scope expansion. I've seen directors pressure LPNs to do things "because we need you," but your license is personal. The board doesn't care about your facility's struggles, and neither should you. For advanced practice, the Missouri Board offers IV certification programs through community colleges and healthcare systems. Not all facilities participate, so check yours. The application process usually takes about two weeks to process, depending on your program's schedule. Moving to another state like Iowa or Arkansas would give you broader LPN scope if Missouri feels too restrictive. Iowa allows more IV access and procedural scope. But then you'd need to recertify and learn new state rules.
The downsides of Missouri's restrictive approach are real. You'll encounter situations where you're perfectly capable but legally unable to help because of scope boundaries. That's frustrating and sometimes compromises care continuity. If the state rules feel too limiting, look into RN bridging programs or explore neighboring states with broader LPN scope. For certification details, the Missouri Board website has current scope documents, but they update annually. Check yours before the next board survey.




