How MLS Laser Therapy Actually Works For Nerve Pain
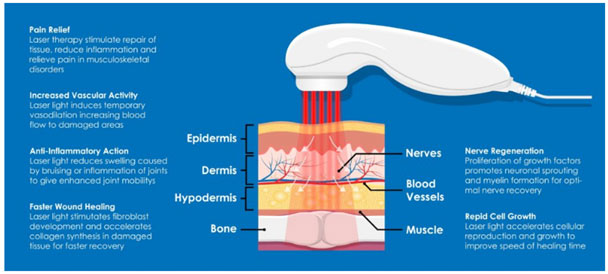
MLS stands for Multiwave Locked System. It is a specific type of low-level laser therapy that combines two wavelengths at once: an 808nm continuous wave and a 905nm pulsed wave. The two are phase-locked together, meaning they fire in a coordinated pattern rather than randomly. This design was built around the idea that one wavelength handles the anti-inflammatory and analgesic effects while the other addresses tissue repair and cellular energy. In practice, that translates to more predictable outcomes than running a single-wavelength device and hoping for the best. For neuropathy, the mechanism matters more than most people realize. Neuropathic pain is not just inflammation. It involves demyelination, axonal damage, and nervous system sensitization. The 905nm pulsed component penetrates deeper and is where you get most of the reduction in ectopic discharges from irritated nerves. The 808nm continuous wave works closer to the surface and manages the inflammatory cascade that often surrounds chronic nerve damage. Running both simultaneously through the MLS lock gives you that dual benefit in a single pass, which is why the protocol tends to be shorter than with older single-wavelength units.
MLS Laser Therapy For Neuropathy: Setting Up Parameters
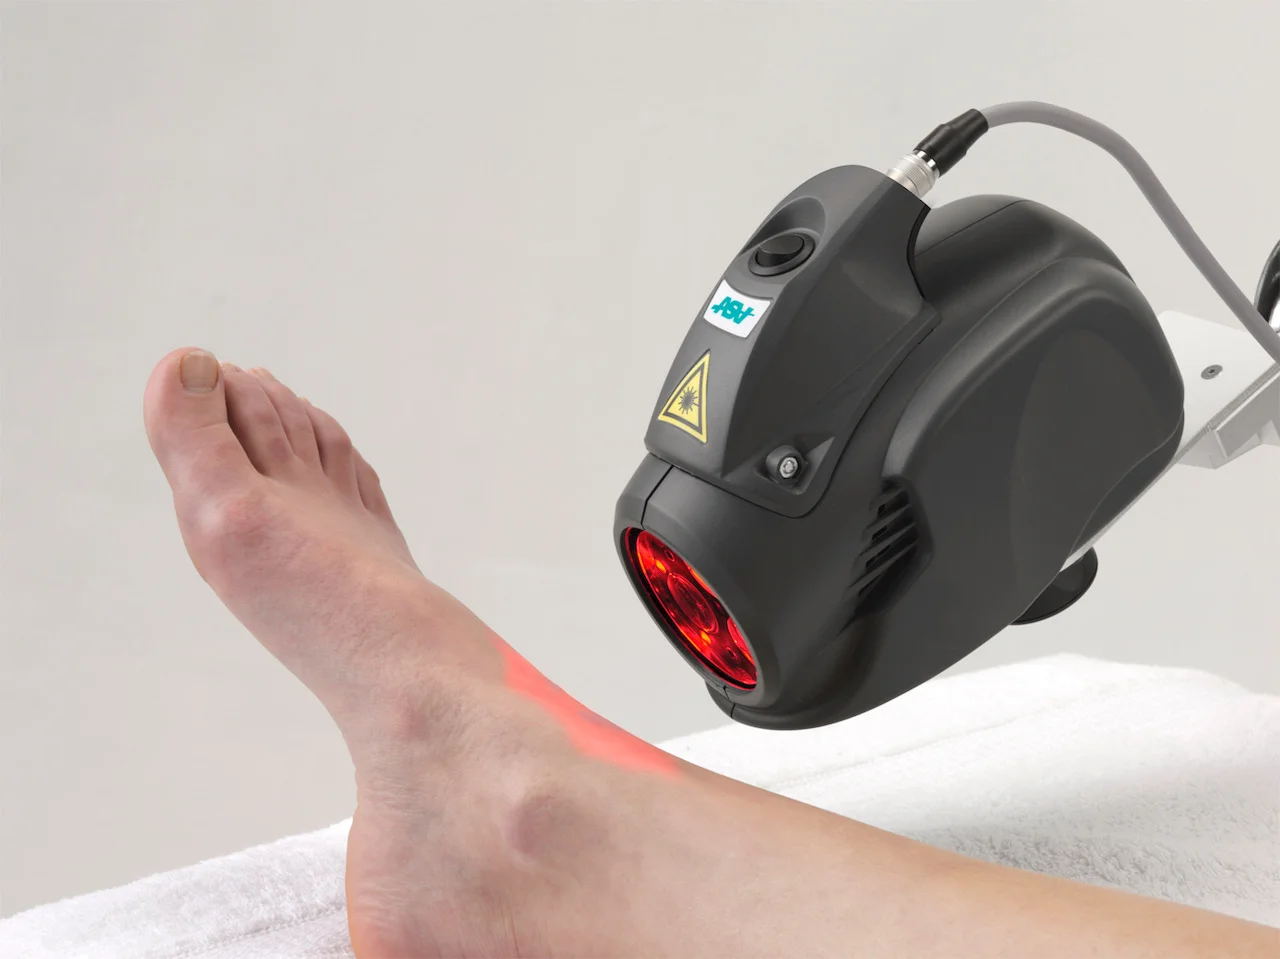
Here is how I set up a standard treatment. Wavelengths are fixed by the MLS device itself — you do not adjust those. What you adjust is power output, treatment time, application method, and contact style. Most neuropathy cases run between 600mW and 900mW effective output at the applicator tip, depending on the model. Treatment time per point is typically 60 to 180 seconds. A full session for bilateral peripheral neuropathy in both feet usually takes between 15 and 25 minutes total. The applicator matters a lot. I use the broad-surface applicator for larger areas like the distal legs and feet, and the pen-style probe when I am targeting specific nerve entrapment sites. For diabetic peripheral neuropathy, I map out treatment along the peroneal and tibial nerve pathways at the ankle, plus the dorsal foot region where sensory loss is most prominent. Each point gets the full dwell time before moving to the next. Contact vs non-contact: I prefer light contact with a small amount of coupling gel for the lower extremities. It keeps the applicator stable and ensures the wavelength delivery stays consistent. Air gap treatment is fine for more sensitive areas but you lose some energy transfer efficiency. The difference is noticeable on patients with thick plantar tissue or significant edema. In those cases, skipping the gel and holding 2cm above the skin gives better penetration because you are not losing energy to absorption in superficial layers.
What The Treatment Feels Like
Patients expect to feel something with laser therapy. Most feel nothing at all during an MLS session. There is no heat buildup, no tingling, no vibration. The 905nm pulsed component can produce a very faint warmth in some people, but it is subtle. If the patient reports heat, you are running too high or the applicator is sitting too still in one spot. Back it off. I have seen practitioners crank the output to 1W+ and wonder why a patient complains of burning. The therapeutic window for neuropathy is not about sensation. It is about dosing correctly. One thing patients do notice over a course of treatment is the change in symptom quality. Neuropathic pain often shifts from sharp and burning to a duller ache before it fades. That is a real clinical signal. It means the nerve is recovering, even if the patient has not yet crossed into full relief. I tell them this explicitly because otherwise they assume the treatment stopped working mid-course.
Get the Full Details

A Real Edge Case I Ran Into
I had a patient with long-standing diabetic peripheral neuropathy and significant autonomic involvement. Their feet were cold, pale, and had very poor perfusion. Standard MLS parameters produced absolutely zero clinical improvement after eight sessions. I kept thinking the dose was too low, so I increased time and output. Still nothing. The breakthrough came when I realized the issue was vascular, not dosing. I switched to a combination approach: MLS laser applied to the lumbar paraspinals at L4-S1 first to address neural input, followed by low-level laser to the plantar surfaces with the patient in a seated position with legs dependent for three minutes before each session. The positional change improved distal perfusion enough that the laser could actually reach the affected tissue. That single adjustment changed the response curve entirely. It took twelve total sessions before they reported meaningful reduction in burning pain, but it happened. The takeaway is that MLS works on the nerve, but the nerve needs blood flow to use the therapy. Without adequate perfusion, the photons hit dead tissue and bounce out. First, pre-treatment assessment with a tuning fork and monofilament is essential. Do not skip this. I track these baseline values at every visit. MLS does not produce dramatic overnight changes in sensation scores. Progress is incremental. If you are not measuring objectively, you will either overpromise or give up too early. Most protocols show measurable improvement around session six to eight, with continued gains through session twelve to sixteen. Treating beyond that point without reassessment is usually diminishing returns. Second, the contralateral effect is real but often overlooked. I treated a patient with unilateral peroneal neuropathy at the fibular head. After four sessions on the affected side only, they reported a 30% reduction in symptoms on the unaffected leg too. The systemic anti-inflammatory effect from MLS is not localized to the treatment site. This matters because it means you do not always need to treat both sides symmetrically in early-stage cases, though bilateral treatment still yields faster results overall.
Third, and this is important: do not combine MLS with topical anesthetic creams on the treatment area. Lidocaine patches or compounded creams numb the skin, which sounds helpful, but they also reduce cutaneous blood flow locally. That vasoconstriction counteracts the photobiomodulation effect. I learned this the hard way with a patient who had been applying lidocaine 5% patches nightly. Her neuropathy scores barely moved during the first ten sessions. Once she stopped the patches three days before treatment, her response accelerated noticeably. Patients will not volunteer this information unless you ask directly.
Limitations And When MLS Is Not The Right Call
MLS laser therapy for neuropathy is not a cure. It is a management tool. It reduces symptoms, improves nerve function markers, and can slow progression in some cases. It does not regenerate lost myelin in advanced diabetic neuropathy. It does not fix structural nerve compression from spinal stenosis or a herniated disc. If the underlying cause is mechanical compression, you need a different intervention. Laser will not decompress a nerve root. Open wounds and active infections in the treatment field are a hard stop. I once treated around a Stage 1 pressure ulcer on the heel by routing the applicator to surrounding tissue. The laser energy did not help the wound itself, and the patient's wound care team was not happy about it. Communication with the patient's primary provider is non-negotiable. Diabetic neuropathy patients are often under the care of multiple specialists, and running laser near compromised tissue without informing the responsible podiatrist is how you create liability problems. Patients on certain medications, particularly those that affect photosensitivity, require extra caution. Metformin itself is not a concern, but many neuropathy patients are on gabapentinoids, SNRIs, or other agents that can alter pain perception. This does not contraindicate treatment, but it does make objective measurement harder. I rely more heavily on quantitative sensory testing in these cases rather than subjective pain scales alone.
Practical Scheduling
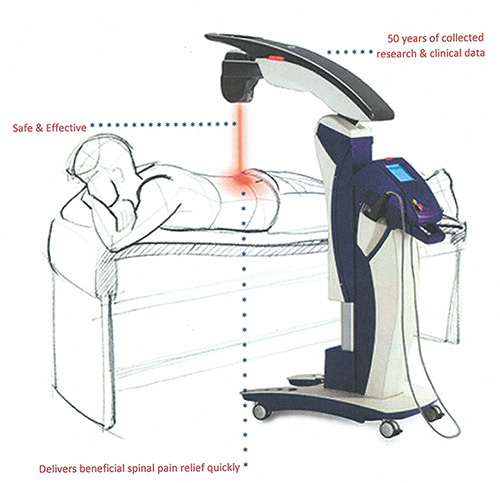
Initial phase: two to three sessions per week for the first three to four weeks. Maintenance phase: once weekly, then taper to every other week as symptoms stabilize. Total typical course is twelve to sixteen sessions before you reassess whether to continue, adjust parameters, or refer for alternative treatment. I have seen some patients maintain results for months after completing a course, while others relapse within two weeks if their underlying metabolic condition is not managed. The laser treats the symptom pathway. It does not fix the diabetes, the B12 deficiency, or the spinal degeneration causing the neuropathy. Those need to be addressed separately or the gains will not hold. There is no software download associated with MLS protocol management. The devices come with manufacturer-recommended parameter tables, but those are starting points, not prescriptions. The actual dosing requires clinical judgment based on tissue condition, comorbidities, and response tracking. If anyone is selling you a downloadable protocol generator that claims to replace clinical assessment, that is not something I would recommend relying on. The technology is well-understood. The application is where the skill lives.