What the MMPI-2 RF Actually Is
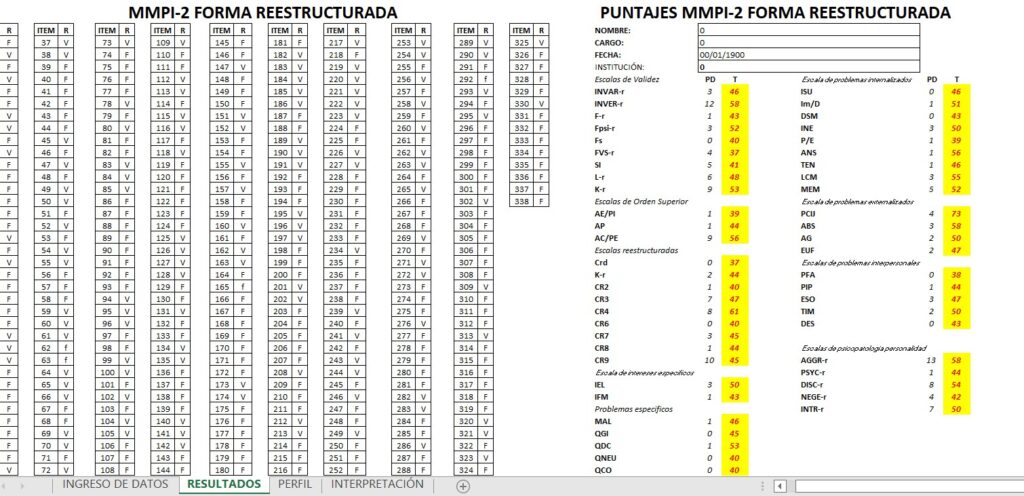
The MMPI-2 RF is a psychometric instrument, not a trick question exercise. It was restructured by Ben-Porath and Tellegen to cut down from the original 567 items on the MMPI-2 to 338, removing redundancy while keeping the core measurement properties intact. The RF version trades the traditional clinical scales for a set of restructured scales that are more internally consistent and less contaminated by demographics or response style artifacts. It's used primarily in clinical and forensic settings. You'll see it in competency evaluations, child custody cases, and pre-employment screening for positions that require psychological clearance. The scoring keys, norm tables, and interpretive guides are all separate from the original MMPI-2 booklets, which trips up a lot of people who grab the wrong manual.
Mmpi 2 Rf Test Questions
Here's the practical side of things. The test consists of 338 true/false statements. Items are drawn from the original MMPI-2 item pool, but a subset was selected based on empirical overlap with the restructured scales. You can't look at the raw items and predict the scale structure because the selection was data-driven, not theory-driven. That means someone studying the test to "beat" it will struggle with pattern recognition in a way they wouldn't with older versions. The restructured scales themselves include RC1 through RC9, plus several supplementary scales. The RC stands for "reconfigured clinical." Each one maps onto something conceptually similar to the old clinical scales but with cleaner psychometrics. RC1 aligns loosely with the old Hs, RC2 with D, RC3 with Pd, and so on through RC9 to Ma. There's also a pseudo-psychopathy scale that doesn't correspond directly to any old scale.
How the Validity Scales Work in Practice
This is where most people get tripped up. The MMPI-2 RF introduced VRIN-r and TRIN-r as replacements for the original VRIN and TRIN. VRIN-r flags inconsistent responding. It uses a pair-based approach where items with opposite scores in a matched pair increase the scale. The r-version has better homogeneity than the original. TRIN-r measures a yes-response bias, and it's modeled after the original TRIN but rescored against the new item pool. Then there's Fp-r, an infrequency-psychopathology scale designed to detect rare responding that isn't just random noise. And Fs-r, which flags atypical but motivated responding patterns. F-r is the frequency-invalidity scale, basically the modern replacement for the old F scale's invalidity function. These five validity scales give you more granular information than the original MMPI-2 provided. The cutoffs matter. VRIN-r above 88 T suggests inconsistency. F-r above 80 is flag territory. But the real issue isn't the numbers, it's the base rates. In outpatient clinical samples, you'll see elevated F-r scores fairly frequently from people who are genuinely distressed and reading items literally. A raw T-score of 85 on F-r isn't automatically invalidating. Context from the clinical interview matters more than people admit.
Get the Full Details

The Scoring Process
Scoring requires the official manual and answer sheets. You mark A for true and B for false, or the newer computer-based format handles it digitally. Raw scores convert to T-scores using the MMPI-2 RF norming sample, which was stratified to match U.S. census demographics from the early 1980s. That demographic profile is one of the book's oldest weaknesses, honestly. Modern populations don't match that baseline very closely, and the T-score tables don't adjust for it. I ran into a specific issue last year with a client who scored in the 130s on RC2 but had a VRIN-r of 82 and an F-r of 78. Standard interpretation would flag this as possibly invalid. But the person was actively paranoid and reading every item as a direct accusation. The items were loading on RC2 but also creating that inconsistent pattern. I cross-referenced the F-scores with the RC scales individually, checked whether the elevated items made thematic sense together, and determined the profile was valid despite the borderline validity scores. The workaround was comparing the RF profile against the full MMPI-2 clinical scales from an earlier administration. When the older profile showed the same pattern in the same areas, you can have more confidence the elevation wasn't a response artifact.
Common Pitfalls
People confuse the RF scales with the traditional clinical scales. They're related but not interchangeable. A score of 75 on RC2 is not the same thing as a 75 on the old D scale, even though both tap depression. The RF scales have different sensitivity and specificity, different cutoff conventions, and different normative bases. Using old MMPI-2 interpretations on RF scores produces wrong conclusions about half the time. Another mistake is treating the RF as a shorter, easier version of the MMPI-2. It's not easier. It's more efficient. The signal-to-noise ratio is higher, which means false positives drop but so does the ability to detect some of the subtler personality configurations that the original instrument caught through its longer form. If you need fine-grained assessment of complex personality pathology, the full MMPI-2 still has advantages. The response format matters too. Some people answer every item as true because they want to present well. Some do the opposite. The MMPI-2 RF has a ?-count field that tracks omitted or double-marked items. If that number gets above roughly 30, the profile becomes questionable regardless of what the scale scores say. Most scorers I know just note it and move on without dropping the whole profile unless the ? count exceeds about 40.
What You Should Know Before Administering
You need the official publisher materials from Pearson. The test is copyrighted and restricted to qualified purchasers with appropriate training. Using unauthorized copies of the item list or answer keys is a violation and produces unreliable results because unofficial versions sometimes have outdated or incorrect scoring keys. The items themselves aren't secret, but the scoring combinations and norming data are proprietary. Reading time for most adults runs about 45 to 60 minutes. People with reading difficulties or cognitive impairments will take longer, and the norms don't account for that extension. The test isn't recommended for individuals below roughly an 8th grade reading level without accommodations, and even then the validity of the responses becomes harder to interpret. There's also the issue of language versions. The MMPI-2 RF has been translated into Spanish and several other languages, but the validation work on those versions isn't as thorough as the English original. Using a translated version without access to the translated manual and norms introduces error. I've seen cases where a bilingual client's elevated scores turned out to be translation artifacts rather than genuine clinical elevations.

When It Falls Apart
The MMPI-2 RF struggles with certain populations. malingering detection is one area. The Fs-r scale helps, but determined feigners who study the test can produce profiles that look valid while being entirely fabricated. The new FBS-r (Response Bias Scale) on the full MMPI-2 helps here, but the RF version doesn't include it in the standard packet. If malingering is a concern, the full MMPI-2 or MMPI-2-RF with supplemental scales is the better choice. Cultural bias is another limitation. The norming sample was predominantly white and non-Hispanic. Black, Hispanic, and Asian American respondents don't always map cleanly onto those norms. Elevated scores in these groups sometimes reflect cultural differences in endorsement patterns rather than psychopathology. I've seen qualified clinicians misinterpret a Black client's moderately elevated RC4 and RC9 scores as antisocial tendencies when the pattern actually reflected cultural response styles and contextual factors that never got discussed. The bottom line is that the MMPI-2 RF is a solid instrument when used correctly by someone who understands its limitations. It's not a shortcut, it's not a magic lie detector, and it doesn't replace clinical judgment. It gives you data points that need interpretation in context. Treat it like a piece of evidence, not a verdict.
Accessing the Materials
Pearson Clinical Assessment distributes the MMPI-2 RF through their official channels. Qualified professionals need to provide proof of credentials before purchasing. The kit includes the stimulus book, answer sheets, scoring key, and manual. There's also a Q-Sort version for qualitative analysis. Software scoring is available through PAR and other authorized platforms, which handles the T-score conversion automatically and flags validity concerns. Research copies are sometimes available through universities with clinical training programs. If you're a graduate student, check with your program director about institutional access before trying to source the materials independently. Unauthorized distribution of the items or scoring keys isn't worth the risk.