Opening and Reflecting the Flap
The Modified Widman Flap Procedure is a periodontal surgical approach designed to gain access to the root surface and underlying bone without excessive tissue removal. It's not a flap you throw open and hope for the best. You make precise incisions, elevate the flap with care, and then you do the actual work—debridement, root planing, maybe some osseous recontouring—before replacing everything exactly where it belongs. I learned this technique during my periodontics residency back when they still expected us to place sutures without complaining too loudly. The thing nobody tells you straight away is that the success of this procedure hinges almost entirely on how cleanly you can reposition the flap. If the margins don't adapt, you're going to have a rough healing period and a patient who wonders what went wrong.
Step-by-Step Modified Widman Flap Procedure
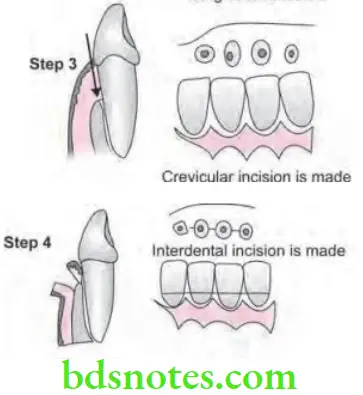
Start with a proper assessment. You need vertical releasing incisions, usually placed at the line angles of teeth or just slightly facial to them. The goal is to preserve papillary tissue on the adjacent teeth so you aren't left with black triangles after healing. I've seen residents place the release too far mesially or distally and then spend twenty minutes trying to work around missing tissue. Don't do that. Measure twice, cut once. Next, you make the internal bevel incision. This is the critical cut. You're aiming for a bevel that removes about 0.5 to 1 millimeter of the sulcular epithelium and gingival margin, angling the blade toward the apical direction at roughly 10 to 15 degrees. Too steep and you sacrifice too much attached gingiva. Too flat and the flap won't reflect properly. The blade should be parallel to the long axis of the tooth as you advance. Once that incision is complete, you elevate the full-thickness mucoperiosteal flap. Use a periosteal elevator starting at the crestal area and work your way coronally. You want subperiosteal reflection to expose the underlying bone and root surfaces fully. Split-thickness flaps have their place, but for a true Modified Widman, you're going full thickness so you can see exactly what you're working with.
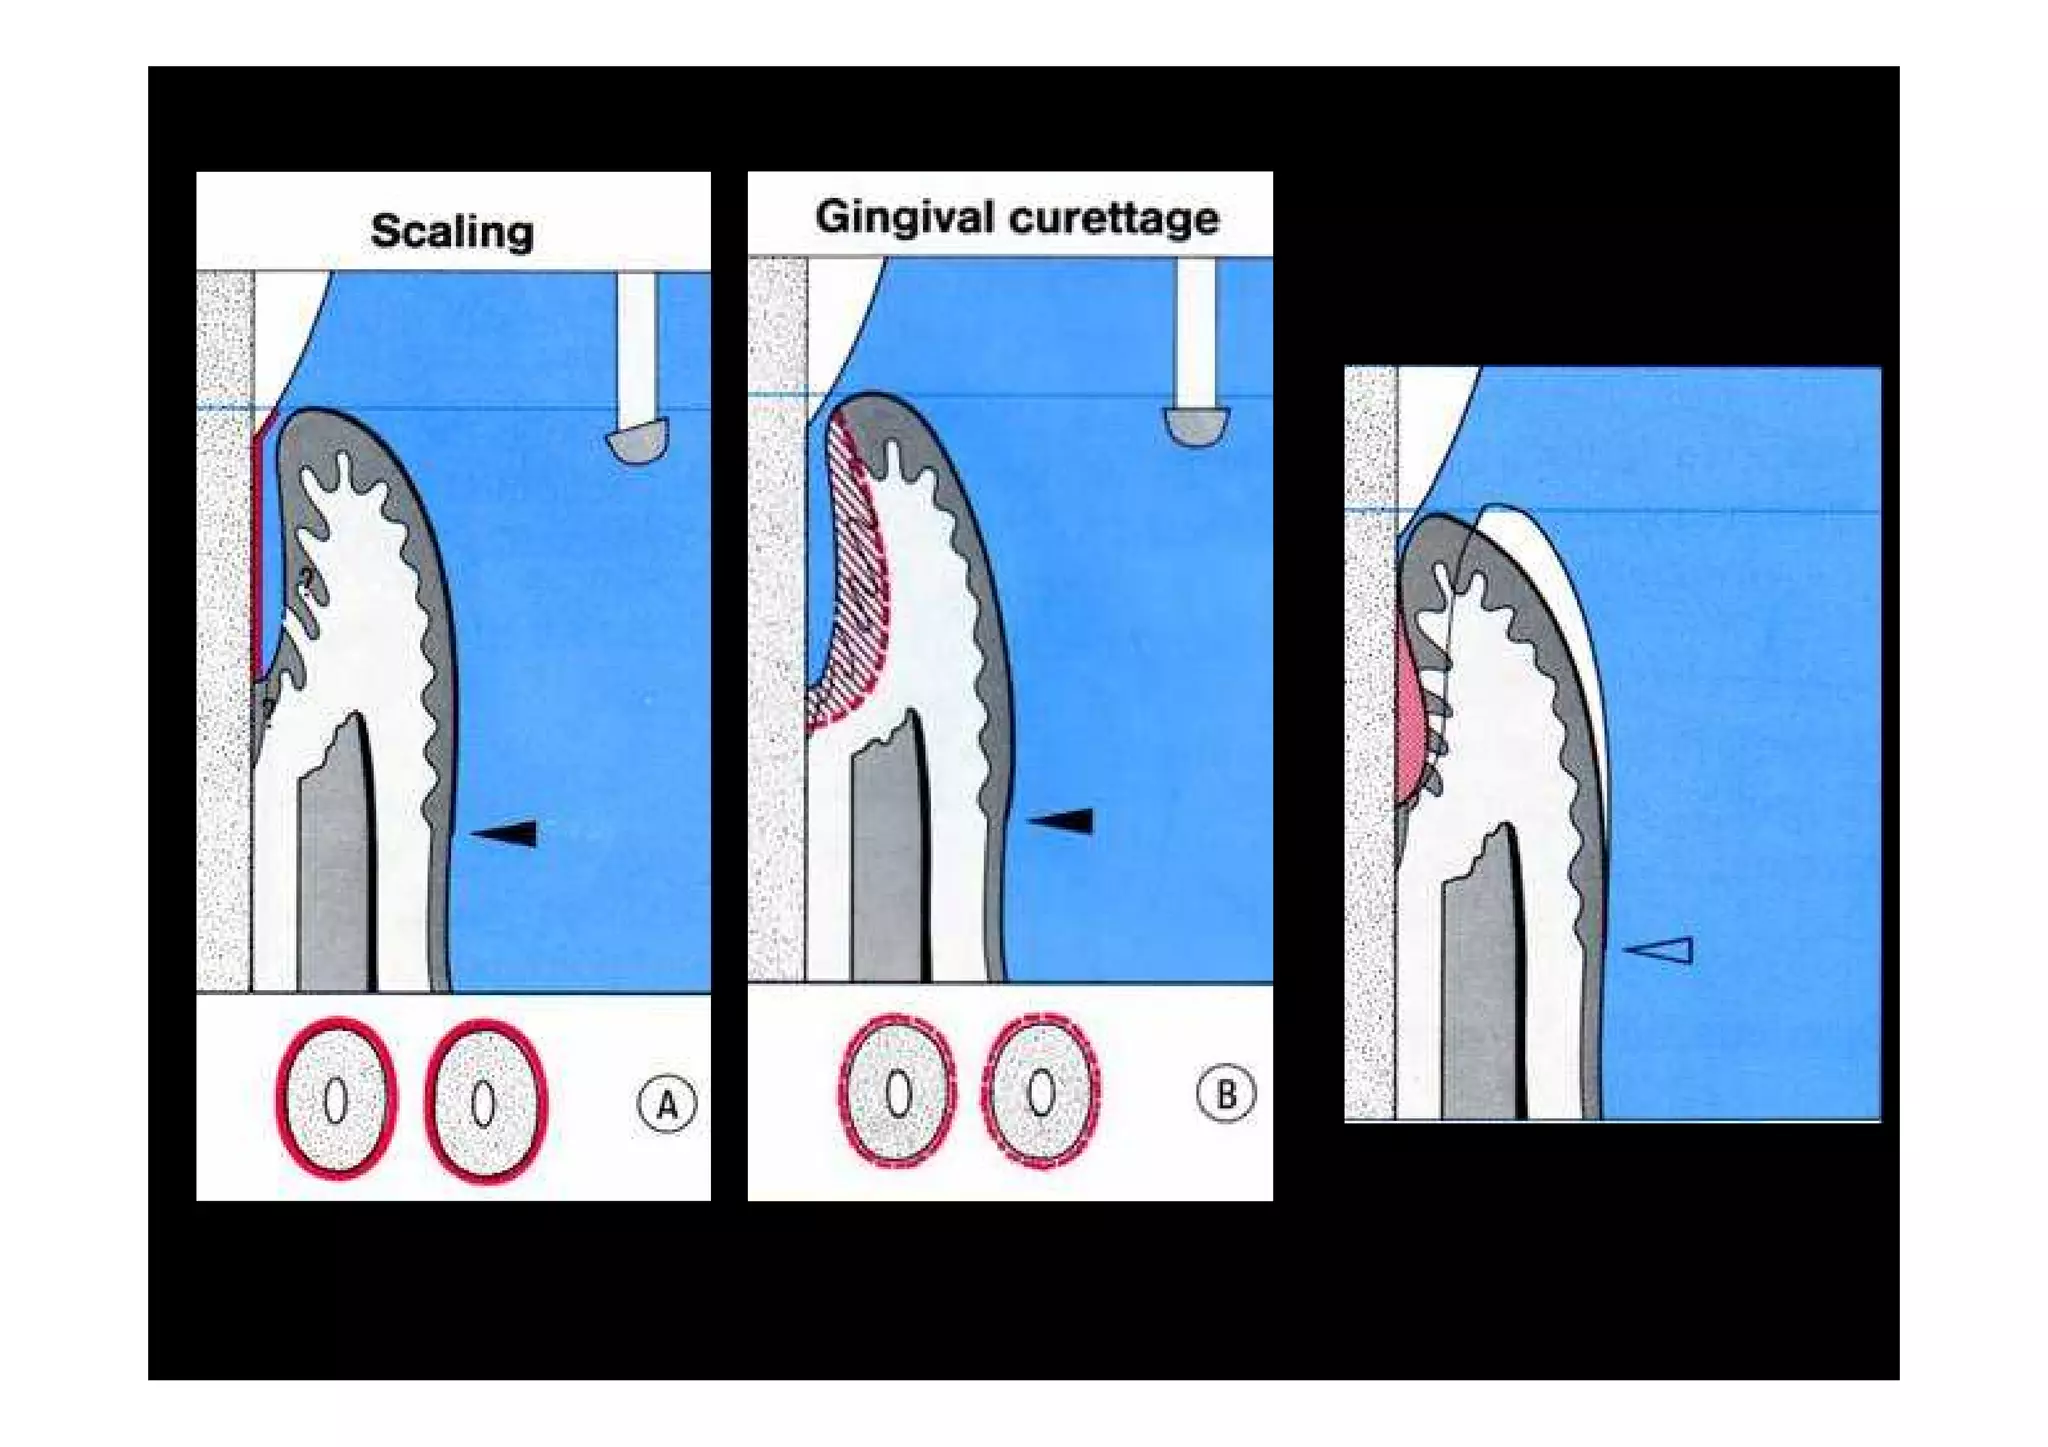
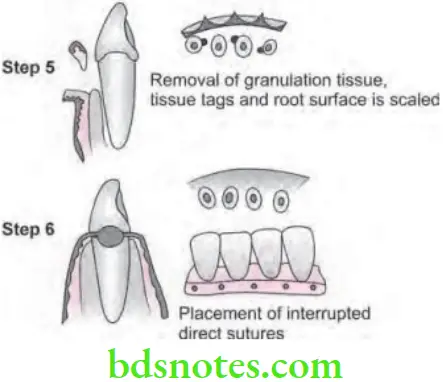
With the flap reflected, you proceed to mechanical debridement. Remove all calculus, plaque biofilm, and granulation tissue from the root surfaces. This is where you do thorough root planing. I typically use a combination of Gracey curettes and ultrasonic tips, finishing with hand instruments to confirm the surface is smooth. You'll know you're done when the root feels glassy under the explorer. Anything rough is a recipe for recurrence. After debridement, you assess the alveolar bone. If there are infrabony defects or irregular contours, you may perform osseous recontouring with a bone file or surgical bur. This is optional depending on the case. Some clinicians skip it entirely for purely soft tissue indications. Fine by me—I tend to do minimal recontouring unless the bone is clearly disrupting the normal architecture. Now comes the part that separates competent surgeons from the rest: closure. Place the flap back into its original position. The internal bevel should mate precisely with the vertical releasing incision. I use 4-0 or 5-0 silk sutures for most cases, placing interrupted sutures every few millimeters along the incision line. The key is to adapt the tissue without pulling it taut. Over-tightening sutures cause ischemia and poor healing. Under-tightening and the flap falls apart before day three.
Get the Full Details
Screw sutures—those little cross-hatched technique where you pass the needle through the papilla both buccally and lingually—are my go-to for the interdental areas. They hold better and maintain papillary position more reliably than simple interrupted sutures alone. I've lost count of how many flaps I've closed this way over the years.
What Makes This Different from Other Flaps
The original Widman flap, developed by Buser and Lang in the 1970s and later modified by Wide man himself, was designed to provide access while preserving as much gingival attachment as possible. The modified version refines the incision design and flap handling to reduce postoperative sensitivity and improve cosmetic outcomes. It's not a gingivectomy. You're not removing tissue—you're reflecting it, cleaning underneath, and putting it back. One counter-intuitive point that catches people off guard: the Modified Widman Flap Procedure actually promotes more root coverage in the long run compared to simpler coronally repositioned flaps in certain situations. This seems backwards until you consider that the preserved blood supply from a full-thickness reflection maintains the viability of the marginal tissue. When you don't denude the tissue or strip the periosteum, the gingiva heals tighter against the root than you'd expect. I've had patients come back at six months with genuinely surprising recession stability. Another nuance beginners miss is the importance of the internal bevel angle relative to the tooth's long axis. If the tooth is tilted labially or lingually, your bevel angle needs to adjust accordingly. A one-size-fits-all approach to the incision produces uneven flap margins that never seat properly. I had a case once where a mandibular premolar was significantly lingually tilted, and my initial bevel was parallel to the arch instead of the individual tooth axis. The resulting gap at the incision line bled for days. I had to reopen, recut, and resuture. Cost me two extra appointments. Now I always trace the long axis of each tooth before making that internal bevel.
Indications and When It Falls Apart
This approach works well for moderate to severe chronic periodontitis with pockets of 5 to 7 millimeters where access is needed for thorough debridement. It's also useful when you need to visualize furcations or perform regenerative procedures underneath. The literature supports its use for pocket reduction and creating a maintainable environment. But here's the blunt truth: if you have a patient with thin biotype, severe recession already present, or inadequate keratinized tissue, the Modified Widman Flap Procedure might not be your best bet. You'll end up with even more recession post-op and a patient unhappy with aesthetics. In those cases, a coronally advanced flap or connective tissue graft combined with a modified approach gives better results. I've watched colleagues push this technique on thin-biotype patients and then scratch their heads when the gingiva receded another two millimeters during healing. Pregnant patients, uncontrolled diabetics, and heavy smokers also represent relative contraindications. The wound healing response is compromised in all three groups, and a surgical flap that should close cleanly can become a source of infection and delayed healing. I always check HbA1c and smoking history before scheduling. A quick conversation about expectations saves everyone frustration later.
Post-Op Reality
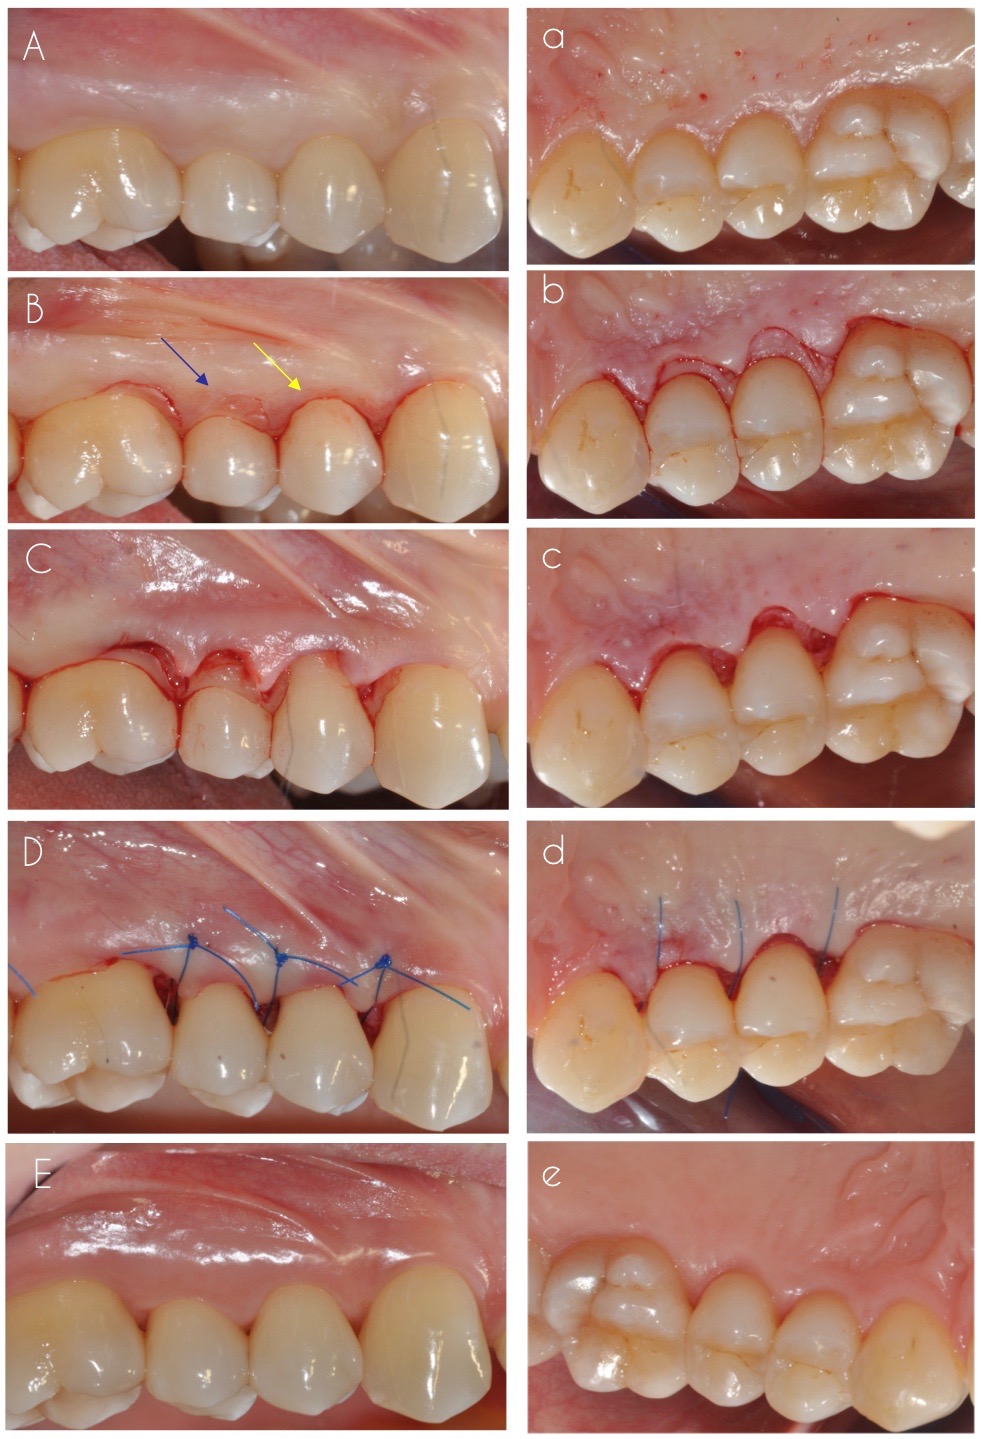
Patients should expect some swelling for 48 to 72 hours and mild discomfort manageable with ibuprofen or whatever analgesic you prescribe. Sutures typically come out around 7 to 10 days. Chlorhexidine rinses for two weeks post-operatively help maintain cleanliness in an area the patient won't want to brush aggressively. I tell them to use a soft brush and be gentle for at least two weeks, then gradually resume normal hygiene. Most patients return to routine care within ten days if everything went smoothly. Long-term outcomes depend heavily on the patient's maintenance schedule. This procedure buys you a cleaner foundation, not a lifetime of free passes. Patients who commit to three-month recall intervals see the best results. Those who slip to six months or longer tend to lose the gains within a year. I've seen it happen repeatedly. The Modified Widman Flap Procedure remains one of the workhorse techniques in periodontal surgery. It's not glamorous. It doesn't make for exciting conference presentations. But when you need reliable access, predictable healing, and preservation of tissue, it does what it's supposed to do without fuss. Just make sure your incisions are planned, your reflection is clean, and your closure is precise. The rest follows.