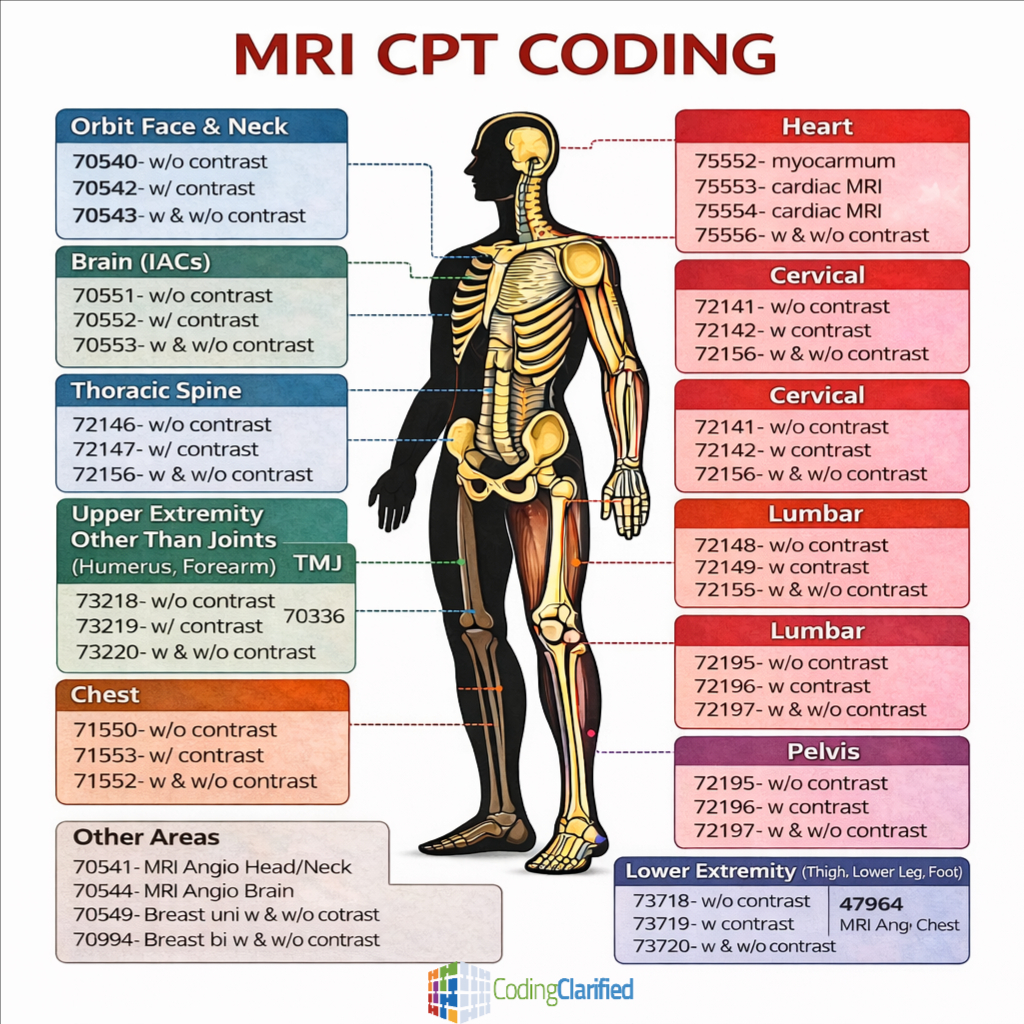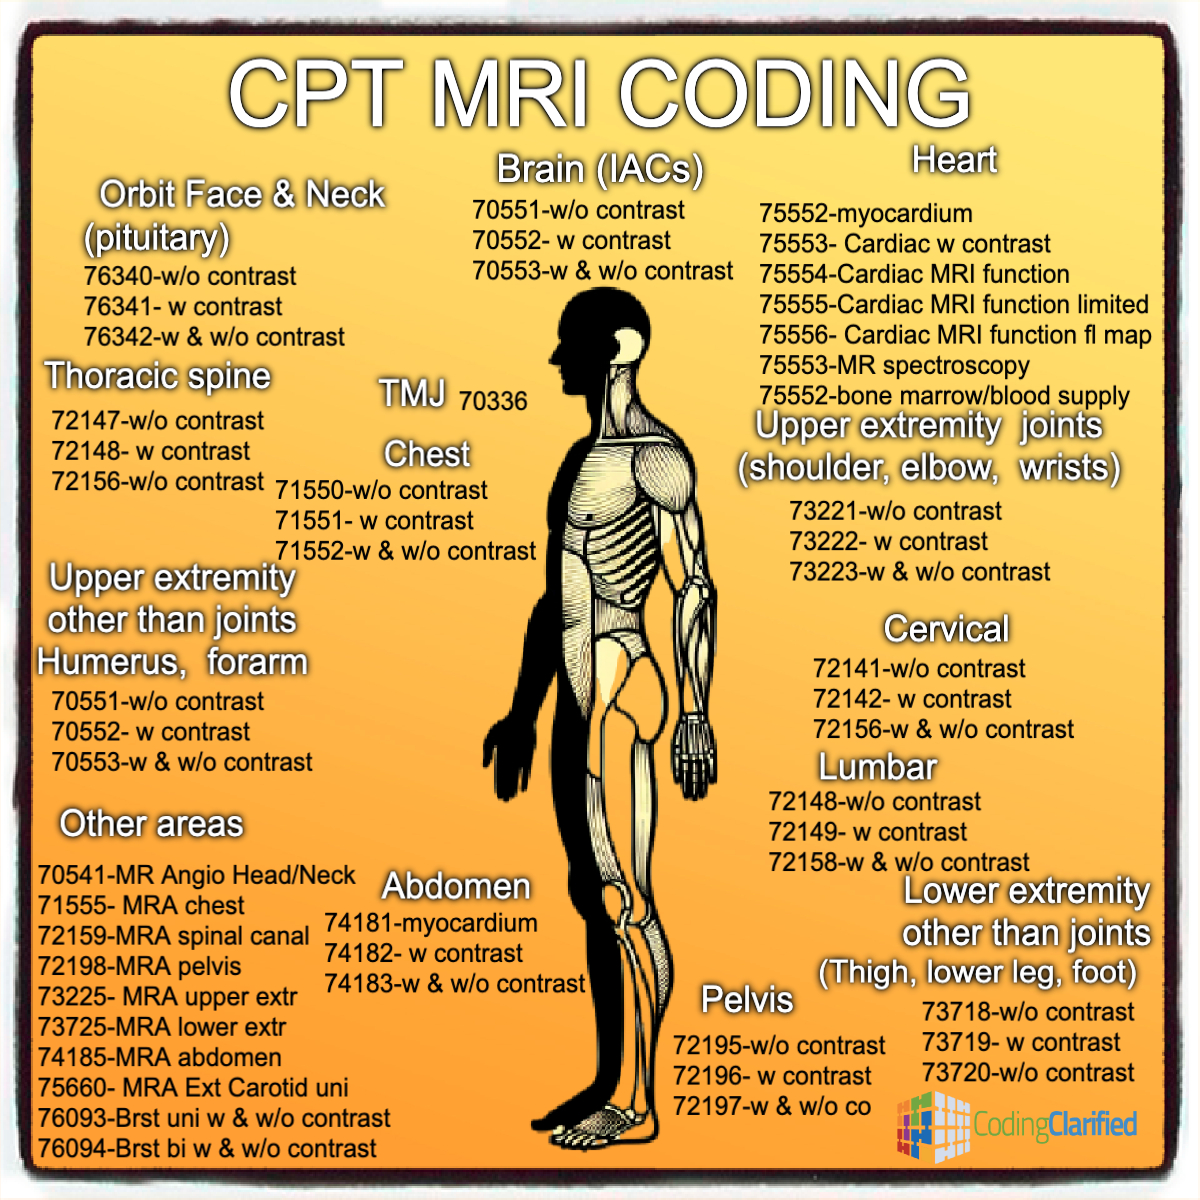
Running MRI CPT codes isn't as simple as looking up a body part and picking a number
I spent three years in a radiology practice where the billing team and the rad docs were constantly at odds over sequencing and modifiers. The core problem was that nobody understood how MRI CPT Coding Guide actually maps to the clinical reality of a scan. You'd get a procedure note that said "MRI brain with and without contrast" and someone would just grab 70553 and call it done. That's one of the most common errors I saw, and it costs practices real money when claims get denied. A CPT code is just a five-digit number that tells the payer what you did. But an MRI is different from an X-ray because you're dealing with multiple sequences, with or without contrast, and sometimes multiple anatomical regions. The American Medical Association publishes the current CPT manual every year, and the radiology section gets updates that matter. For instance, in 2023 they revised several neurological imaging codes to better reflect modern protocols. The guide itself is a reference document that coders use to match clinical documentation to the right code. It's not a substitute for reading the official CPT descriptors. I've seen junior coders copy-paste from online summaries and get burned when payers reject claims based on the exact wording in the manual. The manual always wins in an audit.
How to Actually Code an MRI Correctly
Start by reading the procedure note carefully. I remember one case where the radiologist performed a dedicated MRI of the left shoulder with contrast but the referral said "right shoulder MRI." The coder blindly picked 73221 based on the referral, and we spent four months fighting the denial. The note had the laterality correct, but the request form didn't. Always verify against the actual procedure, not the order. Here's the step that most people skip: check whether the scan included contrast and which sequence was performed. A brain MRI with gadolinium is 70553, but without contrast it's 70552. The difference matters for payment and for whether the payer considers it medically necessary. Some plans require prior authorization for the contrast version and will deny the non-contrast code if the note mentions gadolinium was administered. Multiples are another trap. If you image the brain and the orbits in the same session, that's two separate procedures. The CPT manual has specific guidance on combination imaging. In my experience, bundling these into one code is the fastest way to get an audit flag. Use 70553 for the brain and 70047 for the orbits, and make sure the note documents both separately.
Counter-Intuitive Things Beginners Miss
First, the anatomical extent of the code doesn't always match what the radiologist describes. You might see "MRI spine lumbar" in the note and think 72148 is correct. But if the protocol included the entire lumbar and sacral regions with sagittal and axial views, some payers expect you to document the full extent. The code descriptor says "lumbar spine" but doesn't specify the number of planes. That ambiguity is where audits start. Second, contrast timing affects which code you use. If the gadolinium was injected during the scan and the radiologist performed a post-contrast series, that's part of the same procedure. But if the contrast was given hours before and the scan was done without it, some payers consider it a different encounter. I learned this the hard way when a Medicare contractor denied a claim because the infusion started at 0800 and the scan began at 1400. The time gap mattered more than the code. Third, the body part doesn't always determine the code. You might perform an MRI of the knee and think 73721 is always correct. But if the protocol included fat suppression and T2-weighted sequences that are specifically designed for cartilage evaluation, some payers require you to document the exact sequences. The code says "knee" but doesn't specify the number of sequences. That's a common pitfall for new coders.
Get the Full Details

Where This Method Completely Fails
The biggest limitation is that CPT codes don't capture the clinical complexity of an MRI. You might perform a dedicated study that shows a subtle lesion, but the code is just a number. It doesn't reflect the number of sequences, the contrast timing, or the anatomical extent. That's why experienced coders always read the procedure note, not just the code descriptor. Another failure point is when the clinical indication doesn't match the code. You might order an MRI brain for headache and code 70553, but the payer considers it not medically necessary without prior authorization. Some plans require you to document the specific symptoms and the exact reason for the study. That's a bottleneck for practices that don't have a robust prior auth process. If you're doing a lot of MRI coding, I'd recommend using the official CPT manual and the AMA's guidelines, not online summaries. The manual is updated annually and the radiology section gets revisions that matter. I've seen practices lose thousands of dollars by using outdated code sets from third-party websites. The manual always wins in an appeal.
The work can be tedious, but it pays off. A study that takes 30 minutes to code correctly usually saves about 2 hours of follow-up work when claims get denied. The ratio is roughly 10 to 1 in my experience. That's worth the extra effort, especially when you're dealing with complex neuro imaging protocols.