
Building Music Therapy Lesson Plans That Actually Work
Most people approach music therapy lesson plans as if they're planning a concert rehearsal. They aren't. They're building flexible frameworks that can collapse and rebuild themselves in real time when a kid with autism decides the drum is too loud, or a stroke patient suddenly remembers a lyric from 1967 and starts crying. I learned this after burning through three months of rigid session templates that fell apart the moment anything unpredictable happened.The core mistake beginners make is over-planning. You need enough structure to know what you're doing, but not so much that you can't pivot when the session demands it. A good lesson plan in music therapy isn't a script. It's a menu with backup options. You can build your own from scratch, which is what I recommend once you understand the mechanics. There are also template libraries on sites like the American Music Therapy Association website and some university music therapy program pages that offer downloadable sample plans. I used to rely on those heavily, but here's the thing: generic templates don't account for your specific population, your room setup, or the instruments you actually own. A template saying "drum circle for group cohesion" assumes you have six congas and eight people who can sit still for twenty minutes. If you have two hand drums and three kids who bounce off the walls, that plan is useless. I keep a shared Google Doc with my own revised versions of whatever templates I find. Over the years it's become my primary resource, and I've restructured everything around actual patient responses rather than ideal scenarios.
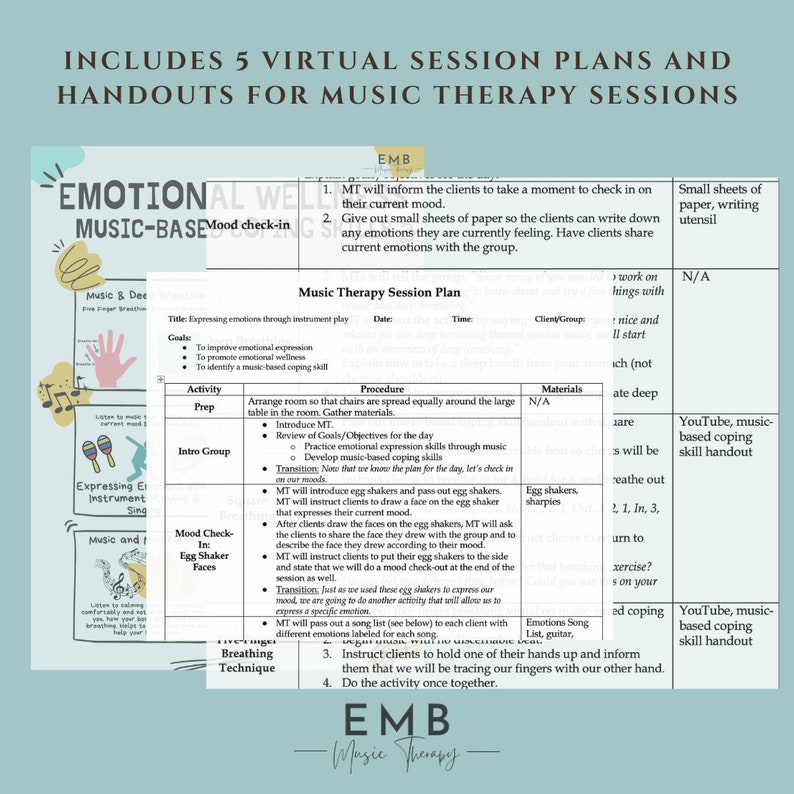
How to Structure a Music Therapy Lesson Plan
Every plan I write has the same skeleton, though the flesh changes every session. Here's the order I use: Greeting song with a purpose. This isn't just warm-up fluff. The opening track establishes the emotional baseline and gives you information before you even start the main activity. If someone sings along brightly, you have a different session than if they mumble the words and avoid eye contact. I note these observations in the plan before I start teaching anything. Goal-oriented activity with a musical mechanism. This is the meat. Every activity needs a clear therapeutic target and a specific musical element driving it. If you're working on fine motor skills, you might use rhythm sticks played at increasing tempos. If you're targeting emotional regulation in teens, you might use songwriting where they choose lyrics that match their mood. The musical choice matters because it determines engagement level and cognitive load.
Transition music between activities. This is something almost nobody plans for. Going from one exercise to another without musical scaffolding creates friction, especially with populations that struggle with transitions. I use short instrumental pieces or vocal exercises as buffers. Three to five minutes of deliberate transition music can prevent an entire session from derailing. Closing routine that provides closure. Ending on an unresolved note leaves patients, especially those with trauma histories, feeling unsettled. A consistent closing song or ritual gives the session a sense of completion. I've seen teachers skip this because they ran out of time, and it showed in the next session's behavior.
Get the Full Details
The Detail Most People Miss: Musical Parameters
Beginners write plans like "play guitar and sing." Experienced therapists specify tempo, key, dynamics, and instrumentation for every activity. These aren't aesthetic choices. They're clinical variables. A slower tempo (around 60-80 BPM) tends to lower heart rate and breathing, which matters when you're working with anxiety or PTSD. A major key generally feels more accessible for patients who are emotionally fragile. Dynamics that start soft and gradually increase can mirror and validate a patient's internal state before guiding them toward regulation. I once had a patient with treatment-resistant depression who didn't respond to any intervention until I switched from a bright C major guitar arrangement to a slower D minor piano version of the same song. Same lyrics. Completely different clinical outcome. This is why your lesson plan needs to specify the musical parameters, not just the activity. A plan that says "sing a goodbye song" is almost as useful as no plan at all.
My Most Common Workaround: The Two-Version Rule
Early in my career I'd write a detailed plan, walk into a room, and realize within three minutes that it wasn't going to work. Maybe the piano was out of tune. Maybe the group was too dysregulated for the structured activity I'd chosen. Maybe the heating system was making noise that drowned out the quieter parts of the piece. Now I write every plan in two versions. Version A is the ideal scenario. Version B is what I do if things go sideways. Version B always strips away the most dependent elements and keeps only what's absolutely necessary. I've saved entire sessions with this approach. The biggest waste of time in music therapy isn't bad planning, it's having a plan and no exit strategy when the plan fails. For example, my Version A for a group session might call for a four-part vocal harmony exercise using chordal instruments. Version B is a simple call-and-response drum pattern using body percussion because I can do it without any equipment and it still hits the same therapeutic targets: turn-taking, auditory discrimination, and group synchronization.
Pitfalls to Avoid
Overloading a single session with goals. One session should focus on one or two therapeutic objectives maximum. Trying to hit five goals in forty-five minutes means you're not doing any of them well. Music therapy sessions are narrow by design. Depth beats breadth every time. Ignoring the physical environment in your planning. Acoustics matter enormously and almost no one accounts for them. A tile-floored gymnasium with fluorescent lights will produce a completely different patient response than a carpeted office with warm lighting, even if the musical content is identical. Factor room conditions into your plan or your carefully chosen tempo and dynamics won't land the way you expect. Planning for the diagnosis instead of the person. I've seen lesson plans that say "for autism spectrum disorder" as if that describes a single person. Autism is not a monolith. A plan written for a nonverbal adult with Down syndrome will be completely wrong for a verbally fluent teenager with ASD. Know the individual. The plan serves them, not the other way around.

Skipping documentation. The lesson plan is useful, but the notes you take during and after the session are more valuable. What worked? What didn't? Which musical intervention produced the strongest response? Without recording this, you're rebuilding from scratch every session. I spend fifteen minutes after each session updating the plan with what actually happened. This compounds over time into a surprisingly accurate map of what works for each patient.
When Music Therapy Lesson Plans Don't Work
Honest assessment: there are situations where a structured lesson plan is the wrong tool. Acute psychiatric crises, patients in medical distress, or individuals who are actively resistant to any form of structured interaction don't benefit from a pre-planned session. In these cases, improvised music-making or even silent presence is more clinically appropriate. No plan can account for every scenario, and forcing a structured lesson into an environment that can't support it usually produces worse outcomes than having no plan at all. Supervision and consultation with a board-certified music therapist (MT-BC) are essential, especially when you're developing plans for complex populations. Templates and self-study get you started, but they won't replace the judgment that comes from supervised clinical hours and ongoing professional development. The best lesson plans I've ever written were the ones I threw away halfway through and replaced with something the session actually needed. The planning process itself is what builds the skill. The document is secondary.



