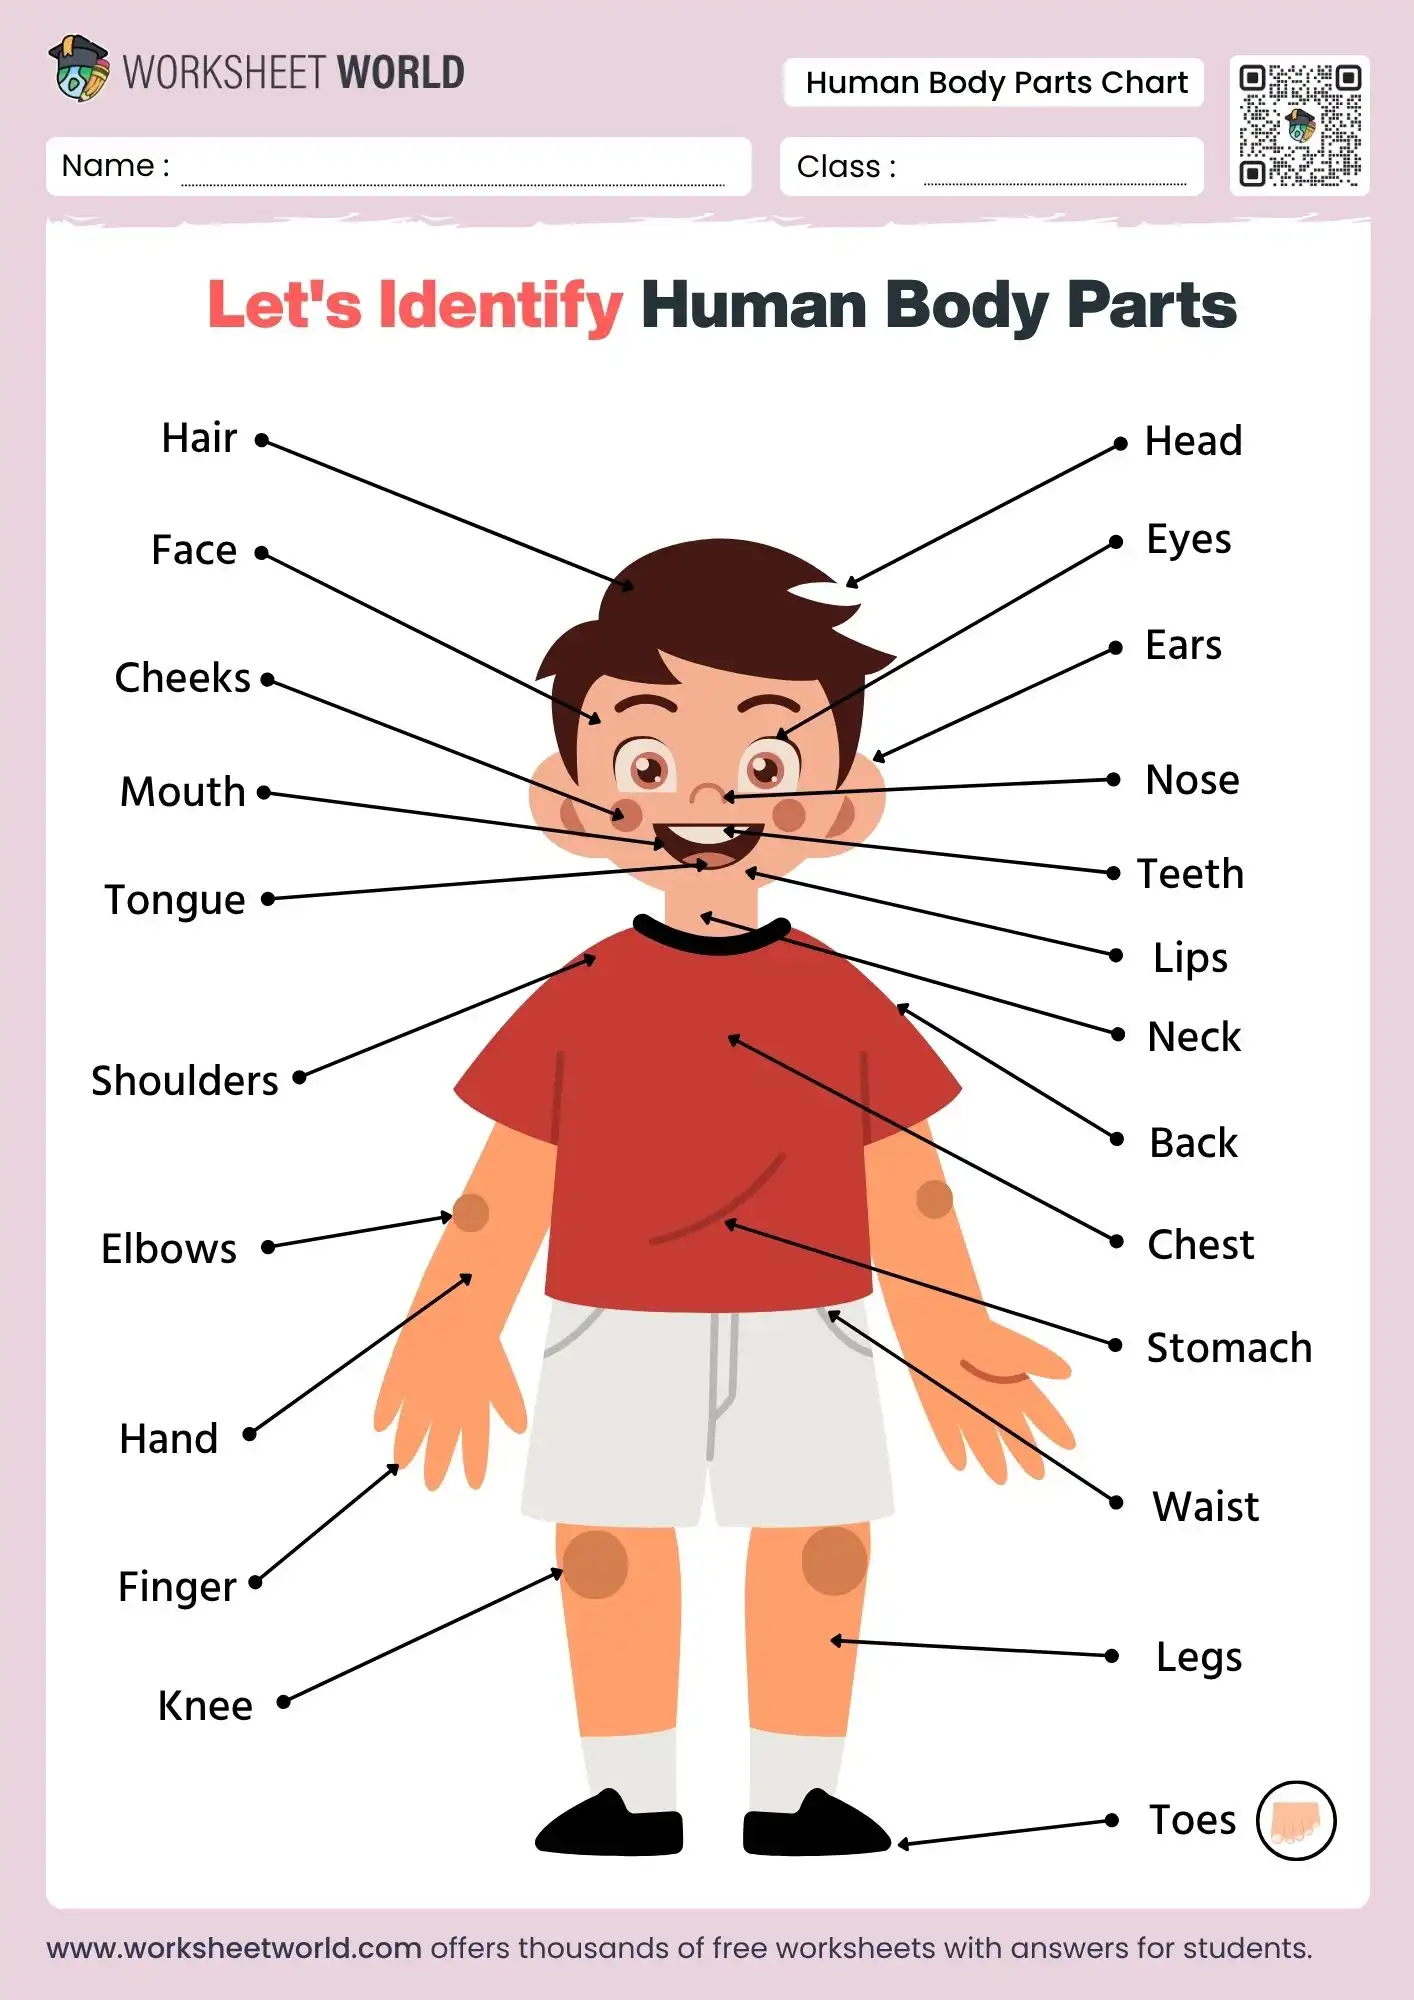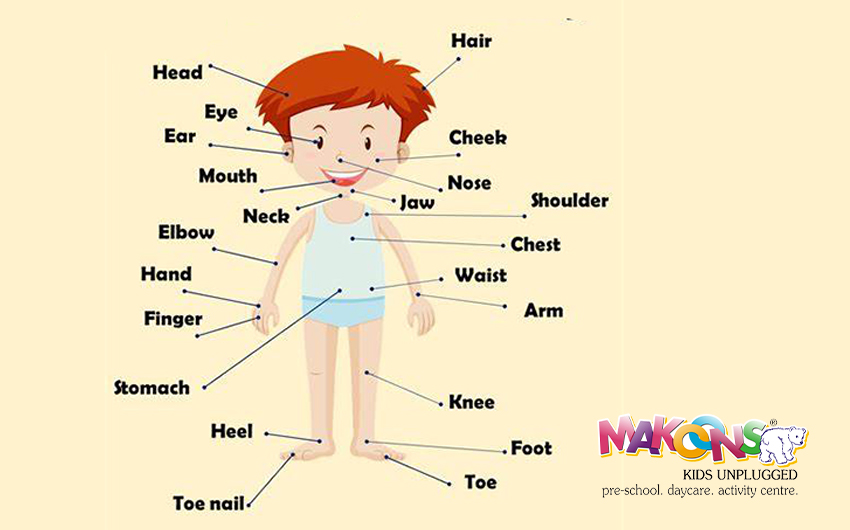
A Practical Way to Learn Human Anatomy Nomenclature
I spent years working on medical illustration projects where getting every single body part name exactly right was the difference between a usable diagram and one that gets returned to the drawing board. The problem is not finding lists online. Anyone can copy a Wikipedia table. The problem is building a working mental system so you can use these names under pressure without second-guessing yourself. Here is how I actually do it now, instead of the way I did it during my first anatomy course where I wasted weeks memorizing flashcards that fell apart the moment I needed to label a diagram from memory.
Starting With a System Rather Than a List
Most people try to memorize Names Of All The Body Parts by going alphabetical or by region in a flat list. That does not work well because the brain stores anatomical terms relationally, not alphabetically. When you know that the brachial region sits between the axillary and antecubital regions, you anchor three terms together instead of treating them as three separate facts. I start by drawing a blank outline of the human body from the anterior and posterior views. Then I layer the terms in from the largest regional groups down to the specific structures. This takes me about two weeks of focused work before I feel confident labeling from memory. The process is slow but the retention is dramatically better than anything I tried before switching to this method.
What Most People Miss About Terminology
One thing that catches people off guard is how much standard anatomical terminology has been refined over the last several decades. The older textbooks still in circulation use terms that the current official nomenclature, Terminologia Anatomica, has replaced or reclassified. If you are studying from a book published before 2010, you will run into terms like the popliteal fossa being called the hollow behind the knee in some outdated references, or the olecranon region being lumped into general back-of-arm descriptions that modern texts now treat separately. I learned this the hard way during a collaboration with a surgeon who was reviewing illustrations I had labeled using older conventions. She stopped at one diagram and pointed out that I had used terms that would confuse a resident taking their boards. It cost me about a week of rework. Since then I cross-reference everything against the latest Terminologia Anatomica listings before finalizing any label set. Another counter-intuitive detail is that many common names for body parts are technically descriptive phrases rather than single standardized terms. The crown of the head, for example, is not a formal anatomical term. The top of the skull is the vertex, and the very top point is the bregma when referring to the suture junction. Knowing the formal equivalent matters when precision is required, even if casual conversation rarely uses the clinical words.
Get the Full Details
The Labeling Workflow I Use
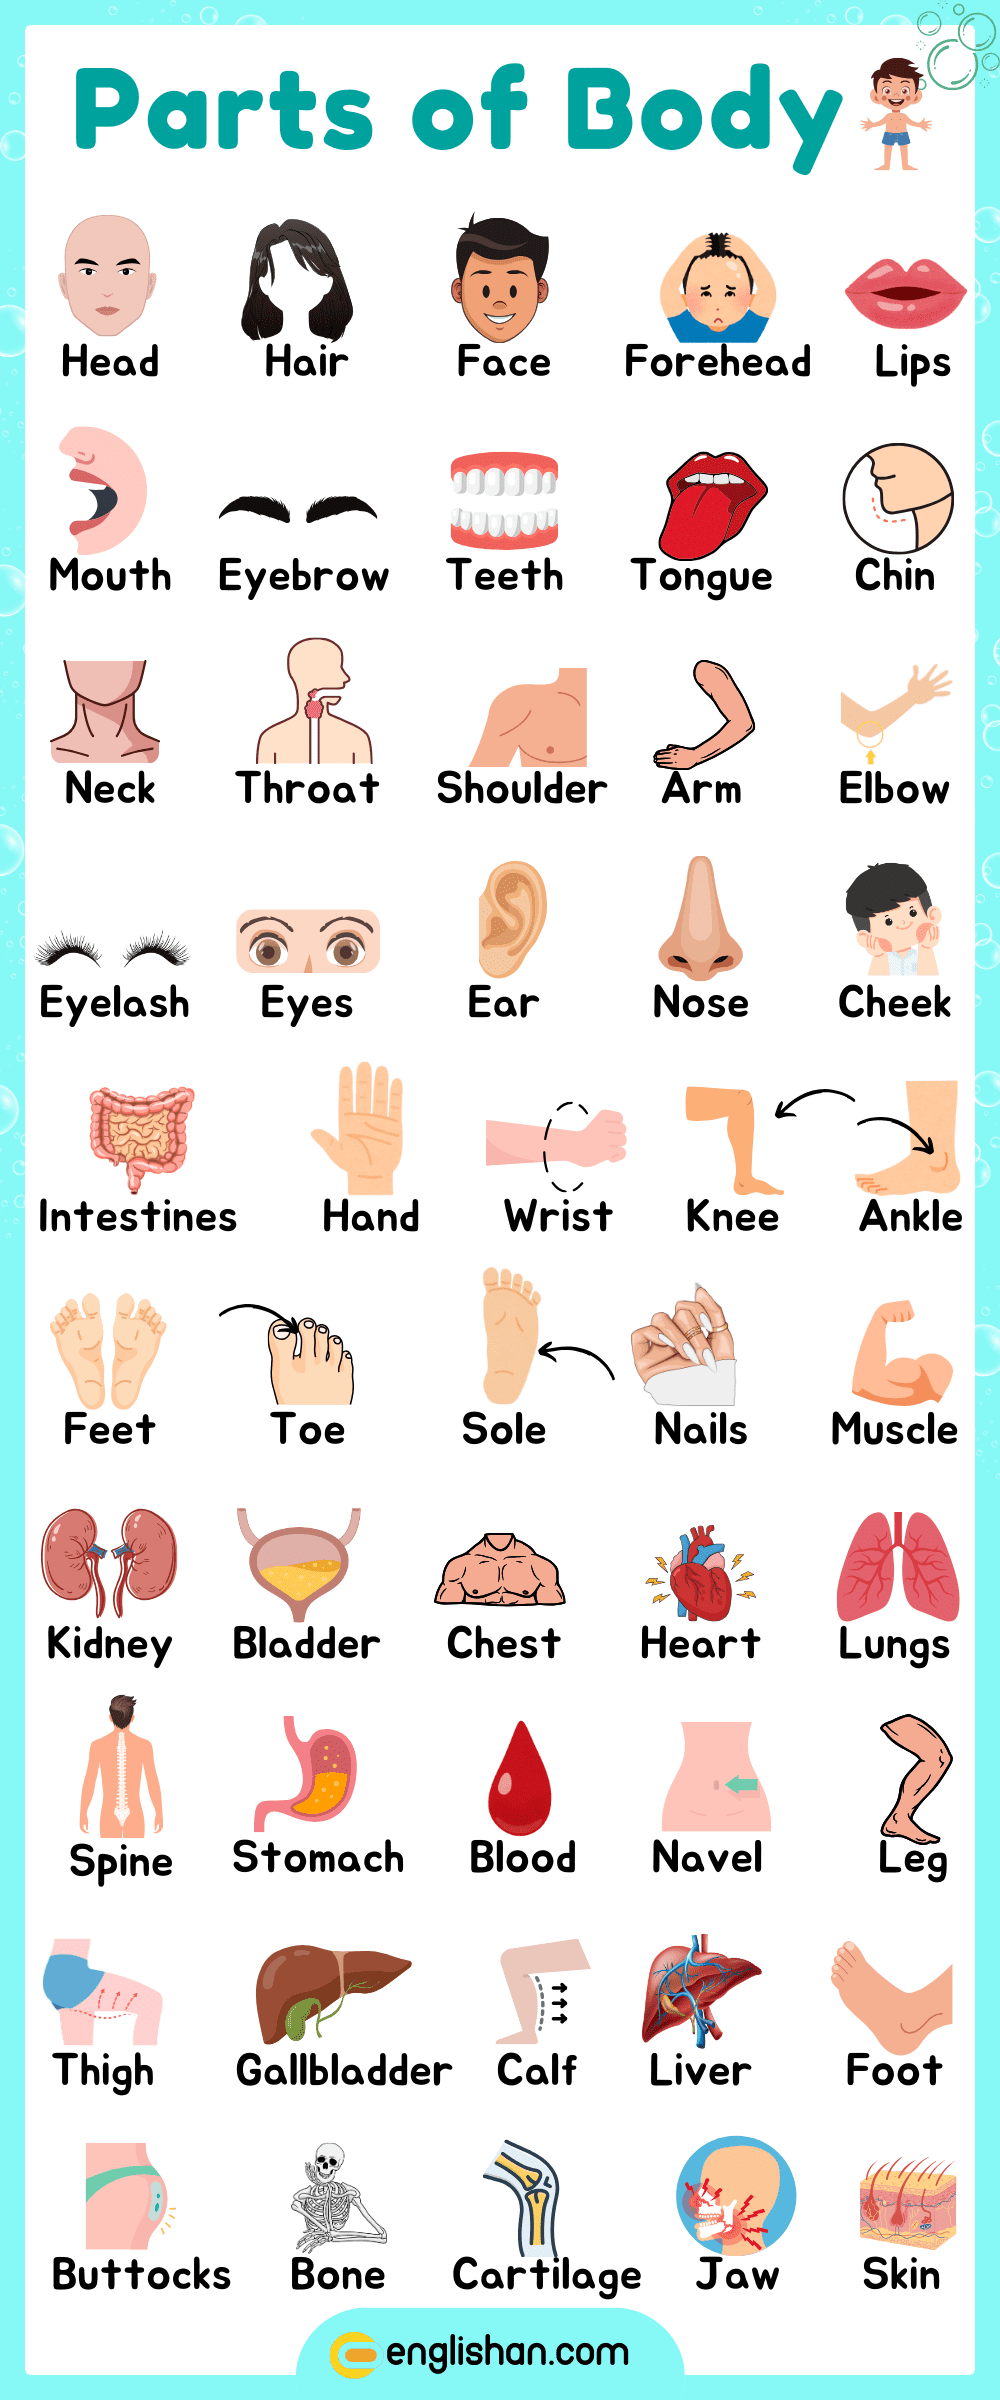
My current process for building a complete labeled reference works like this. I create a master spreadsheet with columns for the Latin term, the English equivalent, the region, the systemic category, and a note field for synonyms or older terms. I fill it out while working through an atlas, not while reading passively. Active labeling forces you to commit each term to a specific location in your mental map. The spreadsheet approach also makes it easy to spot gaps. After a few sessions you will notice certain systems are underrepresented in your list, usually the smaller structures like the intrinsic hand muscles or the deep fascial layers. Those are the ones you end up forgetting under time pressure, so catching the gap early matters. Once the spreadsheet is complete, I move to actual diagram labeling. I print clean line drawings and fill them in by hand without looking at my notes. The friction of recalling the term on the spot is what builds durable memory. Digital tools like Anki or similar spaced-repetition apps help too, but the physical act of writing the name next to the structure on paper creates a stronger spatial association for most people.
When This Approach Falls Apart
I should mention that this system has real limitations. It works well for gross anatomical terminology, which covers the major regions, bones, muscles, and surface landmarks. It does not handle microscopic anatomy, histology, or functional physiology equally well. If your goal is to learn everything from the macro level down to cellular structures, you will need a completely different framework that integrates histological slides and functional systems alongside the naming conventions. There is also the issue of linguistic variation. Clinical terminology differs between English-speaking regions, and medical professionals in different countries may use different standard terms for the same structure. The Terminologia Anatomica provides a universal baseline, but a radiologist in the UK and a surgeon in the US might reference the same area using slightly different conventional phrasing in everyday practice. I keep a secondary reference list for these variations because omitting them causes confusion in collaborative settings.
A Few Specific Structures That Trip People Up
The forearm contains several terms that are routinely confused. The anterior compartment of the forearm is flexor-heavy, while the posterior compartment extends the wrist and fingers. People often mix up the radius and ulna positions until they physically palpate their own arms. The radial styloid process sits on the lateral side of the wrist, and the ulnar styloid process is on the medial side. That directional relationship reverses when you are looking at a diagram versus your own arm, which is another common source of error. The shoulder girdle terms are similarly tricky. The clavicle and scapula form the pectoral girdle, but the shoulder joint itself is the glenohumeral joint. Calling it the shoulder joint casually is fine in conversation, but in any formal labeling context that distinction matters because the term shoulder region encompasses a broader area than the articulation alone. The foot and ankle distinction is another area where people make unnecessary mistakes. The tarsal region includes the ankle bones and the calcaneus, while the metatarsal region runs toward the toes. A label that says ankle when it should say tarsal will look amateurish in professional work, and reviewers will notice it immediately.
Keeping Your Reference Current
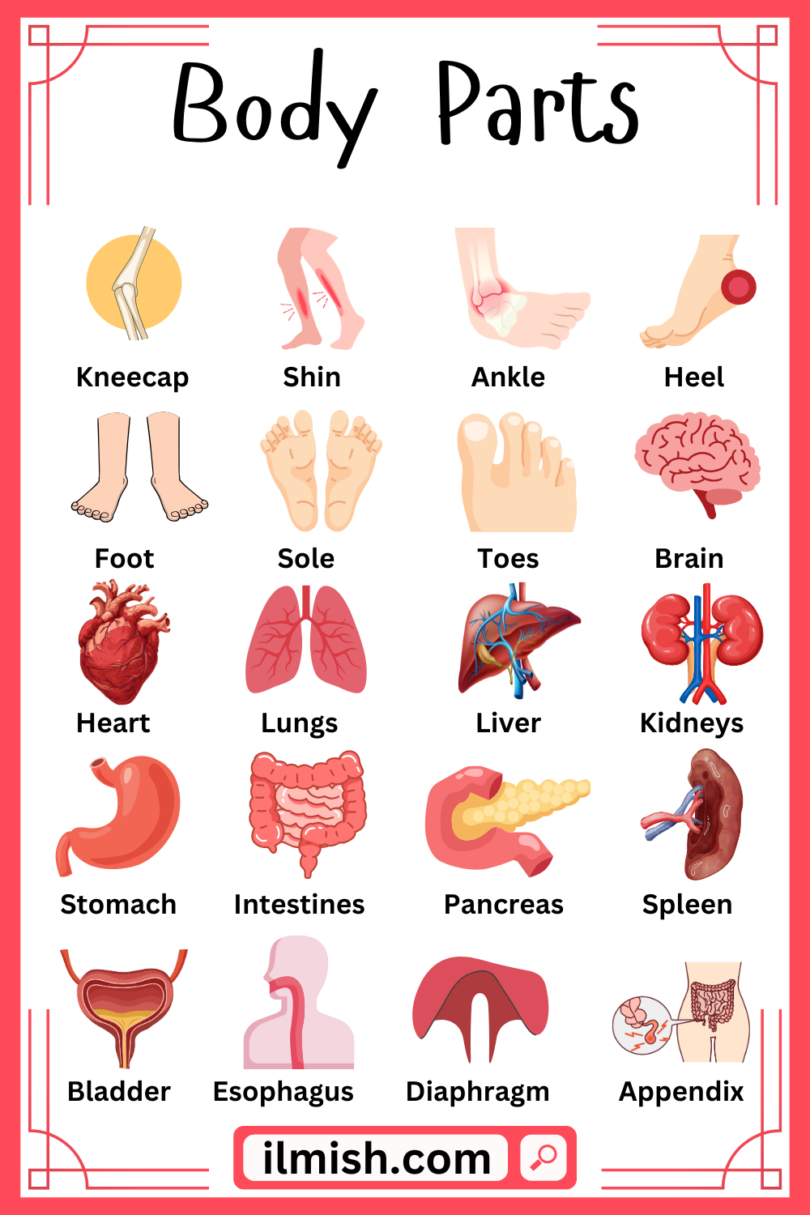
If you are building a comprehensive list of body part names for a project, I recommend downloading the Terminologia Anatomica from the Federative International Programme on Anatomical Terminologies website rather than relying on third-party summaries. The official source is updated periodically, and the free download includes the hierarchical structure that makes organizational sense. I use it as my primary verification step whenever I am unsure about a term's current standing. For quick lookups during labeling sessions, I keep a printed pocket atlas on my desk. The digital versions are convenient but the tactile reference speeds things up when I am working through a dense diagram with forty or fifty labels to place. It is a small thing but it cuts my labeling time significantly compared to switching between windows on a screen.
Practical Tips That Actually Help
Start each study session by reviewing the regions you already know before adding new terms. This reinforces the network structure in your memory rather than treating each term as an isolated fact. Even ten minutes of rapid review before moving into new material makes a measurable difference over a multi-week learning period. Do not skip the directional and positional terminology. Terms like proximal, distal, superficial, deep, medial, and lateral are the scaffolding that holds the entire naming system together. If you are weak on these, every anatomical label becomes harder to place correctly because you lack the coordinate system needed to anchor them. When you hit a block on a particular region, switch to a different system temporarily. Learning all the muscles of the leg at once can be overwhelming. Dropping into the cardiovascular system for an hour and returning to the lower limb later often results in faster retention because your brain processes the information differently on the second pass.
I also keep a separate log of terms I consistently mix up. This personal error log is more useful than any generic study guide because it tracks your specific blind spots rather than general difficulties. Over time the log shrinks as you correct those patterns, and it becomes a targeted review tool for when you need to verify your accuracy before a deadline.