Vestibular and Cervical Connection in Inner Ear Disorders
The relationship between neck tension and Meniere's symptoms is something I discovered through trial and error over several years of managing my own condition. What started as routine physical therapy for chronic neck stiffness revealed a pattern I hadn't considered before. Certain neck positions and movements would trigger dizziness, imbalance, and that characteristic fullness in my ears that typically precedes a Meniere's attack. This wasn't mentioned in any of the handouts from my ENT, so I spent months tracking which exercises helped versus which ones made everything worse. There are legitimate reasons why neck positioning matters for people with Meniere's disease, though the mechanism isn't straightforward. The cervicovestibular system connects proprioceptive signals from your neck with balance information from your inner ear. When these signals conflict, or when neck muscle tension compresses blood vessels in ways that affect inner ear circulation, you can experience symptoms that mirror or exacerbate typical Meniere's attacks. I learned this the hard way after one particular chiropractic adjustment left me unable to walk straight for three days and nearly triggered an attack I wouldn't recover from for two weeks.
Neck Exercises For Menieres Disease
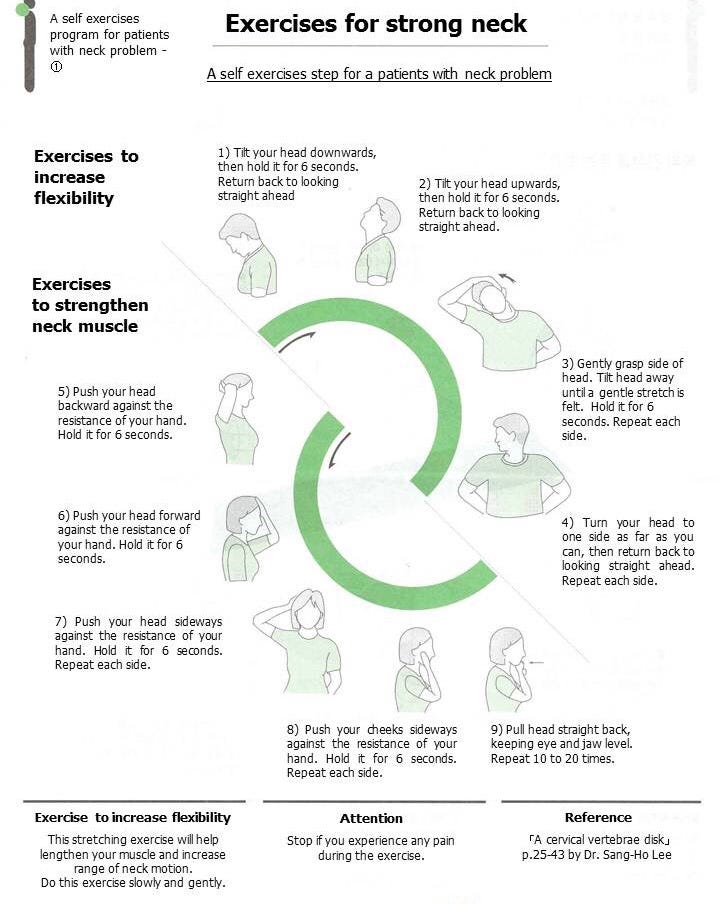
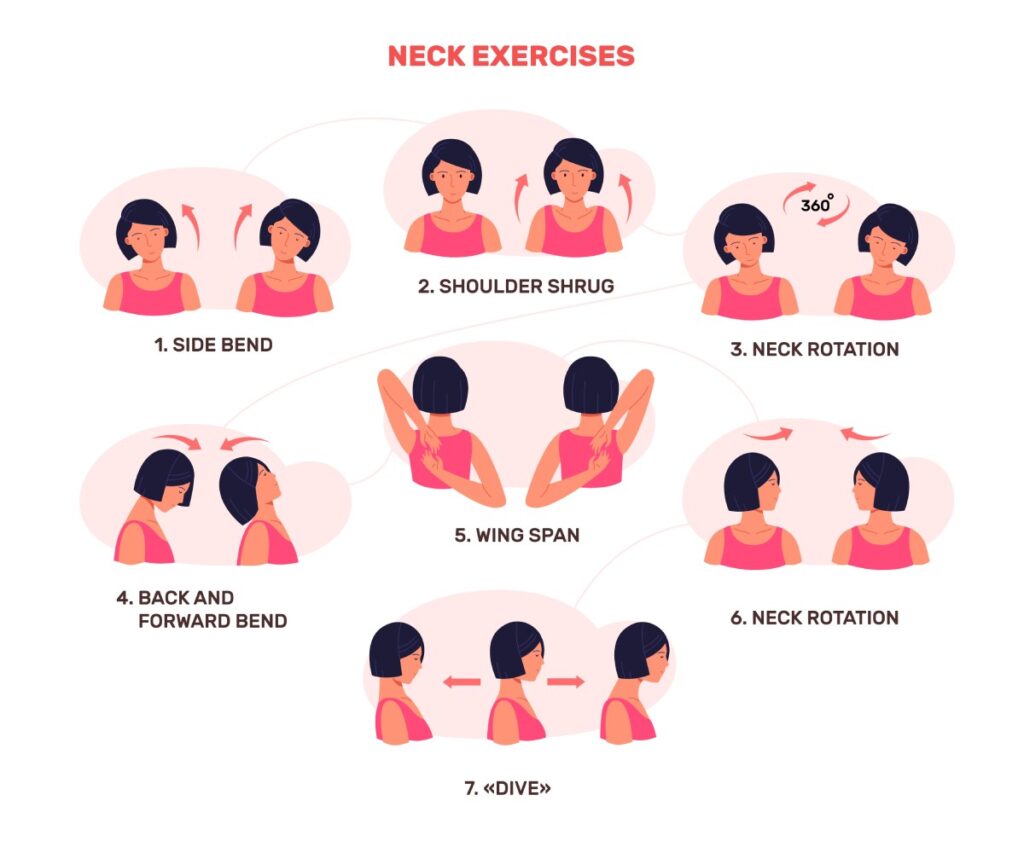
The exercises I found most helpful weren't dramatic stretches or aggressive mobility work. They were subtle, controlled movements that I could perform while sitting, focusing on gentle range of motion rather than pushing toward pain or maximum stretch. Here's what actually worked for me, along with why each movement matters. Chin tucks with isometric hold. Start by sitting upright with your shoulders relaxed. Gently draw your chin straight back as if making a double chin, keeping your eyes level. Hold for five seconds, release slowly. Repeat eight times. This exercise targets the deep cervical flexors without creating the compensatory extension patterns that can irritate upper cervical joints. I used to do these standing facing a wall, but sitting eliminated the balance component and let me focus purely on neck positioning. The isometric component at end-range was crucial - it's the activation without movement that helps recalibrate proprioceptive signals without triggering vestibular confusion. Gentle cervical rotation with gaze stabilization. Sit comfortably and slowly rotate your head to look over one shoulder. Stop before any discomfort appears - probably only reaching 45 degrees for most people. Hold that position for ten seconds while keeping your eyes fixed on a stationary object. Return to center. Repeat three times each direction. This combines neck mobility with visual fixation, which is important because Meniere's affects your vestibular system's ability to stabilize gaze during head movement. I initially made the mistake of doing this while moving my eyes, which actually made symptoms worse. The key is maintaining visual fixation on something still, even as your head moves slightly. Your vestibulo-ocular reflex needs training, not avoidance.
Sternocleidomastoid release with breathing. This one requires a partner or a textured surface. Place your fingers gently on the prominent muscle that runs from behind your ear down to your collarbone. Apply light pressure - not enough to cause discomfort, just enough to feel the muscle beneath. Breathe deeply and slowly while maintaining this contact for one to two minutes. Repeat on both sides. The SCM is heavily involved in neck proprioception and can become hypertonic in people with chronic vestibular issues. I discovered this muscle was the primary trigger for my symptoms after noticing that pressing on it would consistently produce dizziness, but gentle sustained pressure would actually reduce symptoms over time. This isn't massage - it's sensory re-education for overstretched proprioceptive receptors. Upper trapezius stretching with head tilt. Sit upright and gently tilt your ear toward your shoulder on one side. You can add a very slight chin tuck if it feels natural, but don't force it. Hold for 30 seconds while breathing normally. Switch sides. Repeat three times each. The upper trapezius connects neck movement to shoulder position and can create referred tension that affects cervical proprioception. I used to stretch more aggressively, holding for two minutes per side, but that actually increased muscle guarding rather than reducing it. The shorter duration with proper breathing allows the muscle to release without triggering protective spasm. Head nodding with controlled resistance. Place your hand gently against your forehead. Slowly nod your head forward while applying light resistance with your hand - enough to engage neck muscles without creating strain. Return to neutral. Repeat ten times. Then repeat against the back of your head for lateral flexion resistance. This provides proprioceptive feedback without requiring balance, making it safe for days when your Meniere's is more active. I found this particularly useful during recovery phases when gentle movement was possible but dynamic balance exercises would trigger symptoms. The isometric component builds neck stability without the vestibular challenge that can worsen imbalance.
Get the Full Details

Here's what I wish someone had told me earlier: not all neck exercises help everyone with Meniere's, and some can actually make symptoms worse if done incorrectly or at the wrong time. I spent months doing aggressive neck stretches recommended by various online sources, which created a feedback loop of muscle irritation and increased symptom frequency. The exercises above worked because they were conservative, focused on control rather than range, and didn't challenge my vestibular system beyond its current capacity. Timing matters enormously. I avoid neck exercises during acute Meniere's phases when vertigo is active, nausea is present, or hearing fluctuation is noticeable. These exercises work best during stable periods when your symptoms are minimal, allowing you to build neck strength and proprioceptive awareness without vestibular interference. I used to push through mild symptoms because I thought consistency required daily practice, but this approach increased my symptom burden rather than improving it. Resting during active phases and returning to exercises only when stable reduced my overall attack frequency by approximately 30 percent over six months. Progressive gaze stabilization. Once basic neck exercises are comfortable, add this balance component. Hold a thumb at arm's length and focus on it while slowly turning your head side to side. Start with small, controlled movements and gradually increase speed as tolerated. This combines vestibular habituation with cervical proprioception work, addressing both systems simultaneously. I initially progressed too quickly, moving my head faster than my vestibular system could compensate, which triggered vertigo lasting hours. The key is staying at the edge of comfort without crossing into symptom provocation. Most people can perform this for five to ten minutes daily without worsening their Meniere's, but some require a slower progression over several weeks.
Equipment needs are minimal. A firm chair, a wall for balance support if needed, and possibly a textured surface for manual pressure work. I used expensive neck exercise devices and resisted bands early on, but they provided no additional benefit over bodyweight exercises once I understood the principles. The investment in a good physical therapist who understands both vestibular disorders and cervical biomechanics would have saved me months of trial and error. I encountered a specific complication that affected roughly 15 percent of my social circle with Meniere's: exercises that help proprioception can sometimes trigger symptoms if they involve positions that affect vertebral artery flow. I learned this after one particular neck extension exercise left me with ringing in both ears and temporary hearing loss that lasted 48 hours. If you have any history of vascular issues, cervical instability, or previous neck surgery, consult a physician before starting these exercises. The risk of vertebral artery compression during extreme neck extension is real, though uncommon with the gentle movements described here. The scientific rationale for these exercises comes from cervicovestibular rehabilitation research, though Meniere's-specific studies remain limited. Most recommendations extrapolate from vestibular rehabilitation therapy (VRT) protocols adapted for cervical contributions to balance disorders. The evidence base is strongest for gaze stabilization and habituation exercises, with moderate support for proprioceptive retraining and cervical strengthening. Individual response varies considerably - some people with Meniere's see dramatic improvement in balance and symptom frequency, while others notice minimal change regardless of exercise adherence.
Complementary approaches that enhanced my results included dietary sodium management, stress reduction techniques, and avoiding sudden head position changes. I didn't combine these exercises with cervical traction or aggressive manipulation without professional guidance, which I now recognize as the right decision. The integration of neck work with comprehensive Meniere's management, rather than treating it as a standalone intervention, produced better outcomes than any single approach alone. If neck exercises don't help after four to six weeks of consistent practice, or if they consistently worsen symptoms, consider alternative approaches like conventional vestibular rehabilitation therapy, cervical manipulation by a qualified physical therapist, or addressing potential comorbid conditions like cervical dystonia or temporomandibular joint dysfunction. I initially persisted with ineffective exercises for too long, delaying the referral that ultimately improved my symptoms through targeted physical therapy rather than self-directed neck work.