Doing a Neuro Exam On Infant: What Actually Works
Most people overcomplicate the neonatal neurological exam. You don't need fancy equipment. You need steady hands, a quiet room, and the ability to watch a squirming four-kilogram human respond to basic stimuli. I have done thousands of these over the years, mostly in busy community clinics where the baby is already awake, hungry, and not cooperating at all. Here is how the exam actually works in practice. The environment matters more than you would think. A noisy ward with flashing lights and multiple conversations going on will make any infant overstimulated and difficult to assess. I learned this early when a colleague sent me a preterm baby at 36 weeks and the initial exam was completely non-diagnostic because the incubator heater was running and the baby was in a semi-aroused state the entire time. The workaround was simple: wait. Let the baby settle into a quiet sleep state for at least twenty minutes after feeding, then begin. You get a dramatically cleaner read on tone and reflexes that way. There are two main behavioral states you care about: active sleep and quiet sleep. Quiet sleep gives you the best baseline for reflex testing. Active sleep, with its rapid eye movements and occasional grimaces, will give you false positives on several primitive reflexes. I usually do the bulk of the exam during quiet sleep and reserve observation of spontaneous movement for active sleep.
The Core Components
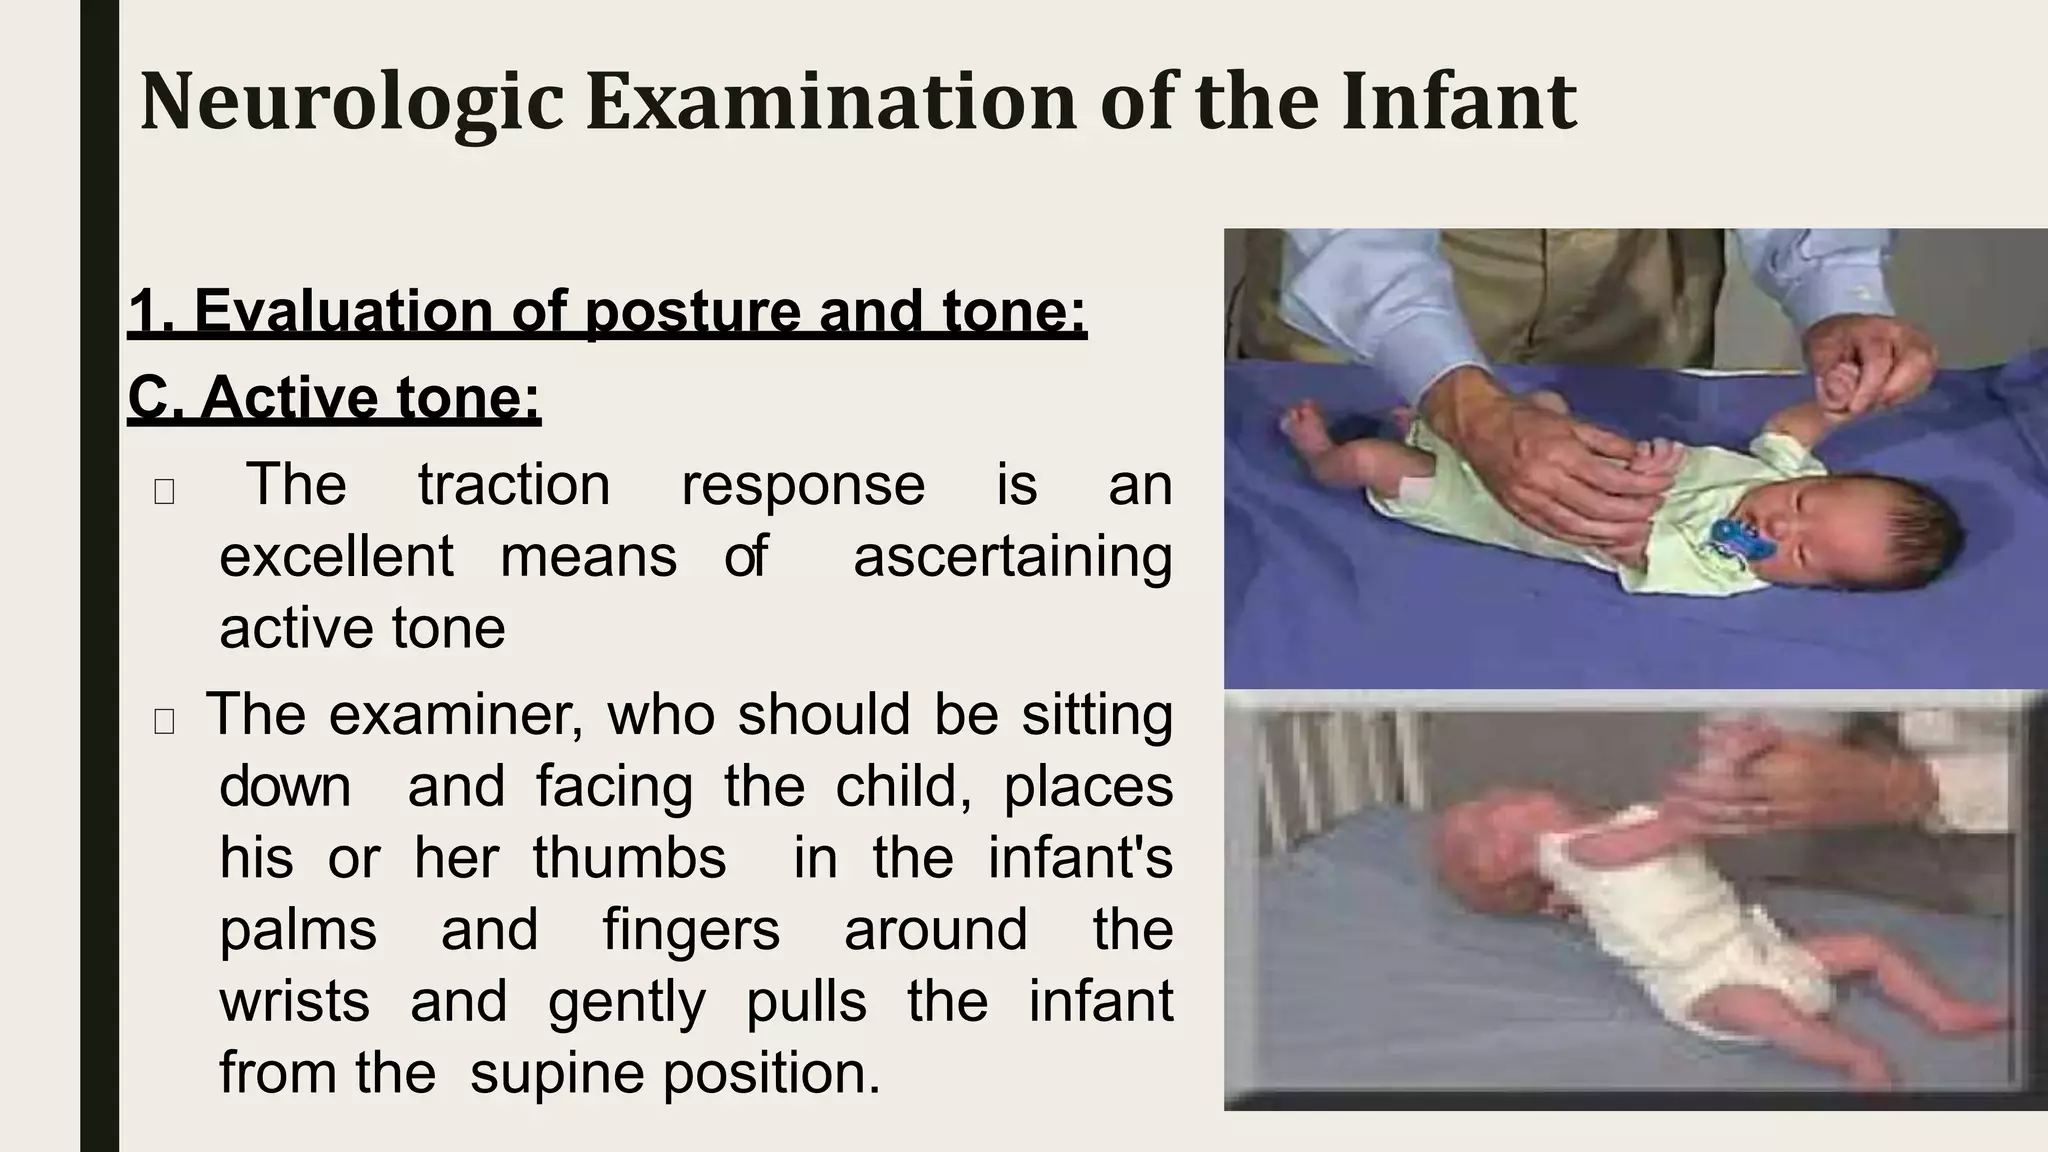
A proper infant neuro exam covers tone, posture, primitive reflexes, cranial nerve function, and joint mobility. That is the textbook version. In reality, you are mainly looking for asymmetry, abnormal tone, and the presence or absence of key reflexes at the right developmental stage. Tone is everything. You start with observation. A normal term infant should be flexed — arms bent, legs drawn up, wrists pronated. If you pick up a baby and they feel like a ragdoll with limbs hanging straight down, that is hypotonia and it needs further investigation. If they are stiff and resistant to gentle flexion, that is hypertonia. Either finding outside the first few days of life warrants concern. I check tone through several maneuvers. The ventral suspension test, where you hold the baby horizontally by the torso, should produce a relatively straight posture with some flexion at the hips and knees in a normal term newborn. The paper slide test is useful too — laying the baby supine on a smooth surface and gently pulling their arms toward you. Normal infants will resist somewhat and keep their arms flexed. Poor resistance suggests low tone.
The scarf sign gives you information about passive tone at the shoulders and elbows. Gently pulling the baby's arm across their chest should meet some resistance up to about ninety degrees in a normal term newborn. If the elbow goes all the way past the midline, that is decreased tone. If it barely moves at all, increased tone.
Get the Full Details

Primitive Reflexes
This is where most people lose their way. Primitive reflexes are not just checkbox items. They tell you about brainstem integrity and spinal cord function. The ones that matter most in the newborn period are the Moro reflex, the palmar grasp, the root reflex, the tonic neck reflex, and the plantar response. The Moro reflex is the most commonly tested and the most commonly misinterpreted. You support the baby's head and torso, lower them about fifteen centimeters quickly but smoothly, then let the head drop back slightly. The normal response is bilateral arm extension followed by abduction, then adduction forming an embrace. The legs may also extend and then flex. Some babies only show a partial response and that can be normal. What you are looking for is symmetry. If one side does not respond or responds differently, that is a red flag for brachial plexus injury or central neurological issues. I once missed a subdural hematoma in a baby because I was fixated on whether the Moro was present or absent. Both sides responded. The issue was subtle asymmetry in the arm extension — the left arm extended slightly less than the right. Going back and rechecking with the baby in a deeper quiet sleep state revealed the difference clearly. Absence of asymmetry in a reflex that looks symmetric at first glance can be the only early sign of an intracranial bleed. Documentation of that subtle finding changed the management entirely.
The palmar grasp reflex is straightforward. Stroke the palm of the infant's hand from the base of the fingers downward. The fingers should curl around your finger. It is usually strong in the first weeks and begins fading around three to four months. Absence at birth in a term infant should raise questions about peripheral nerve function or spinal level issues. The tonic neck reflex, or fencing posture, comes from gently rotating the baby's head to one side while supine. The arm on the face side extends and the opposite arm flexes. This is often present at birth but can be asymmetric. I do not overinterpret asymmetry here because positioning at birth and minor clavicular fractures can both affect it. The key is watching for a complete absence beyond four to six months, which points toward cerebral palsy or other upper motor neuron pathology. Root reflex testing involves stroking the corner of the mouth. The baby should turn their head toward the stimulus and open their mouth. This supports feeding assessment and indicates brainstem function.
The plantar response in infants is different from adults. Stroking the sole from heel to toe should produce dorsiflexion of the big toe and fanning of the other toes — the Babinski sign. This is normal in infants. The misconception that a positive Babinski is always pathological comes from adult neurology and does not apply here. It typically disappears around twelve to fifteen months. Recognizing this prevents a lot of unnecessary anxiety and imaging.

Cranial Nerve Assessment
You are not running full cranial nerve panels on infants the way you would on adults. The relevant ones are second, third through sixth, fifth and seventh, ninth and tenth, and twelfth. Pupil response to light checks the second and third nerves. Following a bright object assesses the third, fourth, and sixth. Facial symmetry and response to suck checks the fifth and seventh. Gag and swallow check the ninth and tenth. Tongue movement checks the twelfth. Pupils in newborns can be difficult to assess reliably. Some babies have irises that are still pigmented and appear uniformly dark. Others have congenital anomalies. I generally note pupil reactivity qualitatively rather than measuring exact millimeter responses. The response is usually brisk but smaller in absolute diameter compared to adults.
Fontanelle and Head Circumference
The anterior fontanelle should be soft and flat when the baby is upright and calm. A bulging fontanelle in that position suggests increased intracranial pressure. A sunken one suggests dehydration. Neither is specific to neurological disease but both are important contextual findings. Head circumference measurement and plotting on a growth chart is essential. Rapid crossing of percentile lines, whether up or down, is more concerning than a single absolute number. I track this serially rather than relying on one reading.
Joint Mobility and Skeletal Examination
Hip dysplasia and clubfoot are closely related to neurological conditions because abnormal tone contributes to developmental hip issues. The Ortolani and Barlow maneuvers should be performed. Limited hip abduction can indicate hip dysplasia or neuromuscular pathology. Ankle position and foot shape are also worth noting. The biggest mistake I see is testing reflexes on a crying baby. A distressed infant will have exaggerated startle responses that mimic pathological reflexes and genuine primitive reflexes may be suppressed or absent simply because the baby is too agitated. Always try to test during a calm state. Another common error is expecting reflexes that should have disappeared to still be present, or worrying about reflexes that should still be there that have faded. Reflex timing is developmental and varies. The Moro should be present at birth and typically integrates by four to six months. The grasp reflex appears at birth and fades around five to six months. The tonic neck reflex appears at birth and integrates by six to eight months. Understanding the timeline prevents false alarms.

Asymmetry is the finding that matters most. A reflex that is present but weaker on one side is more clinically significant than a reflex that is absent bilaterally in an otherwise normal-appearing baby. Global hyporeflexia is easier to explain as a technical issue or normal variation in some contexts. Focal asymmetry almost always demands further workup.
When the Exam Is Not Enough
A normal neuro exam does not rule out all neurological conditions. Some metabolic disorders, early neurodegenerative conditions, and mild cerebral palsy presentations will not show clear abnormalities on a standard infant exam. Conversely, an abnormal exam finding like mild hypotonia can resolve without any underlying pathology, especially in preterm infants. If you suspect a problem beyond what the bedside exam can clarify, neuroimaging and electroencephalography are the next steps. Ultrasound through the fontanelle is useful in infants who still have open fontanelles and can detect hemorrhage, major structural abnormalities, and ventriculomegaly. MRI provides more detail but often requires sedation in infants, which adds risk. EEG is indicated if seizures are suspected, including subtle seizures that may present only as eye deviation or autonomic changes without overt motor activity. The exam is a screening and monitoring tool, not a definitive diagnostic test for most conditions. It tells you whether to worry and whether to refer. It rarely gives you a specific diagnosis on its own.