Why Most Recovery Programs Miss the Point
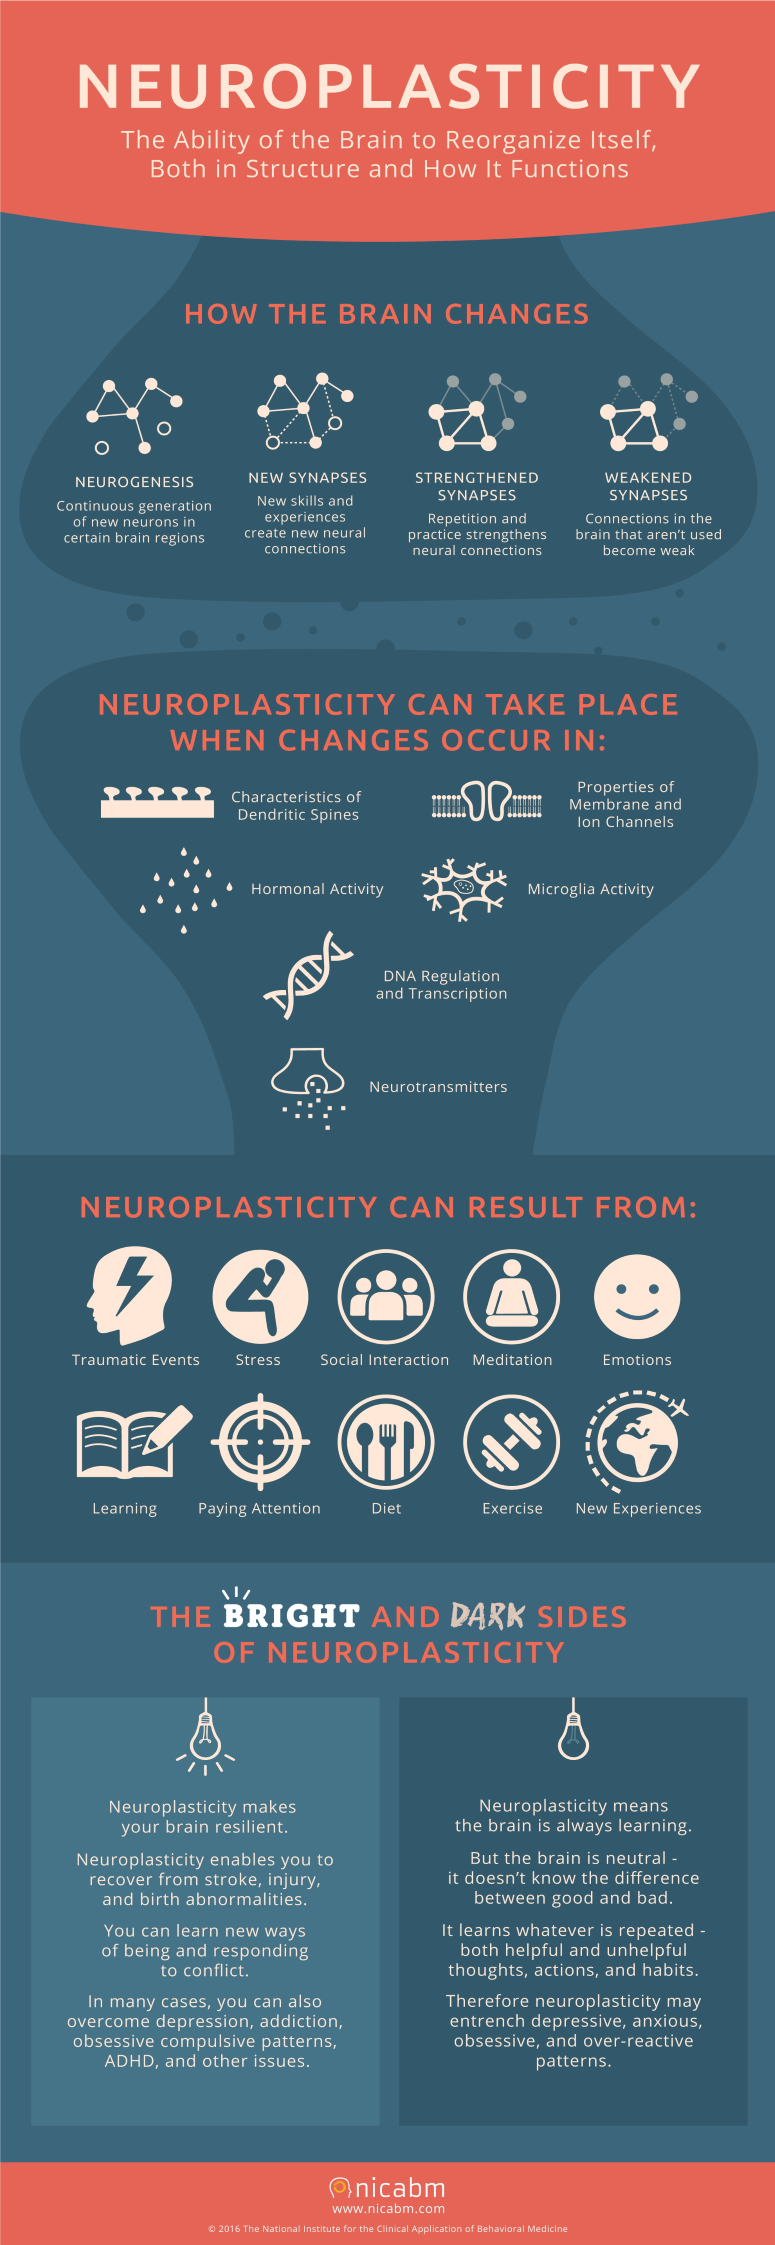
Neuroplasticity after a stroke isn't about doing more of the same movements. It's about forcing the brain to rebuild connections through intense, focused, repetitive effort that pushes just beyond your current ability. The scientific term is activity-dependent plasticity, and the mechanism is pretty straightforward: when you fire a neural pathway repeatedly under the right conditions, your brain reinforces those connections through myelination and synaptic pruning. Weak pathways get myelinated and strengthen. Unused ones atrophy. I spent years working with stroke rehab patients, and the pattern is always the same. The people who make real gains are the ones treating exercise like actual work, not like something they half-heartedly do while watching TV. The ones who complain it doesn't work are usually underestimating the intensity and duration required.
What Neuroplasticity Exercises After Stroke Actually Require
Here's what the research consistently shows and what I've seen play out in clinic: effective neuroplasticity-based rehabilitation requires high repetition (hundreds to thousands of trials per session), task-specific practice, intensity pushed to the edge of tolerance, and tight feedback loops. Not "maybe try this once a day." We're talking structured, deliberate practice that makes you sweat and frustrate yourself. The most common mistake I see is people doing five gentle range-of-motion circles with their affected arm and calling it therapy. That's not going to drive meaningful cortical reorganization. You need error. You need the brain to notice something went wrong and adjust. Without errors, there's no signal for plasticity to act on. This is why constraint-induced movement therapy, where you literally restrict the unaffected limb and force use of the affected side, produces dramatically better outcomes than conventional care for upper extremity stroke recovery. The constraint creates the error signal. Your brain has no choice but to reorganize. One edge case that always comes up: what happens when a patient has severe neglect on one side? I had a patient a few years back who'd had a right hemisphere stroke and completely ignored his left arm. Standard CIMT protocol was impossible because he wouldn't engage with the affected limb at all. The workaround was to start with visual scanning training combined with prism adaptation therapy before introducing any constraint. Prism glasses shift the visual field, which forces the neglected hemisphere to pay attention. After about three weeks of that groundwork, he became aware enough of his left side to eventually tolerate the constraint glove. Without that intermediate step, the whole protocol would have collapsed.
Breaking Down the Core Exercise Categories
Upper extremity work dominates the research, and for good reason. Arm and hand function is the biggest predictor of independent living after stroke. The two strongest evidence-based approaches are bilateral arm training and task-specific training. Bilateral arm training means using both arms together, symmetrical movements. It sounds too simple, but the symmetry drives activation across both hemispheres. Think mirror tray exercises where you move both hands together while watching a reflection. The visual feedback engages the affected hemisphere even when motor output from that side is minimal. I've seen patients with near-zero active movement in their affected hand start to show measurable improvement after eight to twelve weeks of consistent bilateral training, sometimes before they ever make voluntary movement on their own. Task-specific training is exactly what it sounds like: practicing real functional tasks. Not "make a fist," but "pick up this cup, bring it to your mouth, drink, set it down." Every subcomponent is trained in the context it will actually be used. The brain learns the sequence, the timing, the force modulation. General motor exercises don't transfer nearly as well to real-world function because the neural patterns are different.
Get the Full Details

Mirror therapy deserves its own mention. You place the affected arm behind a mirror so the patient only sees the reflection of their unaffected arm moving. The visual input tricks the brain into thinking the affected limb is moving normally. This activates the mirror neuron system and the premotor cortex, which bridges the gap between observation and execution. It's particularly useful in the subacute phase when voluntary movement is still emerging. A typical protocol runs twenty to thirty minutes daily, five days a week. The evidence supports moderate effect sizes for pain reduction and motor recovery, especially for the hand. Lower extremity and gait training follow similar principles. Constraint isn't an option for legs, but intensity and repetition still matter. Over-ground walking with body weight support, treadmill training with robotic assistance, and functional electrical stimulation during gait tasks all show solid outcomes when dosed properly. The sweet spot for gait speed improvement appears to be around forty-five to sixty minutes per session, four to five days per week, sustained for at least six weeks.
The Details Everyone Gets Wrong
Timing matters more than most people realize. The highest neuroplasticity window is in the first three to six months post-stroke, but that doesn't mean nothing happens after that. The brain remains plastic indefinitely. The rate of change just slows down considerably. I've worked with patients eighteen months out who still made meaningful gains, but they needed longer timeframes to see results and higher consistency in their practice. Dosing is another common failure point. The dose-response relationship in neurorehabilitation isn't linear. More isn't always better. There's a U-shaped curve where insufficient practice produces minimal gains, moderate-to-high intensity practice produces the best outcomes, and excessive practice without adequate rest can actually lead to learned non-use or even maladaptive plasticity. The brain can rewire in the wrong direction if you reinforce compensatory strategies too aggressively. This is why therapist guidance is important early on, even if patients eventually transition to home programs. Cognitive engagement is the hidden variable. Passive repetition without attention doesn't drive plasticity effectively. The patient needs to be mentally present, monitoring outcomes, adjusting strategy. This is why exercises that incorporate problem-solving elements—like reaching for objects of different sizes and textures while navigating around obstacles—produce better outcomes than sterile, repetitive robotic exercises. The enriched environment matters.
Virtual reality and gamified programs have entered the space with some promise. They can deliver high repetition in an engaging format and provide precise quantitative feedback. The caveat: the engagement has to be genuine, not superficial. A flashy game that doesn't translate to functional improvement is still just wasted time. The best programs I've seen couple VR delivery with clear functional goals and progressive difficulty adjustment based on performance metrics.

What Doesn't Work and When to Adjust
Let me be clear about the limitations. Neuroplasticity exercises won't reverse large core infarcts. If the primary motor cortex or corticospinal tract is extensively damaged, the capacity for recovery is fundamentally constrained by the amount of surviving tissue. These exercises optimize what's available; they don't regenerate lost structures. Setting realistic expectations early prevents both false hope and premature abandonment of efforts that could still yield meaningful improvement. Spectacular recovery is rare. Most patients plateau at some point, and the rate of decline in gains over time is steep. The early weeks show dramatic improvement, then it tapers. People who stop because they're not seeing week-over-week gains are usually quitting right before the slower, steadier improvements would accumulate into clinically significant results. For patients with severe aphasia or cognitive impairment, standard exercise protocols need substantial modification. Nonverbal communication strategies, visual cueing, and simplified task hierarchies become necessary. The plasticity mechanisms are the same, but the delivery method has to match the patient's actual capacity.
Consistency beats intensity in the long run. Doing thirty minutes of properly dosed exercise five days a week will produce better outcomes than six hours on Saturday and nothing the rest of the week. The brain needs repeated activation across days to consolidate changes. Sleep is where that consolidation happens, so recovery isn't happening during the exercise itself, it's happening afterward. Skipping days interrupts the consolidation cycle. If you're working with a therapist, ask them to specify the exact repetition count, rest intervals, and progression criteria for each exercise. Vague instructions like "do your exercises regularly" are useless. You should know exactly how many trials, what the target intensity feels like, and what benchmark triggers the next level of difficulty. If your therapist can't provide that specificity, consider finding someone who can or supplementing with a structured program that has clear parameters.