What Actually Changed in Implant Planning
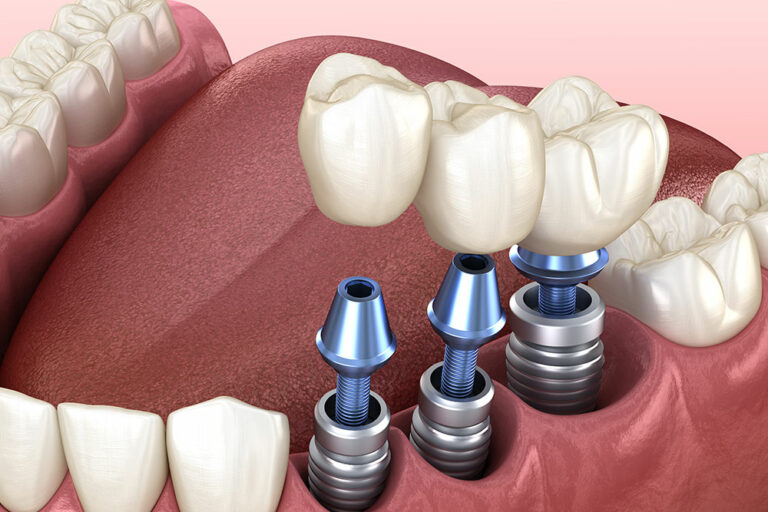
Most people think New Dental Implant Technology means a better drill or a prettier scan. It doesn't. The real shift is happening in how implants are planned, how guides are made, and how we decide whether to load them immediately. CBCT imaging combined with virtual surgical planning has been around for over a decade, but the software improvements in the last few years have pushed this into a much more routine workflow. You take a DICOM file, merge it with an STL from your intraoral scanner, plan the implant position in three dimensions, and then the guide gets milled or printed. That's the basic sequence. The part nobody warns you about is the data registration step. Matching the scan data to the CT scan isn't automatic just because both files exist. I've lost time on cases where the software's auto-registration looked fine visually but was actually off by a millimeter because the bone surface had resorbed in a way that confused the matching algorithm. I learned to check every case by looking at the anterior teeth region specifically. Those tend to be more stable, and if the registration falls apart there, it's going to be worse near the implant site.
New Dental Implant Technology in Everyday Practice
Here's how I approach it now. First, I get a high-resolution CBCT. I don't skimp on this because everything downstream depends on it. Then I take an intraoral scan with as little tissue retraction as possible. The scan doesn't need to be perfect on the soft tissue side since we're mostly dealing with bone anatomy. I merge the datasets using the cross-match feature in whatever planning software I'm using, and I verify the overlay by rotating through axial, coronal, and sagittal views. If I'm placing an implant in the anterior maxilla, I usually start with a guided approach. The bone here is thin, the aesthetics are unforgiving, and a freehand attempt in this region is where most early complications happen. For posterior mandibles, I sometimes still go freehand if the anatomy is straightforward and there's plenty of bone. Guided surgery adds about twenty minutes to the procedure and roughly eighty to a hundred and twenty dollars in costs for the guide fabrication, but it pays for itself in reduced guesswork. One thing that surprised me when I really started doing this consistently is that flapless guided placement doesn't always look like the picture on the box. The guide sits on the teeth or mucosa, and if there's any movement or if the patient bites down differently during the scan versus the surgery, the guide can shift. I've started putting a thin layer of surgical silicone on the guide intaglio surface before seating it. It cushions the guide against the tissue and reduces micro-movement during drilling. Small detail, but it made a noticeable difference in my cases.
The Software Side Nobody Talks About
Different planning platforms handle things differently. Some let you design custom abutments directly in the software before you even place the implant. Others require you to send the implant position to the lab and work from there. The workflow choice affects how much control you have over emergence profile and crown positioning. When I use a platform that supports full digital restorative planning, I work backward from the ideal crown position rather than forward from the available bone. That's the counter-intuitive part most clinicians miss. They see what bone they have and plan the implant into the most convenient position. But the prosthetically driven approach usually means the implant ends up slightly deeper and slightly more palatal than a bone-driven plan would suggest. The final restoration looks better and the biomechanics are more favorable because the screw access channel runs through the cingulum or central fossa instead of leaning toward the facial surface. The tradeoff is that you need good communication with the lab or you need to be comfortable with in-house milling. If you're sending cases out blindly, you might get exactly what the software says, or you might get something that doesn't quite fit the plan. I keep a running log of which labs are accurate and which ones need revisions. It's not glamorous but it saves a lot of headaches.
Get the Full Details
What Still Goes Wrong
I want to be clear about the limitations because the marketing around this stuff often pretends it's foolproof. It isn't. Here are the scenarios where New Dental Implant Technology either fails or creates new problems: Bone density issues remain the biggest challenge. A guided surgery works beautifully until you hit dentin-hard bone and the drill starts deflecting anyway. The guide holes have very little tolerance for error once they're made. I've had cases where the drill walked off the guide path because the bone was Class IV and the osteotomy closed up faster than expected. In those situations, reverting to a partially flapped approach and finishing the guide hole freehand is usually the move. Then there's the issue of soft tissue thickness variation. The planning software assumes a uniform soft tissue layer, but it's rarely uniform. If the mucosa is three millimeters thick in one spot and six in another, the guide sits higher than intended in the thicker area, and your implant ends up shallower. I account for this by adding a compensation layer in the software whenever the mucosal thickness varies more than two millimeters across the surgical site.
Immediate loading is another area where the technology gets overstated. You can definitely place and load an implant in a single visit when the primary stability is above forty newton centimeters and the bone quality is Type II or III. But when you're working in Type IV bone in the posterior maxilla and the stability reading is thirty-two, pushing for immediate loading is gambling. The technology doesn't change the biology here. The implant needs time to integrate regardless of how fancy the planning was.
A Real Problem I Ran Into
Last year I had a case where the CBCT and intraoral scan wouldn't register reliably because the patient had a full denture opposing the implant site. The denture material created scatter artifacts in the CT that messed up the registration. The software kept producing a false match in the edentulous ridge area. I solved it by scanning the denture itself separately and using that as an intermediary reference object. I matched the teeth in the denture to the teeth in the scan, then transferred that coordinate system to the bone level. It added about fifteen minutes to the workflow but it was the only way to get a reliable merge. I remember another case where the opposite happened. The CT was clean but the intraoral scan had air bubbles in the silicone impression, and those bubbles translated into gaps in the STL that threw off the merging entirely. In both cases the fix was to repeat the problematic scan, but knowing which modality was lying to me saved an hour of trying to force a bad registration. If you're thinking about adopting this workflow, here's what I'd suggest based on experience rather than brochures. Start with simple cases in the anterior mandible. The bone is dense but the site is straightforward, and you'll build confidence in the software before you encounter complex anatomy. Don't jump straight into posterior maxillary All-on-4 cases as your first project. The margin for error is small and the consequences of a mistake are expensive.
Invest in a good intraoral scanner before investing in planning software. The scanner is your most frequent tool and it breaks down more often than the software ever will. I've had software updates that broke features I was relying on. I've never had a scanner break in that way, but I have had one that misread dark teeth repeatedly until the calibration was adjusted. Keep a physical surgical kit ready alongside the digital one. There will be nights when the guide doesn't fit perfectly, when the drill breaks, or when the patient can't tolerate the guide for the planned duration. I've pulled guides and converted to freehand surgery about three percent of the time. It's a small number but it's a real number and you need to be prepared for it without panicking. The cost of entering this workflow is real. A decent CBCT setup runs between forty and eighty thousand depending on whether you buy used or new. An intraoral scanner is anywhere from twenty to sixty thousand. The planning software is typically a subscription around four to eight hundred a month. Guide fabrication runs about eighty to two hundred per case. Factor all of that in before you tell patients you're offering digital implant surgery as a premium service. It's a serious investment and the return depends on your case volume.
For people who can't make that investment right now, cone beam imaging alone is already a significant upgrade over panoramic radiographs for implant planning. You don't need the full digital workflow to make better decisions. Start with what you can access and expand from there.