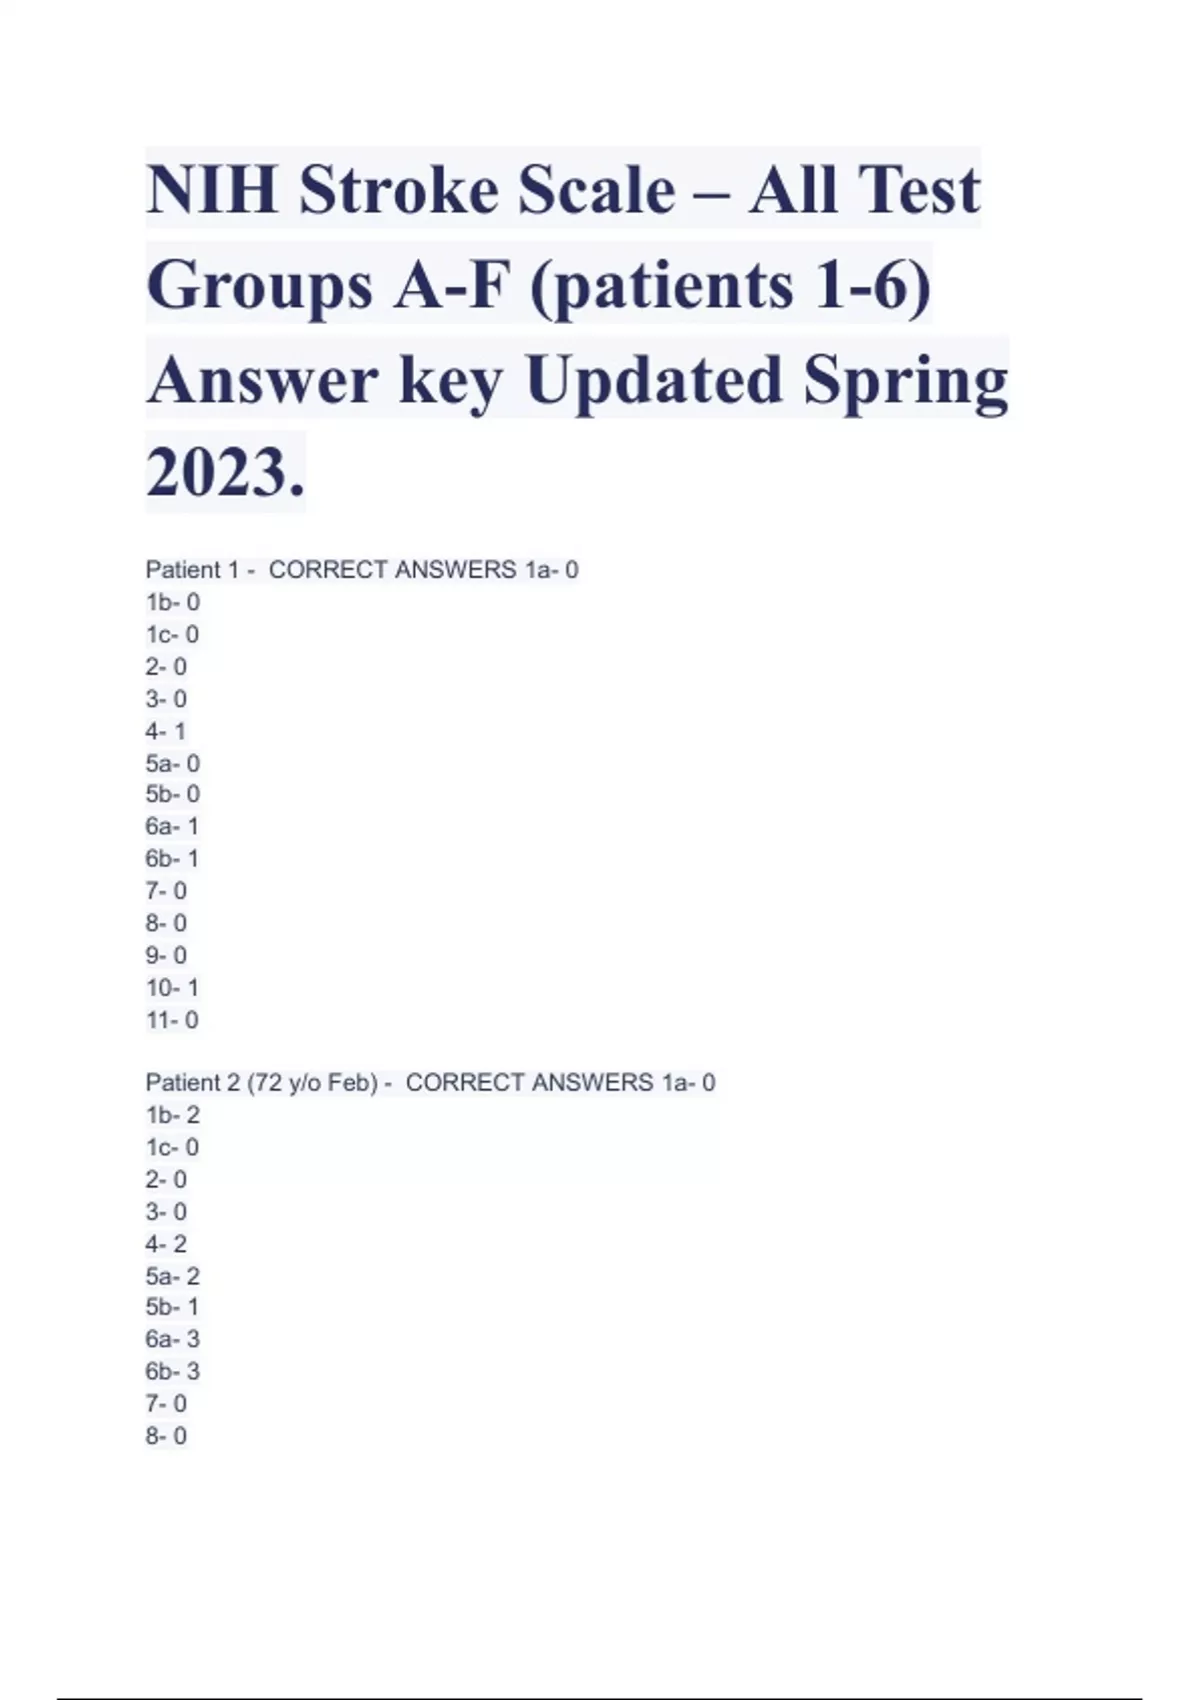
Understanding NIHSS Certification and What Group A Covers
The NIHSS, or National Institutes of Health Stroke Scale, is a 15-item assessment tool used by healthcare professionals to measure the severity of a stroke. It was originally developed through the NINDS tPA Stroke Trial and has since become the standard scale for acute stroke evaluation worldwide. The test isn't particularly hard to learn, but the scoring can be finicky if you haven't done it enough times. I ran a training session at a hospital in Ohio last year where half the nurses scored the language item wrong on their first attempt. They were reading instead of assessing actual comprehension. Group A typically refers to the first section of practice materials or certification exam banks that cover the foundational items: Level of Consciousness, Best Gaze, Visual fields, Facial Palsy, Arm Drift, and Leg Drift. These are the items most people get wrong because they look simple but have specific scoring rules built in. The certification itself is administered by various continuing education providers. There is no single universal body that issues NIHSS certification, which catches people off guard. Here is how I break down the Group A items when I walk someone through it:
Level of Consciousness questions one through three. Question one asks where the patient is. Question two tracks responses to commands. Question three assesses verbal response. Each item is scored zero through two. A score of zero means the patient responds appropriately. A score of two means they are unresponsive or require constant stimulation. The trick is that Question one and Question two are linked. If the patient cannot answer Question one due to a language barrier or intubation, you mark them as unable to test and move to the next item with notation. You do not skip the item entirely and pretend it was scored. Best Gaze is item number four. This is where I see the most casual errors. The rule is straightforward: any involuntary deviation or failure to pursue counts as abnormal. A score of zero requires full pursuit in both directions. A score of one is a partial gaze palsy. A score of two is a complete gaze palsy. I had a resident once score a comatose patient as zero on gaze because their eyes were midline. They were wrong. Comatose patients get a one or a two depending on brainstem function. The eyes being midline does not automatically mean normal gaze. Visual Fields is item five. You test by confrontation unless the patient cannot cooperate, in which case you note it. A score of zero is no visual loss. A score of one is partial hemianopia. A score of two is complete hemianopia. The key thing most people miss is that a patient with a dense hemianopia can still score a zero on gaze if their eye movements are intact. These two items are separate assessments. Do not conflate them.
Facial Palsy is item six. Ask the patient to show teeth or close eyes. Symmetry matters. A score of zero is normal. A score of one is a minor paralysis. A score of two is complete unilateral or bilateral paralysis. Bilateral facial weakness is rare but it happens in Guillain-Barre or certain brainstem strokes. If you see bilateral involvement, score it as a two. Do not second guess yourself because you think facial palsy should always be one-sided. Arm Drift and Leg Drift are items seven and eight. Both use the same scoring structure: zero through four. Zero means no drift. One means drift but the limb does not hit the bed within ten seconds. Two means the limb hits the bed before ten seconds. Three means no effort against gravity at all. Four means no movement detectable. The ten-second window is not a suggestion. It is the actual rule. I timed my first certification practice and accidentally held one arm at eight seconds and scored it wrong because I stopped early. The protocol requires the full ten seconds unless the limb falls sooner. When I help people prepare for the Group A section, I tell them to do at least twenty practice assessments on real or simulated patients before taking the test. Reading the scale is not the same as performing it. The difference shows up clearly on the certification exam. One of my colleagues failed her first attempt because she kept scoring a patient with expressive aphasia as zero on the language item. The item measures comprehension, not speech production. That is item number thirteen, which falls outside Group A, but the confusion carries over. People conflate the items.
Get the Full Details

Downloadable practice materials exist from several providers. The AHA and ASA both offer free NIHSS training modules that include practice scores. Third-party vendors sell compiled answer groups like Group A bundles. I would recommend starting with the free ones from the major stroke organizations before buying anything. The content is essentially the same and the official sources keep their materials updated when the scale gets revised. A few things that will trip you up on the actual exam: Sensory items are not in Group A but they show up later. If you only study the first six items, you will miss the full picture. The sensation item uses a pinprick test and scoring is zero for normal, one for decreased, and two for absent. A patient with hemisensory loss scores a one. You do not need them to be completely numb to give them a non-zero score.
Dysarthria is another item that people mess up. It is scored based on how clearly the patient pronounces words, not on whether they can understand them. A patient who is fluent but slurred gets a one or two. A patient who is mute due to intubation gets marked as unable to test. These are different scores. The distinction matters for the exam. Ataxia is the least tested item and the easiest to forget. It is scored only when the patient can follow commands. If they cannot, you do not score ataxia and you move on. A score of zero is absent ataxia. A score of one is present in one or more limbs. There is no score of two for ataxia on the current version of the scale. Some older study guides list a two, but that is outdated. Make sure your materials reference the 2013 or later revision. If you are going into this certification, do not rush through the items. The test rewards careful observation more than speed. Most people finish well under the time limit because the assessment itself takes longer than the exam portion. I usually see test-takers spending about twelve minutes on the written exam and another eight to fifteen minutes on the practical demonstration. The total time is rarely a problem. The problem is accuracy under fatigue. The items are straightforward when you are fresh. They become ambiguous when you are tired and guessing.
One last thing. The NIHSS total score range is zero through forty-two. A score of zero means no stroke symptoms. A score above twenty usually indicates a severe stroke. Scores between five and fifteen suggest moderate stroke. The exact cutoffs vary slightly by source. What matters for certification is knowing how to arrive at the right number for each item, not memorizing the ranges. The exam tests your scoring ability, not your knowledge of prognostic thresholds.