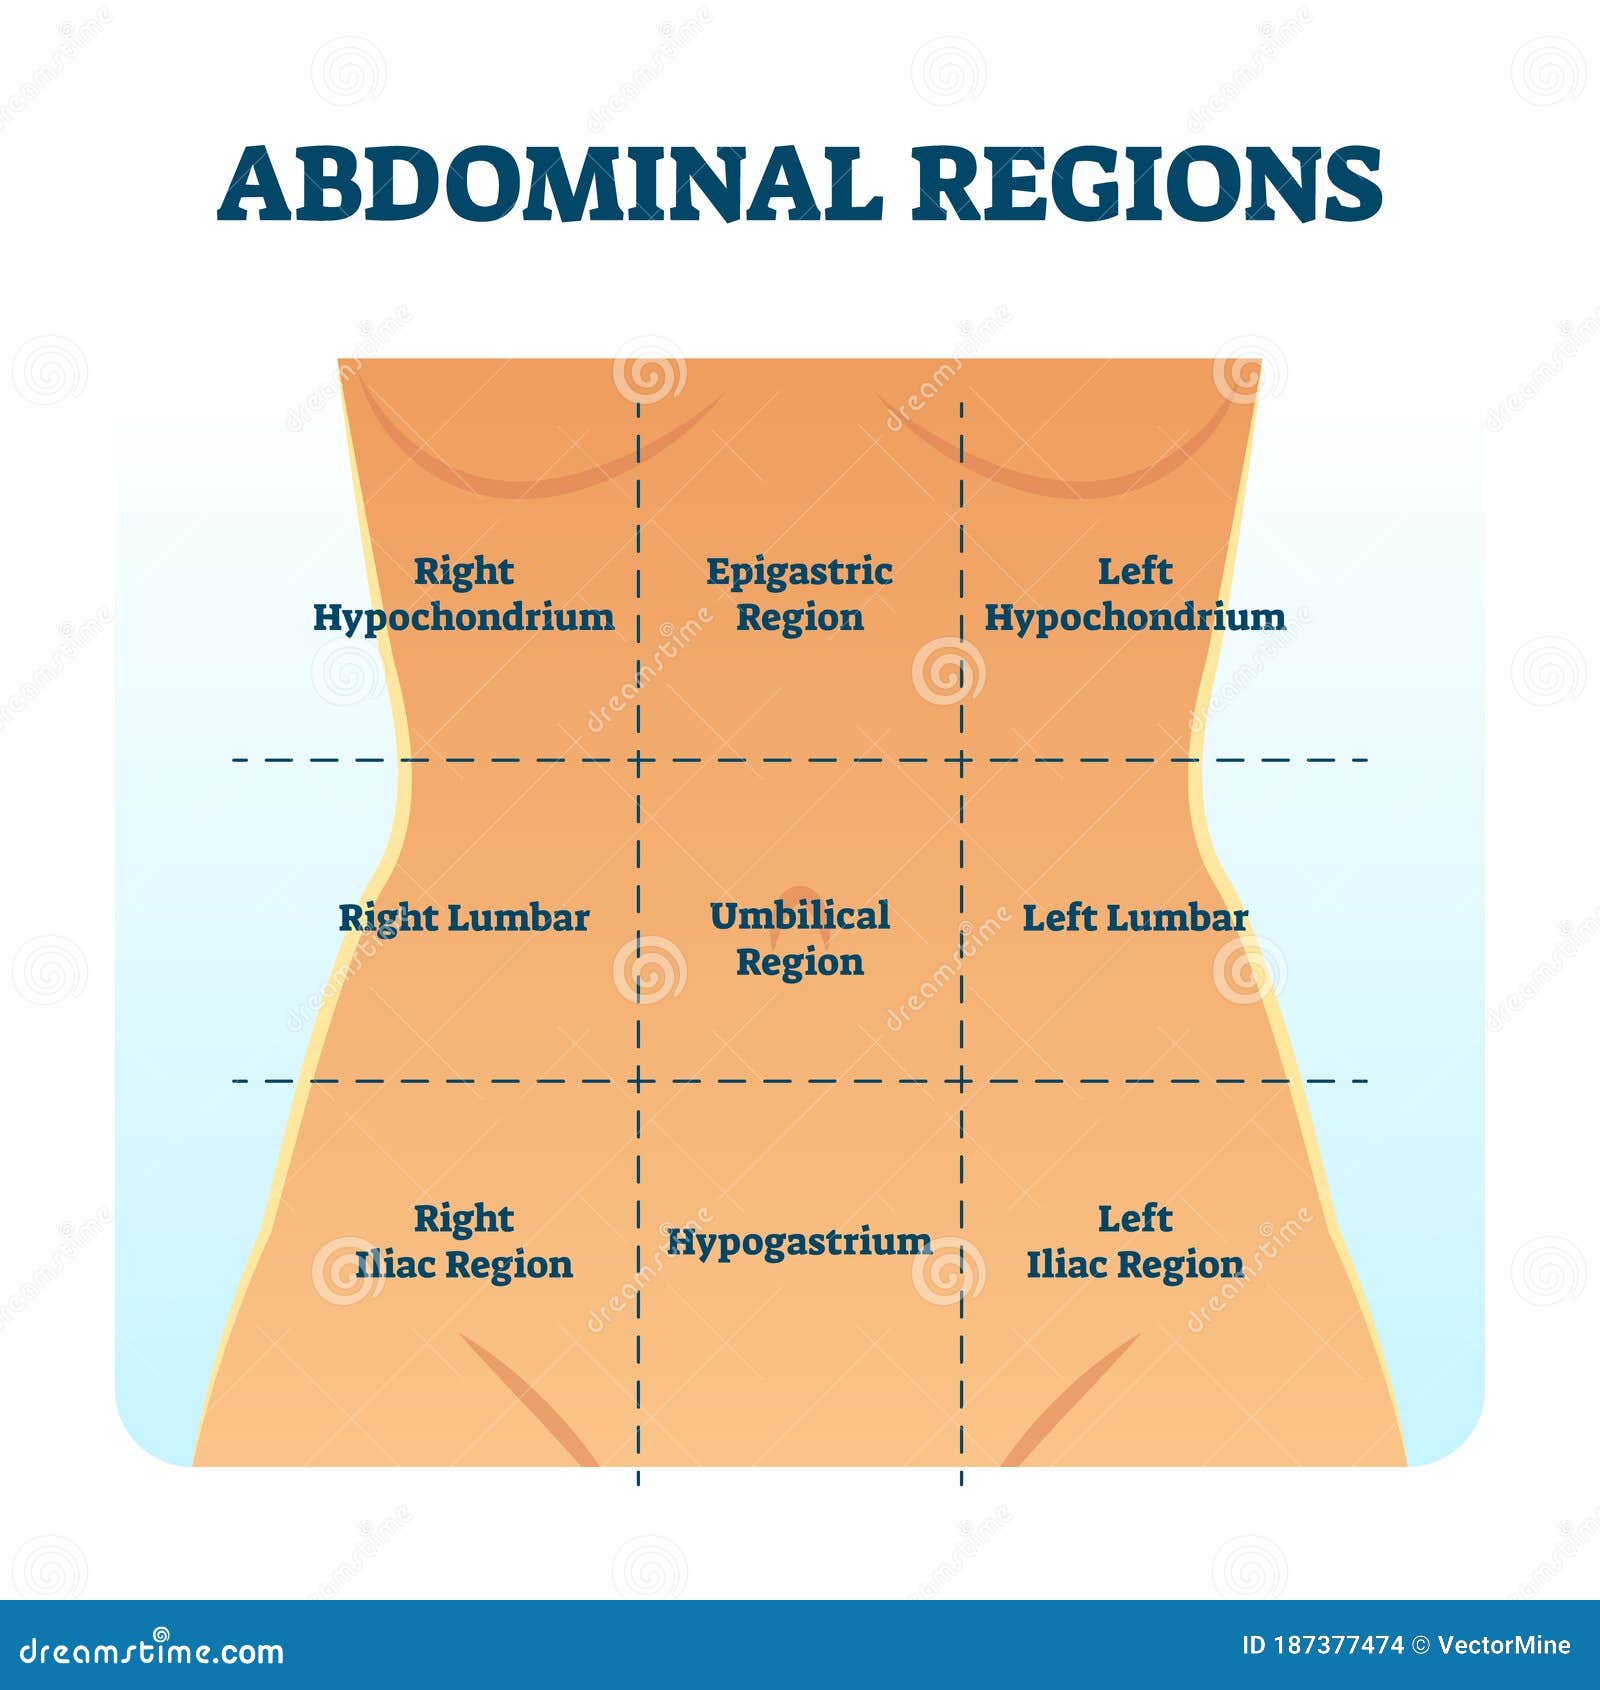
Learning the Nine Regions Of The Abdomen
I remember my first anatomy lab where I had to label a diagram blindfolded — well, not literally blindfolded, but the professor wanted us to draw the regions from memory before touching a textbook. That exercise stuck because it exposed a gap I didn't know I had. I could point to a stomach on a page, but when it came time to name the region above the navel, I blanked. The Nine Regions Of The Abdomen is one of those foundational systems that seems obvious once you see it laid out, but gets messy under pressure in a clinical setting. Before getting into how this actually works, here's the anatomy. The abdomen is divided by two vertical and two horizontal planes. The vertical lines are the midclavicular lines — drawn from the midpoint of each clavicle straight down. The horizontal planes are the subcostal plane (just below the rib cage, at the level of L3) and the transtubercular plane (at the level of the iliac tubercles). Where these four lines intersect, you get nine regions: right hypochondriac, epigastric, left hypochondriac, right lumbar, umbilical, left lumbar, right iliac, hypogastric (or suprapubic), and left iliac. Each region maps to specific organs. The right hypochondriac region sits under the right rib cage and contains the liver, gallbladder, and part of the colon. The epigastric region — the one I kept confusing with the others early on — houses the stomach, pancreas, and part of the duodenum. The umbilical region wraps around the navel and contains the small intestine, transverse colon, and the aorta bifurcation starting around L3. The right and left lumbar regions are the flanks, each containing parts of the ascending and descending colon respectively, along with the kidneys posteriorly. The right and left iliac regions sit in the lower quadrants near the hip bones — the right one contains the appendix and the cecum, the left one holds the sigmoid colon. The hypogastric region in the center lower abdomen contains the bladder, uterus (in females), and rectum.
Here's where it gets practically useful. When a patient comes in with localized pain, you don't just ask "where does it hurt?" You map it. Right upper quadrant pain that radiates to the back — classic gallbladder. Right lower quadrant pain with migration from the umbilicus — that's the textbook appendicitis story. But textbooks are boring. In practice, I've seen appendicitis present with pain in the epigastric region first, then migrate days later. Or a kidney stone that refers pain to the lumbar region but the actual stone is down near the ureterovesical junction. The regions are a starting point, not a diagnosis. One thing I wish someone had told me sooner: these regions are somewhat arbitrary. The lines you draw change slightly depending on whether the patient is standing, lying down, or has a distended abdomen. A thin person at L3 will have a very different subcostal plane from someone with significant abdominal fat or ascites. I worked with a patient once who had a large ovarian cyst that pushed the umbilical region landmarks entirely out of alignment. Palpation became guesswork because the visual guideposts were gone. That's when I learned to rely more on deep palpation and percussion than on the drawn lines alone. Another counter-intuitive point that beginners miss: the regions don't map cleanly to quadrants. The four-quadrant system (RUQ, LUQ, RLQ, LLQ) is simpler and more commonly used in emergency medicine. The nine-region system is more precise but also more cumbersome. In trauma situations, I default to quadrants because speed matters. For detailed GI workups, the nine regions give you better localization. Neither system is wrong — they serve different purposes.
The biggest pitfall I see in students is treating the regions as hard boundaries. They aren't. Organs span multiple regions. The liver occupies most of the right hypochondriac region but extends into the epigastric. The transverse colon runs across the entire mid-abdomen through the umbilical region. When you hear "pain in the umbilical region," don't assume small intestine — it could be anything from the stomach to the colon to the aorta. The region tells you where to look, not what you'll find. If you're studying this for an exam, draw the grid on a piece of paper yourself. Label each region with its Latin name and at least two organs. Then cover it up and redraw it from memory. That's the exercise that finally made it stick for me. You can memorize the names all day, but if you can't draw the lines without looking at a reference, you don't know the system yet.
Get the Full Details

Practical Application and Limitations
In clinical practice, the nine regions are most valuable for gastrointestinal and genitourinary localization. But they have real limitations. The retroperitoneal organs — kidneys, pancreas, aorta — don't respect these surface lines well. A pancreatic tumor might cause epigastric pain but the pathology sits far posterior. A renal colic might refer to the lumbar region but the actual stone has moved into the ureter. The nervous system's referral patterns don't follow anatomical boundaries. For conditions like peritonitis, the regions break down entirely because the inflammation spreads diffusely. A perforated ulcer doesn't stay in the epigastric region — it tracks along the paracolic gutters and can cause pain in every region simultaneously. At that point, the nine-region system becomes a historical curiosity rather than a practical tool. You need imaging, labs, and clinical judgment instead. I've also found that the system works better for adults than for children. A child's abdomen is proportionally different — the liver is relatively larger, the intestines occupy more space, and the landmarks are harder to identify. My pediatric rotations taught me that in kids, you rely more on general descriptors and less on precise regional mapping.
The mnemonic most people use is "Right Hypochondriac, Epigastric, Left Hypochondriac" for the top row, "Right Lumbar, Umbilical, Left Lumbar" for the middle, and "Right Iliac, Hypogastric, Left Iliac" for the bottom. Say it three times and you won't forget it. But memorization without spatial understanding is fragile. Draw the grid. Feel your own anatomy. Press on each region and note what structures lie beneath. That's how it becomes usable rather than decorative. For download or reference materials, most anatomy textbooks include detailed diagrams. Netter's Atlas of Human Anatomy has the clearest illustrations I've found. Online, the Visible Body and Kenhub resources offer interactive 3D models that let you rotate the grid and see underlying organs in context. Those tools fill the gap that flat diagrams leave — understanding the three-dimensional relationships between regions and the structures beneath them.


