Understanding the Practical Reality of Non Rebreather Mask Flow Rate
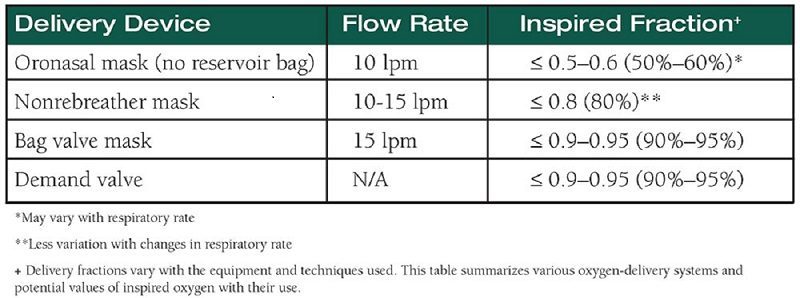
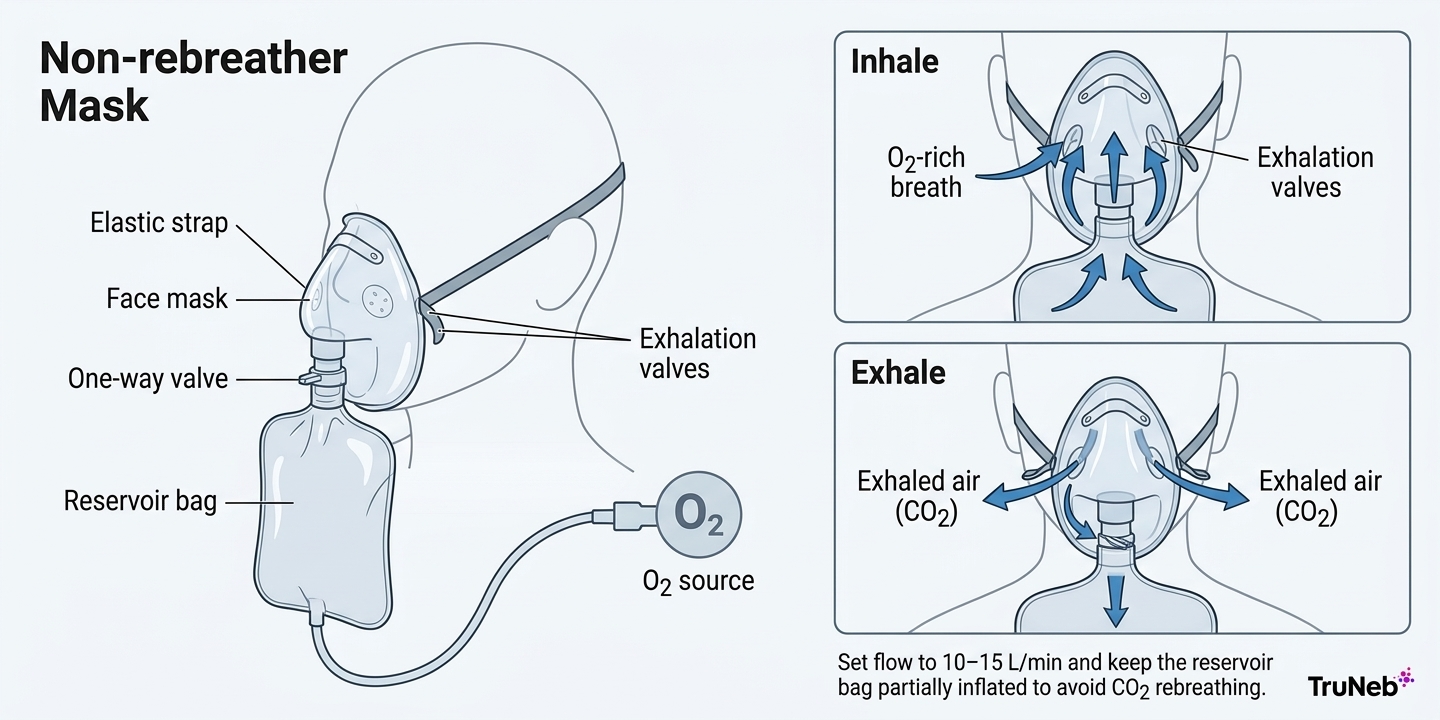
The non rebreather mask is one of the most misunderstood pieces of equipment in acute care. Most people think cranking the flow to maximum gets maximum oxygen. That is not how it works, and it matters when a patient is sitting there struggling for air. You set the flow between 10 and 15 liters per minute. Below 10, the reservoir bag collapses during inhalation and the patient starts rebreathing their own exhaled air. The one-way valves are there to prevent that, but they only work if there is oxygen flowing through them. At 10 to 15 L/min, you are looking at an estimated FiO2 of roughly 60 to 90 percent, depending on how the patient is breathing. That range matters because two patients at the same flow rate can end up with very different oxygenation if one is breathing fast and shallow and the other is slow and deep.
Setting Non Rebreather Mask Flow Rate Correctly
Start by connecting the mask to the oxygen source and turning the flow up before you place it on the patient. Check that the reservoir bag inflates. If it does not, your flow is too low or there is a leak somewhere in the tubing. Place the mask on the patient and adjust the nose clip so it seals against the face without being so tight that it becomes uncomfortable. The side ports should remain open. Those are vent holes and closing them creates a rebreathing circuit that can raise carbon dioxide levels. Here is where I have seen people make mistakes. I had a patient on the ward a few years ago who was tachypneic, breathing around 28 times per minute. We had the mask set at 15 L/min, which should have been enough. The reservoir bag was deflating between breaths anyway. I checked the setup and everything looked fine on paper. The problem was the patient's inspiratory flow demand. During each breath, this person was pulling oxygen faster than 15 L/min could deliver it. The bag emptied, and they were pulling room air in through the vent holes. The fix was not turning the flow dial any higher, because the wall outlet maxes out at 15 L/min anyway. I switched to a high-flow nasal cannula setup. That delivered the higher flow rates this patient actually needed without the bag deflation problem. It would have taken me longer to figure out if I had not run into this before.
There are a couple of things that do not get mentioned in the training modules. First, the estimated FiO2 ranges I gave you assume a normal breathing pattern. If someone is breathing at 40 breaths per minute with a small tidal volume, the actual oxygen concentration reaching their alveoli drops significantly. The math changes because you are introducing more dead space ventilation with each rapid, shallow breath. Second, the material of the mask and the fit quality matter more than most people realize. A loose mask at 15 L/min can deliver substantially less oxygen than a well-sealed one at the same flow rate. You also need to watch for CO2 retention in patients who are chronic retainer, like those with severe COPD. A non rebreather mask is not the right tool for that population. It does not control the oxygen concentration precisely enough, and you risk suppressing their respiratory drive. In those cases, a Venturi mask gives you the controlled delivery they actually need. Some practical limits to keep in mind. You cannot push a non rebreather mask beyond 15 L/min from a standard wall outlet. Any claims about "higher flow" usually just mean there is more gas washing through the system, not that the patient is receiving more oxygen. The bag will not stay perfectly inflated at all times even at 15 L/min if the patient has high inspiratory demands. Monitor the bag, not just the flow meter. And if you are using a non rebreather on a patient who is becoming somnolent or retaining carbon dioxide, recognize that the device has reached its limit and escalate to something more appropriate rather than just increasing flow further.
Get the Full Details