Understanding How Nonkeratinized Stratified Squamous Epithelium Actually Works Under the Microscope
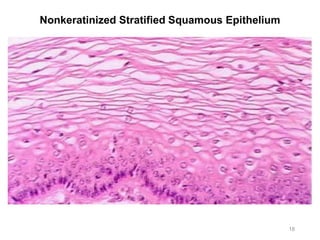
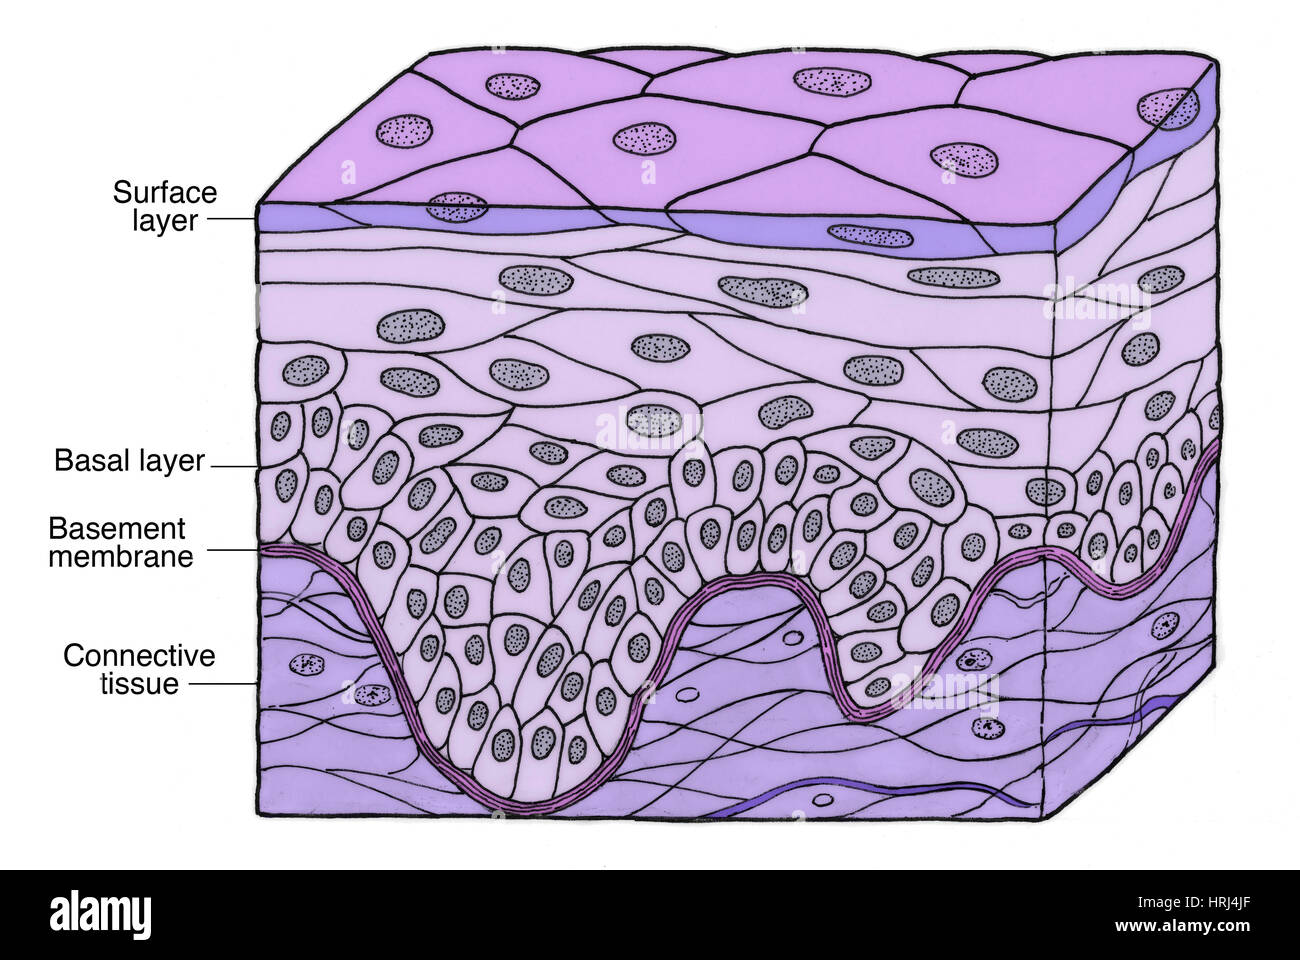
I spent far too long as a grad student trying to distinguish between nonkeratinized and parakeratinized tissue on histology slides. The difference isn't obvious unless you know exactly where to look, and even then you will second-guess yourself when the staining isn't clean. This tissue type is everywhere in the body — the lining of the mouth, the esophagus, the vagina, the anal canal — and it is not as simple as the textbook diagrams suggest. It is a multilayered tissue where the surface cells stay alive and retain their nuclei. That is the critical distinction from keratinized epithelium, where the top layers are dead, flattened cells packed with keratin protein. In nonkeratinized tissue, every layer from the basal cells up to the surface remains viable. The cells get flatter as they move outward, but they do not undergo complete cornification. The cytoplasm stays hydrated, which is why this tissue feels moist and elastic rather than dry and scaly. The basal layer sits on the basement membrane and contains cuboidal to columnar cells actively dividing. Above that are several layers of polyhedral cells that gradually flatten. The most superficial cells are squamous but still nucleated. This whole structure typically measures between 100 and 400 micrometers thick depending on the location. Areas with higher mechanical stress, like the hard palate or the gingiva, can show slight keratinization under normal conditions, which is something to keep in mind if you are trying to classify tissue samples.
One thing beginners miss entirely is that intercellular bridges, the desmosomes connecting these cells, are far more prominent here than in keratinized variants. Under high magnification they look like fine spines between cells. If you are using a lower power objective, you might mistake the tissue for something else entirely because the cellular detail blurs together.
Where You Will Find It and Why It Matters
The oral mucosa is the classic example. The buccal mucosa, the floor of the mouth, the ventral surface of the tongue, and the soft palate all rely on nonkeratinized stratified squamous epithelium. These areas need to stretch and remain flexible while resisting friction from food and dental structures. The esophagus uses the same tissue type for similar reasons, and it transitions abruptly from this to the simple columnar epithelium of the stomach, which is a boundary pathologists watch carefully during biopsy evaluation. During surgery or biopsy procedures involving the esophagus, you may encounter Barrett's esophagus where the normal lining has been replaced by intestinal-type columnar epithelium due to chronic acid exposure. That metaplastic change starts precisely where the nonkeratinized stratified squamous epithelium meets the acidic environment, and identifying the transition zone correctly affects clinical management significantly.
Get the Full Details

A Specific Problem I Encountered
While processing oral swab samples for a research project, I kept getting ambiguous results where the epithelial cells appeared to have lost their surface nuclei. The H&E staining was inconsistent across different batches, and I could not tell whether the tissue was genuinely parakeratinized or if the fixative was causing nuclear degradation. The samples were from the buccal mucosa, which should clearly show viable surface cells. The workaround was twofold. First, I switched from formalin fixation to cold acetone for 10 minutes, which preserved nuclear detail much better for this particular tissue type. Second, I adjusted the hematoxylin staining time from the standard 5 minutes down to 2 minutes, which prevented overlying the subtle nuclear features in the superficial layers. After that change, the surface cells clearly showed intact nuclei instead of the ghost-like outlines I had been seeing. It saved me from wasting weeks collecting more samples and rerunning protocols.
Practical Considerations and Limitations
This tissue type has real vulnerabilities. Because the surface cells are not keratinized, they provide less mechanical barrier protection compared to keratinized variants. In the oral cavity, chronic friction from dentures or sharp teeth can cause reactive hyperkeratosis, essentially forcing the tissue to produce a keratin layer it does not normally make. Pathologists sometimes read this as a separate abnormality when it is actually a benign adaptive response. In diagnostic settings, biopsies from nonkeratinized sites tend to heal faster than keratinized ones because the underlying vascular supply in the lamina propria is robust and the tissue regenerates quickly. However, that same vascularity means bleeding can be more pronounced during surgical excision, which is a practical concern in the oral cavity where blood obscures the operative field rapidly. Another issue is that this epithelium is the primary site for HPV-related lesions in the anogenital region and the oropharynx. The basal cells are the target, and early dysplastic changes can be nearly invisible at low magnification. You need to examine the architectural pattern — loss of polarity, nuclear enlargement, increased mitotic figures — rather than relying on single-cell morphology. Skipping the low-power survey and going straight to high power is a common mistake that leads to missed diagnoses.
If you are working with this tissue in a research or clinical context, investing time in proper section orientation matters more than anything else. Cutting the sample tangentially instead of perpendicularly will compress the layers and make thickness measurements unreliable. A proper cross-section through the full epithelial thickness takes about 30 seconds longer per sample but prevents misclassification that could invalidate your data entirely.