Understanding a Normal Hand X Ray
A normal hand radiograph is one of the most routine imaging studies you'll encounter in any department. It's also one where small technical mistakes can lead to real diagnostic problems if you're not paying attention.Normal Hand X Ray Positioning Basics
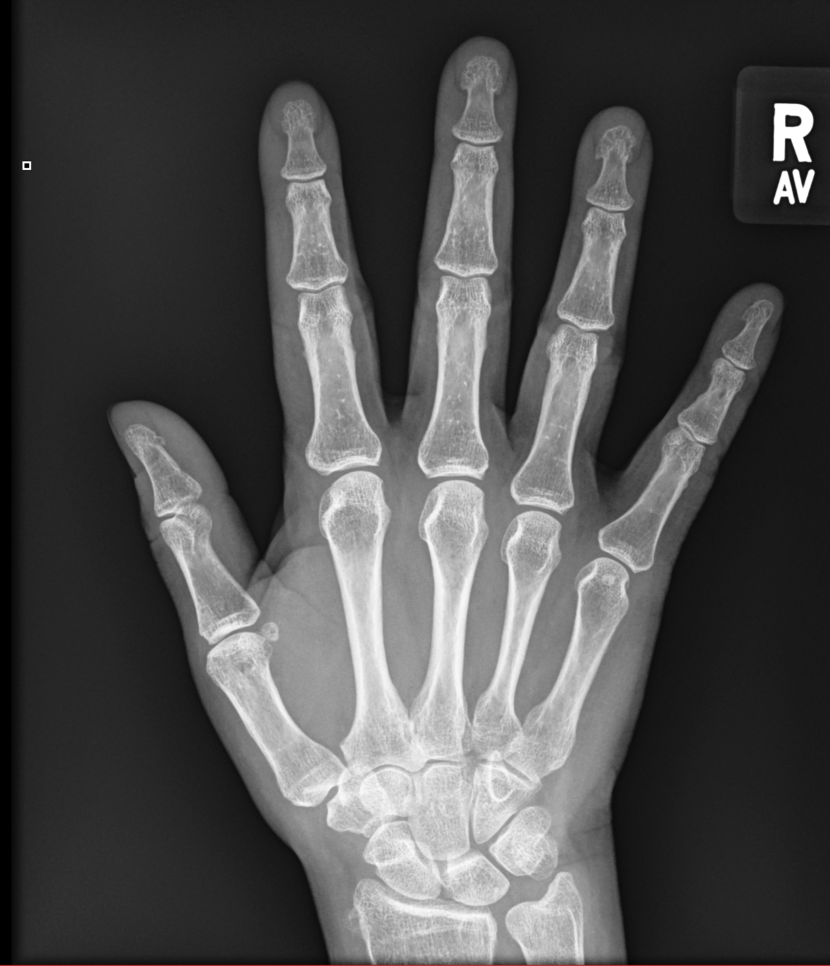
The standard PA (posteroanterior) view requires the patient's hand flat on the detector, fingers slightly spread, and the wrist neutral. For the lateral view, you rotate 90 degrees so the hand is on its side and the humerus, olecranon, and proximal radius/ulna are visible in profile. You'll also get oblique views by rotating the hand approximately 45 degrees toward the PA position. These three views give you the bulk of what you need for a basic assessment.I can't tell you how many times I've seen a "normal" hand film where the PA was actually done as an AP instead, just because the tech couldn't get the patient's hand to press flat. The metacarpophalangeal joints look different on AP versus PA. On a true PA, the metacarpal heads are superimposed over the bases. On an AP, they splay apart. Radiologists notice this immediately and will flag it. It's better to just redo the view. Here's something beginners miss about joint spacing. You're not looking for symmetry between the left and right hand. You're looking at the relationship between adjacent bones on the same hand. The joint spaces between the metacarpal heads and proximal phalanges should be roughly uniform. If one MCP joint looks narrow compared to its neighbors on the same side, that's worth something even if the contralateral hand looks fine.
What You Actually Look For
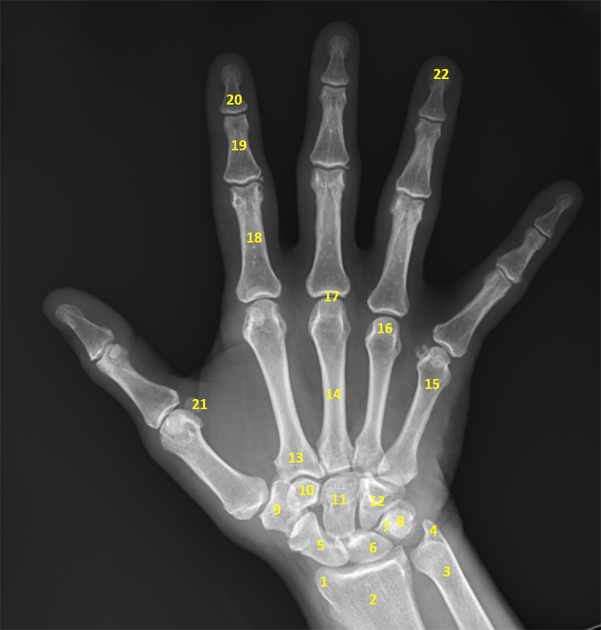
Bone density and architecture come first. The cortex should be smooth and continuous. Trabecular patterns within the phalanges, metacarpals, and carpal bones should be visible but not exaggerated or disrupted. You're checking for lytic lesions, sclerotic spots, periosteal reactions, and any cortical break that might indicate a fracture.Soft tissues matter just as much as bone. Swelling around the extensor tendons over the metacarpals, for instance, can suggest tenosynovitis. Prevertebral or pretracheal fat doesn't apply here obviously, but you look for soft tissue thickening over the dorsal aspect of the hand, along the flexor surfaces, and within the thenar and hypothenar eminences. A mass or fluid collection shows up as a localized soft tissue bulge. The carpal bones are where things get tricky. There are eight of them arranged in two rows, and the way they overlap on a plain film means you have to mentally separate them. The scaphoid is the most commonly fractured carpal bone and the easiest to miss on a standard PA view. That's why you need dedicated scaphoid views or at least a dedicated ulnar deviation position. I've lost count of the initial reads where a nondisplaced scaphoid waist fracture was only caught because the attending noticed subtle cortical stepping on a review.
Technical Factors and Common Pitfalls
For an adult hand, you're typically looking at around 55 to 65 kVp with a low mAs setting. The hand is relatively thin, so you don't need much penetration. Overexposure washes out the trabecular detail, and underexposure makes the soft tissues look denser than they are. Either way, you lose diagnostic information.The most frustrating edge case I deal with involves patients with edematous hands. Swelling distorts the anatomy, makes positioning harder, and changes the required exposure factors. I had a patient recently with significant dorsal hand swelling from an infection. The standard PA was essentially unreadable because the soft tissue was so thick it required more penetration, but then the bones were overpenetrated relative to what you'd get on a normal hand. What worked was bumping the kVp by about 10, keeping the mAs stable, and using a slightly longer source-to-image distance to maintain sharpness while getting the extra penetration the soft tissue demanded. Another issue that comes up constantly is rotation. On the PA view, the distal phalanges should show the interphalangeal joint spaces as symmetric as possible. If one condyle of a phalanx is more prominent than the other, the finger is rotated. This is especially problematic when you're trying to assess for small avulsion fractures or early erosions. Rotation can mimic pathology or hide it entirely.
Get the Full Details

Normal Hand X Ray: Specific Anatomical Landmarks
The sesamoid bones at the first MCP joint are present in roughly 60 percent of the population. They show up as well-corticated oval densities adjacent to the metacarpal head. When they're absent, that's normal variation. When they're present bilaterally, that's normal. When one appears and the other doesn't, or when they look fragmented without a history of trauma, that's worth a second look.The hook of the hamate and the pisiform are variably visible depending on projection. Don't mistake the pisiform for a loose body. It's a sesamoid bone embedded in the flexor carpi ulnaris tendon and sits anterior to the triquetrum. On a true PA, it often appears as a round density overlapping the triquetrum or distal ulna region. Growth plates in pediatric patients deserve their own attention. The distal radius and ulna physis are the most commonly injured in the hand and wrist complex. You need to know the normal ossification timeline to avoid calling a physes a fracture. The capitate and lunate are typically the first carpal bones to appear, around 2 to 4 months of age. The rest follow a fairly predictable sequence through childhood. I still see misreads where a normal ossification center is called an osteochondral fragment.
When a Normal Hand X Ray Isn't Enough
Plain radiography has limitations that people forget. You can't reliably see ligament injuries, tendon tears, or early inflammatory changes. A normal X ray does not rule out a scapholigate injury, a TFCC tear, or early rheumatoid arthritis that hasn't yet caused bony erosion.If clinical suspicion is high and the X ray is normal, you move to MRI or ultrasound depending on what structure you're concerned about. For suspected occult fracture, a bone scan or MRI is more sensitive in the first week. CT is useful for complex intra-articular fractures but adds radiation and isn't a first-line tool for basic hand imaging. Contrast isn't used in standard hand X rays unless you're doing an arthrogram, which is a specialized procedure for detecting ligamentous or capsular pathology. The vast majority of hand radiographs are non-contrast and non-invasive. That simplicity is also what makes them accessible and fast, which is why they remain the first-line imaging modality for hand complaints.