What Normal Actually Looks Like in a Nose Exam
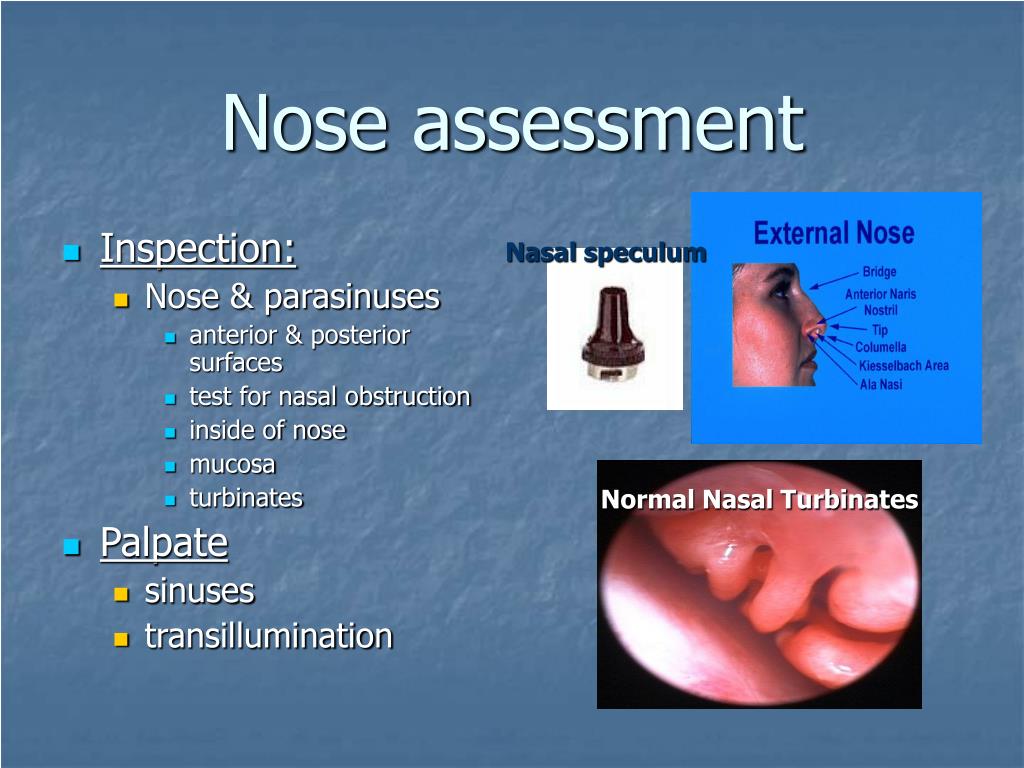
A lot of people studying clinical skills gloss over the nose because it's quick. Five minutes tops if you're not dealing with a messy patient. That's exactly why it gets missed on OSCEs and real practice alike. You walk into a room and need to document Nose Assessment Normal Findings cleanly, but the details matter more than most realize. I ran into a situation a while back during a residency skills check where I missed a tiny septal deviation on the left side. I had it filed under normal because the mucosa looked fine and there was no obstruction. The examiner caught it and it wasn't even symptomatic. Just a subtle cartilage ridge. That one cost me a redo and made me actually slow down on every exam after that. Start with inspection. The nose should sit midline on the face. No trauma, no deformity, no external lesions. The skin covers the whole structure evenly. Inside the nares, the mucous membranes are pink and moist. No erythema, no ulceration, no polyps, no crusting, no discharge. The septum is midline. I know that sounds obvious but it's not always true. A deviated septum shows up often enough that you have to actively look for it rather than assuming it's centered. The turbinates are visible and not enlarged. They shouldn't be swollen or pale. Pale turbinates suggest allergic rhinitis. Red and swollen points toward infection or irritation from something like chronic vasomotor issues. Palpation comes next. Gently press on the frontal sinuses at the brow area and the maxillary sinuses along the cheekbones. Normal is no tenderness. If the patient winces or pulls away, you've found something. Document it. Don't brush it off as them being sensitive. I've seen people lose points on practical exams for not actually doing the palpation. They looked at the nose, said the words, and moved on. That's not enough.
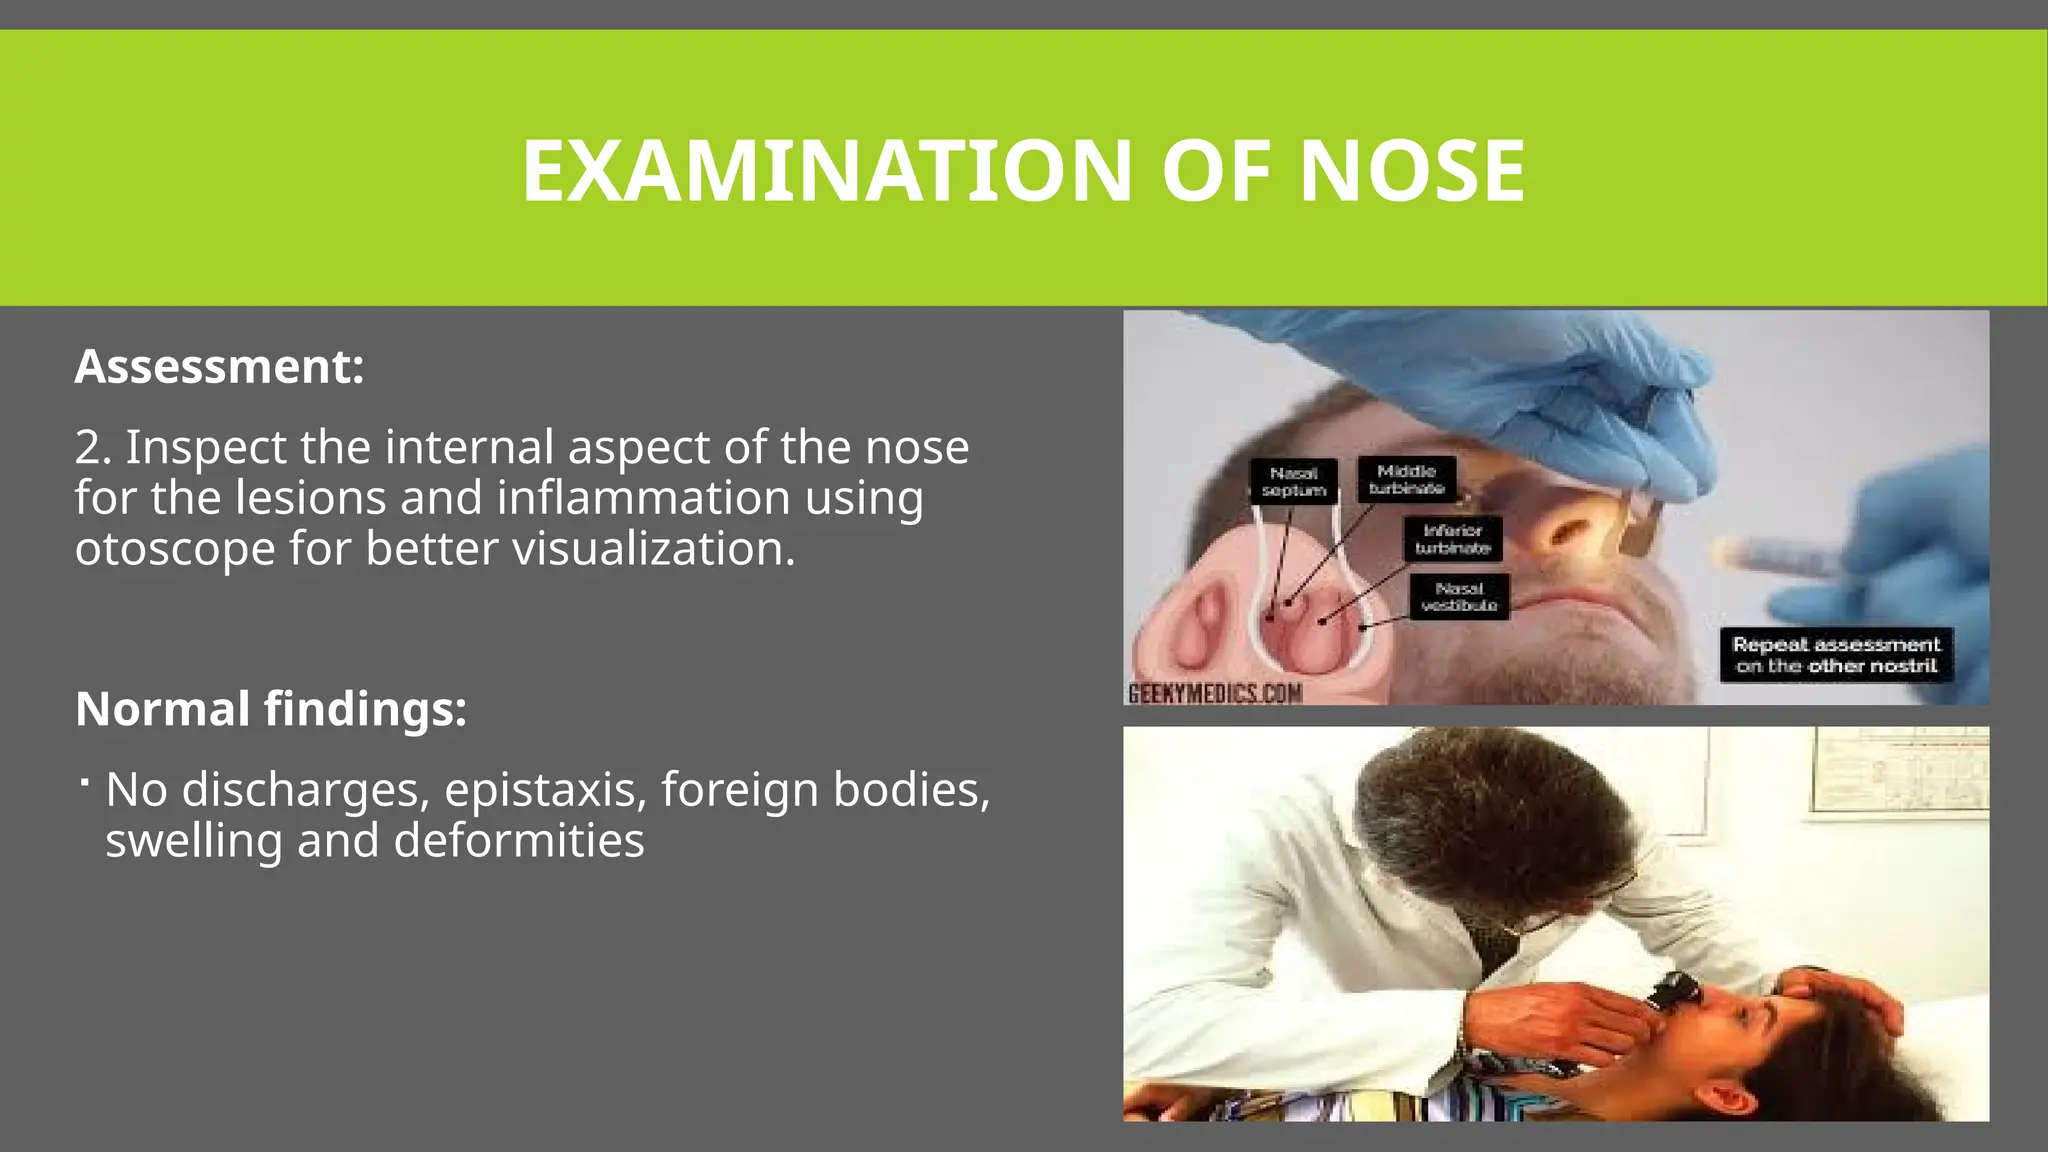
For the internal structures you need a light and either a nasal speculum or just good positioning. Tilting the head back slightly and asking the patient to breathe through their nose gives you a decent view. The anterior septum is where most problems show up.Kiesselbach's plexus sits right there. It's vascular and it bleeds easily. That's normal anatomy, not pathology. Don't mistake it for trauma. Olfaction is part of the assessment too. Most people skip it because it feels awkward. Ask the patient to close their eyes and identify a common scent. Coffee, vanilla, mint. Do it one nostril at a time. Normal is the ability to detect and identify at least one tested odor on each side. If they can't smell anything, that's a finding. Document it as unilateral or bilateral anosmia depending on what you see. The olfactory nerve is CN I. A complete loss on one side with a normal contralateral side can signal something involving the cribriform plate or an intracranial issue. Not something to shrug off. Here's the part most study guides don't emphasize enough. Nasal patency testing. Close one nostril and have the patient breathe in through the other. Switch sides. Normal is equal airflow. Reduced flow on one side doesn't automatically mean a deviated septum. It could be a swollen turbinate from ambient dry air or mild irritation. I usually note it but don't overcall it unless there's a clear structural reason. Context matters. A decongestant spray given before the exam changes everything. If the patient used Afrin that morning, the turbinates will look shrunken and the septum will appear straighter than it actually is. Always ask about that.
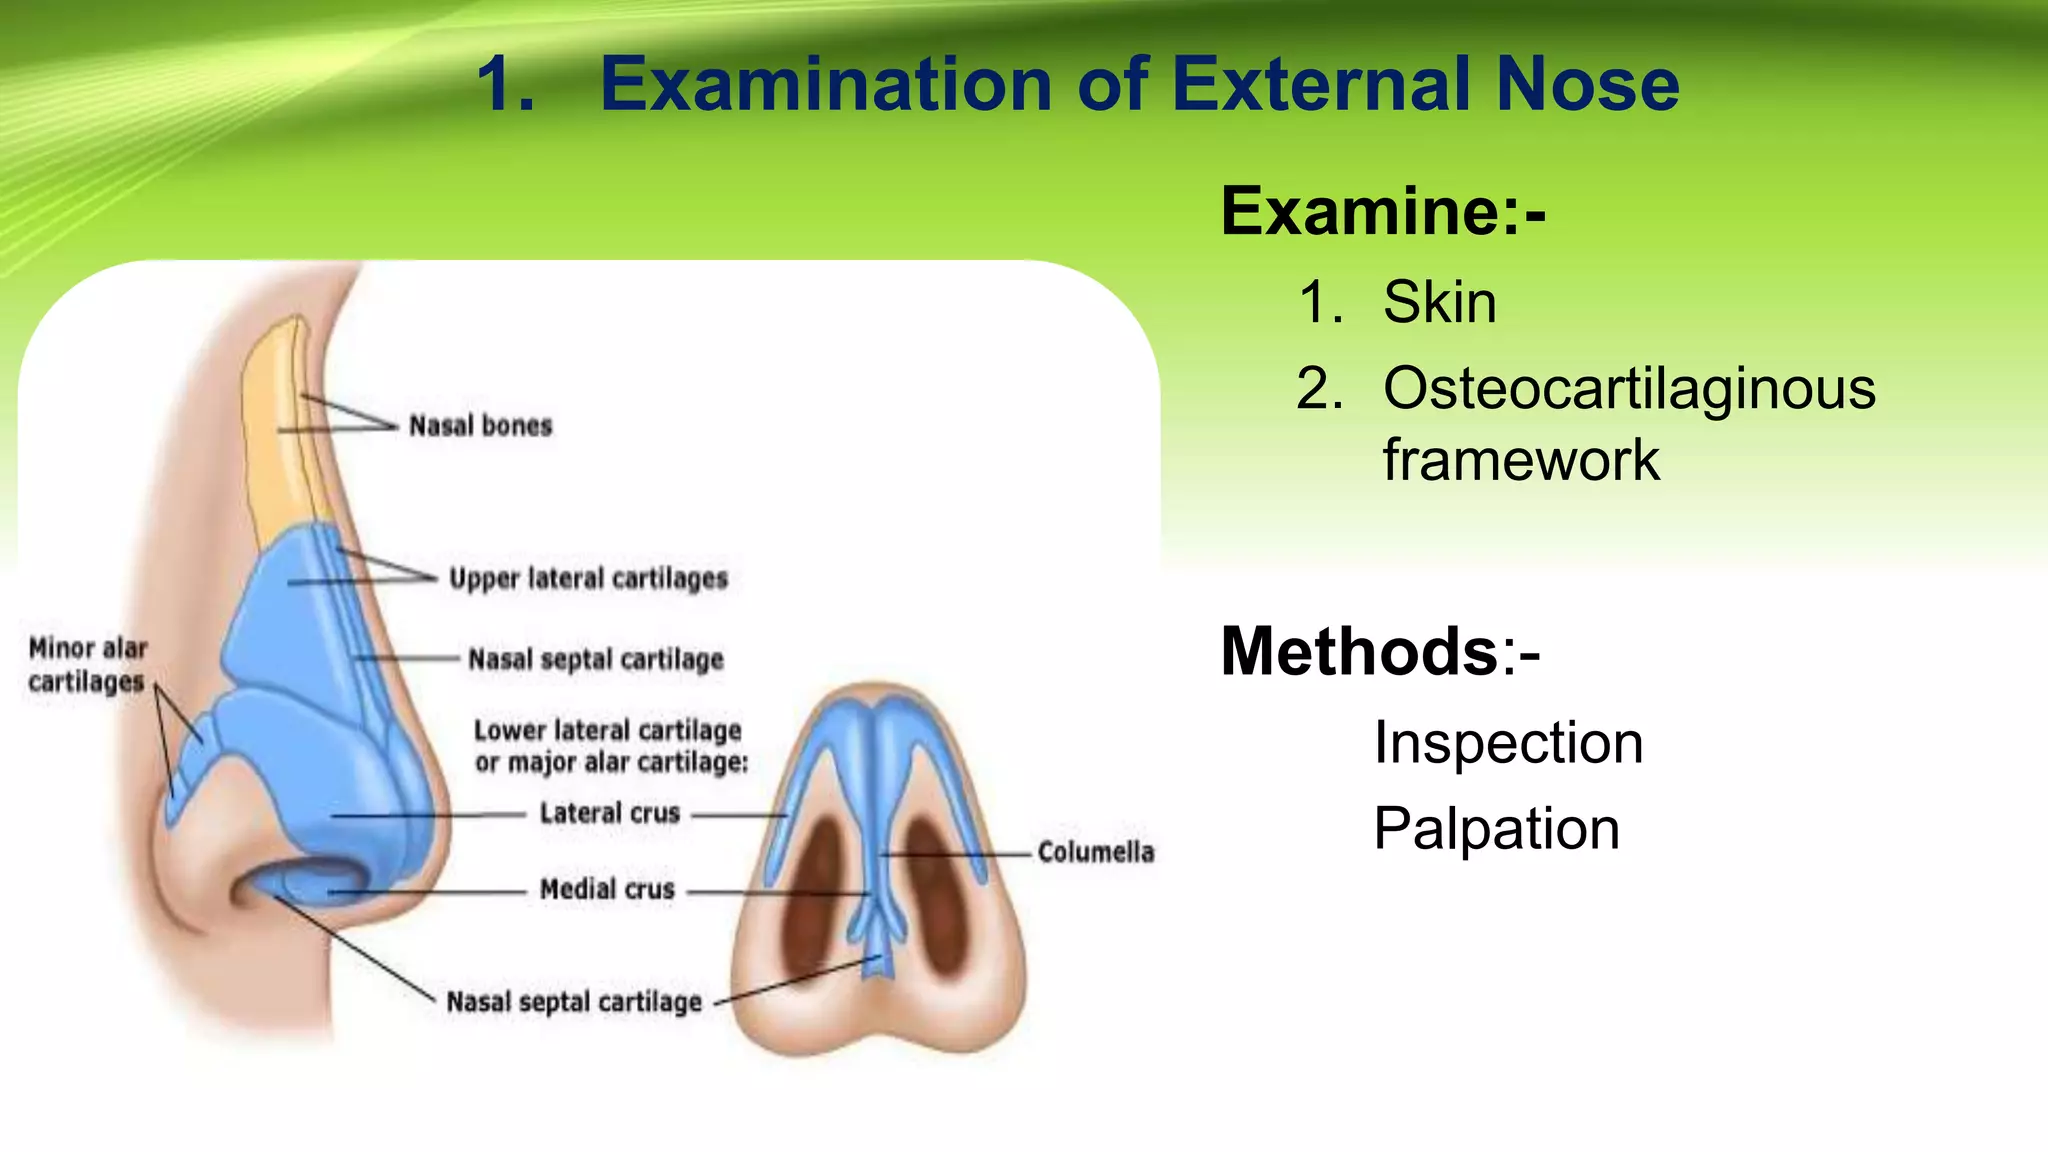
Common pitfalls to avoid Assuming symmetry equals normal. The septum rarely sits perfectly centered in healthy adults. A slight deviation is standard. The question is whether it's causing obstruction or just sitting there. Documenting "midline septum" when there's a minor bend is inaccurate. Documenting "deviated septum" when it's asymptomatic and minimal is technically correct but unnecessary for a normal assessment. The trick is specificity. Note any deviation, note its direction, note whether it's causing airway restriction. If nothing else is wrong, it's still within normal limits. Another mistake is ignoring the nasal tip and alar regions. The cartilage at the tip should be firm but flexible. Pinching the alae and asking about comfort checks for tenderness. Crusted material inside the nostrils near the vestibule is usually from nose picking or dry air. Small amounts are benign. Large amounts with bleeding suggest a more significant issue.
Get the Full Details

What abnormal findings look like so you know what you're ruling out Polyps present as pale, grape-like masses hanging from the superior meatus. They don't bleed easily and they cause progressive obstruction. Septal perforation shows as a hole in the cartilage with crusting around the edges. Hemangiomas appear as red vascular lesions. These are rare but worth knowing because they look alarming. Nasal fractures show external deformity, swelling, ecchymosis, and crepitus on palpation. If you suspect a fracture, do not probe the nose. Get imaging. Internal assessment waits. The vestibulitis angle is another thing. Redness and tenderness at the entrance of the nasal passage, sometimes with small pustules. Usually Staphylococcus related. Common in people who pick their noses or use nasal sprays aggressively. It's a clinical diagnosis and it's outside the scope of normal findings but it's something you'll see after doing enough exams.
Practical Approach for Quick Competent Assessments
Do it in order. Inspection, palpation, internal exam with light, patency check, olfaction. Don't jump around. You'll miss something and then you'll waste time going back. I time myself at about three to four minutes for a thorough normal assessment on a cooperative patient. Five if they have thicker nasal hair or a lot of nasal secretions that need clearing. The secret to speed is practice. Once you've done fifty of these you can go through the whole thing without thinking about it. Documentation template I use: Nose externally midline, no deformity or lesions. Nostrils patent bilaterally. Mucosa pink and moist. Septum midline with mild rightward convexity, no obstruction noted. Turbinates normal size and color. No polyps, discharge, or crusting. Olfaction intact bilaterally to coffee and vanilla. Sinuses non-tender to palpation.
That covers it. It's complete without being verbose. Any deviation from normal goes in place of the relevant line. If something is abnormal you expand that line with specifics rather than tacking on a separate paragraph. The whole assessment should fit in three to five lines in the chart. One more thing nobody tells you about. Lighting. A standard penlight isn't always enough. The internal nasal cavity is deep and shadowy. An otoscope with the otoscopic head and a speculum works better if you have one available. The direct light gets further in. I carried one in my pocket during clinical rotations and it made a noticeable difference in what I could actually see versus what I assumed was normal based on a partial view. If you're doing these assessments regularly and you only have a penlight, you're working at a disadvantage. Just something to keep in mind.