What Nurse Self Scheduling Actually Looks Like
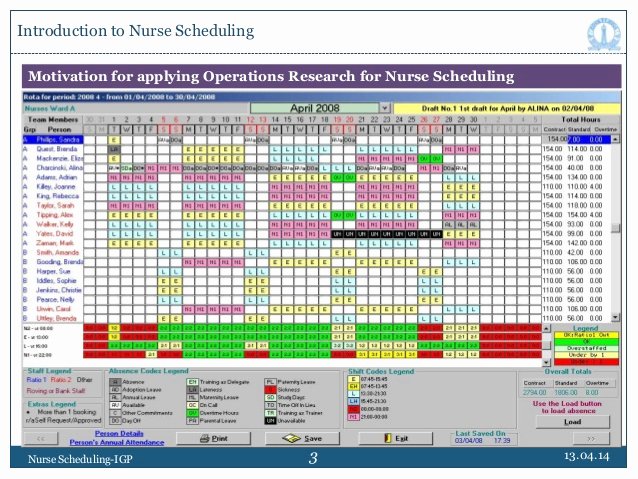
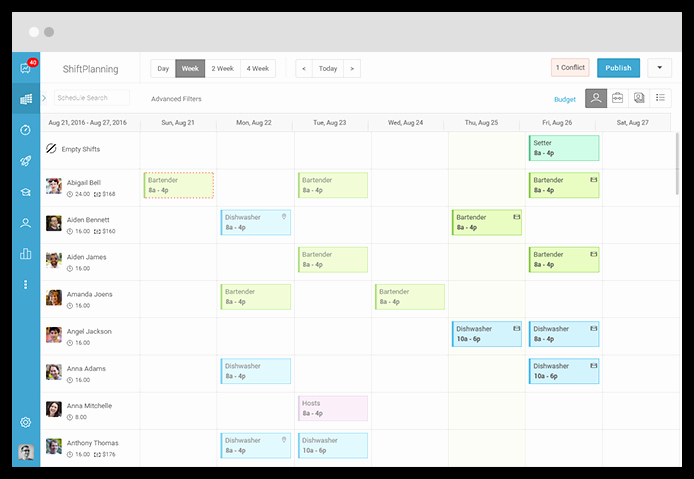
I spent three years running scheduling for a 120-bed medical-surgical unit before we moved to a self-scheduling model, and the transition was uglier than any vendor presentation would have you believe. The core idea is straightforward enough: nurses pick their own shifts through a software platform instead of waiting for an assignment from a scheduling coordinator. You log in, you see open shifts, you grab the ones you want within your contract constraints. Done. The reality is messier. You need hard rules baked into the system first, or you will spend six hours every two weeks untangling conflicts that a competent human scheduler would have prevented before the board even opened. Let me walk through how to set this up without losing your mind.
Why Nurses Prefer Nurse Self Scheduling Over Methods
The main driver is autonomy, obviously, but the secondary driver that actually makes it stick is that it cuts scheduling administration time dramatically. A typical manual scheduling process for a mid-size unit takes one to three full working days per pay period. With a properly configured self-scheduling system, that drops to maybe two hours of exception handling. That is the number that gets buy-in from administration. The nurse satisfaction numbers are a bonus, not the primary argument. That said, nurse satisfaction only improves if the system actually works. I have seen units where self-scheduling made things worse because the IT department configured the rules poorly and nobody could pick the shifts they needed. The unit ended up with more complaints than when the charge nurse was just handing out schedules by hand.
Setting Up the Rule Engine
This is the part everyone rushes through and then regrets. You need to define your hard constraints before you touch a single line of software. Hard constraints are non-negotiable rules that the system will not allow anyone to violate. Soft constraints are preferences that the system should try to honor but can override if necessary. Your hard constraints should include things like certification requirements for specific units, maximum consecutive work days, minimum rest between shifts, total hour limits per pay period, and labor law requirements for your state. If your state mandates one day off per seven worked, that goes in as a hard constraint. If you want nurses to have at least two weekends off per month, that is a soft constraint. I learned this the hard way. We launched our self-scheduling system with what I thought were adequate constraints. Within two weeks, a nurse on the telemetry float pool picked up a shift in the ICU because the system had a gap in its certification verification logic. She had a telemetry certification but not a critical care designation, and the platform let her book anyway. The night supervisor caught it, obviously, but it created a real patient safety concern and a very uncomfortable conversation with risk management.
Get the Full Details
The workaround was straightforward but expensive in terms of time. I wrote a custom validation script that cross-referenced each nurse's certifications against unit-specific requirements before allowing a shift to be claimed. It ran overnight and flagged any violations for review the next morning. We then fed those flags back into the platform's configuration so the same error would never happen again. That took about forty hours of my time spread over two weeks. I would have saved most of it by being more thorough in the initial rule setup.
The Configuration Process
Most platforms follow a similar pattern even though the interfaces look different. You start by defining your scheduling templates. These are the base shift patterns your unit uses. A standard day shift template might be 7a to 7p, a night shift 7p to 7a, and a flex shift something like 8a to 6p. You assign hourly rates, differentials, and any union-grievable premium pay to each template. Next you build your nurse profiles. This is where you input each nurse's contract type, preferred shift pattern, certification matrix, availability restrictions, and any personal scheduling limitations they have submitted. Some platforms pull this data from your HRIS automatically. Many do not, which means someone has to enter it manually and verify it twice. Then you configure the rule engine itself. This is the stage where you import the hard and soft constraints I described above. Most platforms give you a visual rule builder. You drag and drop conditions like "no more than four consecutive day shifts" or "must have 10 hours between clock-out and clock-in." Test every single rule before you go live. I cannot stress this enough. Create a dummy nurse profile with edge-case constraints and run it through every possible combination of shift selections. If you skip this step, you will find out during an actual pay period, which is the worst possible time.
Going Live and Managing Exceptions
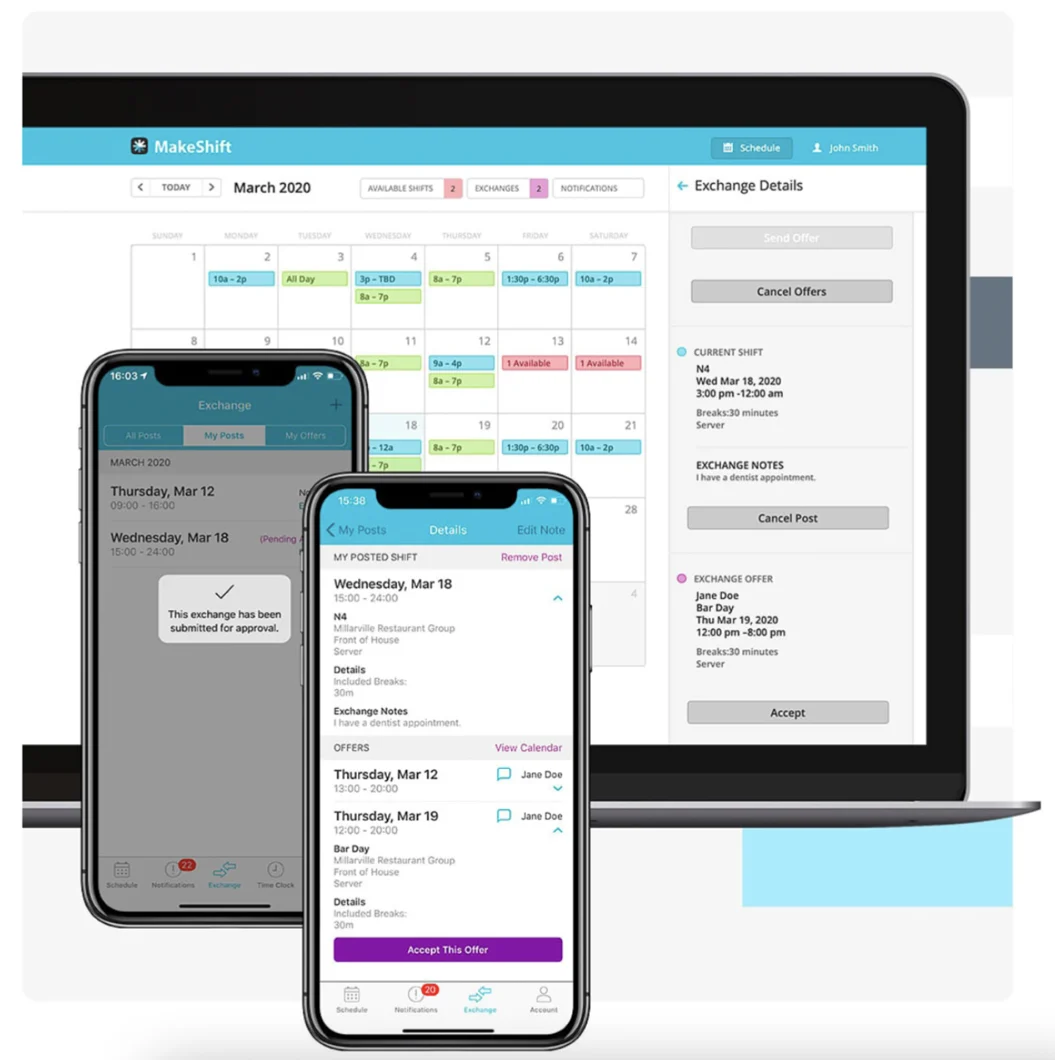
When you launch, start with a limited group. Do not flip the switch for your entire nursing staff on day one. Pick one unit, maybe twenty to thirty nurses, and run it for two full scheduling cycles before expanding. You will encounter problems that your testing did not catch. You will discover that the shift trades feature works differently than the documentation says it does. Someone will figure out a loophole you did not anticipate. I recommend designating a go-live champion on the floor. This person should be a senior nurse who is comfortable with technology and has the authority to make real-time decisions about scheduling conflicts. During my unit's launch, our go-live champion was a charge nurse named Patricia who had been scheduling by hand for fifteen years. She immediately spotted that the system was allowing nurses to claim shifts that violated their pre-approved vacation blocks because the vacation module and the scheduling module were not fully integrated. That was a two-week fix that could have been caught in testing if we had included vacation conflicts in our test scenarios. The exception management workflow is critical. When a nurse picks a shift that violates a soft constraint, the system should flag it but not block it. The scheduling coordinator or designated manager reviews the flag and either approves the override or denies it with a reason. For hard constraint violations, the system should simply not allow the selection. You do not want people booking shifts they cannot legally work.
Common Pitfalls
The biggest pitfall I see is under-configuring the rules. Vendors will tell you that you can always adjust rules later. They are not wrong, but every adjustment requires communication to the nursing staff, potential reshuffling of already-picked shifts, and erosion of trust in the system. People need to know that what they booked today will stay booked tomorrow. If rules change retroactively, they lose confidence quickly. A second pitfall is assuming that self-scheduling eliminates the need for a scheduling coordinator. It does not. You still need someone to monitor the board, handle shift trades, fill gaps when coverage drops, and manage last-minute changes. The role shifts from creator to moderator, but it still exists. Units that try to fully automate scheduling without maintaining oversight usually end up with coverage holes that nobody noticed until a patient census spike hit and there were no bodies on the floor. The third pitfall is technical. Integration failures between your scheduling platform and your HR system, your timeclock system, and your EHR credentialing module. I have watched platforms fail to update a nurse's shift differential after a promotion because the HRIS sync ran on a different schedule than the scheduling module. The nurse worked thirty hours at the new rate and got paid at the old rate. Correcting it required manual adjustment and an apology email to the affected nurse. That kind of error damages credibility faster than anything else.
What Works in Practice
After eighteen months of running self-scheduling across four units, here is what I can say with confidence. It works well when you invest time upfront in rule configuration and ongoing time in exception monitoring. It fails when you treat it as a set-it-and-forget-it solution. The platforms that claim full automation are selling something that does not exist for most hospital environments. The nurses who embrace it tend to be those who value predictability. If someone knows they want every other weekend off because of child care, or they need three consecutive days during a specific week for a family event, self-scheduling lets them lock that in early. The ones who struggle are typically new grad nurses who are still figuring out their preferences, or nurses with highly variable personal obligations. For those groups, a hybrid approach works better. Let them pick from a pre-generated schedule that respects their known constraints rather than giving them complete freedom from day one. Cost-wise, a decent self-scheduling platform for a 100 to 200 bed hospital runs somewhere between fifteen thousand and forty thousand dollars annually depending on features and vendor. The savings come from reduced scheduling coordinator hours and lower turnover related to schedule dissatisfaction. Whether those savings offset the cost depends on your local wage environment and your baseline staffing model. Do the math for your specific situation before committing.
Bottom Line
Nurse self-scheduling is a real solution to a real problem, but it is not a simple one. The technology is mature enough that implementation failure is usually a process problem, not a software problem. Get your rules right. Test aggressively. Start small. Maintain oversight. Communicate changes before they happen. If you do those five things, the system will work. If you skip any of them, you will learn about it in the most inconvenient way possible.