How Nurses Notes Actually Get Written in Real Practice
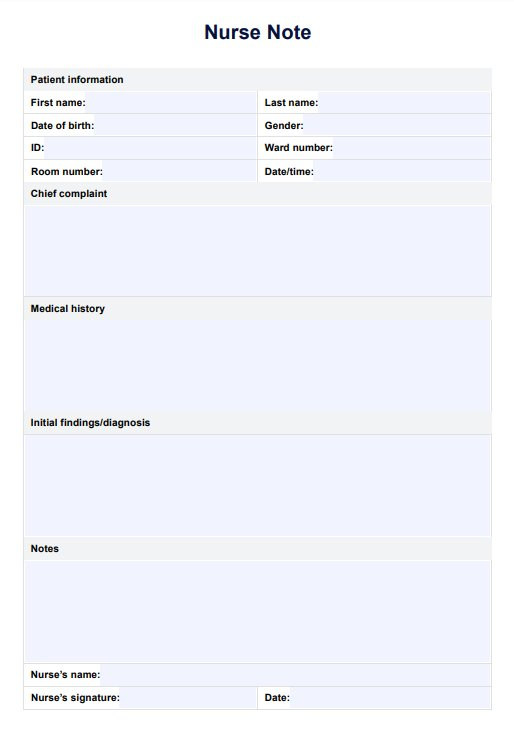
I spent years at a 36-bed medical-surgical unit before moving into chart auditing. The template system there was built around SOAP notes, but nobody actually used it the way the policy manual described. What you end up with is a hybrid document that combines structured data entry with narrative flow, and the quality of the end result depends almost entirely on how disciplined the nurse is when they log in to document. A Nurses Notes Template is basically a structured framework that standardizes what gets recorded during patient shifts. It typically includes sections for subjective findings, objective measurements, assessment notes, and planned interventions. The idea is that every shift gets the same level of detail across every patient, which makes legal review faster and clinical handoffs more reliable.
Why a Basic Nurses Notes Template Is Not Enough
The standard template most hospitals hand out is a one-size-fits-all form. It works fine for routine admissions, but it breaks down fast once your patient list includes wound vacs, ventilator weaning, or telemetry for cardiac monitoring. I ran into this problem repeatedly with a sepsis patient in 2019 whose vitals were changing hourly. The template had a single vital signs block that assumed a q4h or q8h check schedule. By the time I noticed the gap in documentation during my next audit cycle, we had gone six hours without a recorded trend line that would have been critical for the rapid response team if the patient had deteriorated overnight. The workaround I implemented was adding a custom "acute change tracking" field into our template that forced a timestamped narrative note whenever vitals were pulled q1h or more frequently. This took about twenty minutes to set up in our Cerner system and cut the documentation review time for high-acuity patients from roughly ten minutes per shift to about three. The counter-intuitive part that nobody tells you about these templates is that they often reduce rather than increase documentation quality. When nurses have to fill in every single box, they tend to rush through the later sections because they have already spent fifteen minutes on the first half. The vital signs block gets detailed, the intake output gets logged, but by the time you get to the "plan" section, it reads like a copy-paste from the previous shift. The template gave the illusion of thoroughness while the actual clinical reasoning got thinner.
Another thing people miss is the relationship between template fields and billing compliance. In the US, specific documentation elements map directly to E/M coding levels. If your Nurses Notes Template doesn't explicitly prompt for the components that support a higher-level encounter, you will leave money on the table or, worse, get audited for upcoding when the documentation doesn't back it up. The template needs to be aligned with current CMS guidelines, not just clinical best practices. Here is what a functional template should include in practice: Subjective section needs patient-reported symptoms with onset timing and severity scales. Objective section requires vitals, lab results, and physical exam findings with exact timestamps. Assessment must contain a clinical impression that connects the subjective and objective data rather than restating it. Plan needs specific interventions ordered by priority with responsible party and expected completion timeframe. Pain scores belong in objective with the agent and dosage documented alongside them, not buried in a narrative paragraph where they can be missed during handoff.
Get the Full Details
IO balance templates need to auto-calculate net totals and flag discrepancies greater than five hundred milliliters over a twelve-hour period. Most systems I have seen do not do this by default, which means a nurse could miss a one-point-two-liter negative balance until it becomes a clinical emergency. This is not a theory, it happened in my unit twice within a single quarter.
What a Nurses Notes Template Should Actually Look Like
A well-structured version includes pre-populated fields for common conditions so the nurse does not waste time rewriting the same language. It also includes conditional logic that shows or hides fields based on patient acuity and admission type. A post-op patient gets different prompts than a med-admit. The template should adapt rather than present the same blank form every time. The format breakdown: Header section with patient identifiers, RN name, shift designation, and primary diagnosis. Vitals block with date, time, and parameters for blood pressure, heart rate, respiratory rate, temperature, oxygen saturation, and pain score. Neurological assessment with Glasgow Coma Scale when indicated. Cardiac and respiratory evaluation fields. GI and GU function documentation. Skin integrity with Braden scale scoring where applicable. Medication administration timestamps cross-referenced to the MAR. IV site checks with site location and condition notes. Patient education provided with specific topics covered. Family communication log with name and relationship. Changes in condition with notification of attending provider, time, and response. Shift plan with ongoing priorities and concerns for the incoming nurse.
Writing in narrative form within each section is necessary for things that do not fit into drop-down boxes. But the narrative should be concise. Three to four sentences maximum per shift unless something unusual occurred. Documentation bloat is a real problem. I have seen notes that run two pages for a routine shift with zero clinically actionable information beyond what the vital signs panel already showed. That takes away time from actual patient care and creates legal exposure because important details get buried in prose. The biggest limitation of any template system is that it cannot capture nuance. A patient who is "stable per template criteria" might actually be showing subtle signs of decline that a checklist will never flag. The template tracks trends in aggregates, but clinical judgment happens at the individual level. I would recommend pairing template documentation with a daily nursing huddle where the team reviews flagged cases manually. This adds roughly fifteen minutes per shift but catches issues that the system silently passes over. If you are building or updating a Nurses Notes Template for your facility, start with a workflow analysis of your current process. Document where the bottlenecks are, which fields get skipped most often, and what information nurses wish they could record but the form does not allow. Then redesign from that data instead of importing a template from a vendor website. Vendor templates are generic by design and rarely fit a specific unit's actual work pattern.
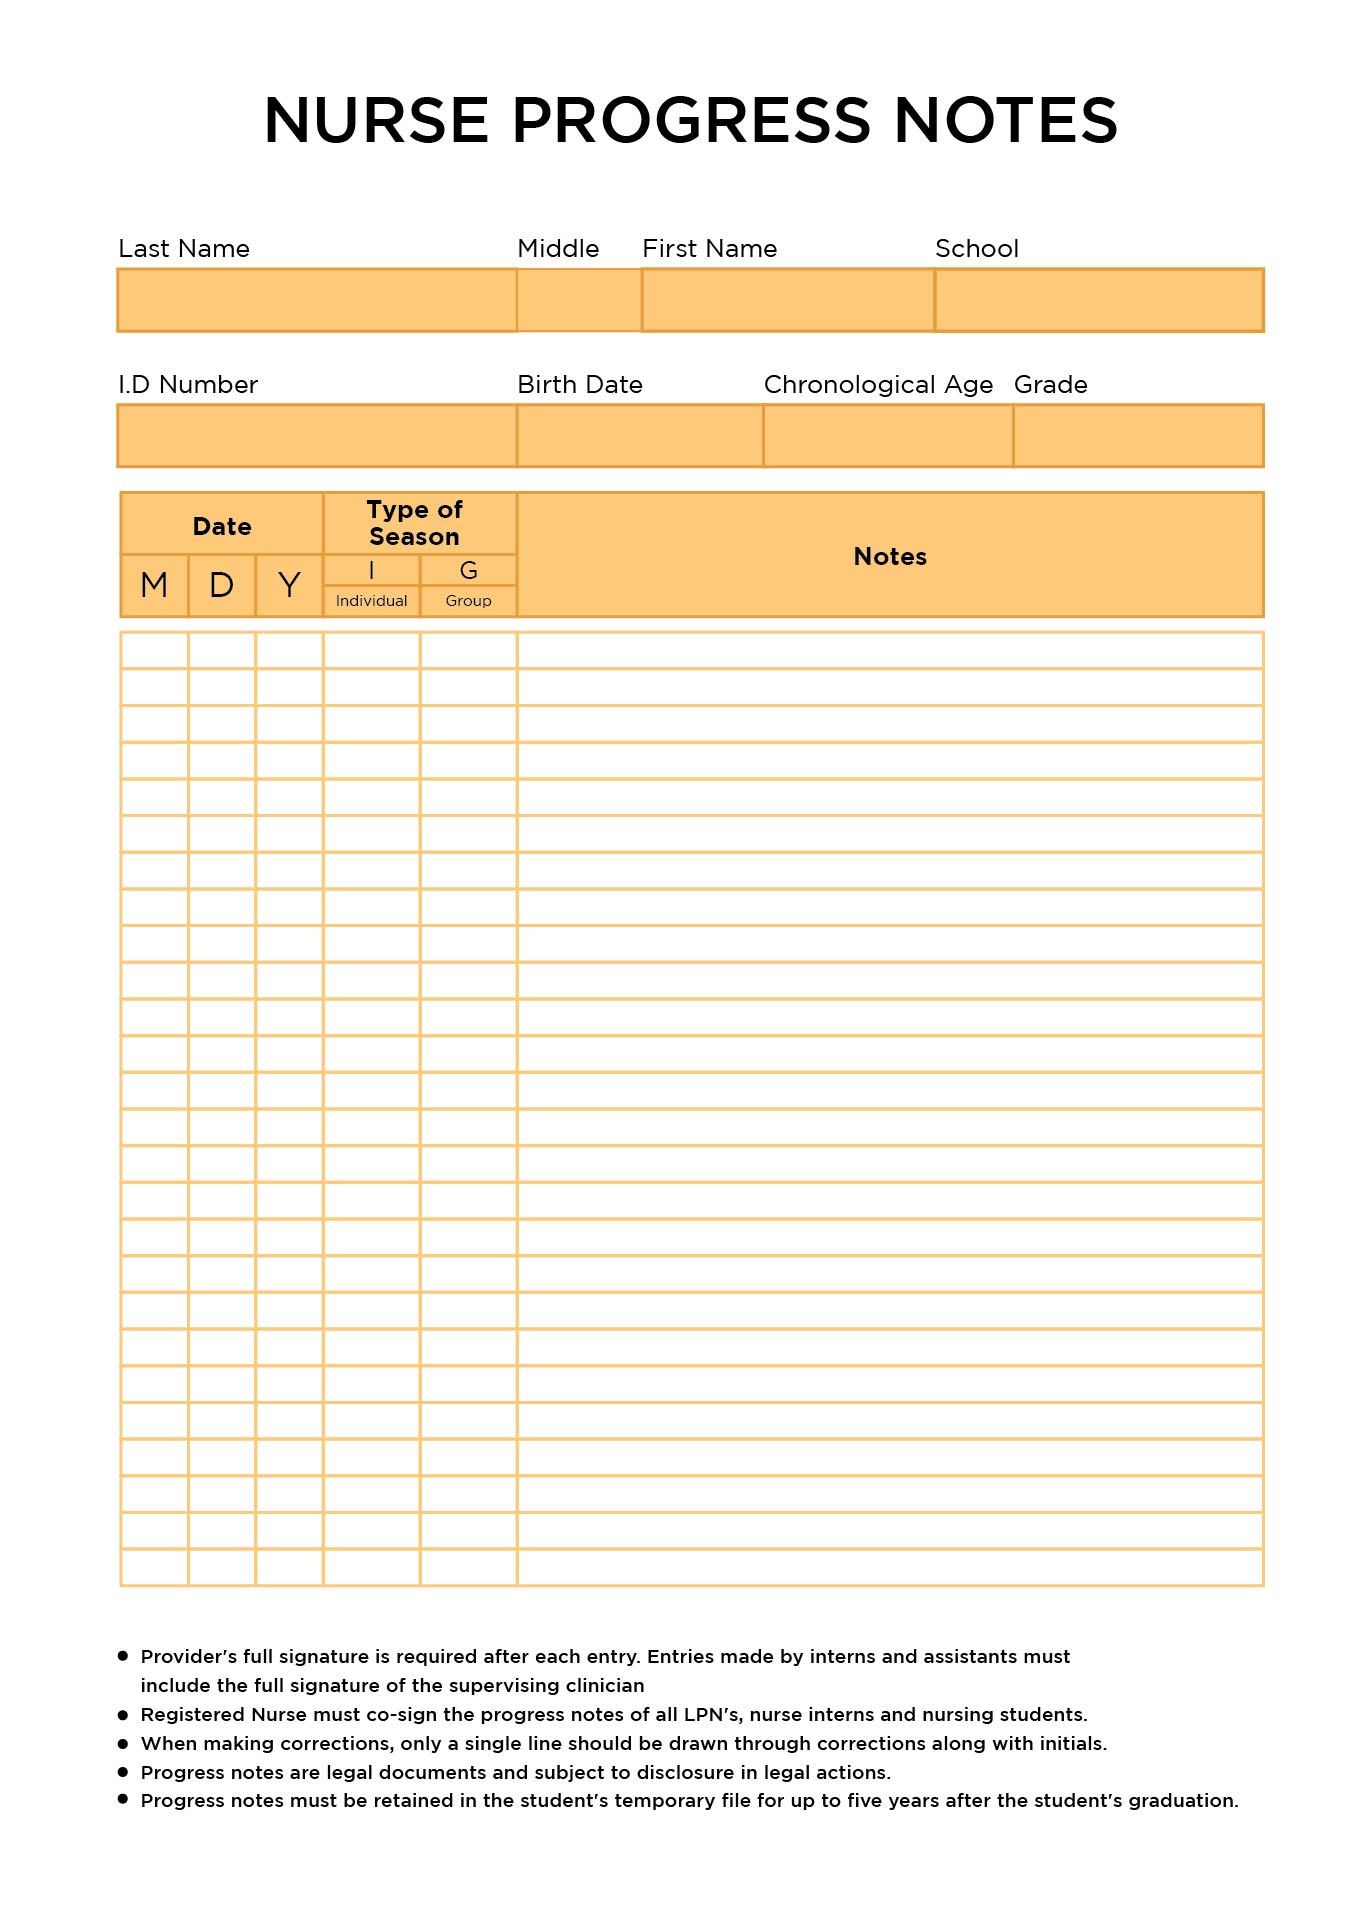
A simple version you can adapt right now: Patient name, MRN, date, shift. Chief complaint and admission diagnosis. Vitals with timestamps and trend notation. Focused assessment findings organized by body system. Interventions performed during shift with times. Response to interventions noted briefly. Labs and imaging results reviewed during shift with significance. Pain management details. Fluid balance total with any concerns. Communication with provider including time, method, and orders received. Patient and family education topics. Plan for next shift with specific priorities and red flags to monitor. This covers the essentials without inflating the document into something that takes twenty minutes to complete. Documentation should take about eight to twelve minutes for a standard med-surg shift and up to twenty minutes for a high-acuity case where more detail is warranted. Anything longer usually means you are recording irrelevant information or the template is poorly designed.
There is no single download link I can give you that will work universally because every electronic health record system structures templates differently. Epic, Cerner, Meditech, and Allscripts all handle template creation through their own authoring tools with different permission requirements. Your IT or nursing informatics team will need to build or customize the template inside your specific platform. The content I outlined above translates across all major systems, but the implementation method depends entirely on which EHR your facility uses. What I can say with confidence is that the template approach works when it is treated as a documentation guide rather than a compliance checkbox. Nurses who understand why each section exists tend to fill it out more thoroughly and accurately. Those who see it as paperwork to survive will minimum-effort their way through it every shift, and the template will fail to serve its actual purpose regardless of how well-designed it is on paper.