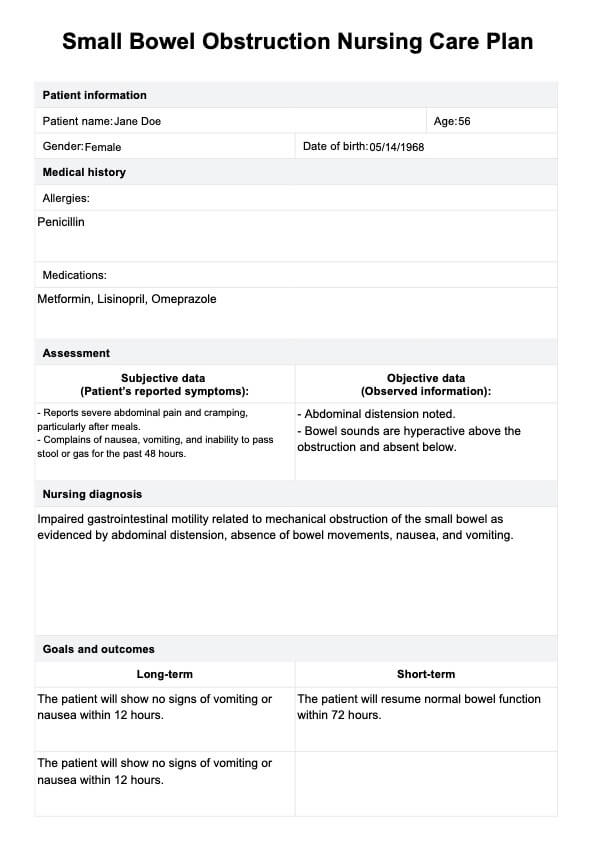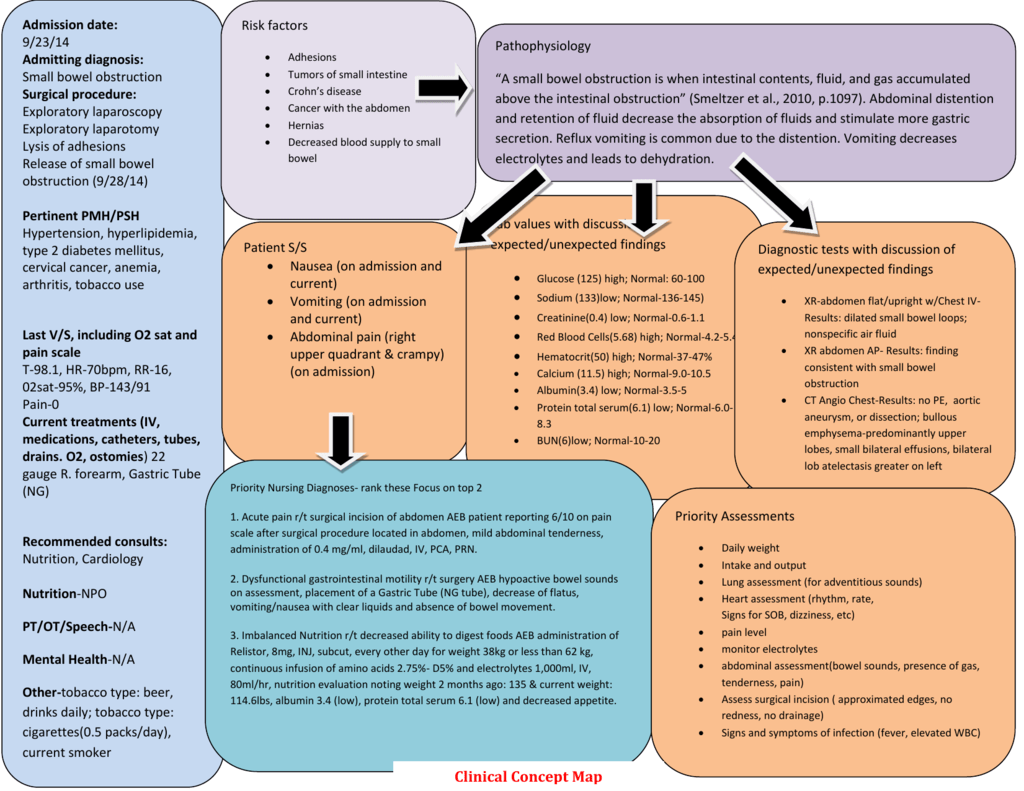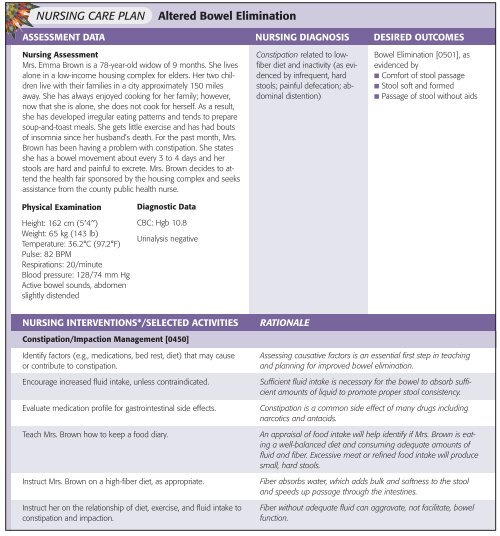
Setting up a Nursing Care Plan For Bowel Obstruction that actually works
Most nursing care plan templates you find online are worthless for bowel obstruction cases. They list "impaired bowel elimination" as the problem and then say "monitor I&Os" as the intervention. That's not a plan. That's a placeholder. Here's how I build one that survives actual clinical review.Key Assessment Data You Need Before Writing Anything
Before you document a single nursing diagnosis, gather these specifics. Without them your plan reads like fiction. Pain characteristics: Location (periumbilical versus generalized), quality (crampy/colicky versus constant), timing (intermittent waves correlating with hyperactive bowel sounds early, becoming absent later). The shift from hyper to hypoactive is a real warning sign. I had a patient whose pain pattern changed at 0300 and their sounds went silent. Turned out they were transitioning from simple to strangulated obstruction. The care plan didn't account for that progression. It should. Auscultation findings: Document the actual sounds, not just "present" or "absent." High-pitched tinkling sounds in the early phase are specific to mechanical obstruction. Absent sounds after 24-48 hours suggest ileus or peritonitis developing. Write it down with timestamps.
Nausea and vomiting details: Character of emesis matters. Feculent vomiting means distal obstruction. Bilious vomiting points more proximal. Electrolyte replacement strategies differ significantly depending on what's being lost. ABSOLUTE NO MARKDOWN I mean that in the HTML sense, but also in the writing sense — don't use asterisks or hashes for formatting. Just write clean HTML.
Nursing Diagnoses Ranked by Actual Priority
Beginners list all diagnoses equally. In bowel obstruction, priority shifts with the patient's acuity. Here's the order I use, based on what actually kills people if you miss it: 1. Risk for deficient fluid volume — This is usually the real killer, not the obstruction itself. Third-spacing in the bowel lumen, vomiting, and NPO status combine to create significant volume depletion within hours. I've seen patients hit hypovolemic shock before anyone connected the dots because the care plan didn't flag this as the top concern. Fluid resuscitation isn't optional. It's the first intervention. 2. Acute pain — Colicky pain from peristaltic struggle against an obstruction is severe. But here's the counter-intuitive part: don't give opioids too aggressively early on. Opioids slow gut motility further and can mask the clinical picture. Use them, yes, but document the timing relative to assessment findings. If pain scores drop but the abdomen becomes distended and tender, that's not improvement. That's deterioration masked by medication.
Get the Full Details

3. Imbalanced nutrition: less than body requirements — Relevant for partial or chronic obstructions, less urgent in acute complete obstruction where surgery is likely imminent. Don't over-plan for nutrition in the first 48 hours of an acute presentation. 4. Anxiety — Real and valid. The patient knows they feel awful and they know surgery might be coming. Address it, but don't let it bump fluid volume risk to second place.
Interventions That Actually Matter
The standard interventions — NPO, NG tube, IV fluids — are table stakes. Every plan includes them. What separates a competent plan from a good one is what you add around those basics. Serial abdominal assessments: Not just one assessment at admission. Every 2-4 hours initially, documenting distension measurements (umbilicus circumference), tympany patterns, and bowel sound character changes. I used to chart this on a standard flow sheet and it was adequate. Then I started using a simple diagram where I sketched the abdomen and shaded areas of tympany versus dullness. It took 30 seconds longer per assessment but caught a localized distension pattern in one patient that flagged a closed-loop obstruction two hours before vitals deteriorated. That patient went to surgery promptly. Another patient with the same obstruction pattern missed on the flow sheet alone developed ischemia before we acted. The diagram made the difference. NG tube management: Most plans say "maintain NG tube suction." Specifics matter. Check patency every shift. Irrigate only per physician order and protocol — some surgeons want it left alone, others have specific saline volume protocols. Document output color, consistency, and volume hourly in the first 24 hours. A sudden increase in output after it had been decreasing can mean the obstruction is partially resolving OR that there's a new issue proximally. Context tells you which.
Laboratory monitoring: Get a baseline CBC, comprehensive metabolic panel, and lactate on admission. Repeat the metabolic panel every 12-24 hours depending on severity. Lactate is the one beginners skip. Elevated lactate in the context of bowel obstruction suggests ischemia. It's a surgical trigger, not a medical management trigger. Flag it prominently in your plan. Pain reassessment timing: After any intervention for pain, reassess in 30-60 minutes for IV medications, 2 hours for oral. Document the actual change, not just "pain improved." If it went from 8 to 6, that's a specific finding. If it stayed at 8, that's a different finding that needs a different response.
What Most Plans Miss Completely
Bowel obstruction care plans almost never address the surgical transition explicitly. Here's the thing: most adult mechanical obstructions ultimately need surgery. Your plan should have a clear branch point. If conservative management (NG decompression, fluids, bowel rest) doesn't show improvement within 48-72 hours, the plan shifts from medical management to preoperative preparation. Document that decision threshold in the plan itself so any nurse on any shift knows exactly when to escalate. Another gap: discharge planning doesn't start until it's clear the patient is going home. But the risk factors for recurrence or readmission should be identified early. Adhesive bandage care, understanding of symptom recurrence, and when to return to the hospital are all part of the plan from day one, even if you're nowhere near discharge yet.
Common Mistakes That Break These Plans
Copying and pasting from a previous admission: I've reviewed care plans where the previous admission's dates were still in the document. More seriously, I've seen plans where the obstruction level from a previous small bowel obstruction was carried forward for a new patient with a large bowel obstruction. The management is fundamentally different. Small bowel obstructions often resolve conservatively. Large bowel obstructions, especially in older patients, frequently indicate malignancy and need different workup and timing. Ignoring the psychological component of NPO status: Not being able to eat or drink is harder on patients than most nurses account for. Thirst is brutal. Dry mouth from mouth breathing through an NG tube is miserable. Basic mouth care with swabs and lip moisture isn't a nice-to-have. It's a documented intervention that affects compliance and comfort significantly. Not specifying who does what and when: A care plan that says "monitor vital signs" is useless. It needs "assess VS every 4 hours, report HR above 110 or BP below 90 systolic to attending physician immediately." Specific numbers. Specific thresholds. Specific actions. Anything less shifts the burden of clinical judgment onto whoever is reading the plan at 3 AM.
The Bowel Obstruction Nursing Care Plan Template Approach
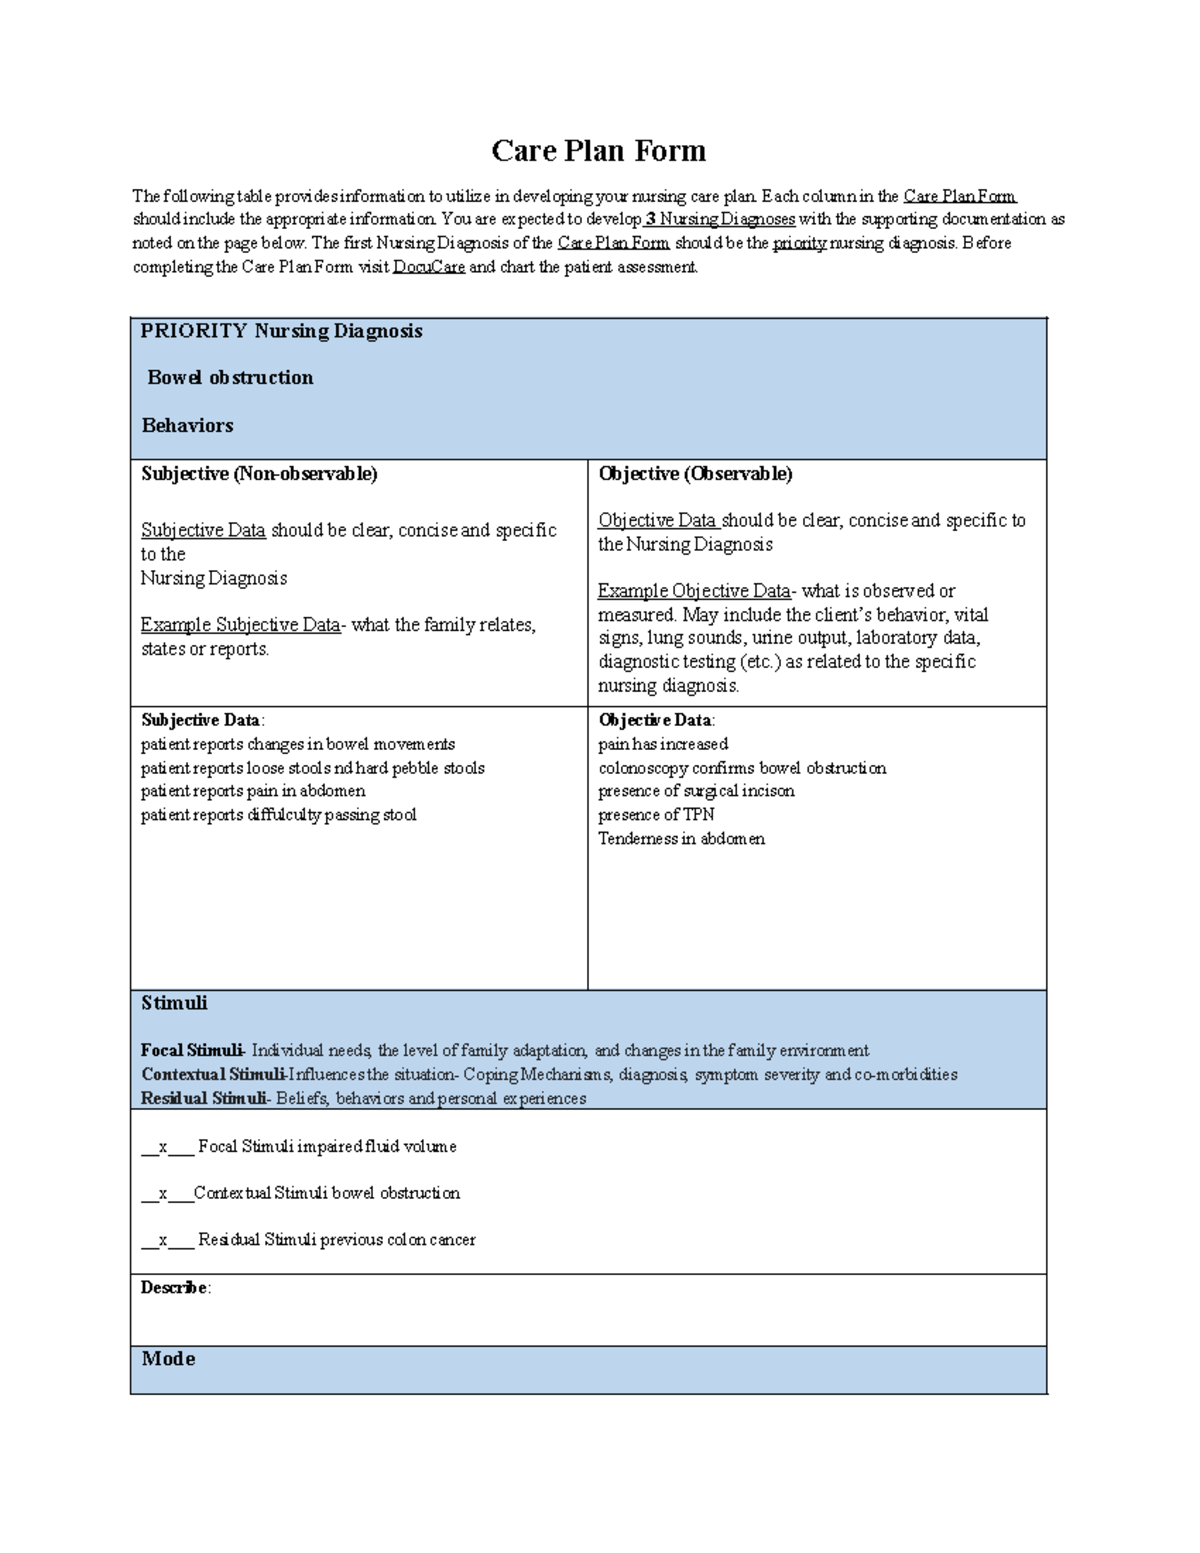
I don't use a single downloadable template. The conditions vary too much between complete and partial obstruction, small bowel and large bowel, simple and strangulated. What I use is a structured framework that covers the domains above, filled in with patient-specific data at the time of admission and revised daily. The framework has five sections: assessment priorities with specific parameters, nursing diagnoses ranked by acuity, interventions with frequency and escalation thresholds, evaluation criteria with timeframes, and patient education milestones keyed to the expected trajectory of their specific condition. If you need a starting point, the core structure works across most bowel obstruction presentations. Customize the fluid rates, the assessment frequencies, and the surgical decision thresholds to match your facility's protocols and your patient's specific lab values and imaging findings. A plan written for a partial adhesive SBO in a 45-year-old looks very different from one for a complete colonic obstruction in a 78-year-old with atrial fibrillation and renal insufficiency. Treat them as different patients with different plans.
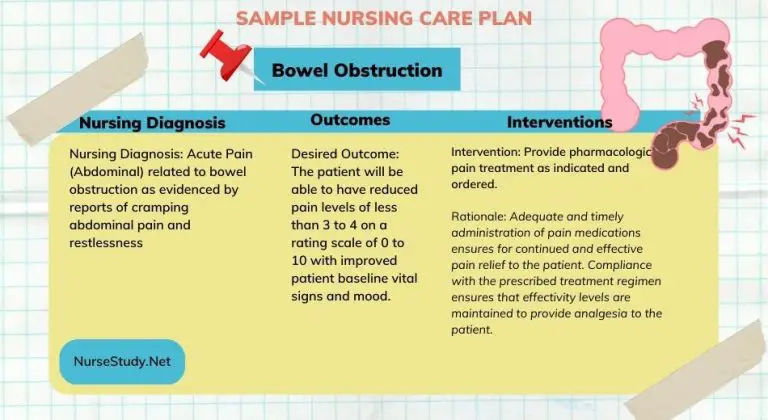
The one thing that stays constant: fluid and electrolyte management is always the priority. Everything else follows from whether that patient is adequately resuscitated or sliding into shock.