What actually moves the bowels in a hospital bed
Most nurses I know approach constipation like a medication problem. The patient hasn't pooped in three days so you give them something and move on. That approach works sometimes. It also leaves a lot of patients uncomfortable and increases the risk of impaction before anyone catches it. I'm going to walk through the practical side of this because the textbook version leaves out a lot of the stuff that actually matters at 2am when you're doing your final rounds and the patient still hasn't gone.
Nursing Interventions For Constipation: Starting With the Obvious
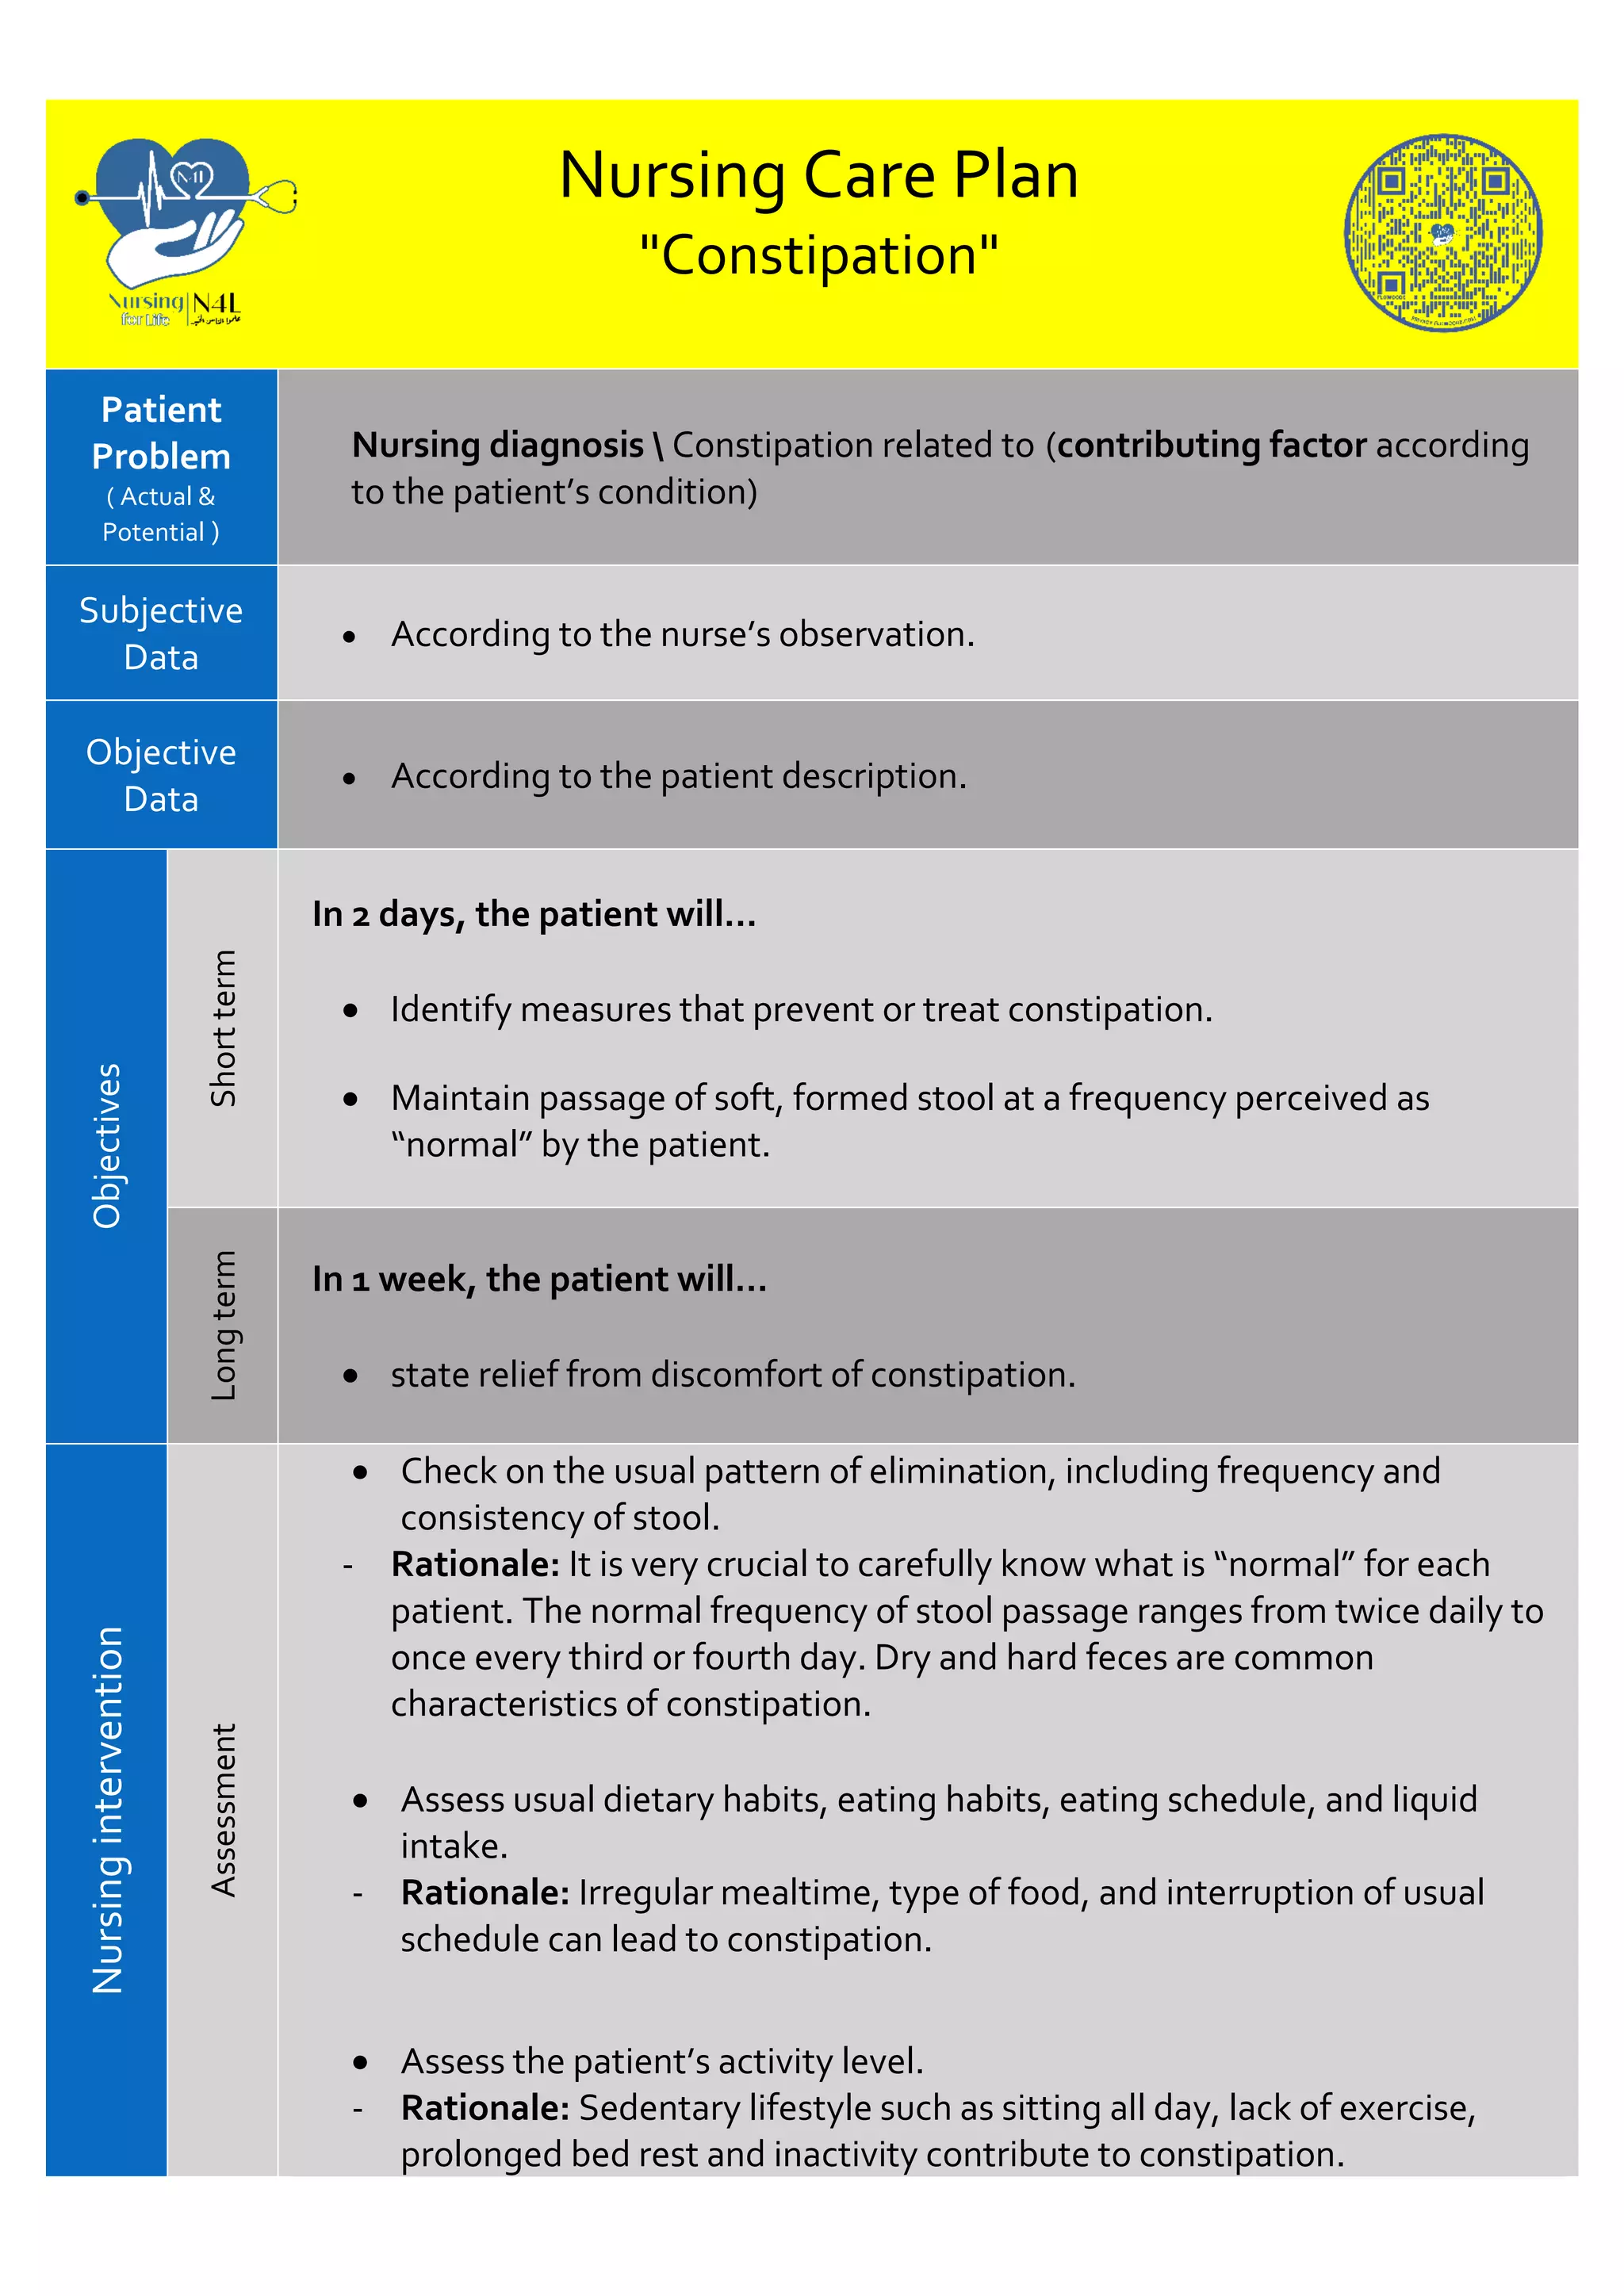
The first thing to check isn't a drug order. It's fluid intake. I had a patient on post-op day two from a hip replacement who hadn't had a bowel movement in four days. Their stool softener order was in the system, but nobody had documented a single ounce of what they'd actually drunk that day. When I pulled the I&O sheet, it came back at 600 milliliters total. We increased their fluids to two liters over twenty-four hours and they passed soft stool the next morning without a single laxative. That's not a special case. Dehydration is the single most common reason nursing interventions for constipation fail on the first attempt. Oral intake documentation is often a guessing game on busy floors, which is why I started personally tracking fluid volumes for any patient who hasn't gone in three days or more.
Building the intervention plan
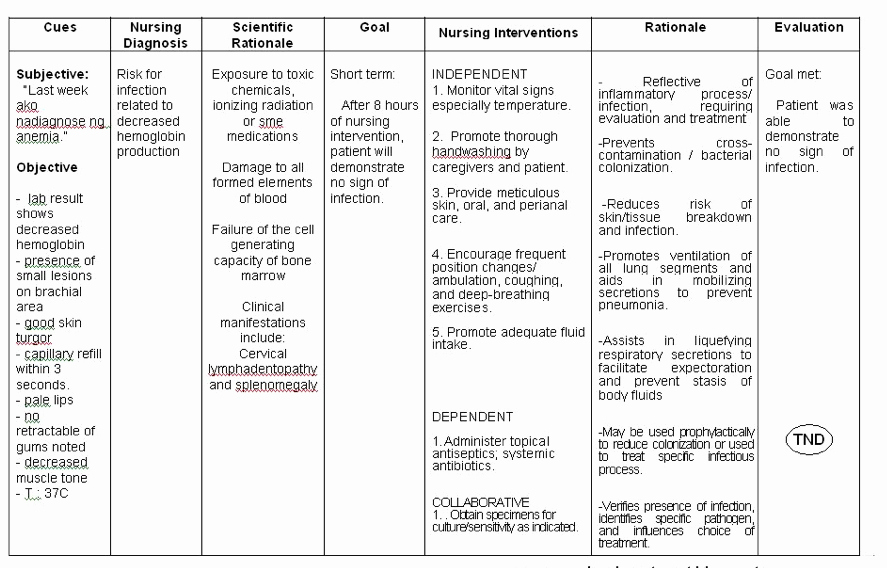
Here's how I approach it now, and it's different from the algorithm most nursing schools teach: Step one is assessment before treatment. Before you touch a laxative order, you need to know the baseline. Listen to bowel sounds in all four quadrants. Palpate the left lower quadrant for fecal mass. Ask about the last normal bowel movement and whether they've felt the urge to go. If the patient has nausea, vomiting, or abdominal distension, hold off on stimulants and get a physician notification in because impaction or obstruction needs to be ruled out first. I learned this the hard way on a med-surg rotation when I gave a patient a bisacodyl suppository and they ended up in the ED with a volvulus the next morning. The patient had been passing gas normally, so I should have caught it sooner. Now I always check for abdominal tenderness and distension before escalating bowel regimen interventions. Step two is diet and mobility. This gets skipped constantly. A patient who is bedbound and eating white bread and jelly is not going to have regular bowel movements regardless of what PRN medications you give them. Advance the diet as tolerated. If the patient can chew, prune juice is genuinely effective. Six to eight ounces in the morning. It's cheap, it works, and patients respond to it better than they respond to senna. Mobility matters just as much. Gravity and peristalsis are connected. A ten-minute walk after breakfast does more for colonic motility than another dose of docusate.
Get the Full Details

Pharmacological interventions
Let's talk about the medications because that's where most of the confusion lives. Docusate sodium is a stool softener. It reduces surface tension so water can enter the stool. It's safe. It's also slow and mild. You're looking at maybe thirty-six to forty-eight hours before you see any effect, if you see any effect at all. Multiple studies have questioned whether it works better than placebo for routine use. I still prescribe it because it's gentle and patients tolerate it well, but I don't rely on it as the primary intervention. Senna and bisacodyl are stimulant laxatives. They irritate the intestinal lining to trigger peristalsis. They work faster, usually within six to twelve hours for oral senna and five to twenty minutes for a bisacodyl suppository. The problem is tolerance and dependency. Long-term daily use can blunt the colon's natural response over months and years, though this is mostly a concern for chronic outpatient users rather than acute inpatients. For short-term inpatient use, they're appropriate and effective.
Miralax (polyethylene glycol) is an osmotic laxative. It pulls water into the colon. It's my go-to for most inpatient cases because it's predictable and doesn't cause cramping. Onset is typically twelve to seventy-two hours orally. The downside is that patients need adequate hydration for it to work properly, which brings us back to step one. There's also a combination product called Senna-S that some facilities prefer. It pairs the stool softener with the stimulant. It's a reasonable middle ground but it's not universally superior to using either agent separately based on clinical judgment.
What nobody tells you about enemas and suppositories
I worked on a unit where we had standing orders for Fleet enemas and glycerin suppositories for any patient with four days of no BM. Within six months, I noticed a pattern: patients who got enemas on schedule actually had more impaction issues than those who didn't. The enemas were treating the symptom without addressing the underlying motility problem, and repeated enema use was causing electrolyte shifts and mucosal irritation in vulnerable patients. The workaround I started using was to reserve enemas for confirmed impaction or pre-procedure preparation, and to use glycerin suppositories only after oral interventions had been trialed for at least twenty-four hours. It's a smaller intervention window, but it keeps the bigger tools available for when they're actually needed. If you do administer an enema, here's the practical part: position the patient on their left side with the right knee flexed toward the chest. This follows the anatomical path of the rectum and sigmoid colon. Lubricate generously. Insert no more than seven to ten centimeters for an adult. Administer the solution slowly. Have the patient hold it for at least five to fifteen minutes if they can tolerate it. And document everything, including the position, the volume, and the patient's response.
Special populations
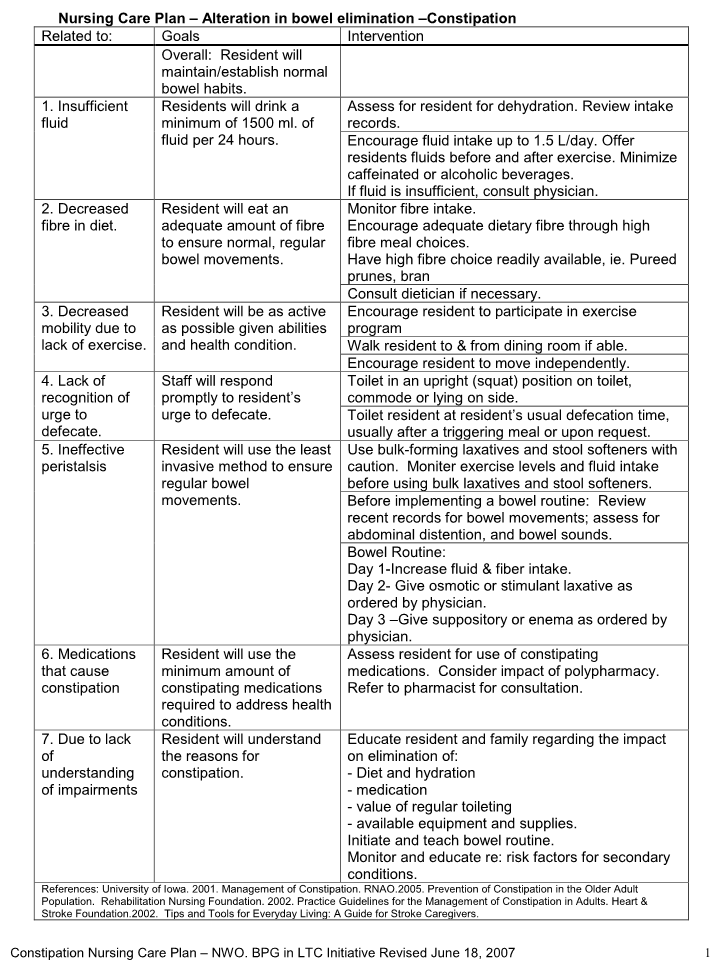
Opioid-induced constipation deserves its own category because the standard interventions often fall short. Opioids don't just slow bowel movements. They bind to mu-opioid receptors in the gut wall and directly inhibit peristalsis. Stool softeners do almost nothing here. Senna helps some patients but often isn't enough. The evidence supports starting a prophylactic regimen the moment opioids are started, not waiting for constipation to develop. PEG 3350 plus senna is a reasonable first line. If that fails, methylnaltrexone or other peripherally acting mu-opioid antagonists exist but require physician oversight and are expensive. Elderly patients present another challenge. Decreased mobility, decreased fluid intake, polypharmacy, and age-related changes in colonic transit time all compound the problem. I've seen patients on eight or nine medications that contribute to constipation, including calcium channel blockers, anticholinergics, iron supplements, and antidepressants. The intervention here is medication review. If you can identify and reduce even one offending agent, you may solve the problem without adding more drugs.
When interventions fail
Sometimes you do everything right and the patient still hasn't had a bowel movement. At that point you need to escalate. A KUB or abdominal X-ray can differentiate between simple constipation and fecal impaction. If impaction is confirmed, digital disimpaction may be necessary before any enema or oral agent will be effective. It's uncomfortable for the patient and unpleasant for the nurse, but it's a standard nursing intervention when conservative measures fail. The biggest mistake I see is continuing to pile on medications without reassessing. If a patient has received multiple laxatives and enemas over seventy-two hours with no result, the problem isn't more medication. The problem is the diagnosis needs to be revisited. Impaction, obstruction, medication side effects, metabolic causes like hypercalcemia or hypothyroidism — these don't get better with more senna.
Patient education that actually sticks
Teaching a patient to drink more water and eat fiber sounds correct until you realize most patients will forget it by the time they leave the room. Be specific. Tell them to drink one glass of water with each meal and one between meals. That's eight glasses minimum. Suggest they keep prune juice at the bedside. For fiber, recommend concrete items like bran cereal or an apple rather than the vague instruction to "eat more fiber." Set expectations about timing. Explain that most oral laxatives take twelve to forty-eight hours to work. Patients get anxious when they don't go within a few hours and demand stronger interventions. Reducing that anxiety with clear timelines actually improves the clinical outcome because patients cooperate better and report symptoms more accurately.

The documentation piece
I can't emphasize this enough because it's where most nurses cut corners. Document the bowel regimen order, the administration times, the type and dose, the patient's response, and the characteristics of any stool passed. Bristol Stool Scale type three or four is the target. Type one or two means the regimen is working but could be optimized. Type five through seven means you've overcorrected. All of this matters for continuity of care and for protecting yourself legally.