Why the Standard Form Fails Before You Even Start Charting
Most nurses I work with spend about 40 minutes on documentation for a single shift change. The problem isn't the writing itself, it is the empty-page paralysis. You stare at a blank flow sheet and suddenly every vital sign, every med pass, every skin assessment needs to be recreated from scratch. That is where a Nursing Template stops being optional and starts being your only defense against a 2-hour charting session.
I built my first one in 2018 after a resident turned in a wound care note that said, "Patient's left heel looked red again." There was no staging, no measurement, no photo reference, no intervention timeline. The charge nurse had to call three people to reconstruct what actually happened. That incident cost our unit a compliance finding that took us four days to resolve. After that I stopped trying to write notes from memory and started forcing everything into a structured skeleton.
Building a Nursing Template That Actually Gets Used
Start with the sections your unit touches most often. Head-to-toe assessment, medication administration, pain scale tracking, skin integrity, falls risk, and discharge teaching. Do not add five more subsections for the rare events. Nobody fills those out consistently, and the ones they skip are usually the ones auditors look for first.
Each section should have a fixed set of prompts, not open fields. "Wound location:" "Wound stage:" "Dimensions in cm:" "Exudate amount:" " dressing type:" Those are the inputs. Everything else is context that belongs in a separate comment box, not mixed into the scoring criteria. I learned that the hard way when our electronic health record flagged a contradiction between my Braden score and my wound documentation because I had combined both into one paragraph. The system could not parse which number applied to which domain.
Keep the language plain. Avoid terms like "erythema" unless your facility specifically requires them for insurance billing. If your documentation goes to Medicare or Medicaid reviewers, they want standardized wording. If it is mostly internal, plain language cuts charting time by about 30 percent. I timed it across three shifts before and after switching from "patient demonstrated poor knowledge of condition" to "patient could not repeat medication schedule after teaching."
One detail that trips people up repeatedly: make sure every template section can stand alone. I used to nest skin assessments under general assessment because it felt organized. But when an auditor pulled a wound care note, they could not find the Braden score without clicking through four layers of collapse. A nurse on night shift should be able to print or expand just the skin section and have all required fields visible. That alone cut my average note time from 12 minutes to roughly 7 minutes for routine shifts.
The Counter-Intuitive Part About Structure
You might think more structure means more work. The opposite is true once you stop treating templates as rigid forms and start treating them as decision trees. A good template forces you to answer a question before moving on. It catches omissions in real time instead of at the end of a 14-hour shift when you cannot remember whether you documented the fall risk assessment.
Here is a pitfall beginners miss: do not make the template too long. I saw a hospital roll out a 28-page nursing template that required 147 checkboxes per shift. Compliance looked great for the first week. By month three, nurses were copy-pasting entire blocks of "N/A" without reading a single field. The audit showed perfect scores and zero actual documentation value. We ended up with a template that was technically complete and substantively empty. That is worse than an incomplete note because it creates a false sense of security.
A practical alternative is the modular template. Build one master structure with 12 core sections, then let each specialty layer in their own sub-sections. Med-surg keeps the standard flow. Oncology adds a chemo-specific module. ICU adds their own. The master still enforces the baseline requirements, but nobody is forced to fill out 15 irrelevant fields just to document a normal vitals check.
Another thing nobody mentions openly: templates create a legal record faster, which means you get sued faster if they are wrong. I had a nurse paste a temperature of 98.6 for three consecutive days because the template remembered the last entry and auto-filled until she caught it. The real temperature was 101.2. She missed the discrepancy because the formatting was identical to previous days. Now I build in a mandatory "confirm against device readout" prompt that cannot be cleared without an explicit acknowledgment. That extra click prevents the copy-forward errors that account for roughly 18 percent of charting mistakes I have seen in our incident reports.
When a Nursing Template Is the Wrong Tool
Not every situation benefits from templating. Rapid declines, code responses, and unpredictable trauma presentations require narrative documentation that captures sequence and clinical reasoning in real time. A template forces you into static fields when what you need is a running log of what changed and why. I use templates for stable chronic patients, medication passes, routine assessments, and discharge planning. For anything unstable, I switch to free-text with time-stamped entries and supplement the template only after the crisis stabilizes.
If your facility does not support conditional logic in the template, do not try to simulate it with hidden sections. Nurses will find a way to click through everything, and then you get the same 28-page problem with different wording. Either invest in a system that collapses sections based on prior answers, or accept that the template will only cover the common cases and keep a separate running narrative field for the exceptions.
The best templates I have used cut documentation time from an average of 45 minutes per shift to around 18 minutes for standard med-surg admissions. That is not a trivial saving. It means one fewer charting error, one less exhausted nurse calling in sick, and one less chance that an audit pulls a note and finds a missing consent form because someone skipped a section out of habit. Templates do not fix bad habits. They just make the gaps visible sooner.
Gallery Nursing Template
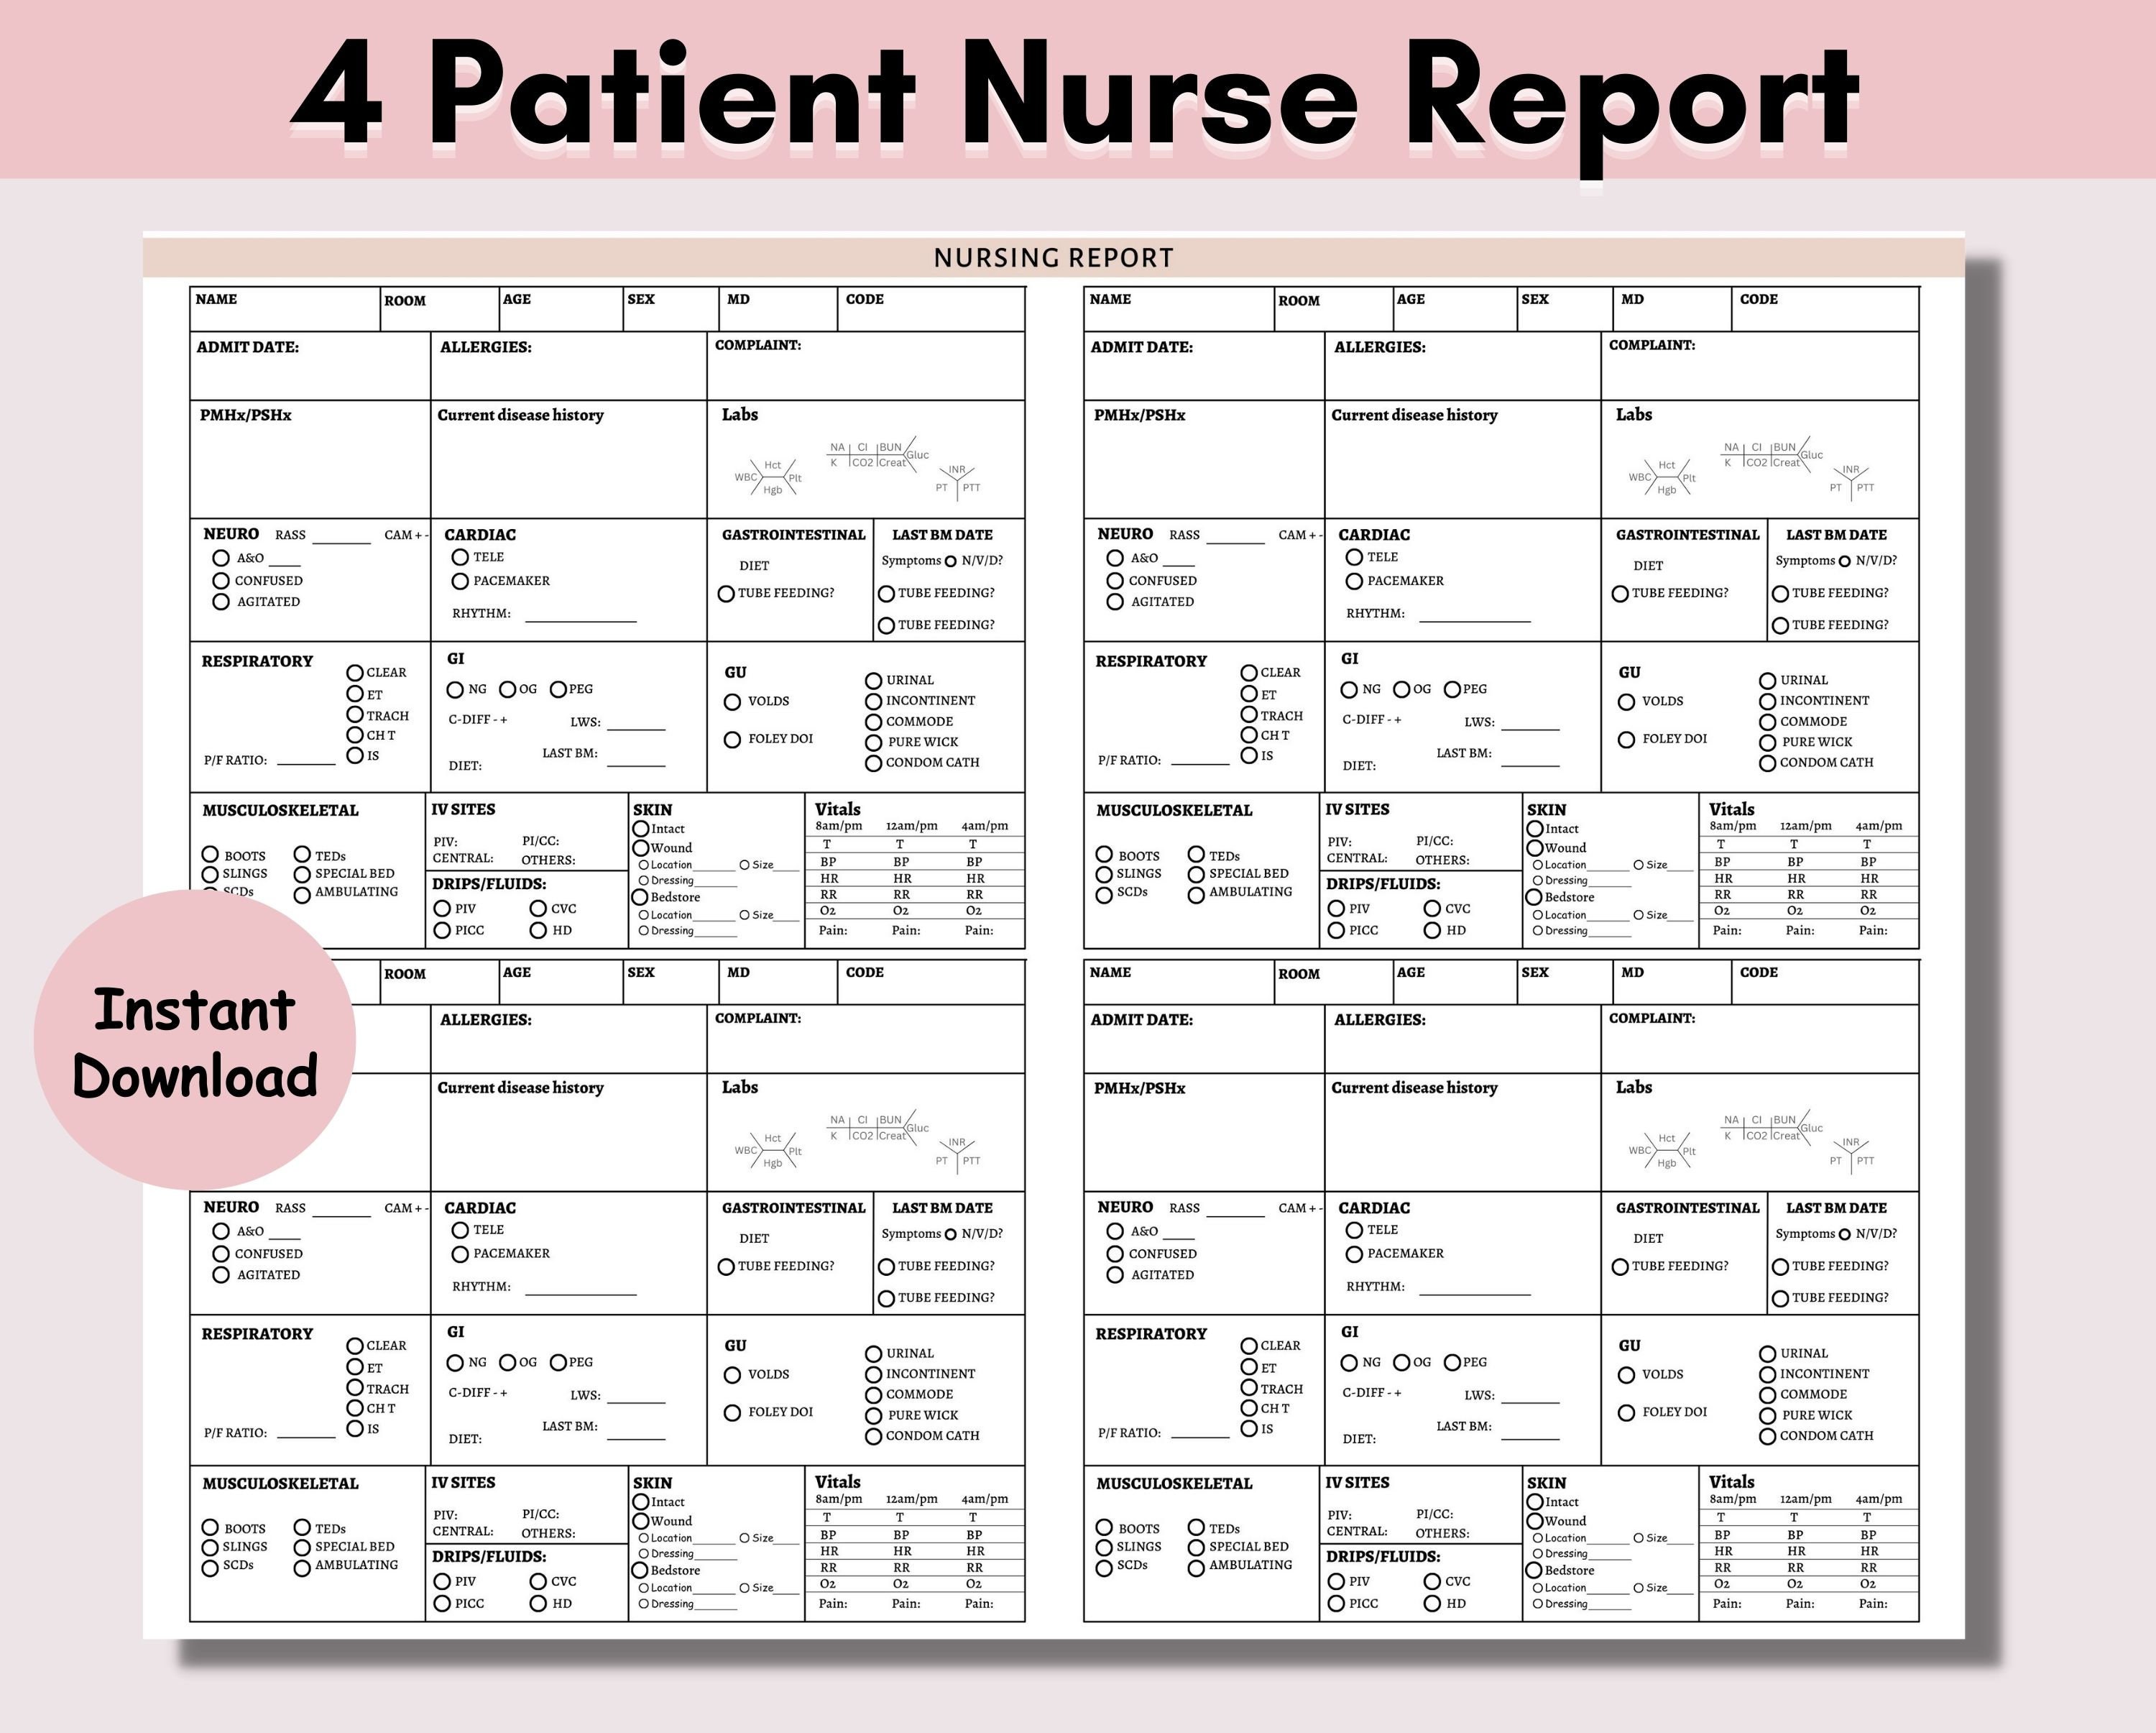
Nursing Charting Template | AT A GLANCE
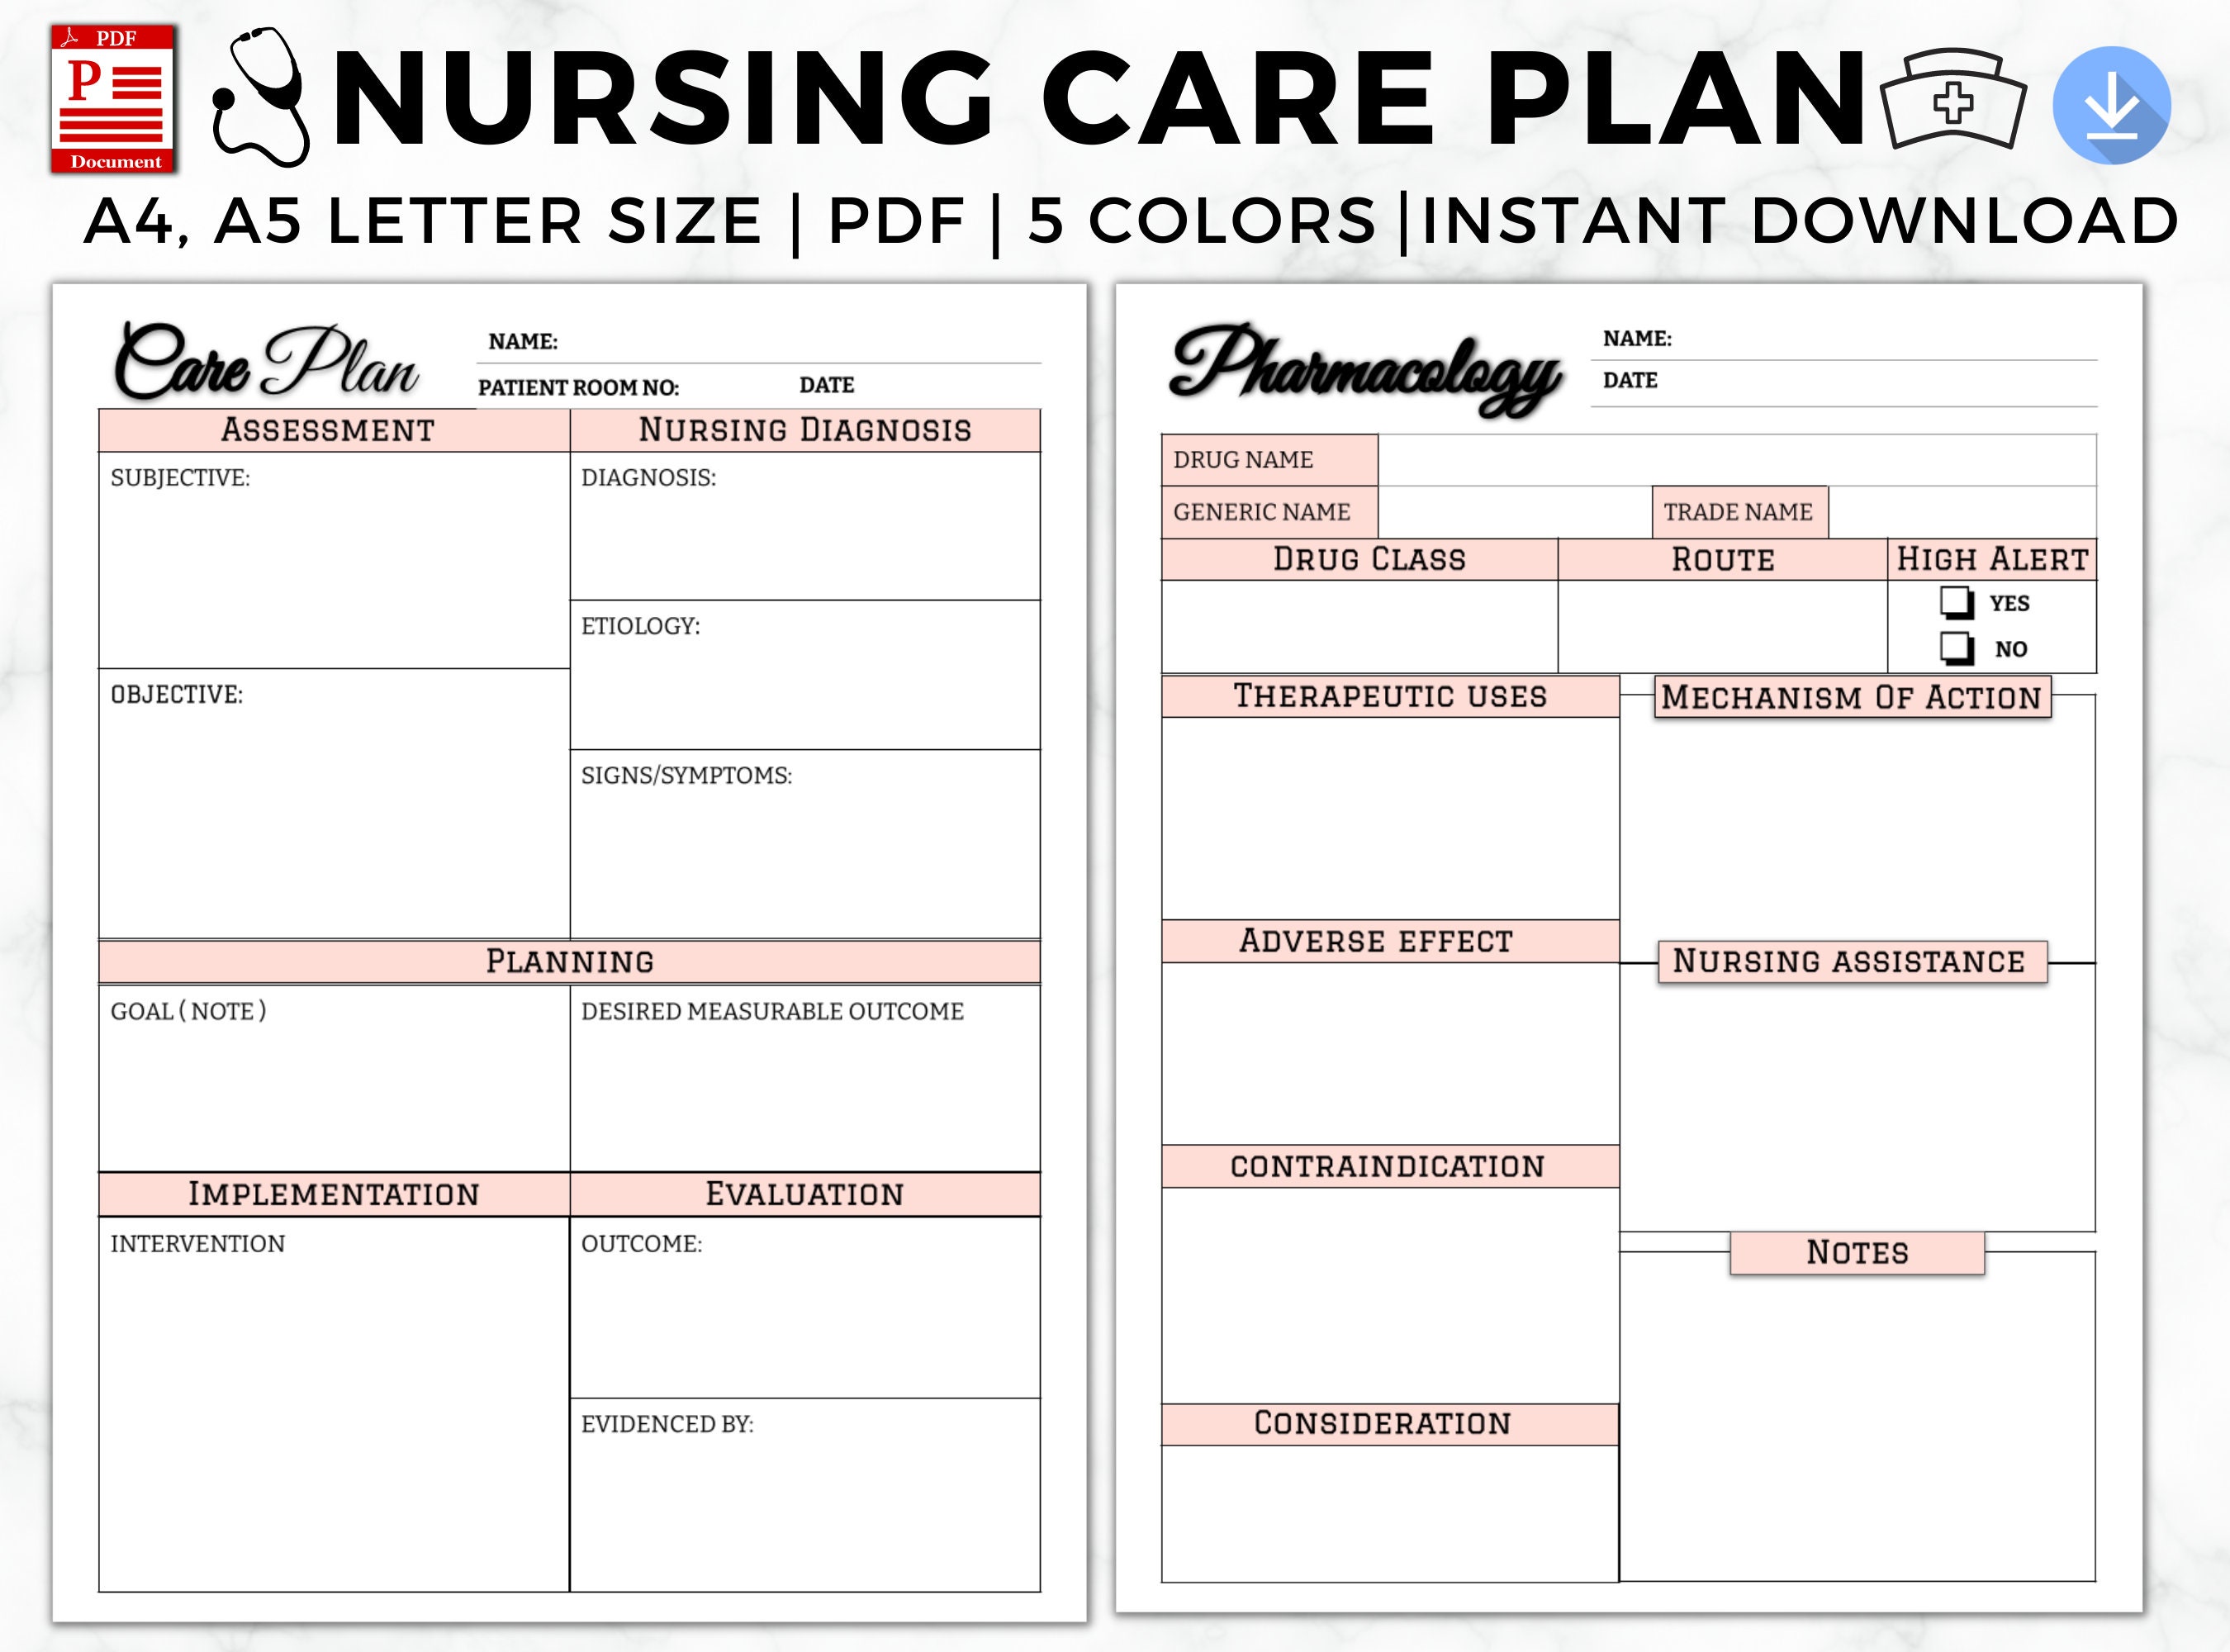
Nursing Care Plan Template - Etsy
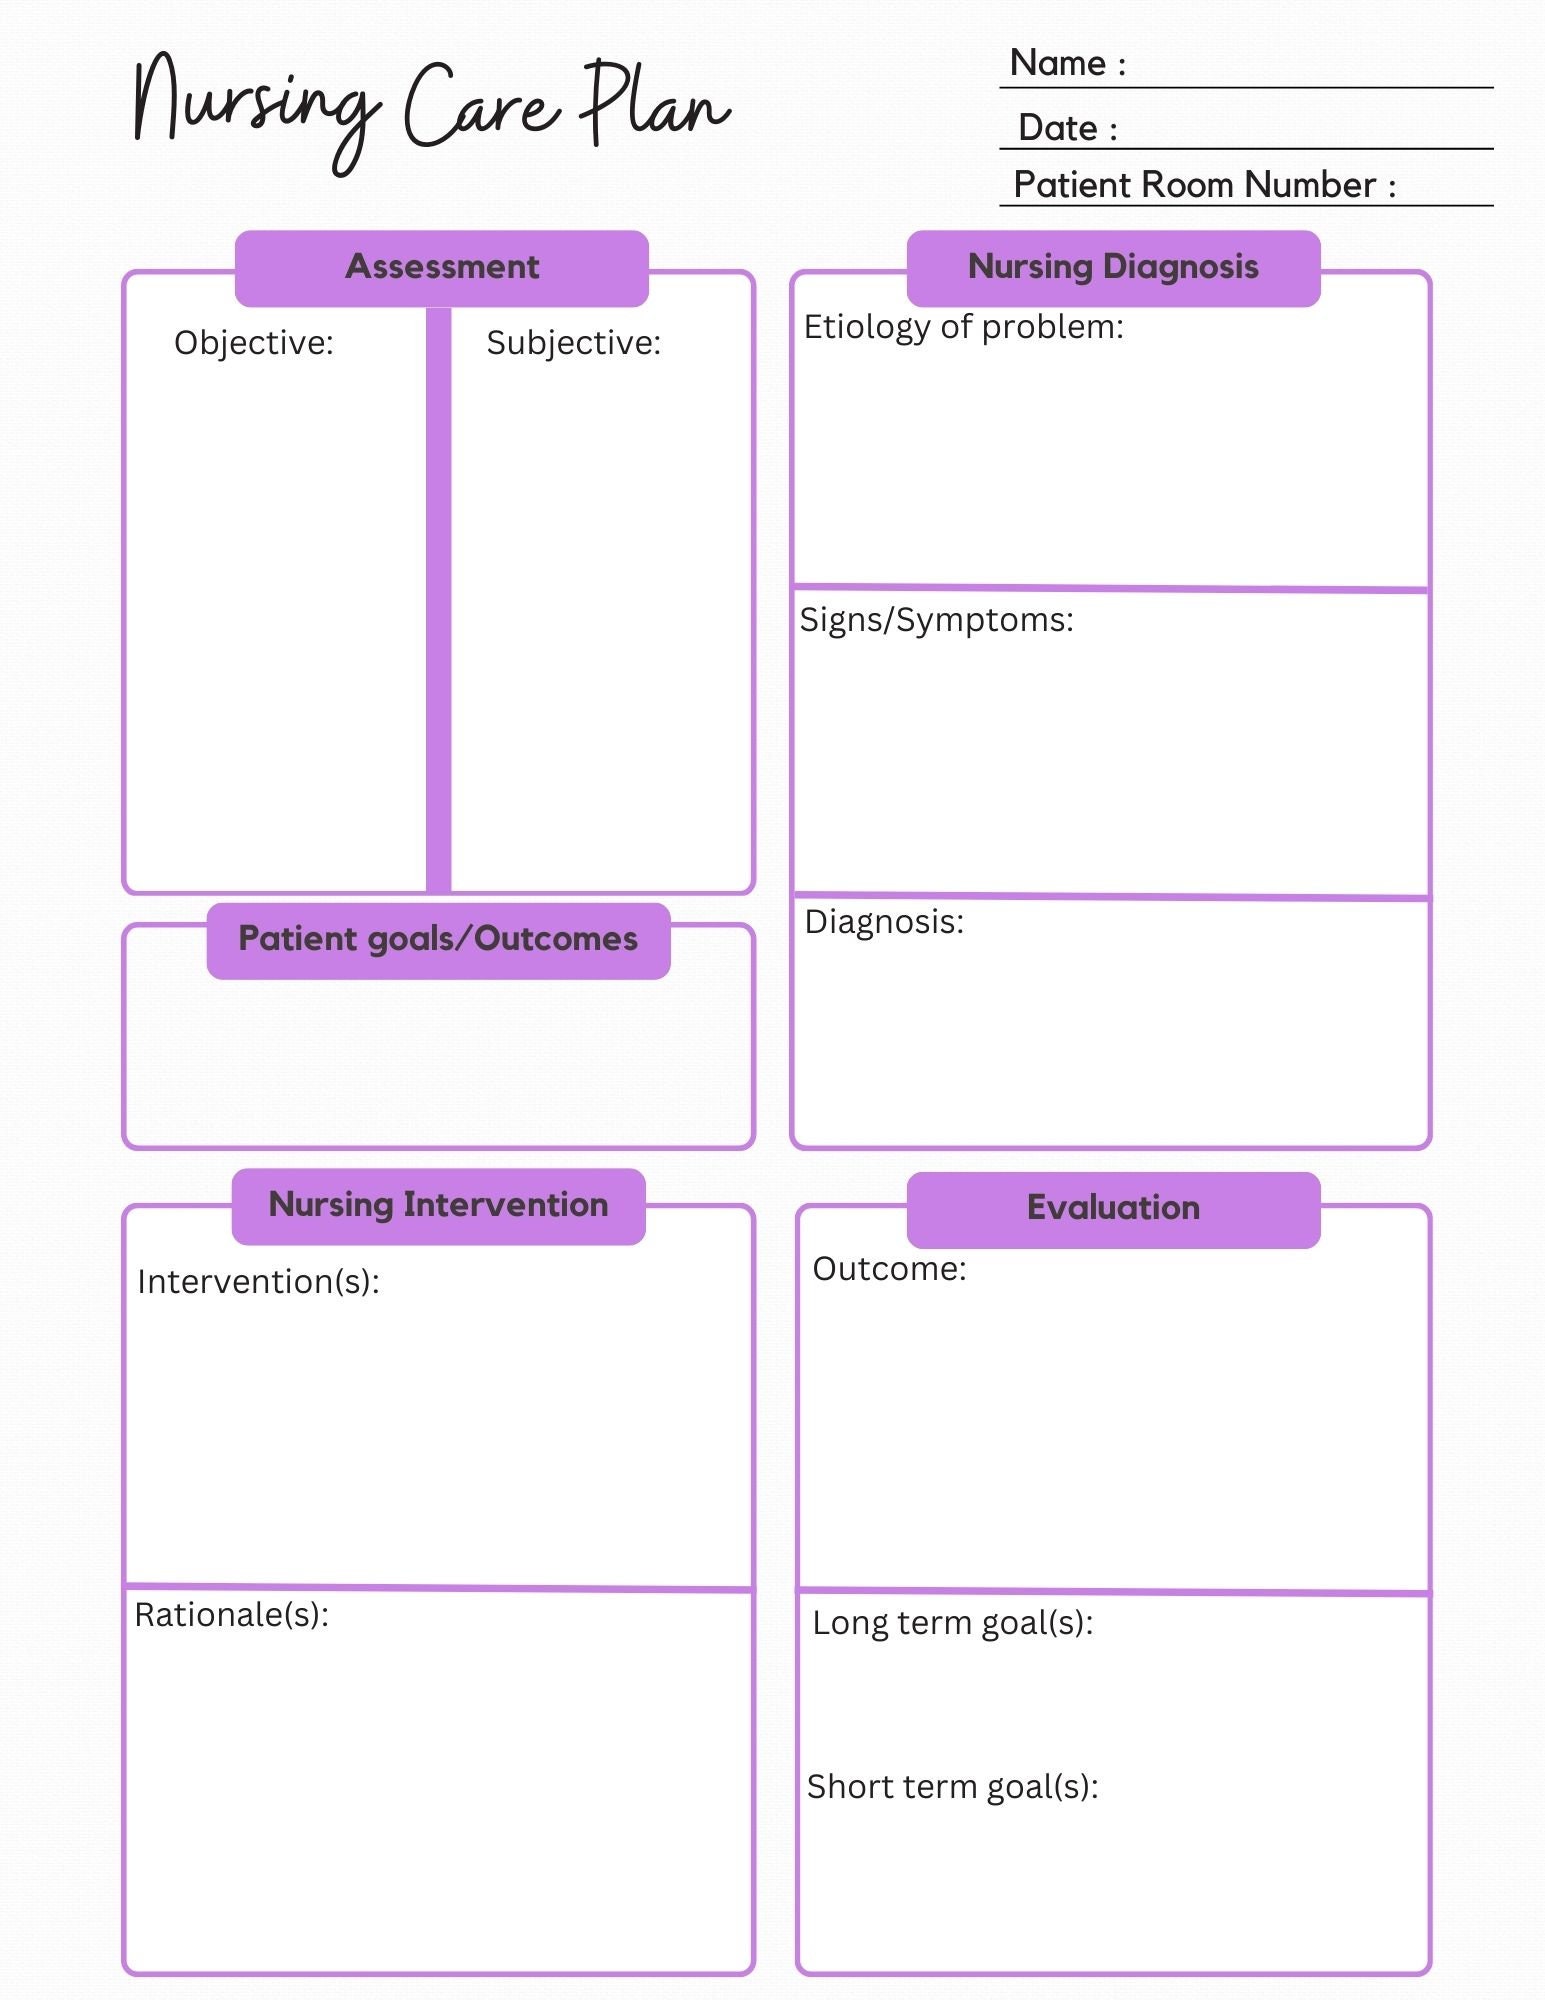
Nursing Care Plan Template Free - Free Printable Templates
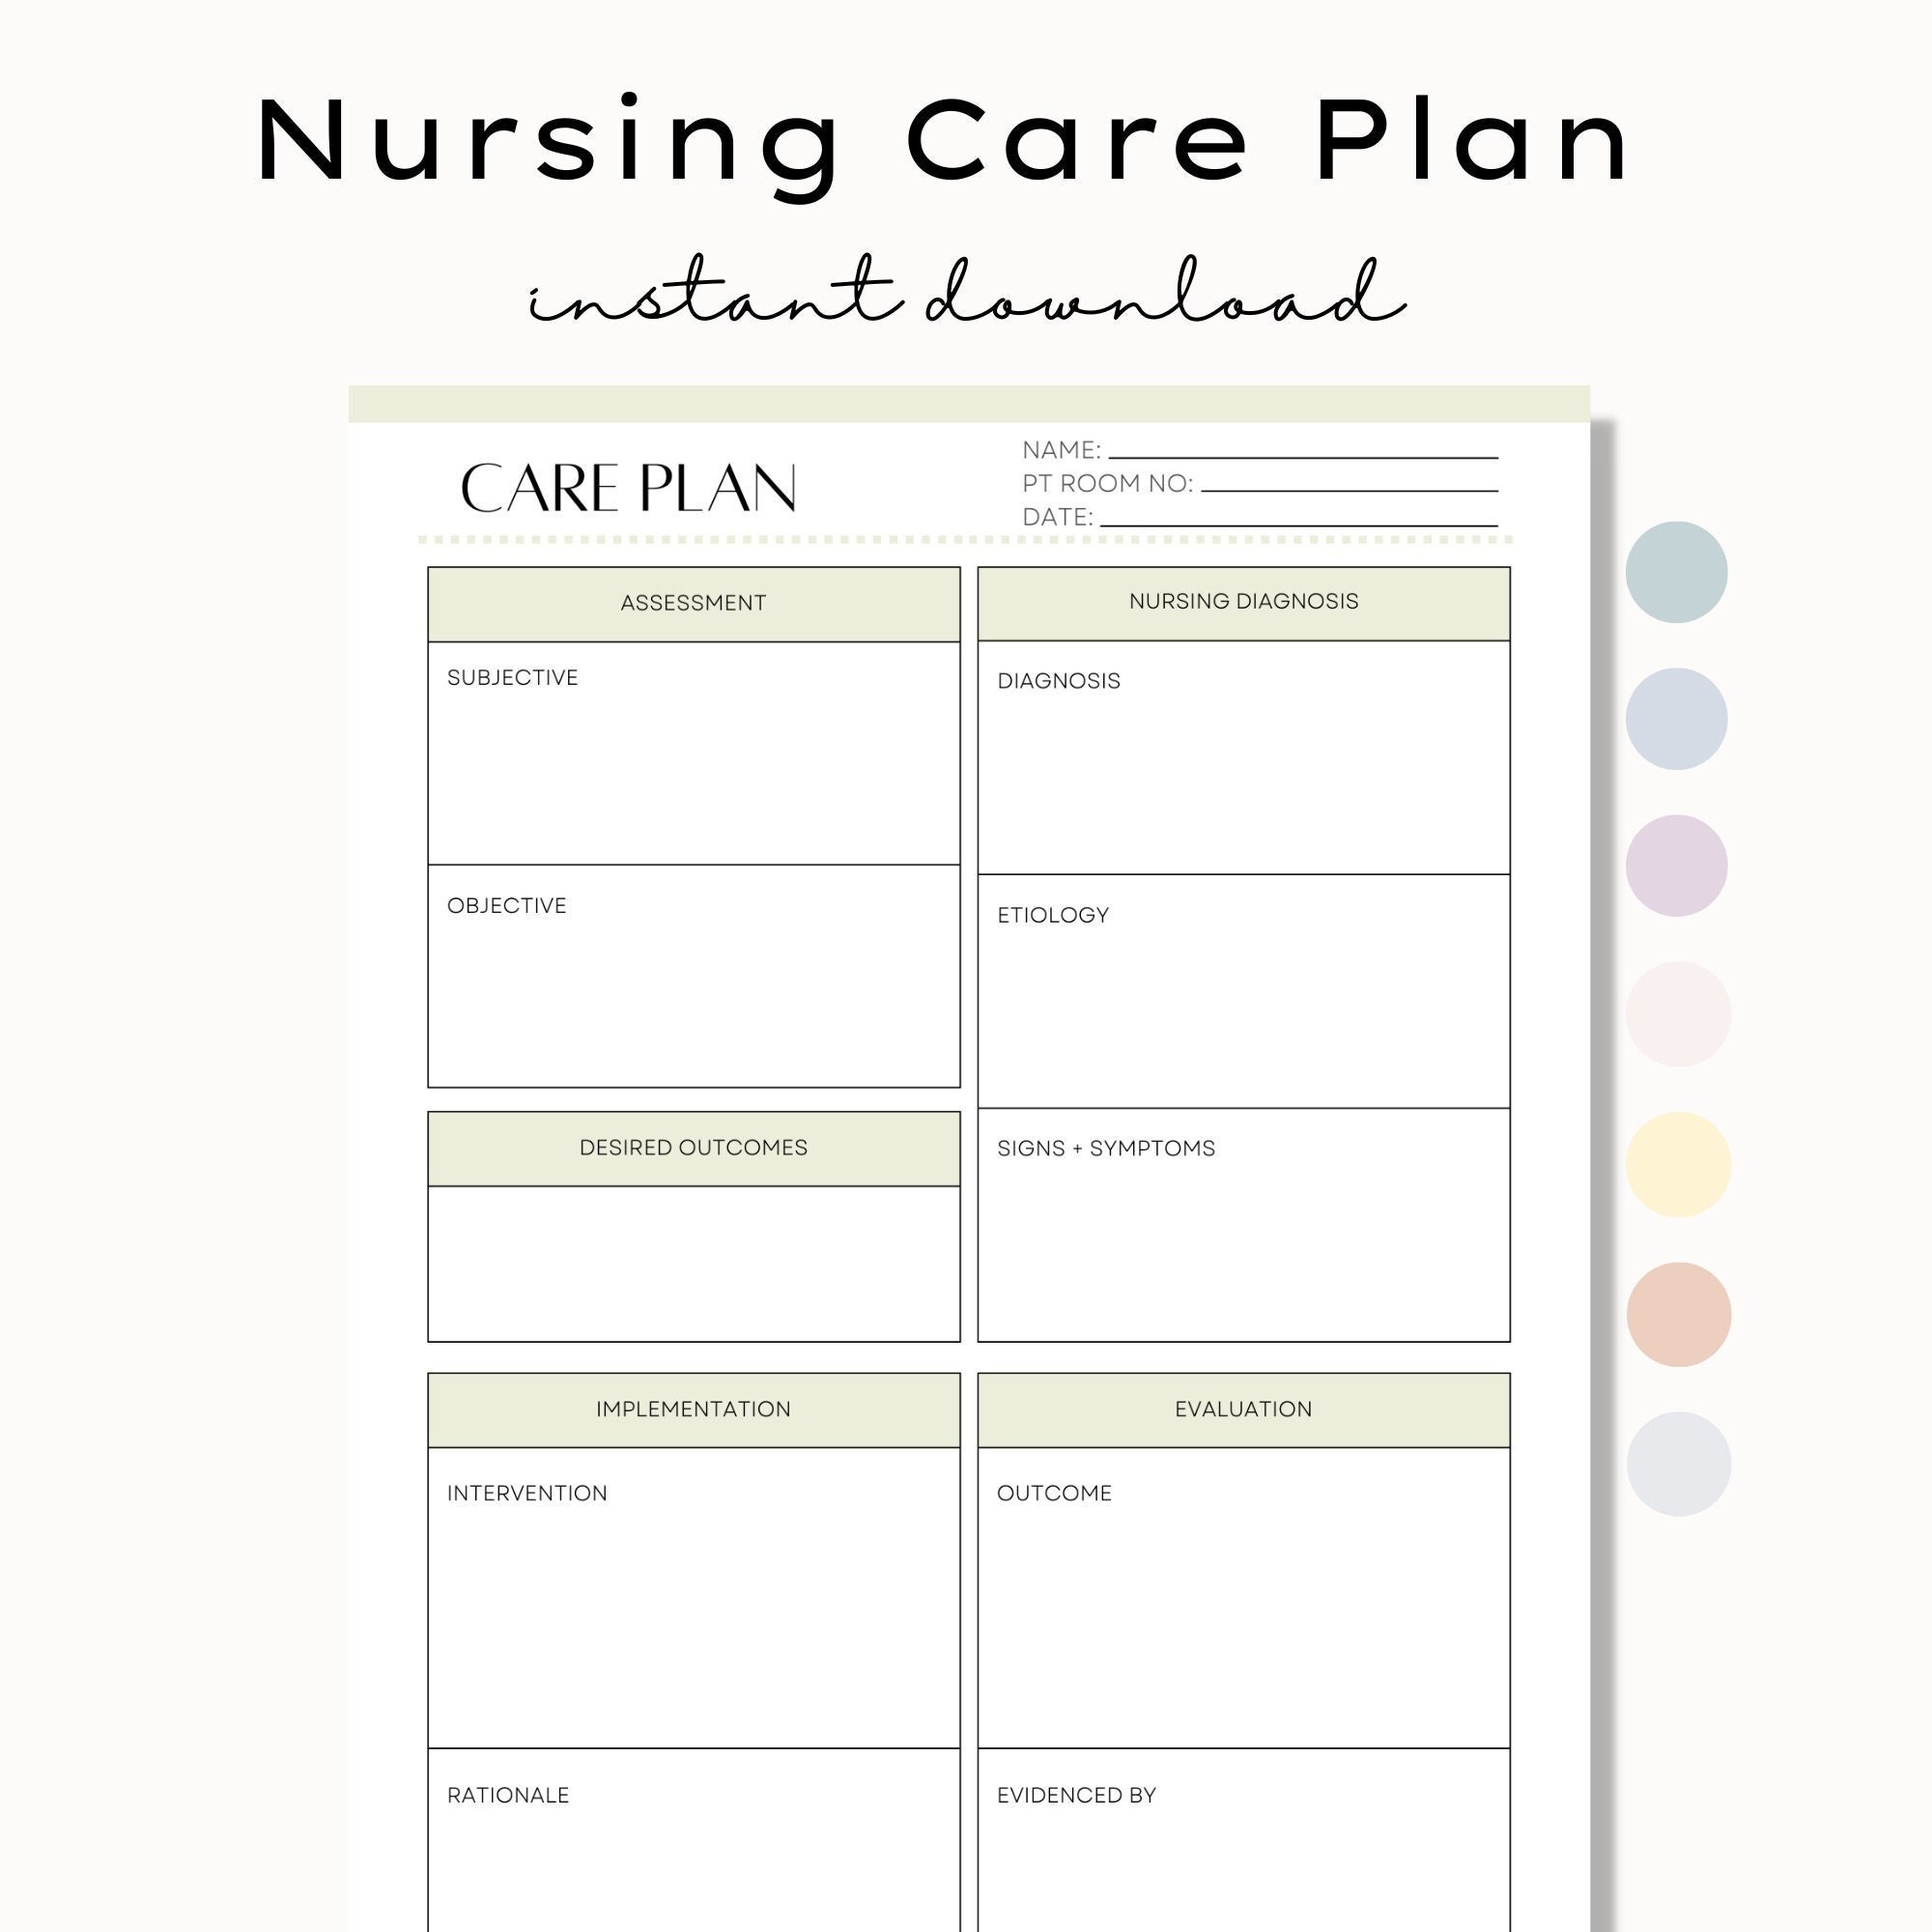
Printable Nursing Care Plan Nursing Care Plan Template - Etsy
Editable Nursing Care Plan Template, Nursing Report Sheet (PDF) - Etsy