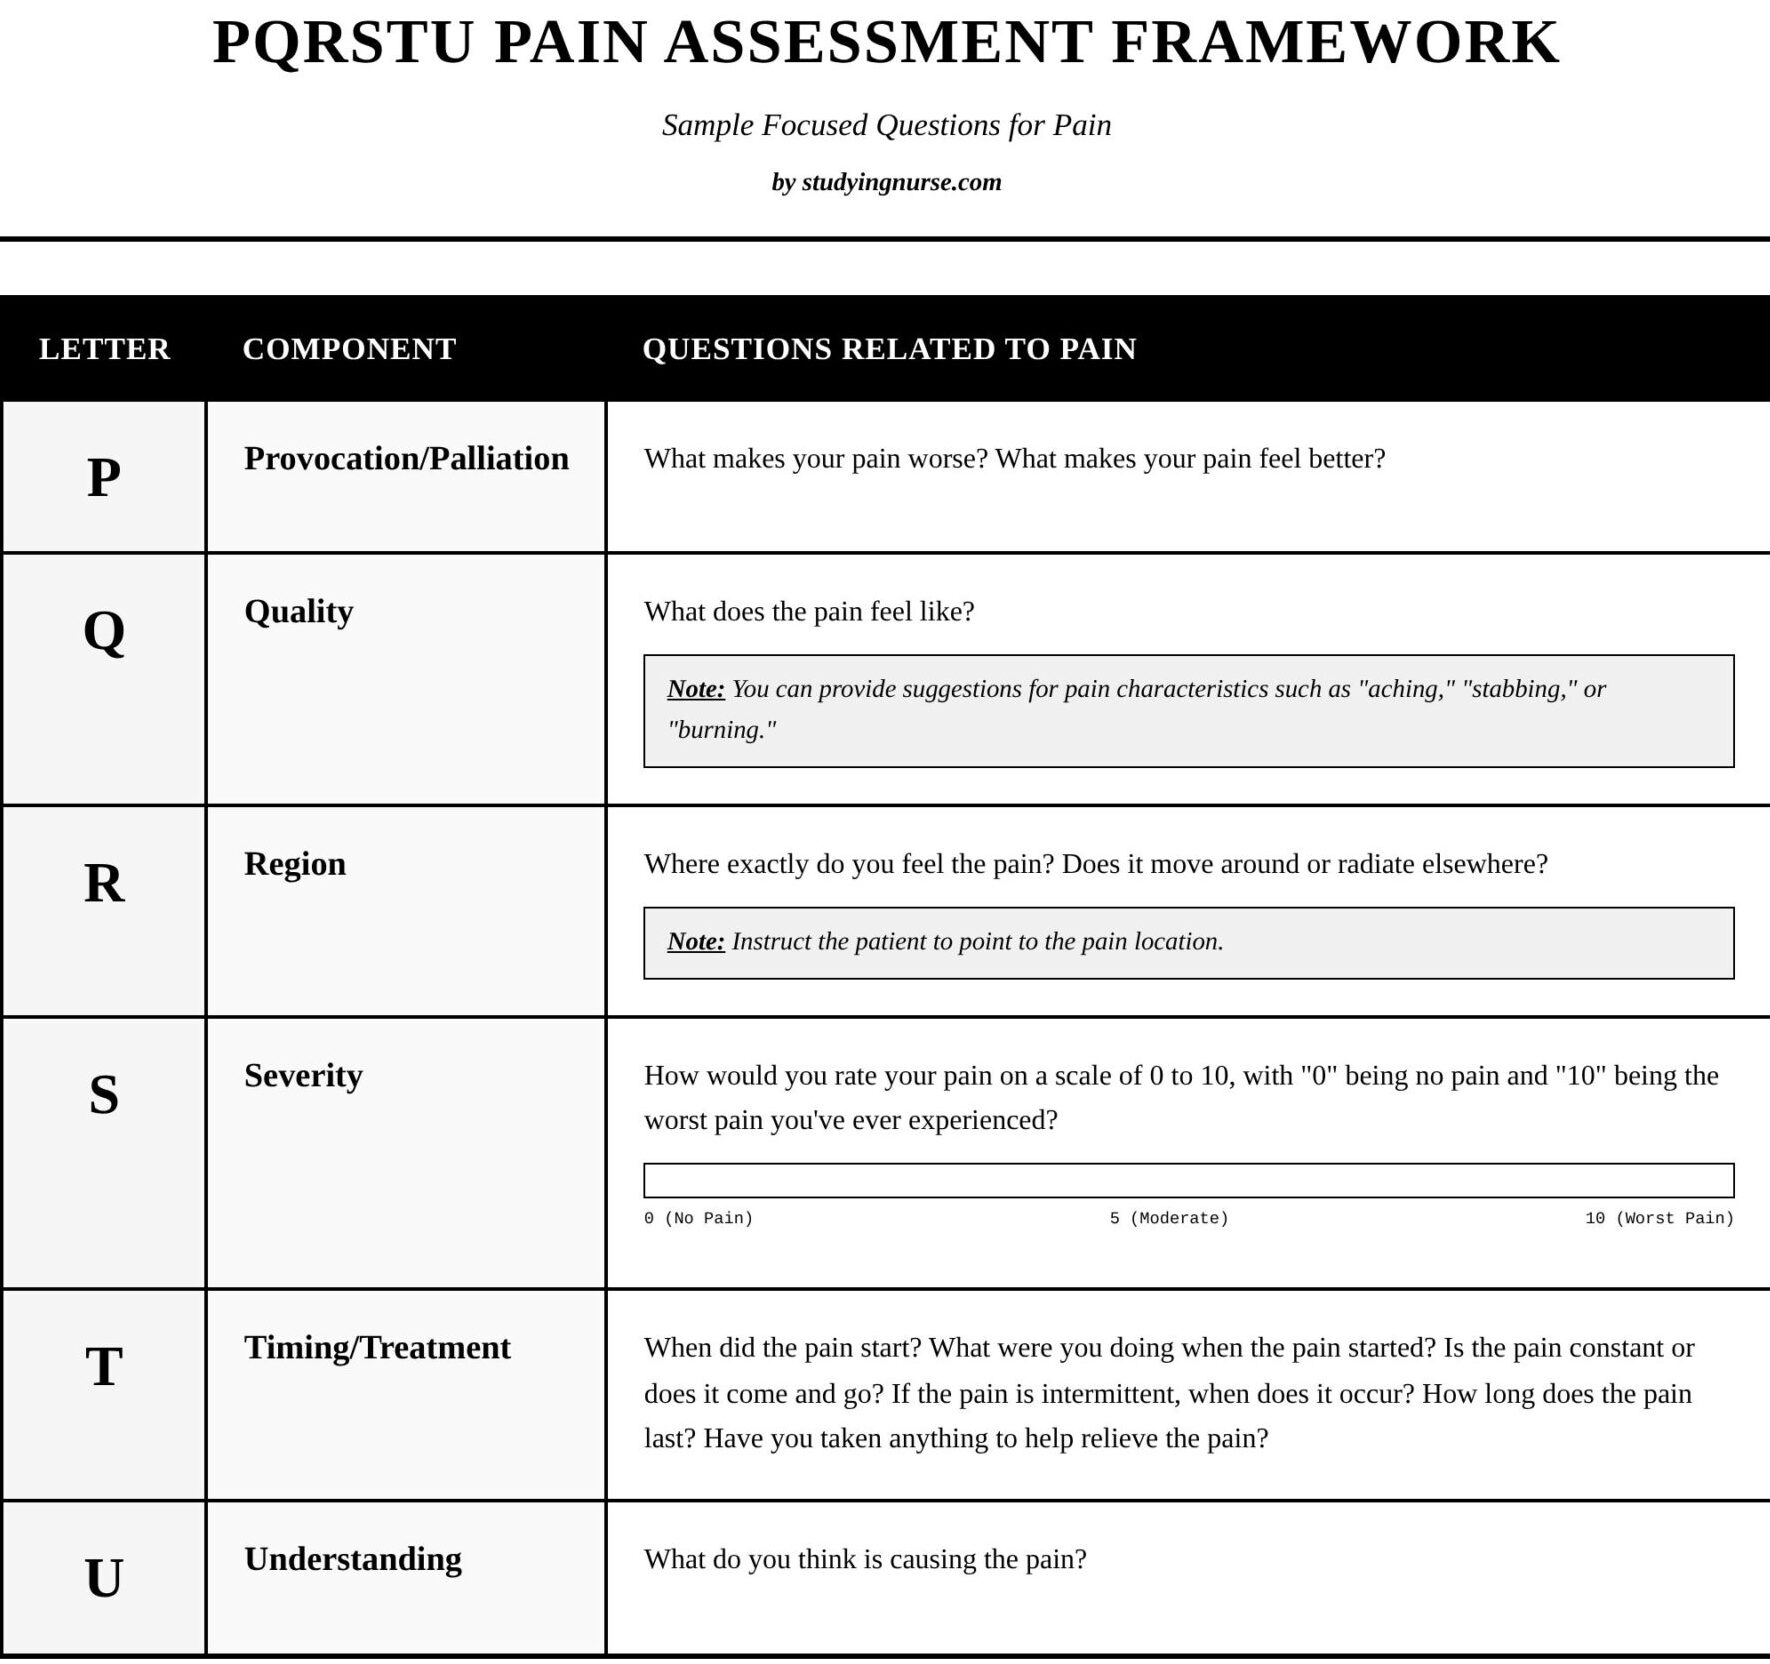
Pain assessment feels like guesswork until you anchor it to a framework most people botch anyway.
I use O P Q R S T Pain Assessment regularly, and the version I recommend includes Onset as the first step, followed by the traditional PQRST letters. That extra O catches timing and situational detail that gets lost when you jump straight into asking about severity. The method itself is straightforward—Onset, Provocation, Quality, Radiation, Severity, and Time—but most clinicians rush through it and miss the parts that actually change management. Here's how I run through it in practice. I ask the patient to describe exactly when the pain started and what they were doing at the moment it began. Then I move to provocation: what makes it better or worse. The quality question is where most people get vague answers. I push for specifics—burning, tearing, crushing, gnawing—and I use those descriptors to differentiate neuropathic pain from nociceptive pain. A patient describing "electric shock" pain along the T10 dermatome is telling you something very different from someone describing a deep, constant ache.
How to actually use O P Q R S T Pain Assessment at the bedside
Radiation follows naturally after quality. I have patients point to where the pain is and then trace where it travels. This single question has saved me from missing referred pain patterns multiple times. Gallbladder issues refer to the right scapula. Cardiac ischemia refers to the left arm or jaw. If I skip this step, I'm relying on the patient's medical knowledge to connect dots they may not have the vocabulary for. Severity stays with a numeric scale, but I always pair it with a functional question: "On a scale of zero to ten, what number would make it hard for you to walk across the room or sleep through the night?" Those self-reported numbers are notoriously unreliable, and I've learned to distrust any score that doesn't change meaningfully across consecutive assessments. Time rounds out the framework. I document onset, I track changes over the assessment period, and I note the temporal pattern—constant versus colicky, morning stiffness versus afternoon worsening. Time tells you whether you're looking at an acute surgical abdomen or a chronic flare that needs a different entirely conversation.
I ran into a real problem once with a post-operative patient who reported a pain score of 4 out of 10 consistently, yet their heart rate was climbing, they were grimacing with movement, and they refused to take deep breaths. Their numbers were calm but their body wasn't. I realized they had been dosed on a fixed schedule and were experiencing breakthrough pain between doses that the numeric scale couldn't capture in a single snapshot. The workaround was switching to serial assessments every 30 minutes and tracking the pain trajectory rather than trusting a single data point. That patient ended up needing a different analgesic approach altogether, not just more of the same medication. The biggest pitfall I see is treating each letter as a checklist item to move through rather than a sequence of clues. When you rush O through T in under two minutes, you miss the connection between onset characteristics and quality descriptors that should be steering your differential. Take the time. The process usually adds about 3 to 5 minutes to the encounter, but it cuts down on misdiagnosis rates significantly, especially in complex presentations where pain is the only symptom the patient can reliably report. There are real limitations to this method that people rarely discuss honestly. The framework assumes the patient can communicate clearly, which immediately excludes people with advanced dementia, intubated patients, or those with significant language barriers unless you have a translator available. Pain is subjective by definition, and inter-rater reliability between clinicians assessing the same patient is notoriously poor. A score of 6 from one patient does not equal a score of 6 from another patient, and no amount of structured questioning fixes that fundamental problem.
Get the Full Details

Cognitive impairment and pharmacological sedation further degrade the reliability of self-report. I've seen opioid-naive patients at trauma centers report low pain scores while showing clear signs of compensatory distress, and I've seen chronic pain patients minimize their symptoms because they assume healthcare providers will dismiss them as drug-seeking. The tool doesn't correct for those biases. If your patient population includes many non-communicative or cognitively impaired individuals, the O P Q R S T Pain Assessment is still worth attempting, but you need to supplement it with behavioral observation tools. The FLACC scale or the PAINAD scale for dementia patients gives you objective behavioral markers that complement the subjective framework. Combining both approaches is more reliable than relying on either in isolation. The other structural weakness is that the framework doesn't account for pain's psychological and social dimensions. It's designed for the physical experience, and while the time component touches on chronicity, it doesn't explore how pain affects sleep, mood, or daily functioning. A brief supplementary question about how the pain is impacting their life usually reveals information that changes the treatment plan more than any detail the framework itself captures.
Practical workflow for running through the assessment efficiently
I start with onset and let the patient describe the event without interruption. Then I move through provocation and quality together since they naturally connect. Radiation comes next, then severity with the functional anchor I mentioned earlier. Time wraps it up. The entire structured interview takes about 4 minutes if the patient is coherent and cooperative, less than 2 minutes if they're in obvious distress and I need to prioritize quickly. For documentation, I keep a template that mirrors the framework but records responses in clinical shorthand rather than verbatim quotes. An example entry looks something like: Onset: sudden, 2 hours ago, during weightlifting. Provocation: worse with movement and palpation, partially relieved by rest. Quality: sharp, localized. Radiation: none. Severity: 7/10, limits ADLs. Time: constant since onset, no episodic pattern. That entry tells another clinician everything they need to know in four lines and creates a baseline for comparison on follow-up. The comparison piece is where the framework actually earns its keep. A single assessment is descriptive. Serial assessments using the same O P Q R S T Pain Assessment structure are analytical. Tracking how the severity number changes after intervention, whether radiation patterns shift, or if the quality descriptor evolves from sharp to dull gives you objective evidence of whether your treatment is working. That longitudinal data is what separates competent monitoring from guesswork, and it's the part of the framework most people underutilize because they only fill it out once during an encounter and never come back to compare.
If you're new to this, practice the sequence aloud until it feels natural rather than mechanical. The goal isn't to sound like you're reading from a form. The goal is to extract information the patient may not volunteer because they don't know what detail matters. Once the framework becomes automatic, you'll notice patterns across patients that make your diagnostic reasoning faster and your treatment decisions more grounded.