
A Practical Guide to Using the PDMS-2 in Pediatric OT
The PDMS-2 is one of those assessments that shows up on every school district's evaluation battery and every private clinic's intake packet. It measures motor development from newborn to age 18. Gross motor and fine motor are the two main categories, each broken into subtests that look at things like posture, balance, locomotion, object control, and manual precision. The scoring gives you standard scores, age equivalents, and a motor quotient that lets you compare a child to their peer group. You do not need a special certification to administer it, though the manual is about 500 pages and most people never read all of it cover to cover. I bought the kit in 2014 and have used it maybe forty times since then. Here is what actually matters when you open that box. When people search for Peabody Assessment Occupational Therapy, they are usually looking for either how to administer the PDMS-2 in a clinical setting or how to interpret the results for treatment planning. The test itself was never designed specifically for OT. It was built by developmental psychologists. That distinction matters more than you might think. An OT using the PDMS-2 is borrowing a psychometric tool and applying it to a clinical population that often does not fit the normative model. A child with cerebral palsy, a child with autism, a child who had a traumatic brain injury at age six. The norms on the PDMS-2 are based on typically developing children. Applying them blindly can give you numbers that look accurate but actually tell you very little about functional ability. The PDMS-2 has six gross motor subtests: reflexive and postural responses, balance, locomotion, ball skills, strength and transit, and reaction and agility. The fine motor subtests are grip, manipulation, and manual precision. Each subtest has items arranged in hierarchical order. If a child fails an item, you work backwards until you find where they start passing consistently. That becomes the starting point for that subtest. Then you go forward until they fail a certain number of consecutive items. The protocol tells you exactly when to stop. The manual is precise about this. Most clinicians I know just wing it on the backward stopping rule and guess. That is a bad habit.
The fine motor section alone takes roughly 20 to 30 minutes for a cooperative child. Gross motor can take another 30 to 45 depending on age and mobility level. Total testing time is usually between 60 and 90 minutes for a full administration. You need the kit, which includes weighted balls, beanbags, miniature obstacle courses, pegboards, scissors, crayons, and various other items. The kit costs around $400 to $500 depending on whether you buy used or new. The manual and scoring sheets run another $150 or so. If your funding source reimburses at a low rate, these materials eat into your margin pretty quickly. One thing nobody tells you during training: the ball skills subtest on the gross motor side is where most assessments fall apart. Not because the items are hard. Because the environment matters enormously. You need a space that is at least 20 feet by 30 feet with smooth flooring and no obstacles. If you are testing in a crowded therapy gym with kids playing basketball nearby, the ball skills subtest is going to produce garbage data. I learned this the hard way in 2017 when a six-year-old scored in the 2nd percentile on ball skills despite being able to throw, catch, and kick proficiently during regular OT sessions. She just could not focus in a chaotic environment. We rescheduled to an empty room on a Saturday morning and her score jumped to the 45th percentile. The child had not changed. The conditions had. Interpreting the results requires understanding what a standard score actually represents. A standard score of 100 is the mean. Sixty-eight percent of children fall between 85 and 115. Below 70 is considered significantly below average. Between 70 and 84 is borderline. This is basic psychometrics, but it is worth emphasizing because I have seen many reports where clinicians write "significant delay" for a child who scored 72 on one subtest and 88 on another. Those are borderline scores. They do not support a diagnosis of significant delay on their own. The motor quotient combines all the subtests into one number. It is useful as a quick reference but it obscures the profile. Two children can have the same MQ but completely different patterns of strength and weakness. Always report the individual subtest scores alongside the MQ.
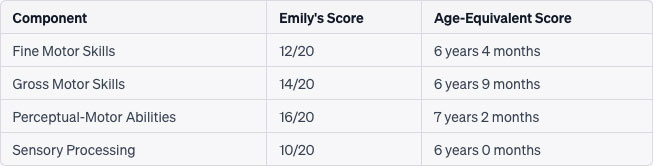
The age equivalent scores are the most misused numbers in the entire instrument. They sound intuitive. A seven-year-old scoring at an age equivalent of five years and three months. Seems clear. But age equivalents have no standard deviation attached to them. They are not statistically valid for making clinical decisions. If a child is on the borderline of passing an item, the age equivalent can swing by months depending on which direction they tip. I once saw a report where a half-point difference on one item changed the age equivalent by four months. That swing meant nothing clinically. It was pure noise. Stick with standard scores and percentile ranks. Age equivalents belong in the narrative description of what the child can do, not in the statistical summary. For children with physical disabilities, the PDMS-2 has significant limitations. The locomotion subtest includes running and hopping. A child who uses a wheelchair or has spastic diplegia will not be able to complete these items regardless of their true motor capacity. The test does not provide alternate items or accommodations within the standard protocol. Some clinicians skip the affected subtests and calculate a partial score, but the manual explicitly warns against this. There is no published validity for partial administrations. The safest approach is to use the PDMS-2 as one piece of data alongside functional assessments like the GMFM or the FMS. The PDMS-2 tells you about developmental motor milestones. It does not tell you about functional mobility in the child's actual environment. Re-teaching and transfer effects are a real problem that most administrators ignore. The PDMS-2 items are repeated across subtests in slightly different forms. A child might see a ball-throwing task in the ball skills subtest and then encounter a similar throwing task in the strength and transit subtest. If they practiced throwing during the first subtest, their performance on the second will be artificially inflated. I have started noting which items involved similar movements and flagging potential practice effects in my reports. It takes an extra five minutes and it prevents reviewers from questioning inflated scores.
Get the Full Details
The visual-motor integration component is where fine motor precision gets assessed. The copy subtest asks children to reproduce geometric shapes. The match subtest requires matching lines to printed patterns. These items correlate strongly with handwriting readiness and visual perception skills. OTs should pay attention here because a low score on visual-motor integration often predicts handwriting difficulty even when grip strength and dexterity look normal. I have found that combining PDMS-2 fine motor scores with the Beery VMI gives a much clearer picture of what is actually driving a child's writing challenges. The PDMS-2 alone leaves a gap. Scoring is straightforward if you follow the protocol exactly. Each item is scored as pass or fail. There is no partial credit. The raw score converts to a standard score using tables in the manual. There are separate tables for chronological age and for mental age when the mental age is significantly lower than chronological age. The second edition introduced this Mental Age Adjustment for children whose cognitive delays might suppress their motor scores. If the child's mental age is more than 24 months below their chronological age, you use the mental age tables instead. This adjustment was added in the PDMS-2 specifically to address criticism of the original PDMS. It is a meaningful improvement and most clinicians still miss it. Reliability data for the PDMS-2 is generally good but not uniform across all subtests. Test-retest reliability ranges from 0.85 to 0.95 for most subtests. Inter-rater reliability is around 0.90. These are solid numbers. The exception is the manual precision subtest, where reliability drops to approximately 0.78. Scoring subjective quality of movement introduces variability. Two trained raters might disagree on whether a grasp pattern is efficient or compensatory. If you are doing research or participating in a multisite study, you need formal inter-rater calibration before administering the test. Just completing the online scoring course does not guarantee agreement with other testers.
The biggest practical complaint about the PDMS-2 is the time investment relative to reimbursement. In many states, an OT can bill for one hour of direct assessment but the PDMS-2 plus scoring plus report writing routinely takes three to four hours of actual clock time. If your rate per unit does not account for that, you are losing money on every PDMS-2 administration. Some clinics get around this by having a technician set up and manage the materials while the OT focuses solely on scoring and interpretation. This cuts the total time by about a third but it requires a skilled support person who knows the protocol well enough to handle the equipment without influencing the child's performance. There is also the issue of floor and ceiling effects. Younger children under 36 months tend to score at the floor on several fine motor subtests because the items assume a level of hand-eye coordination that simply has not developed yet. Older children and adolescents tend to hit the ceiling on basic locomotion and balance items. The PDMS-2 stops at age 18 but the upper range of the normative data is thin for teenagers. A 16-year-old with a motor disability scoring in the 90th percentile is essentially indistinguishable from a typically developing peer on this test. The assessment loses discriminative power at both ends of the age spectrum. If you need a motor assessment that covers the full lifespan with better functional relevance, the Bruininks-Oseretsky Test of Motor Proficiency second edition (BOT-2) is a reasonable alternative. It has a longer age range, better ceiling for older children, and a separate brief form that takes about 15 minutes. The BOT-2 also includes a coordination quotient that is more informative than the PDMS-2's single motor quotient. However, the BOT-2 requires a separate certification to purchase and administer, which adds cost and administrative overhead. The PDMS-2 remains the more accessible option for clinicians who need a motor assessment without additional credentialing barriers.
The scoring software that comes with the PDMS-2 is functional but dated. It runs on Windows and the interface looks like it was designed in the early 2000s. It does what it needs to do. It calculates standard scores, age equivalents, percentiles, and motor quotients from your raw scores. It also generates a printed report template that you can customize. The main frustration is that the software does not auto-populate from scanned protocols. You still have to type in every raw score manually. If you have 30 subtests with 20 to 30 items each, that is roughly 600 to 900 data entry points per administration. I time myself and it takes about 15 minutes. Not terrible, but not negligible when you are running a high-volume clinic. Documentation quality matters more than most clinicians realize. Insurance reviewers and school IEP teams do not care about your clinical impressions. They care about the numbers. A well-written PDMS-2 report includes the chronological age, the mental age if applicable, each subtest standard score with percentile rank, the gross motor and fine motor standard scores, the motor quotient, and a clear statement of how the results relate to functional outcomes. Mentioning that a child scored in the 15th percentile on manual precision and therefore requires adapted utensils for self-feeding is far more useful than stating the child has fine motor delays. Specificity wins every time in review. The PDMS-2 is a solid tool for what it does. It is not a comprehensive occupational performance assessment. It does not measure sensory processing, Activities of Daily Living, play skills, or social participation. Using it as a standalone evaluation is a mistake. Pair it with something like the Sensory Processing Measure or the Pediatric Evaluation of Disability Inventory and you get a much more complete picture. The PDMS-2 tells you about the hardware. The other assessments tell you about the software running on it.


