What Actually Happens in Hand OT After an Injury
Most people think occupational therapy for hand injury is just exercises and some passive modalities. That's not what it looks like after you've sat through enough sessions to recognize the difference between effective treatment and billable theater. The real work starts with understanding what was damaged, how the body is compensating, and where the movement is actually getting stuck. I'm going to walk through what this looks like in practice, including the parts that usually get skipped in patient handouts. There's a specific case I dealt with recently that shows why the textbook approach doesn't always work, so I'll get to that.
Assessment Comes Before Any Intervention
Before you touch a therapy table or hand out a splint, you need a clear picture of the injury. Range of motion measurements matter, but what matters more is identifying which tissues are actually limiting movement. Is it the joint capsule? Scar tissue? Tendon adhesion? Muscle tightness? These all look the same from the outside but require completely different approaches. I measured ROM on a patient last month who had sustained a laceration to the volar aspect of their index finger near the PIP joint. The wound had healed, but they couldn't flex past 45 degrees. Standard protocol would suggest scar mobilization and stretching. But when I palpated the area, I found a distinct step-off about two centimeters proximal to the incision site. That wasn't just scar tissue. It was a flexor tendon nodule at the repair site that was physically blocking glide. Stretching that would have just aggravated the repair. We needed tendon gliding exercises first, then later progressive loading once the nodule softened. Got that wrong and you're either making things worse or wasting weeks of recovery time.
The Three Phases Nobody Talks About the Same Way
Textbooks divide hand rehab into inflammatory, proliferative, and remodeling phases. That's correct but incomplete. In practice, the transitions between these phases are messy and individualized. A surgical repair doesn't follow the same timeline as a crush injury. A mallet finger recovery looks nothing like a proximal phalanx fracture rehabilitation. Phase one is protection with controlled motion. This is where most protocols diverge. Some therapists immobilize. Others start active motion immediately. The right answer depends on what was repaired and how secure the repair is. A flexor tendon repair done by someone who ties their knots conservatively needs more protection than one done with modern core suture techniques. You should know which technique was used before you clear a patient for anything beyond protected gentle motion. During this phase, edema control is non-negotiable. I've seen patients skip compression and elevation because they were impatient, then spend six weeks fighting stiffness that started as swelling. Swelling within a joint capsule doesn't just cause discomfort. It changes the arthrokinematics. The joint surfaces don't glide properly when the capsule is distended. Every motion attempt during significant edema reinforces abnormal movement patterns.
Get the Full Details
Phase two is progressive loading and desensitization. Once the tissue can handle more stress without risking re-injury, you introduce resistance. This isn't just squeezing a ball. It's directional loading that mimics the forces the hand will actually encounter. If someone is returning to construction work, grip strength at specific angles matters more than generic squeeze tests. I use a pinch gauge and a dynamometer, but I also have patients simulate their actual task demands — turning a screwdriver, carrying a tool belt, gripping a hammer handle. Desensitization is another area where people rush or skip it entirely. Neuroma pain or complex regional pain syndrome starting to develop in the healing tissues means you can't progress loading until the nervous system calms down. I've used graded exposure techniques here — touching different textures for set intervals, progressing from soft to rough over days or sometimes weeks. Some patients resist this because it feels pointless while the pain is acute. It's not pointless. Pushing through neuropathic pain without desensitization just reinforces central sensitization. Phase three is return to function with endurance. Strength gains happen fast compared to the endurance work that follows. A patient might regain 80 percent of their grip strength in eight weeks but still fail a functional test because they fatigue after two minutes of repetitive use. This is where I build in repetitive task practice that mirrors actual demands. Typing, cooking, dressing, lifting. The hand needs to sustain activity, not just produce a maximal contraction.
Specific Techniques Used in Occupational Therapy For Hand Injury
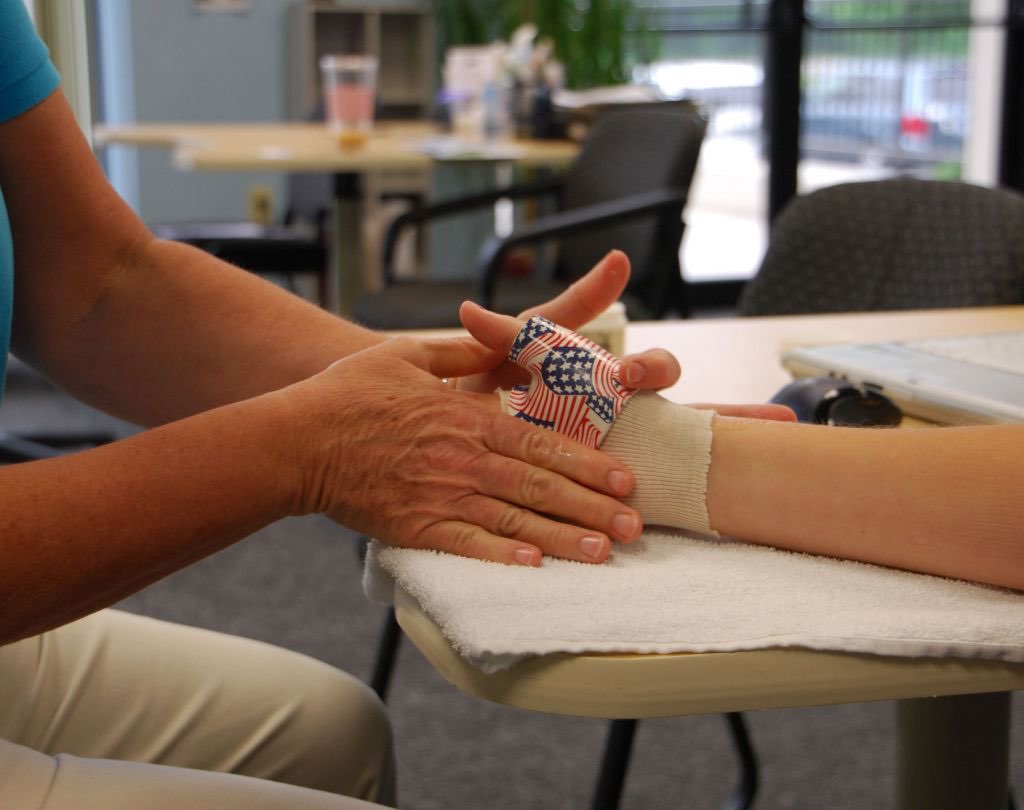
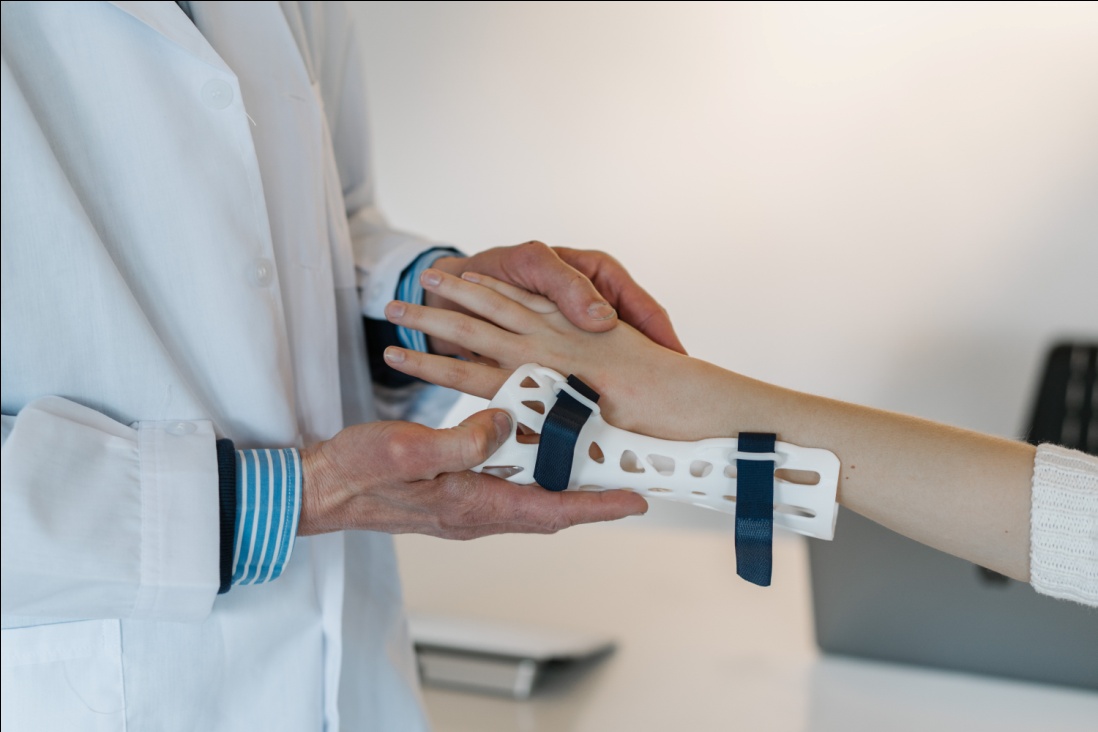
Scar management is probably the most misunderstood component. People assume massaging a healed wound is enough. It's not. Mature scars above two to three months old respond poorly to manual therapy alone. The collagen bundles are laid down in a random, dense pattern. You need mechanical force across multiple planes to remold them. I use cross-friction massage combined with static progressive splinting for resistant scar tissue. The friction breaks up adhesions. The splint applies sustained low-load stretch to lengthen the tissue. Tendon gliding is another technique that gets botched because people do the exercises wrong. The standard five-position sequence — straight fist, hook fist, tabletop, full fist, straight hand — is designed to move tendons through their full excursion. Patients often rush through it or hold positions incorrectly. I watch them do it every session initially and correct form. A half-range hook fist doesn't glide the flexor digitorum profundus through the A2 pulley region effectively. That's where most adhesions form after volar hand surgery. Splinting decisions are where experience really shows. A static Progressive splint versus a dynamic splint versus a functional splint — each serves a different purpose. I've had patients who needed a static progressive splint for a contracted PIP joint who were prescribed a dynamic rubber-band splint instead. The dynamic splint applies intermittent force, which isn't ideal for a stiff joint that needs sustained low-load elongation. The static progressive version holds the joint at the end range and gets adjusted incrementally. Big difference in outcomes.
Edema control techniques include retrograde massage, compression wrapping with ACE or Coban wraps applied in a figure-eight pattern from distal to proximal, and elevation protocols. I also use contrast baths selectively — not for everyone, but useful when circulation is adequate and there's no acute inflammation. Ten minutes in warm water followed by one minute in cold, repeated four to five times. This creates a pumping action in the vasculature that can help mobilize stagnant fluid.

Edge Case: When the Protocol Doesn't Apply
I had a patient with a volar plate injury from a hyperextension mechanism who presented with significant extensor lag at the PIP joint three weeks post-injury. Standard protocol for volar plate injuries is early active motion with blocking extension. This patient had followed that faithfully. But the extensor lag persisted and the PIP joint felt boggy on palpation with decreased arc of flexion. The issue was an extensor mechanism adhesions that weren't apparent on initial assessment. The volar plate injury drew attention away from the dorsal aspect where the central slip and lateral bands were adhering to the underlying capsule. I performed a dorsal capsular mobilization using Mulligan periarthritic mobilizations while the patient actively flexed the PIP. The change was immediate — gained about 25 degrees of flexion in a single session. What took two months afterward was maintaining that gain through repeated mobilization and active motion, because the adhesions wanted to reform. This is the kind of case where textbook timing rules fail you. Volar plate injuries are supposed to progress quickly because the risk is hyperextension recurrence. But when the dorsal structures are involved simultaneously, you need a different approach entirely. I've learned to palpate the entire dorsal aspect of every PIP joint, not just the area of primary injury. It takes thirty seconds and has changed my management plan more times than I can count.
Common Mistakes That Set Recovery Back
One mistake I see constantly is progressing too aggressively based on pain tolerance rather than tissue healing status. Pain is a poor indicator of structural integrity. A patient might feel fine doing an exercise while the tendon repair is still vulnerable. I rely on objective measures — swelling reduction, ROM progression, tissue consistency on palpation — rather than subjective pain reports when deciding to advance. Pain tells you something is irritating. It doesn't tell you whether the tissue can handle increased load. Another mistake is neglecting the proximal chain. Hand function depends on shoulder position, scapular stability, and cervical nerve root integrity. I've treated patients whose hand deficits didn't improve until we addressed a C7 radiculopathy that was contributing to weakness. The hand was the complaint, but the bottleneck was higher up. Similarly, poor scapular positioning changes the length-tension relationship of the extrinsic hand muscles. A patient with rounded shoulders and depressed scapulae will have reduced grip efficiency regardless of what you do to the hand itself. Not addressing psychological factors is a third error. Hand injuries often affect people's ability to work and perform activities of daily living in ways that aren't obvious to outsiders. A chef who can't grip a pan handle. A musician who can't press strings. A parent who can't lift a child. The frustration and anxiety around these losses can create pain amplification and avoidance behaviors that slow progress. I screen for this early and address it directly rather than pretending it doesn't exist.
Realistic Expectations and Timeline
Hand recovery timelines vary enormously depending on the injury type, treatment quality, and individual factors. A minor ligament sprain might resolve in three to four weeks with proper management. A complex tendon repair with secondary adhesions can take six months or longer to reach functional goals. Fractures involving the joint surface have unpredictable outcomes depending on reduction quality and articular congruity. What I can say with confidence is that consistent, appropriate intervention produces measurably better outcomes than neglect or inappropriate treatment. Patients who attend sessions regularly, perform home programs correctly, and follow activity modifications recover faster and retain more function. The patients who skip home exercises because they "feel fine" are usually the ones who plateau and need extended therapy. Return-to-work clearance should be based on functional capacity, not just ROM and strength numbers. A construction worker needs to demonstrate they can handle the specific demands of their job — sustained grip, vibration exposure, awkward wrist positions — not just pass a grip dynamometer test. Office workers have different requirements. The assessment should match the demand.

Occupational therapy for hand injury isn't glamorous work. It involves repeated measurement, careful tissue assessment, gradual progression, and dealing with patients who are frustrated by slow progress. But it works when it's done with attention to detail and willingness to adjust when standard protocols don't fit the individual case. The hand is a complex structure and the rehab needs to match that complexity.