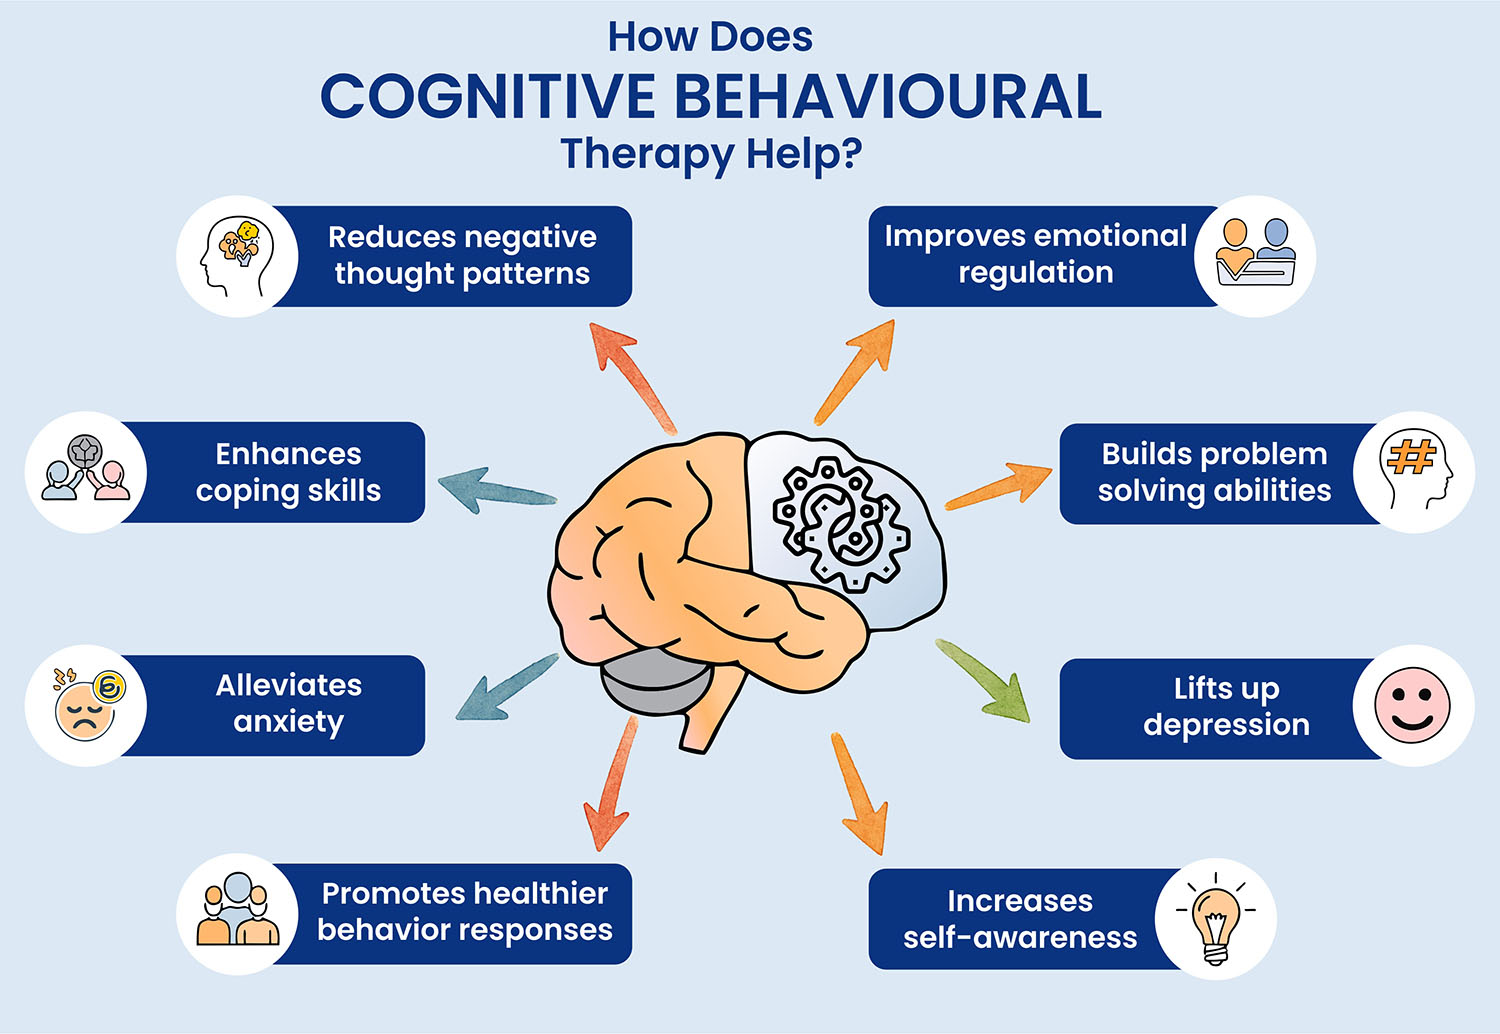
What Actually Happens When You Sit in a Behavioral Therapy Room
I still remember the first time a client told me they didn't believe the exercises would work. They said it out loud, not bitter or aggressive, just tired. I didn't try to convince them. We just talked about what their life had looked like over the last three months and traced the behaviors back to what was reinforcing them. That conversation lasted maybe twenty minutes and it set the direction for everything else. The reality of this work is that people come in expecting transformation. They walk out sometimes just having a clearer map of what's keeping them stuck. That gap between expectation and outcome is where most of the friction lives. The goal of behavioral therapy is to help people change patterns that maintain psychological distress, but doing that in practice looks very different from how it gets described in textbooks.
The Goal Of Behavioral Therapy Is To Break The Cycle That Keeps Someone Stuck
Behavioral therapy focuses on observable actions and the environmental factors that reinforce them. It treats problems by changing what people do rather than spending most of the session time digging into why they feel a certain way. The core idea is straightforward: behavior is learned, and behavior can be unlearned or reshaped through new learning experiences. When I started working with clients on anxiety, the standard protocol would have me jump straight into exposure hierarchies. Instead, I found myself spending the first few sessions just mapping out what their avoidance patterns actually looked like on a typical Tuesday. A 34-year-old woman I worked with avoided grocery stores between 10am and noon because that was when her anxiety spiked. She hadn't noticed the pattern herself. Once we wrote it down, the intervention became obvious. We didn't need to reframe her thoughts about being judged. We needed to shift the timing and build a repeated approach sequence. The work tends to fall into a few main buckets. Cognitive behavioral therapy blends thought patterns with behavioral experiments. Dialectical behavior therapy adds emotion regulation and distress tolerance skills on top of exposure work. Acceptance and commitment therapy pushes harder on values-based action rather than symptom elimination. Each approach has a slightly different flavor, but they share the same basic engine: identify the maintaining factors, intervene on them, measure whether the behavior changes.
How The Process Actually Unfolds Session By Session
The first session is rarely about any technique. It is about getting a timeline. When did the problem start. What was happening in the person's life before it appeared. What strategies have they already tried. I usually let the client talk for forty-five minutes without interrupting and then I ask them to describe a single recent example of the problem in full detail. Not the general version. The specific one. From there, behavioral activation starts to take shape for depression cases. People who are depressed tend to move less, socialize less, and engage in fewer rewarding activities. The cycle reinforces itself. Getting them to schedule small, measurable activities can shift mood within two weeks, but only if the activities are actually achievable. I once had a client who insisted on going to the gym five days a week as part of her plan. She went exactly once. The failure made her feel worse. We dropped the gym entirely and replaced it with a fifteen minute walk after breakfast. She kept that for eleven weeks straight. Exposure work is where most people hit resistance. The theory says you present the feared stimulus without allowing the avoidance response. In practice, clients will negotiate, skip sessions, or do the exposure half-heartedly while distracing themselves. I stopped accepting partial exposures early on. If the client is counting seconds on their phone during a social anxiety drill, the exposure doesn't count. We do it again. That boundary seems harsh but it saves months of stalled progress.
Get the Full Details

Homework is non negotiable in this framework. Sessions alone produce minimal change. The behavior has to be practiced outside the room. Most clients complete roughly sixty percent of assigned exercises. I track completion rates and adjust accordingly. When the rate drops below forty percent, something is wrong with either the assignment or the therapeutic alliance, and one of those needs to change.
Common Pitfalls That Slow Progress Down
One mistake I see therapists make regularly is treating surface behavior as the actual problem. A client keeps checking the stove. The surface behavior is checking. The maintaining factor might be a catastrophic belief about what happens if the stove is left on. If you only address the checking without touching the belief, the checking returns within days. You have to hit both levels. Another pitfall is pushing exposure too fast. Clients need a manageable hierarchy. Jumping to the top of the fear ladder creates dropout. I usually aim for a subjective units of distress score around four or five out of ten at the starting point. If the client scores higher than seven, the step is too big. Measurement is where many programs fall apart. Without baseline data and ongoing tracking, you cannot tell whether the intervention is working. I use simple weekly symptom checklists and behavior logs. The act of recording itself sometimes produces change. That is not a flaw. It is part of the mechanism.
There are also cases where behavioral therapy hits a wall. Severe personality disorders with entrenched relational patterns respond slowly. Complex trauma often requires a longer preparatory phase before direct behavioral work is safe. Medication assisted treatment may need to be in place first for certain anxiety disorders. Acknowledging those limits early prevents wasted months.
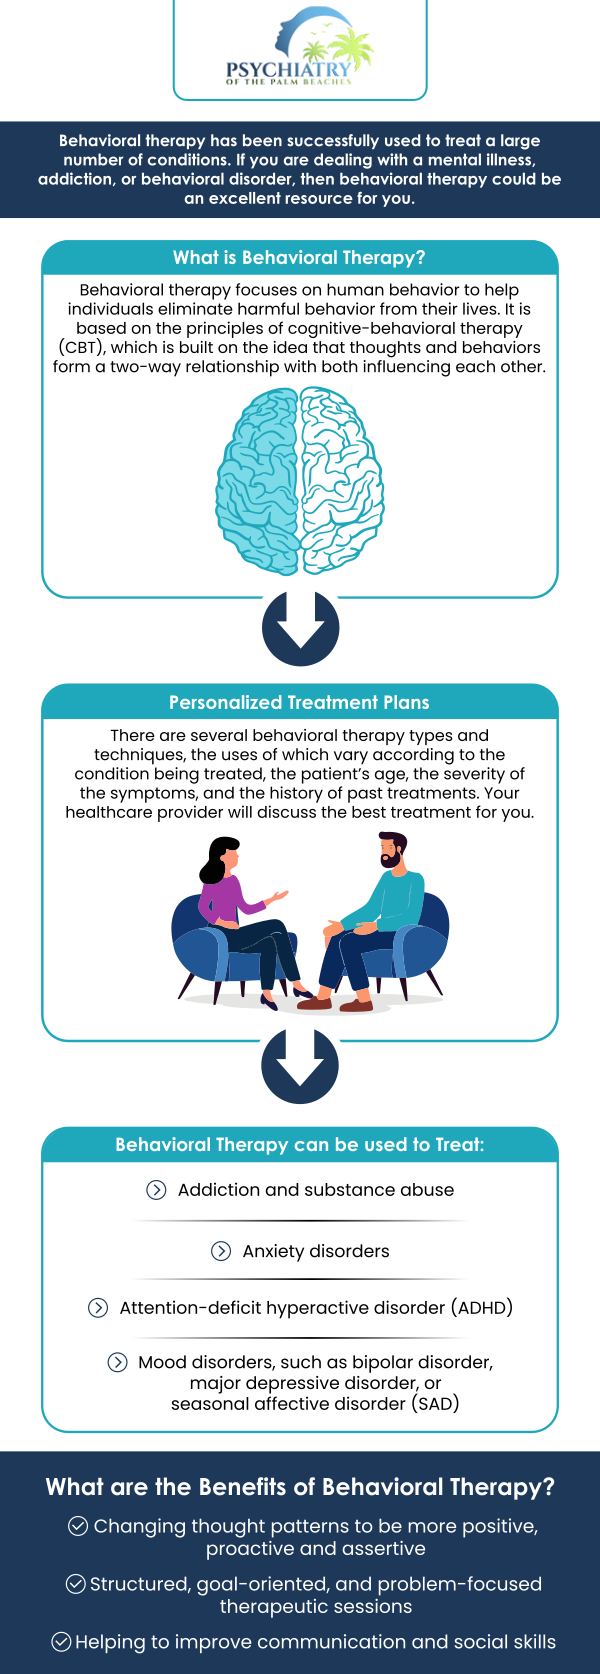
What Works When Things Stall
When progress stalls, I revisit the functional analysis. What am I missing about the reinforcement schedule. Sometimes the answer is that the behavior is being unintentionally rewarded by attention or escape from an uncomfortable situation. Removing or altering that reward shifts things quickly. Other times the issue is motivation. Values clarification work from acceptance and commitment therapy helps here. Asking a client what kind of life they want even if the symptoms stay present can reopen engagement. It is not a technique for every person, but it works often enough to be part of my standard toolkit. Consultation or supervision becomes necessary when the therapist feels stuck. I have lost track of how many times bringing a case to a colleague revealed an obvious maintaining factor I had been blind to. Therapists are not immune to pattern blindness.
A Real Case That Changed How I Practice
I had a client with obsessive compulsive disorder who contaminated fears centered on public restrooms. Standard exposure would have her touching a doorknob and then delaying handwashing. She tried it. She cried. She refused to do it again. We spent six sessions just discussing what the ritual meant to her beyond cleanliness. It turned out the ritual was tied to a guilt complex from childhood. The behavioral piece still mattered, but the emotional meaning was blocking compliance. We introduced a modified approach. She touched the doorknob and then wrote down the thought that popped up instead of performing the wash. Writing replaced the ritual. After three weeks of that, she returned to the doorknob exposure. This time it worked. The lesson was clear. Behavior change without addressing the meaning underneath stalls every time. That experience changed how I structure treatments. I still use behavioral tools aggressively. Exposure, activation, contingency management. But I leave space now for the narrative layer to surface before pushing the behavioral lever too hard.
What Evidence Actually Supports
Behavioral therapy has strong empirical backing for depression, anxiety disorders, obsessive compulsive disorder, and post traumatic stress. Meta analyses consistently show effect sizes in the moderate range, often matching or exceeding pharmacological interventions for certain conditions. The durability of gains tends to be better than medication alone because the skills transfer outside the treatment setting. Limits exist. The therapy requires regular attendance, honest self monitoring, and willingness to face discomfort. It is not passive. People who expect a therapist to fix them inside a quiet room will leave disappointed. The change happens between sessions, not during them. Access remains a practical problem. Trained providers are unevenly distributed. Wait times in some areas stretch past six months. Digital delivery models have improved things but they do not replicate the therapeutic relationship for everyone. In-person work still produces better outcomes on average for complex cases.

If you are considering this path, the most useful thing you can do is commit to the process and track your own behavior. The goal of behavioral therapy is to create lasting change through action, and action requires showing up even when motivation is low. That is the hard truth of it.