What OT Actually Looks Like for SPD in Adults
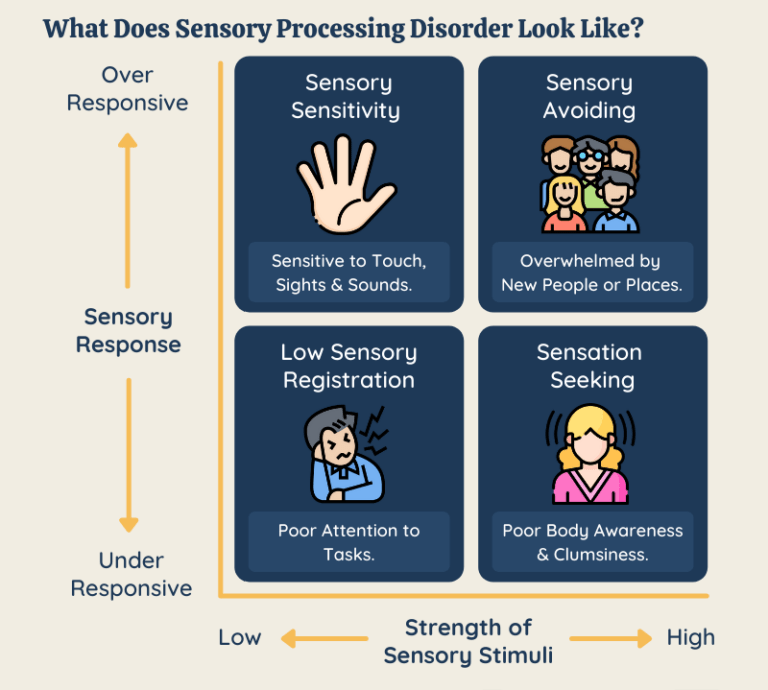
Most people walking into occupational therapy for sensory processing disorder as an adult have already tried a dozen self-help strategies that didn't work. They come in exhausted, frustrated, and suspicious. That's fair. A lot of SPD content online treats adults like oversized children who just need to find the right fidget toy. It doesn't work that way. The actual clinical approach is more specific and significantly less glamorous than you'll see on Pinterest. Sensory processing disorder in adults isn't a diagnosis you get from a single test. It's a pattern of neurological responses where the brain has trouble receiving, organizing, and responding to sensory input. That sounds academic, but it translates into real functional problems: fluorescent lights at the grocery store can feel physically painful, certain fabric textures make it impossible to focus on a work task, background noise in a restaurant makes comprehension nearly impossible. These aren't character flaws or anxiety disorders, though they're frequently misdiagnosed as both.
Occupational Therapy For Sensory Processing Disorder Adults
The therapeutic framework for adults with SPD generally follows the Ayres Sensory Integration model, though modified significantly from how it's used with children. The core mechanism involves creating a controlled sensory environment where you're systematically exposed to inputs that your nervous system over- or under-reacts to, gradually building tolerance through repeated, graded exposure. This is called sensory reactivity training, and it's nothing like the "exposure therapy" model used for phobias, even though they share a surface similarity. Here's what I've observed repeatedly in practice that most guides don't mention: the biggest predictor of success isn't how hard you push during sessions, it's how well you manage your nervous system recovery between sessions. Adults typically come in wanting to brute-force their way through discomfort. That almost never works because the nervous system doesn't adapt through repeated stress alone. It adapts through repeated stress followed by adequate down-regulation time. If you're working through sensory challenges five days a week without significant rest periods, you're probably making things worse, not better. The standard assessment process usually takes two to three initial sessions. The therapist will complete something like the Sensory Processing Measure or the Adolescent/Adult Sensory Profile, then observe your responses to various stimuli. You'll be asked about your reactions to textures, sounds, movement, proprioceptive input, and interoception — that's your awareness of internal body signals like hunger, thirst, and heart rate. Most adults haven't really thought about interoception before, and it turns out to be a major factor in sensory dysregulation that nobody addresses until it's too late.
After assessment comes the actual intervention, which typically falls into one of three categories. First is sensory diet planning, which sounds made up but is actually a structured schedule of sensory activities designed to keep your nervous system regulated throughout the day. Second is environmental modification, where you systematically change your living and working spaces to reduce unnecessary sensory load. Third is direct sensory integration therapy, where you work one-on-one with the therapist using specialized equipment like weighted blankets, swings, and tactile tools to build adaptive responses. I should flag something important here that clinics rarely advertise upfront: occupational therapy for adult SPD doesn't have a strong evidence base for outcomes. The research is thin, primarily focused on pediatric populations, and most of what we know comes from clinical observation rather than controlled trials. Some studies show moderate improvement in daily functioning, others show minimal change beyond what you'd expect from general life adjustments. The effect size is real but small. If a therapist promises you'll be "cured" within six months, find someone else. What you can realistically expect is better recognition of your triggers, improved coping strategies, and a measurable reduction in how often sensory overload disrupts your life. That's valuable, but it's not a transformation story. There's also a significant limitation that every adult with SPD needs to understand before committing to therapy. Sensory processing differences are neurologically based, which means they don't go away. Therapy helps you manage them, not eliminate them. People who go into OT expecting to reach a point where they can tolerate any environment without discomfort end up deeply disappointed. The goal isn't normalization. The goal is functional adaptation — learning to navigate a world that wasn't designed for your nervous system.
Get the Full Details

One edge case I ran into fairly regularly involves adults who have developed significant avoidance patterns over years of untreated SPD. These clients show up with extremely narrow behavioral repertoires. They might avoid whole categories of environments — supermarkets, construction sites, open-plan offices — because of sensory triggers they've learned to associate with distress. The problem is that by avoiding these situations entirely, their nervous systems never get the chance to build tolerance. The avoidance itself becomes part of the disorder. The workaround I found effective for this was called graded community exposure. Instead of trying to fix everything in the clinic, we'd identify one manageable public environment and visit it together in small, timed increments. Ten minutes at the edge of a hardware store. Twenty minutes in a quiet bookstore. The key was keeping the exposure brief enough that it didn't trigger a full dysregulation episode, then gradually extending duration across weeks. It required significantly more coordination than standard clinical work, but it addressed the avoidance cycle that was maintaining the problem. Another counter-intuitive insight that takes most clients a while to accept: proprioceptive input is almost always more regulating than vestibular input for adults with SPD. Proprioception comes from muscles and joints — heavy work, resistance, compression. Vestibular input comes from movement and balance — swinging, spinning, rocking. Many adults instinctively gravitate toward movement-based activities because they feel more immediately calming. But the effects tend to be shorter-lived and sometimes counterproductive for people who are already anxious. Proprioceptive input tends to produce more sustained regulation. Deep pressure vests, weighted lap pads, resistance band exercises under desks — these things actually move the needle more than the swinging therapy they love in session.
The practical implementation of a sensory diet for adults requires tracking, and most people skip this step because it feels tedious. Don't skip it. Keep a daily log for at least two weeks noting what sensory inputs you encountered, your stress level on a one-to-ten scale, and what you did to recover. You'll start seeing patterns that you genuinely couldn't have identified without the data. Some people discover that their afternoon crashes are linked to visual overstimulation from screens, others find that certain types of auditory input consistently derail their evening. This data directly informs your therapist's recommendations and makes the intervention significantly more targeted. Cost is a realistic barrier that deserves mention. Occupational therapy sessions typically run between seventy and one hundred fifty dollars per appointment in the United States, depending on location and insurance. A standard treatment plan might recommend one to two sessions per week for three to six months. That's easily four hundred to twelve hundred dollars out of pocket if insurance doesn't cover it fully. Some clinics offer group sessions at reduced rates, and a few therapists provide telehealth options which tend to be cheaper. Insurance coverage for adult SPD specifically varies wildly by provider and plan. Some will cover it under an autism spectrum diagnosis, others under an unspecified sensory processing issue, and some won't cover it at all. Call your insurance company before committing to a provider and ask specifically about sensory integration therapy coverage for adults. Self-management between sessions matters enormously, and most of it doesn't require special equipment. The basics include: identifying your primary sensory triggers and ranking them by impact, creating low-sensory recovery routines for high-demand days, modifying your immediate environment to reduce unnecessary input (dimmer switches, noise-canceling headphones, simpler clothing choices), and learning to recognize early signs of sensory overload before they escalate into full dysregulation. Early signs are usually subtle — irritability, difficulty concentrating, physical tension, increased heart rate. Catching these early and implementing a regulatory activity can prevent a much larger crash later.
If occupational therapy isn't accessible or affordable, there are established alternatives worth considering. Cognitive behavioral therapy adapted for sensory issues can help with the anxiety and avoidance components that often accompany SPD. Neurofeedback has shown some promise in regulating sensory processing patterns, though the evidence is still emerging and it's expensive. Mindfulness-based stress reduction can improve interoceptive awareness, which helps many adults recognize and respond to sensory signals earlier. Community support groups for neurodivergent adults often share practical strategies that clinical settings don't always cover. The hardest truth about adult SPD and occupational therapy is that progress is slow and nonlinear. You'll have weeks where everything feels manageable followed by weeks where simple tasks become overwhelming. This isn't failure. It's how nervous system regulation actually works. Consistency matters more than intensity. Showing up for weekly sessions and doing your sensory diet daily will produce better results than occasional intense efforts. Your therapist should be someone you can be honest with about setbacks without feeling judged. If they're pushing you harder than you can sustain, that's not good therapy — that's just stress.