
What Occupational Therapy Actually Looks Like in the NICU
Most people who hear about occupational therapy in the neonatal intensive care unit picture a therapist walking in with a bin of sensory toys and going to work. That is not what happens here. TheNICU environment is loud, bright, and full of machines that beep at regular intervals, and every intervention has to be measured against whether it is going to upset a baby who weighs three pounds and is surviving on mechanical ventilation. Occupational Therapy In Nicu is a very different discipline from what you see in outpatient pediatrics, and understanding that gap is the first step if you actually want to do it right. I spent several years doing bedside OT in a Level III NICU before moving into clinical education, and the first thing I learned was that the standard pediatric OT toolkit is almost entirely useless at this end of the weight spectrum. You cannot hand a preterm infant a rattle and expect sensory integration to occur. The nervous system is so underdeveloped that even the sound of plastic rattling nearby can trigger a desaturation event. The work is almost entirely about state regulation and family-centered environmental modification rather than traditional therapeutic activities.
The Real Work of Occupational Therapy In Nicu
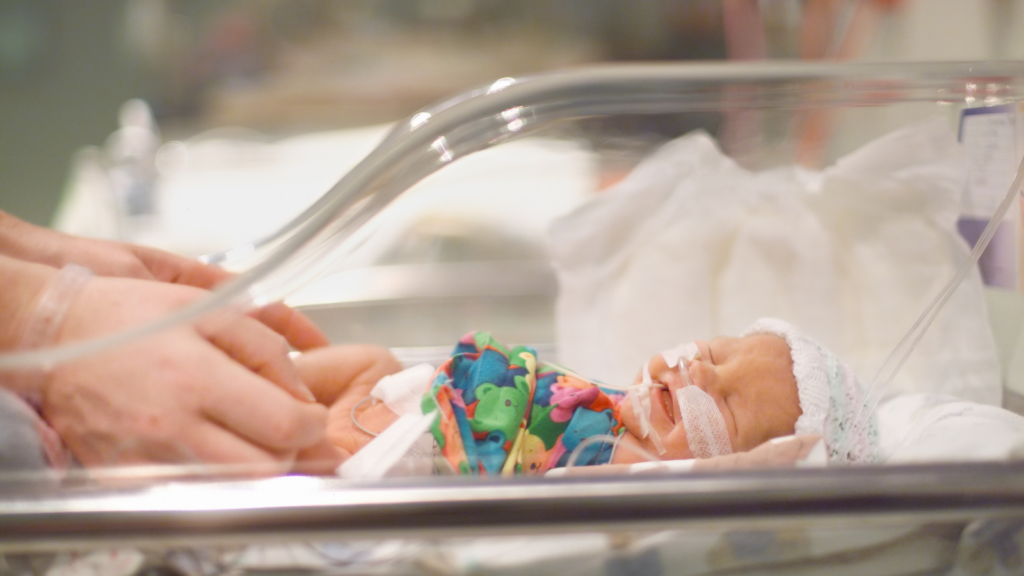
The primary objective in NICU occupational therapy is helping the infant achieve and maintain a regulated state. State regulation means the baby can stay in a quiet alert or calm sleep state without tipping into distressed crying, oxygen desaturation, or heart rate instability. This sounds simple but it is surprisingly difficult to achieve in a unit where feeding tubes, respiratory support, and monitoring leads are constantly irritating the infant's limited range of motion and comfort. I approached each session by first assessing the baby's current physiological parameters and behavioral cues. Heart rate, oxygen saturation, respiratory rate, and ventilator settings were all part of the baseline I needed before touching the infant. Then I evaluated their state using the Brazelton Neonatal Behavioral Assessment Scale and the NICU Network General Information System criteria simultaneously. These tools are not optional. They provide the framework for understanding whether the baby can tolerate even minimal therapeutic handling or whether the session needed to be aborted immediately. The actual interventions fall into several categories. There is positioning and postural support using specialized nests and rolls made from gauze and conformable foam. Joint compression and deep touch pressure applied with extremely light force can help with body awareness when the infant is in a quiet state. Oral motor stimulation using sterile silicon swabs is common for infants who are not yet feeding by mouth. Environmental modification around the incubator including reducing ambient light and clustering care activities to minimize interruptions is something therapists do routinely.
Why This Is Different From Regular Pediatric OT
One of the most significant differences between NICU occupational therapy and general pediatric practice is the absence of standardized outcome measures for many of the skills being targeted. In an outpatient clinic you can use the Peabody Developmental Motor Scales or the Bruininks-Oseretsky Test. Those instruments simply do not apply to a twenty-six-week preterm infant who cannot lift their head independently. Instead NICU therapists rely on measures like the PREM (Premature Infant Profile) and the IDELA (Infant Development and Early Learning Assessment) which were specifically designed for this population. Another difference is the pace at which progress occurs. A term infant recovering from a mild injury might show measurable improvement over two or three weeks. A preterm infant whose nervous system is still undergoing myelination may need six to eight weeks before you see the same degree of functional change, and even then the progress will not be linear. Some days the best outcome is that the baby did not desaturate during the session. That is a valid outcome and it should be documented as such. The family component is also far more intensive than in typical pediatric OT. Parents of NICU infants are dealing with trauma, sleep deprivation, medical decision fatigue, and often guilt. The therapist needs to engage them as partners in care from day one rather than bringing them in for a discharge education session. I spent more time coaching mothers on how to hold their infants in a contained midline position while managing their own anxiety than I did on direct infant therapy during the first month of the stay. This is not secondary. It is central to the therapeutic process.
Get the Full Details

A Problem I Encountered With Positioning Protocols
There was one particular case that illustrates how complicated NICU OT can become. I had an infant born at twenty-five weeks who had bilateral intraventricular hemorrhage graded two and was on gentle ventilatory support. The standard positioning protocol for this gestational age called for flexion and containment using a Nest roll on all sides. The problem was that this baby had significant diaphragmatic dysfunction and the lateral rolls, while excellent for trunk stability, were compromising his ability to expand his chest laterally enough to maintain adequate tidal volumes. He was desaturating consistently whenever the lateral containment was applied. Simply removing the rolls left him in a poor posture but did not solve the breathing problem. The workaround I used was to switch to a modified prone positioning approach with a rolled towel placed only under the abdomen and chest rather than the sides, which allowed lateral rib cage expansion while still providing the flexion support his muscles could not generate on their own. I also coordinated with respiratory therapy to adjust the pressure support settings slightly during positioning sessions. The result was that we could maintain acceptable oxygenation while still achieving the postural benefits of containment. This required constant communication with the neonatology and respiratory therapy teams and frequent reassessment every fifteen to twenty minutes during the session.
Common Mistakes New NICU Therapists Make
The most frequent error I see is attempting too much too soon. There is a natural instinct to want to accomplish something meaningful in every session, and therapists often push beyond the infant's tolerance window because they feel pressure to justify their involvement. This leads to sessions that end in distress rather than regulation. A session that lasts four minutes because the baby became tachycardic and oxygen sats dropped is not a failed session. It is data that tells you the infant needs more time at the current level before progressing. Document it and adjust the plan. Another mistake is underestimating the impact of the therapist's own presence and energy on the infant. NICU infants are extremely sensitive to environmental stimuli and the tone of voice, the speed of movement, and even the emotional state of the person entering the room can affect the infant's stress response. If you walk in rushed or distracted, the infant will register that. Taking thirty seconds to sit quietly at the side of the incubator before beginning any intervention is not wasted time. It is part of the assessment. A third pitfall is neglecting the parents' need for education about the infant's behavioral cues. Many parents do not understand why their baby cannot tolerate being held for more than a few minutes at a time. They may interpret the infant's intolerance as rejection or discomfort with them personally. Explaining the physiology behind state regulation and the concept of the tolerance window in plain language can transform a parent's experience from one of helplessness to one of partnership. This is where occupational therapy in the NICU overlaps significantly with family-centered care models and why therapists who focus exclusively on the infant miss a critical piece of the work.
Documentation and Communication With the Medical Team
NICU occupational therapy documentation needs to be precise and clinically relevant. Vague notes like "infant tolerated session well" are not useful in this setting. The documentation should include specific physiological parameters before, during, and after the intervention. Heart rate range, oxygen saturation trends, respiratory pattern changes, and color changes all need to be recorded alongside the therapeutic activities performed and the infant's behavioral state throughout the session. Communication with the medical team is equally important. The neonatologist, respiratory therapist, nursing staff, and other therapists all need to understand what is happening during OT sessions because the infant's condition can change rapidly. I found that including a brief verbal update to the nursing staff at the end of each session and flagging any significant physiological changes to the attending physician within the shift was essential. This is not bureaucratic overhead. It is clinical safety. There are also institutional considerations that vary widely. Some hospitals have formal NICU therapy programs with dedicated therapists on staff. Others rely on per diem contractors or shared therapy services across multiple units. The level of integration with the medical team and the scope of practice allowed can differ significantly between these models. If you are new to this area it is worth understanding the specific protocols and expectations at your facility before assuming anything transfers directly from outpatient or inpatient pediatric settings.
Progression and Discharge Planning
The goal of NICU occupational therapy is to prepare the infant and family for the transition out of the intensive care unit. This involves building skills gradually as the infant matures neurologically and physiologically. Early sessions focus on stabilization and regulation. As the infant grows more stable the focus shifts toward oral motor development in preparation for feeding, improved postural control, and increased tolerance for handling and environmental stimuli. Discharge planning is a collaborative process that begins early and continues throughout the stay. The therapist needs to assess what supports the infant will require after discharge, whether that is specialized seating, ongoing home therapy referrals, or parental guidance on managing sensory sensitivities. Some infants who have had prolonged NICU stays benefit from follow-up occupational therapy in an outpatient setting, particularly those with diagnosed hypotonia, feeding difficulties, or sensory processing challenges that become apparent as they grow. The transition from NICU to a special needs nursery or step-down unit is another critical point where occupational therapy input matters. The infant's tolerance for handling, their feeding status, and their regulatory capacity may change significantly during this transition, and the therapist needs to be involved in determining the appropriate level of support and intervention for the new environment.
What This Work Requires From You
NICU occupational therapy is not a career path for someone who needs immediate visible results. The progress is slow, the outcomes are often subtle, and the infants you work with are among the most fragile patients in the hospital. You will have sessions where nothing changes and days where the infant's condition deteriorates despite your best efforts. This is normal. It is not a reflection of your competence. The work does require patience, attention to detail, and the ability to think on your feet when an infant's condition changes unexpectedly. It also requires a genuine interest in family-centered care and the communication skills to work effectively with a multidisciplinary team. The pay and job satisfaction vary by setting, but the clinical learning curve is steep and the skills you develop in the NICU are transferable to other areas of pediatric and neurological rehabilitation. If you are considering this path, I would recommend seeking out a mentor who is currently practicing in a NICU setting and asking to observe several sessions before committing. The theoretical knowledge is important but the practical application is where the real learning happens, and no textbook can prepare you for the reality of working with an infant who is this small and this medically complex. The work is demanding but it is also one of the most meaningful areas of pediatric therapy practice, and the relationships you build with the families you work with tend to stay with you long after the clinical details fade.



