Writing occupational therapy notes that don't make you want to quit
I spent six years in acute rehab before moving to outpatient. The number one thing I learned isn't about documentation software or note templates. It's about understanding what a payer actually wants to see versus what a clinician thinks is important. These two things overlap about 60 percent of the time.Most OTs I train spend 45 minutes to an hour on a single shift's documentation. That's not sustainable. Here's how I got mine down to about twelve minutes per day without getting audited.
What Occupational Therapy Notes Actually Require
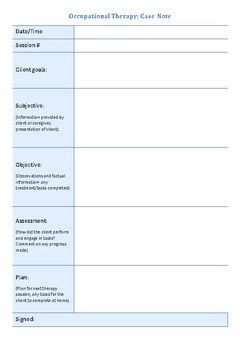
There's a misconception that notes need to be literary. They don't. A proper OT note needs four things: the problem being addressed, the intervention delivered, the patient's response, and the plan going forward. Everything else is decoration. I once had a case where an insurer denied coverage for twelve sessions because the note said "patient tolerated session well" instead of "patient demonstrated improved dressing independence from assist level 2 to modified assist after 10 minutes of adaptive clothing techniques." Same clinical event. Completely different financial outcome. That one changed how I write forever.The key detail people miss is specificity around assist levels. "Required minimal assistance" means nothing to a reviewer who wasn't in the room. "Required verbal cueing and standby assist on trunk rotation during transfer from bed to chair, performed 3 repetitions with a 2-minute rest between sets" tells the whole story. It also takes thirty seconds longer to write.
The SOAP Method and Why You Should Still Use It
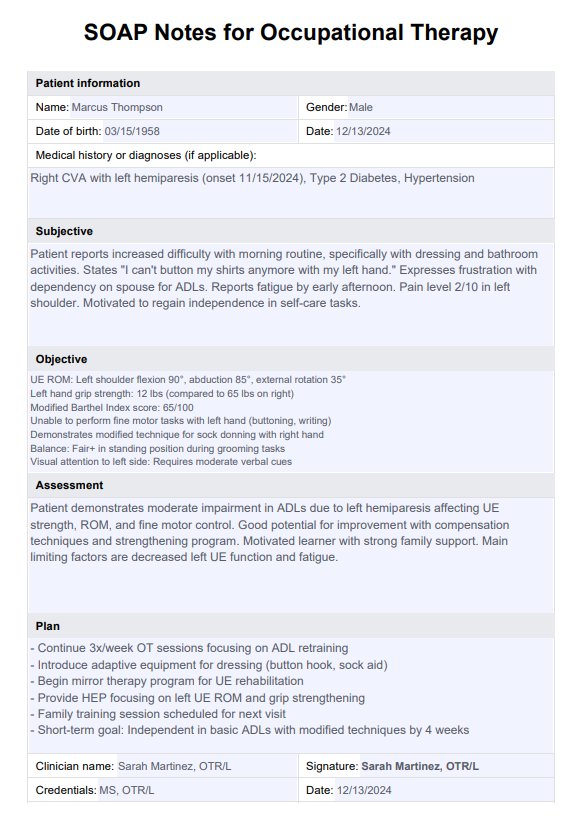
Subjective, Objective, Assessment, Plan. It feels outdated but it exists for a reason. Subjective captures what the patient or caregiver reports. Objective is your measurable data. Assessment is your clinical reasoning. Plan is what happens next. I use a modified version. Some clinics push DAP notes now, but I find the subjective section of SOAP saves you headaches when a family member disputes what was discussed during treatment. Having their exact quoted concerns on file is worth the extra five minutes.Here's a realistic example from my own practice. A patient with a stroke came in with goals around feeding independence. The note read: "PT reported using adaptive utensil with right hand, required verbal prompt to check remaining food on plate. Tolerated 20 minutes of training without signs of fatigue. Continued with adaptive strategies for next 2 weeks. Reassess feeding safety if weight loss exceeds 5 pounds." Clear. Defensible. Done in about four minutes once you know your shorthand.
Get the Full Details

Common Mistakes That Get Notes Flagged
Copying and pasting from previous encounters is the fastest way to get an audit. Automated detection tools catch these now. I've seen legitimate notes rejected because someone cloned a template from three days prior without adjusting the dates or vitals. Another mistake is disconnecting the plan from the objective data. If your objective section shows the patient couldn't complete a task, but your plan says they're ready for discharge, that's a red flag. Reviewers follow a logical chain. Break it anywhere and the claim wavers. My workaround for the first problem is using a base template with clearly marked placeholder brackets. I fill each bracket before submitting. Takes two extra minutes but it's faster than rewriting a stolen note after a rejection.Building Efficient Documentation Habits
Set aside the last twenty minutes of your shift strictly for notes. Not before. Not during. After. If you try to document while treating, both suffer. I've watched therapists write notes and fiddle with their charting tablet while a patient was mid-transfer. It happened more than once in my old clinic and it's a liability waiting to happen. Use templates but customize them every time. Create one for upper extremity neuro, one for lower extremity, one for ADL training, one for cognition. Switch between them rather than building from scratch. I keep mine in a cloud-synced document that I can access from any workstation.Voice dictation tools have improved enough that I dictate my objective sections now. Saying "standby assist left transfemoral amputation, 3 reps, rest 2 min" takes eight seconds. Typing it takes forty. The transcription accuracy is about 92 percent which means I correct roughly two words per dictation. Net gain is significant over a full charting load.
When Notes Alone Won't Save Your Claim
No amount of beautifully written documentation fixes a gap in medical necessity. If the patient hasn't made measurable progress toward their goals in six weeks, a perfect note won't justify continued services. I've argued this point with utilization reviewers more times than I'd like to admit. The data either shows progress or it doesn't. In those situations, the right move is documenting the barrier to progress clearly and requesting a plan modification rather than continuing the same approach blindly. Sometimes that means involving the referring physician. Sometimes it means adjusting the diagnosis code to reflect a changed clinical picture. Notes should capture the pivot, not just the routine.One edge case I ran into: a patient with complex regional pain syndrome whose functional gains were plateauing but who was making enormous effort during each session. The effort itself was clinically meaningful for pain modulation even if ADL scores weren't moving. I documented the effort metric alongside the functional outcomes and included a pain management framework. The reviewer accepted it because the clinical reasoning was transparent. Worth noting for anyone dealing with pain-related functional disorders where progress isn't linear.
Practical Workflow for a Full Day of Notes
Start each note as the session ends. Even two sentences captured immediately beats reconstructing everything from memory at 6 PM. I type the objective section right after the patient leaves while the details are fresh. I fill in the subjective and plan sections during a break or at the end of the day. Keep a running log of goal progress scores. Rather than calculating them mentally at note time, maintain a separate tracking sheet updated after each session. When it's time to write the assessment, you're copying numbers, not estimating them. This alone cuts my assessment writing time in half.I recommend doing a quick peer review swap once a week. Have another therapist scan your notes for clarity and completeness. You'll catch gaps you didn't know existed and you'll learn shortcuts from how others structure their work. I picked up the voice dictation method this way after watching a colleague wrap her charting in ten minutes while I was still struggling through mine.