Writing OT Notes That Don't Make You Want to Quit
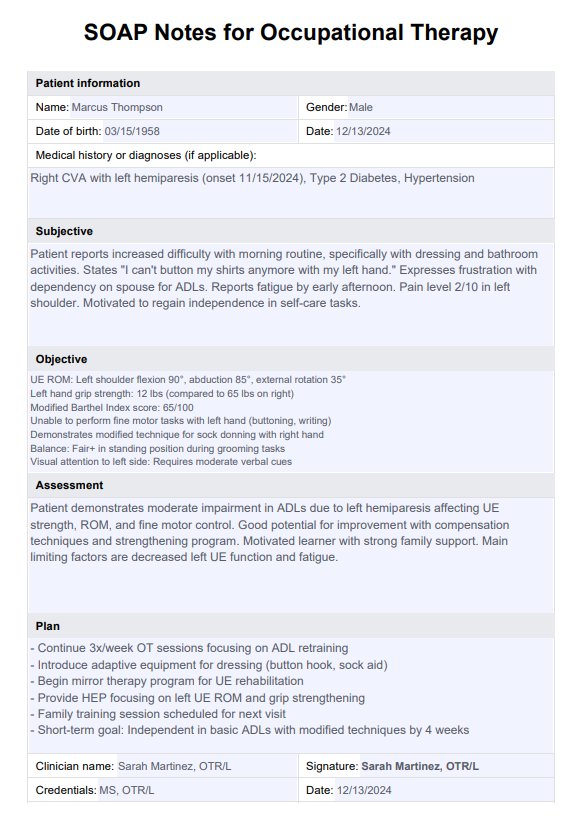
Most OT notes are boring because the people writing them treat documentation like an afterthought. It should be treated like a legal document that happens to also help the next provider understand what's going on. I've been doing this long enough to know that the best notes come from thinking about the chart while you're in the session, not scrambling at 4:30pm to fill out ten missing templates. The basic structure most clinics expect is the SOAP format. Subjective, Objective, Assessment, Plan. It's not a suggestion. It's literally what auditors look for. But within that framework there's a lot of room to write something useful or something that will get you flagged for a review. Here's how I approach it.
Subjective Section
This is what the patient tells you. Not what you think they tell you. I had a patient once who said during session, "I haven't been cooking at all lately." Standard note would say "patient reports difficulty with ADLs." That's vague enough to be useless. The specific note says: "Pt states has not prepared meals in 3 weeks due to right hand pain and inability to hold utensils." That tells me exactly what's happening. The patient also reported doing laundry twice a month versus weekly before the injury. Specifics matter more than broad categories. When documenting subjective complaints, include the patient's own words in quotes when possible. Insurance reviewers can spot paraphrased language immediately. They've read ten thousand notes. They know the difference between "Pt denies pain" and "Pt states 'my shoulder does not hurt' during activities." One is a clinical conclusion. The other is a factual statement.
Objective Section
This is where most notes fall apart. You need measurable data. Range of motion numbers, strength grades, functional scores, time on task, accuracy percentages. If you write "patient improved in fine motor skills," you have written nothing. Write: "Patient completed 8/10 pegboard tasks in under 45 seconds, up from 4/10 in 2 minutes at last visit." That's objective. That's defensible. That's useful. I deal with a lot of clinic setups where the EMR forces you into dropdown menus and checkboxes. Don't let the template replace actual observation. I've seen notes where the checkbox said "grip strength improved" but the actual numbers dropped from the previous visit. The system had a default value that someone forgot to override. It happened three times in one quarter. Check your numbers before you sign out.
Get the Full Details

Assessment Section
This is the hardest part to write well. You need to connect the objective data to the diagnosis and explain why the treatment is still needed. The assessment is where you justify medical necessity. I learned this the hard way when an auditor rejected a full episode of care because the assessment section only contained progress descriptions without linking back to the functional limitations in the plan of care. Here's the counter-intuitive part that nobody teaches you: the assessment doesn't need to show dramatic improvement every visit. It needs to show continued need. A patient who plateaus at 65% of baseline function for three visits still qualifies for continued therapy if you document the specific barrier and the plan to address it. The mistake people make is writing "no progress" and then stopping the notes, which looks like abandonment. Write "progress limited by pain and fatigue. Plan: modify intervention strategy to address barriers." That's a clinically sound assessment. You also need to tie everything back to the ICF framework. International Classification of Functioning, Disability and Health. It's not just jargon. CMS and most private insurers expect to see the connection between impairment-level findings and activity-participation level goals. If your note only addresses shoulder range of motion without mentioning how that affects dressing or feeding, it's incomplete from a documentation standpoint.
Complete SOAP Note Example
Here is a full example from a geriatric outpatient case. The patient is a 78-year-old female post-right total hip arthroplasty, six weeks out, with diagnoses of osteoarthritis and mechanical fall risk. Subjective: Pt reports increasing difficulty with stair negotiation at home, stating "I can manage the bottom three steps but the top three make my hip stiff and I hesitate." Reports using a front-wheeled walker for community ambulation but has stopped using it indoors due to "clutter from family members moving it around." Denies falls in past 30 days. Pain rated 4/10 at rest, 7/10 with prolonged standing beyond 10 minutes. Objective: ROM: Right hip flexion 95°, extension 5°, abduction 30°, external rotation 20°. Left hip ROM WNL. Strength: Right hip extensors 4-/5, abductors 4/5, quadriceps 4/5. Right lower extremity. Gait: 20 ft walk with FWB, 2-speed CWB, moderate contact RLE assistance. Antalgic pattern present on R side. Stair negotiation: step-to pattern with rail, requires 45 seconds for 8 steps with rail, guarded presentation. Balance: Single leg stance RLE 4 seconds (eyes open), BLES 8/10. Functional: Bed to chair transfer independent with sliding board, moderate verbal cueing for hip precautions. Modified Barthel Index: 85/100.
Assessment: Pt demonstrates persistent gait deviations and stair difficulty related to right hip abductor/extensor weakness and protective movement patterns post-THA. Current interventions are addressing ROM and strengthening gains; however, community mobility and stair safety remain compromised. Pt's home environment barriers (walker storage issues) present ongoing safety concerns. Continued OT recommended to address higher-level functional tasks and home safety planning. Progress toward goal 2 of 3 goals met. Goals 1 and 3 remain in progress. Plan: Continue OT 2x/week for 4 weeks. Interventions: continued strengthening R hip abductors/extensors, gait retraining with focus on symmetrical step length, stair training progression, home safety assessment and caregiver education. Discharge criteria: independent stair negotiation with rail, gait distance 150 feet without assistive device, modified Barthel score 95 or above. Next eval in 4 weeks.

Common Mistakes That Get Notes Flagged
The biggest issue I see is templated notes that don't match the patient. I had a colleague whose entire caseload had the exact same objective section word-for-word except the patient's name was swapped. The ROM values were identical across five different diagnoses. An auditor caught it in a random review. The clinic had to repay $47,000 in claims. This isn't hypothetical. It happened in 2023 in the Midwest. Another common problem is billing for time that isn't documented. If you bill 22 minutes of re-evaluation but the note shows 15 minutes of direct contact time with 7 minutes unaccounted for, that's a red flag. Time billing needs to add up. Every minute matters during an audit. Goal tracking is the third major pitfall. Goals that are never updated, goals that are impossible to measure, or goals that don't match the diagnosis. "Improve quality of life" is not a measurable goal. "Increase community ambulation distance from 100 feet to 300 feet with walker" is measurable. Write goals that you can actually measure.
What Works in Practice
Keep a running list of functional benchmarks for common diagnoses. Post-stroke upper extremity, you should know what typical milestones look like at two weeks, four weeks, six weeks, twelve weeks. When your patient falls outside the expected range, that's clinically interesting and worth documenting specifically. When they're right on track, you can still document it efficiently because you know what standard performance looks like for that condition at that stage. Dictation with a speech-to-text tool cut my documentation time from roughly 12 minutes per note down to about 4 minutes. The key is talking in full clinical sentences rather than phrases. Say "Patient demonstrated fair trunk control during seated balance activities with moderate cueing" instead of "good balance moderate cue." The latter requires you to fill in words afterward, which takes more time than just speaking clearly in the first place. I use a hybrid system. I write the SOAP structure in my head as I'm finishing the session, then I dictate it immediately while the details are fresh. I review the generated text for accuracy, fix any misheard medical terms, and attach it to the chart. The whole process takes about five minutes per note after the habit is established.
The Bottom Line
Good occupational therapy notes are not creative writing exercises. They are structured clinical records that need to withstand scrutiny from insurance reviewers, auditors, and other providers. The format is rigid. The content should be specific. The justification should be clear. Write like someone will read it twice and try to find a reason to deny payment. Because someone will.