What you need to know before using ofloxacin drops for bacterial conjunctivitis
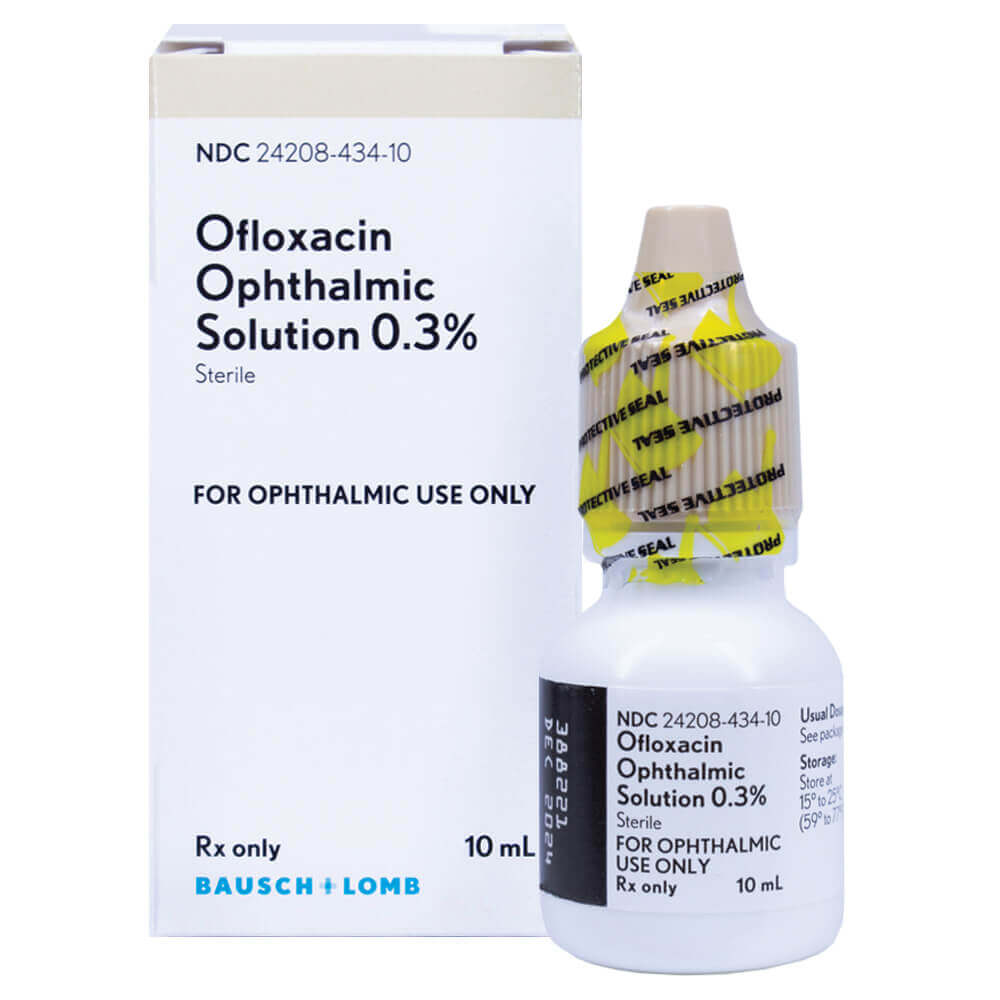
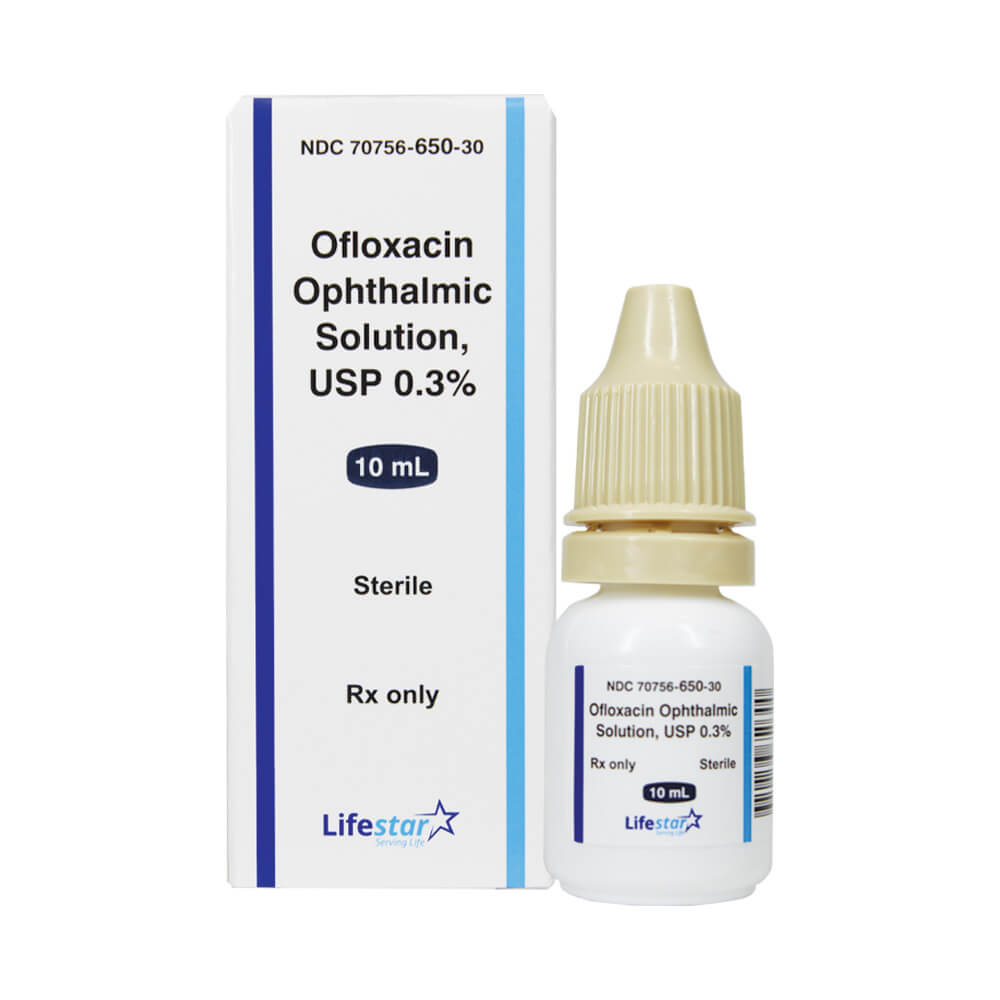
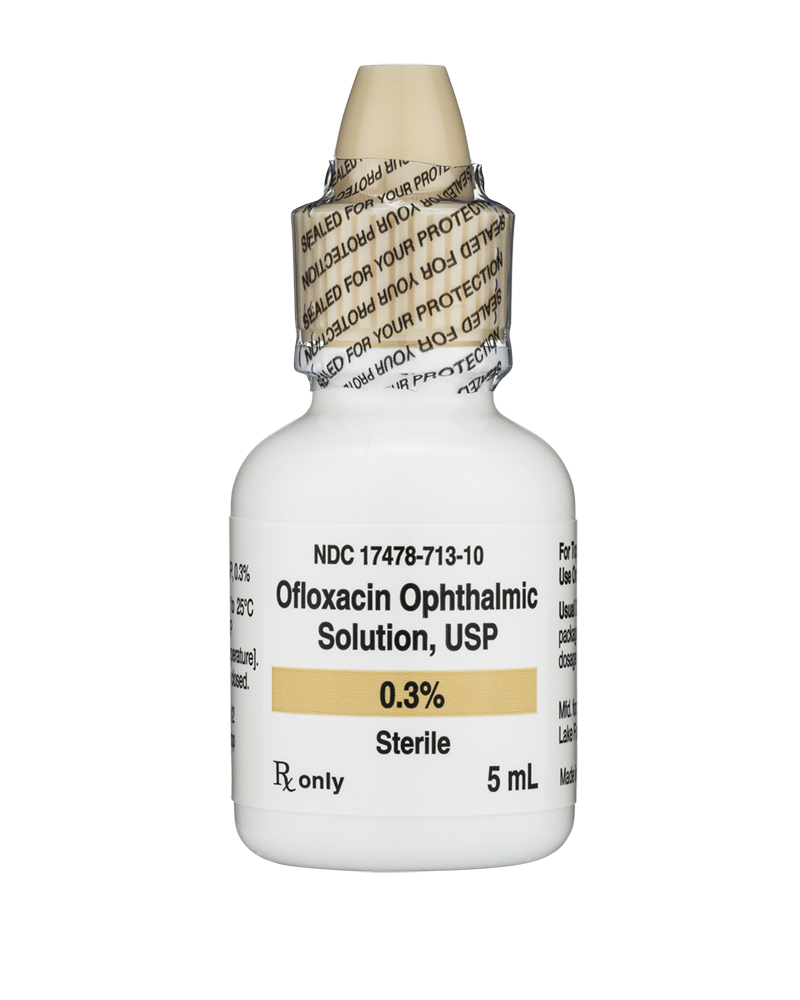
Ofloxacin ophthalmic solution 0.3% is a fluoroquinolone antibiotic eye drop prescribed for bacterial pink eye. It's not a cure-all. It doesn't touch viral conjunctivitis, and it's overkill for most allergic reactions. But when you have a confirmed or strongly suspected bacterial infection, it does what it says on the bottle. The drug kills bacteria by inhibiting DNA gyrase and topoisomerase IV, which stops them from replicating. That's the textbook version. In practice, you're instilling one drop into the affected eye(s) two to four times daily, usually for seven to fourteen days depending on severity. I've seen protocols vary widely between clinicians. Some prescribe ten days. Others push for two weeks even for mild cases. The drop itself is slightly viscous. It stays on the ocular surface longer than plain saline, which helps with absorption. One thing people get wrong is the timing between drops if they're using multiple formulations. If you need a steroid drop alongside ofloxacin, wait at least five minutes between each. Stacking them immediately just flushes the first one out before it does anything.
I ran into a specific issue with a patient who kept complaining the drops weren't working. Two days in, no improvement. Turned out they were rinsing their eyes with tap water between doses, which literally washed the antibiotic away and introduced new contaminants. They switched to preservative-free saline for cleaning and stuck to the dosing schedule. By day three, the purulent discharge stopped. By day five, the redness was noticeably down. It's a small thing but it matters more than most people realize. Important: Do not wear contact lenses while you have an active infection and while you're on this medication. Ofloxacin contains preservatives that can bind to soft contact lenses and irritate the cornea. You need to be lens-free for at least forty-eight hours after symptoms resolve before putting anything back in.
Common pitfalls and what the package insert won't tell you
The most common mistake I see is stopping the drops too early. People feel better around day three or four and assume they're cured. Bacterial load drops fast with fluoroquinolones, but eradicating the infection completely takes the full course. Stopping early is how you get resistant strains and recurrent conjunctivitis, which then forces you into a stronger antibiotic anyway. Another issue is contamination of the dropper tip. Once that tip touches your eyelid, eyelashes, or any surface, the entire bottle is compromised. I've watched patients cap the bottle with the tip resting on their desk and then use it again an hour later. Don't do that. Hang the bottle upside down for a few seconds after each use to clear the tip, and never let it make contact with anything. Some people report a bitter taste in the back of their throat after instilling the drop. That's the medication draining through the nasolacrimal duct into the nasal cavity and hitting the taste receptors. It's unpleasant but harmless. To reduce it, press gently on the medial corner of your eye — the tear duct area — for about sixty seconds after applying the drop. That simple maneuver blocks most of the drainage and keeps more medication on the ocular surface where it belongs.
Get the Full Details

When ofloxacin isn't the right call
Not all pink eye is bacterial. Viral conjunctivitis, which is far more common, especially in community outbreaks, will not respond to ofloxacin. It's self-limiting and usually resolves on its own within ten to fourteen days. Using an antibiotic for a viral infection is pointless and contributes to resistance. Allergic conjunctivitis responds to antihistamine or mast cell stabilizer drops, not antibiotics. If you're unsure whether your conjunctivitis is bacterial or viral, a clinician can do a quick slit-lamp exam and sometimes a culture. Bacterial infections typically present with thick yellow or green purulent discharge that crusted the eyelids shut overnight. Viral infections tend to produce a watery or stringy discharge and often start in one eye before spreading to the other. If you have significant pain, light sensitivity, or blurred vision that doesn't clear with blinking, that's a red flag for something more serious like keratitis or uveitis, and you need prompt evaluation rather than waiting it out.
Dosing and storage specifics
Store the bottle at room temperature, away from light and moisture. Don't keep it in the bathroom cabinet where humidity fluctuates. Once opened, most formulations are good for twenty-eight days. After that, the preservative system degrades and contamination risk goes up. Label the bottle with the open date so you don't have to guess. The typical adult dosing is one drop in the affected eye(s) every two to four hours during the first two days, then reduced to one drop four times daily. Pediatric dosing follows the same schedule unless your prescriber adjusts it. There's no systemic absorption concern at these doses for most patients, but fluoroquinolones carry warnings about tendon rupture and QT prolongation when taken orally. The ocular route minimizes those risks significantly, but if you have a history of tendon issues or are on medications that prolong QT, mention it to your doctor before starting treatment. Side effects from ofloxacin ophthalmic solution are generally mild: temporary stinging upon instillation, mild conjunctival injection, dry eye sensation, and occasionally headache. Serious adverse reactions like corneal toxicity or hypersensitivity are rare but documented. If you develop severe eye pain, worsening redness, or changes in vision after starting the drops, stop using them and contact your provider immediately.
I've also seen patients try to supplement with over-the-counter artificial tears during treatment. That's fine, but separate them by at least ten minutes from the antibiotic drop. Applying tears right after the ofloxacin dilutes it and reduces efficacy. Preservative-free tears are the safer choice if you're going to use them frequently, since benzalkonium chloride in some formulations can irritate an already inflamed eye. There's no reliable free download of this medication since it's a prescription-only product. Any site offering to sell you ofloxacin ophthalmic solution without a prescription is operating illegally, and the product quality is unverifiable. Stick to pharmacy-sourced bottles with intact seals. The difference between a legitimate prescription and an unauthorized source isn't just legal — it's about sterility, concentration accuracy, and whether the preservative system is actually intact. If bacterial conjunctivitis is mild and your clinician feels comfortable with watchful waiting, some guidelines support observation for up to three days before starting antibiotics, since a significant portion of presumed bacterial cases resolve spontaneously. But if symptoms are moderate to severe, or if you're in a high-risk group — contact lens wearer, immunocompromised, or working in environments with high exposure risk — starting ofloxacin promptly is reasonable and standard practice.