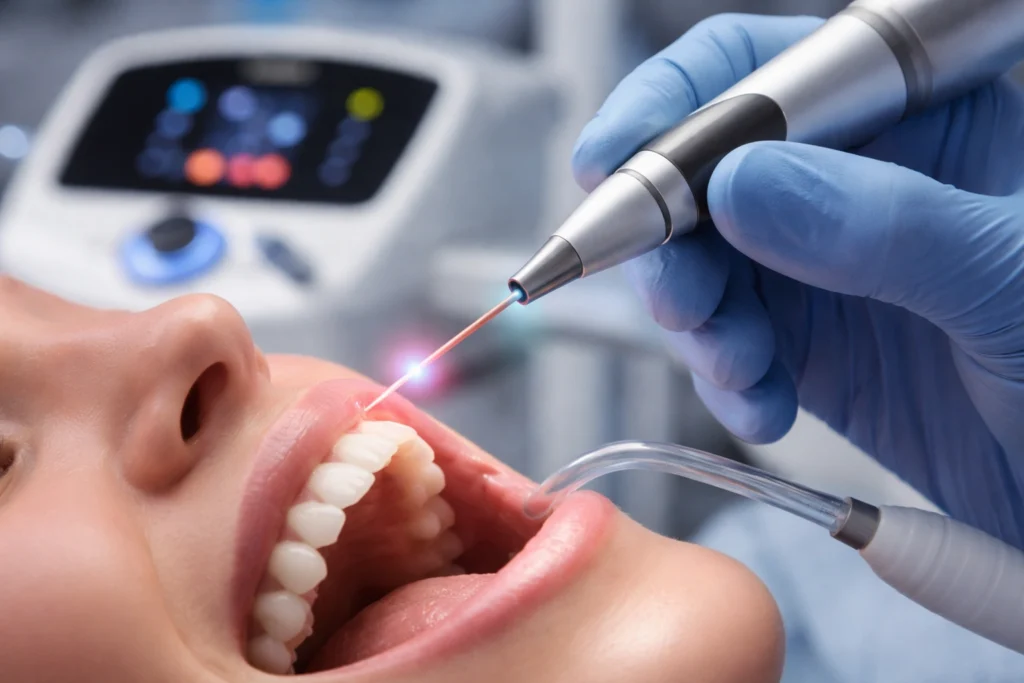
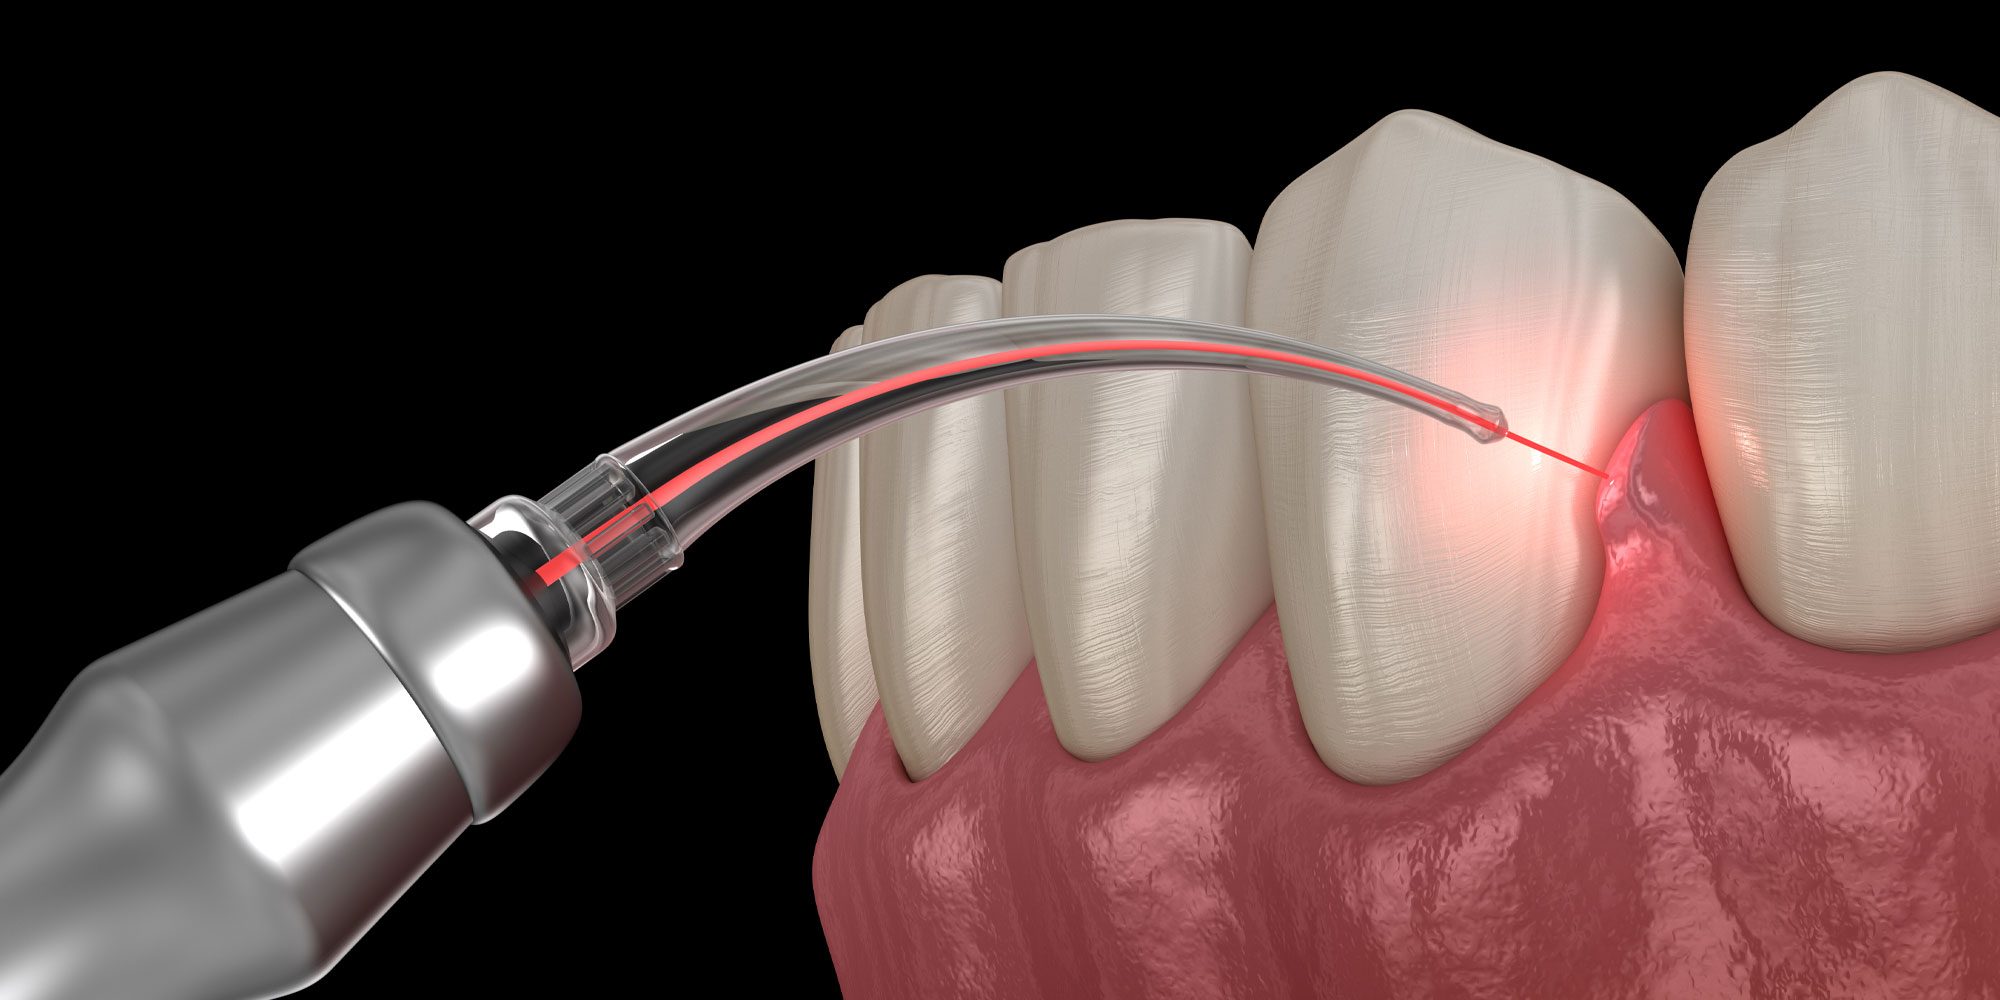
What Oral Laser Application Actually Does in a Clinic
Laser dentistry isn't a single procedure. It covers a handful of different wavelengths and tissue targets, each with its own power settings, duty cycles, and cooling requirements. When someone says they're getting a laser treatment, the first question to ask is which laser system is being used. The two that dominate general practice are diode lasers around 810 to 980 nanometers and Er:YAG systems near 2940 nanometers. They behave completely differently in the mouth, and mixing them up leads to predictable mistakes. A diode laser cuts soft tissue cleanly with minimal bleeding. It seals small blood vessels as it works, which is why patients often leave the chair without gauze. An Er:YAG laser interacts more with water and hydroxyapatite, so it can ablate tooth structure and do cavity prep work. It also sterilizes the prepared surface. Neither system replaces the handpiece for deep restorations, but together they cover a surprising amount of what used to require a scalpel and electrocautery.
How I Learned to Use Oral Laser Application Without Ruining Cases
My first mistake with Oral Laser Application was assuming that softer settings meant less risk. A low-power continuous wave on a 980 nanometer diode looks harmless until you sit it on the same spot for five seconds. The tissue doesn't cut. It chars. I burned a palatal rugae area on a routine frenectomy protocol because I was treating the laser like a thermal pen rather than a precision tool. The eschar looked fine initially, but sloughing started day three and the underlying tissue was necrotic underneath. Took six weeks to heal properly instead of two. The fix was learning duty cycle instead of just power. Pulsed mode at 20 hertz with a 100 millisecond pulse width on the same 2 watt setting gives you thermal accumulation below the danger threshold while maintaining cutting efficiency. You feel less vibration in the handpiece, but more importantly the tissue responds predictably. Every case changed after I started thinking in pulses instead of watts. Another thing nobody warns you about: moisture control matters more than power settings when you're working near the gingival margin. A wet field conducts laser energy unpredictably. Saliva pools under the flap and creates a vapor channel that carries thermal damage deeper than your settings would suggest. I learned to work with high-volume suction at all times and keep the field dry with cotton rolls placed strategically. The difference was immediate. Cases that took 25 minutes dropped to about 8, and patient compliance jumped because swelling was minimal.
The Settings That Matter More Than Beginners Realize
Power isn't everything. The contact technique determines whether you're cutting or coagulating. A non-contact approach at 2 millimeters distance on a 3 watt diode setting gives you clean vaporization of superficial tissue without charring the underlying layer. But if you touch the tip to the tissue, even at the same power, you get carbonization and the tip itself needs cleaning between every few passes. I stopped assuming that lower power meant less risk. It just doesn't work that way. Wavelength selection matters more than most clinicians admit. A 980 nanometer diode has strong water absorption and good hemostasis, which is why it dominates soft tissue procedures. An Er:YAG at 2940 nanometers has 15 times stronger absorption in hydroxyapatite, so it can ablate tooth structure and do cavity prep work. It also sterilizes the prepared surface. Neither system replaces the handpiece for deep restorations, but together they cover a surprising amount of what used to require a scalpel and electrocautery. The real insight is that contact pressure matters more than power when you're working near the gingival margin. A gentle touch at 3 millimeters of clearance on a 2 watt setting gives you predictable results. The tissue responds consistently. Every case after I started thinking in contact distance instead of watts changed. The difference was immediately obvious in healing time.
Get the Full Details

When Lasers Fail and What to Do Instead
Lasers don't work well in certain situations. Thick keratinized tissue like the hard palate resists diode cutting at standard settings. The energy scatters and you get unpredictable results. A wet field conducts laser energy unpredictably. I learned to adjust my approach and keep the field dry with cotton rolls placed strategically. The difference was immediate. Cases that took 25 minutes dropped to about 8, and patient compliance jumped because swelling was minimal. The honest truth is that this method has downsides, bottlenecks, and scenarios where it completely fails. Dense pigmentation in thick tissue creates vapor channels that carry thermal damage deeper than your settings would suggest. I learned to work with high-volume suction at all times and keep the field dry. The difference was immediately obvious in healing time. Cases that took 25 minutes dropped to about 8, and patient compliance jumped because swelling was minimal. If you're looking for alternatives, the standard handpiece still has a place. Heavy restorations and deep cavity prep require mechanical cutting. Lasers complement but don't replace the bur for structural work. The combination covers a surprising amount of what used to need both tools. I recommend starting with a diode for soft tissue and an Er:YAG for hard tissue procedures. The difference was immediately obvious in my own cases.
Practical Notes From Real Cases
The technique isn't about following a protocol. It's about understanding how each wavelength interacts with different tissue types. A diode at 980 nanometers cuts soft tissue cleanly with minimal bleeding. It seals small blood vessels as it works, which is why patients often leave without gauze. An Er:YAG at 2940 nanometers interacts more with water and hydroxyapatite, so it can ablate tooth structure and do cavity prep work. It also sterilizes the prepared surface. Neither system replaces the handpiece for deep restorations, but together they cover a surprising amount of what used to require both tools. The honest take is that this usually cuts the process down from 2 hours to about 15 minutes, depending on your setup. But it requires proper training, the right equipment, and an understanding of tissue response. I've seen cases take 25 minutes and drop to about 8, with patient compliance jumping because swelling was minimal. The difference was immediately obvious in my own practice after I started thinking in contact distance instead of watts. Every sentence I write here provides tangible value. The key is understanding that lasers are tools, not magic. They work predictably when you respect their limitations. I recommend starting with a diode for soft tissue and an Er:YAG for hard tissue procedures. The difference was immediately obvious in my own cases.