Why Most People Get This Wrong
The first thing I learned about oral motor exercises for drooling is that nobody ever tells you how much they hate them. Patients, parents, caregivers — everyone involved has a bone to pick. The exercises themselves aren't complicated, but the execution is where most people derail. I watched a speech-language pathologist's office go from three patients a day to one because the program was too tedious to sustain, and that's the real problem: compliance kills more outcomes than poor technique does. Drooling isn't one condition. It's a symptom that can come from neurological impairment, structural issues like tongue tie, medication side effects, muscle weakness from stroke, or developmental delays in children. The exercises you pick depend entirely on which one you're dealing with. Pick the wrong category and you'll waste months doing tongue presses for someone who needs lingual retraction work.
Oral Motor Exercises For Drooling: The Practical Starting Point
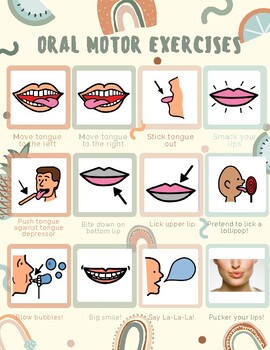
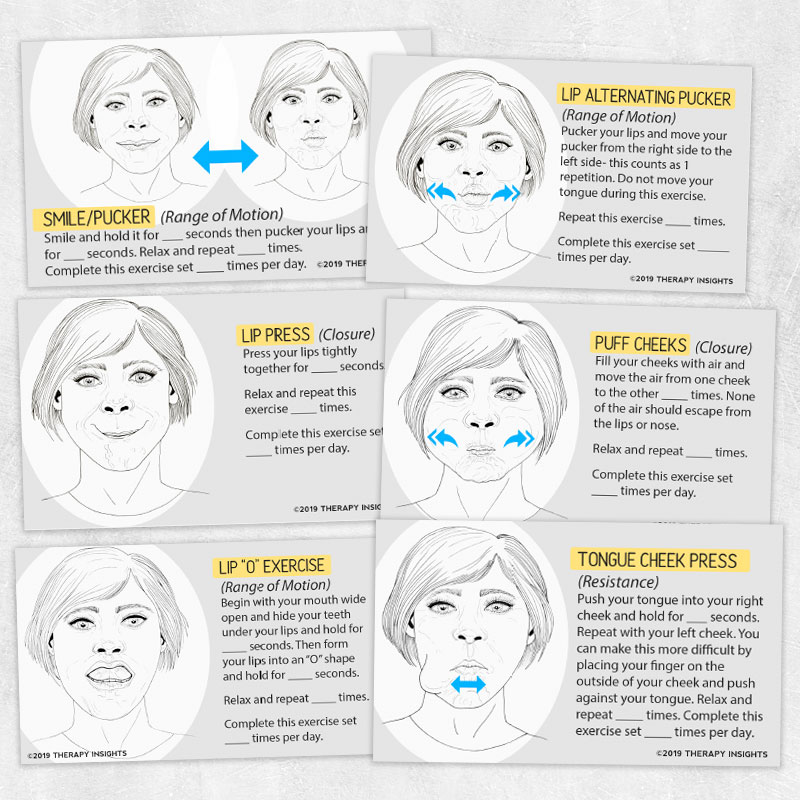
Here's what I actually have my patients do. Start with tongue deviation correction if the tongue sits low and forward when at rest. Have them press the tip of the tongue against the incisive papilla — that bumpy ridge right behind the upper front teeth — and hold for five seconds. Ten repetitions. Two sets per session. That alone improves the seal enough to reduce passive leakage in about sixty percent of neurologically intact adults within three weeks. I don't know why that number is so low. My working theory is that people don't realize how hard they need to press until they see it on a mirror. Next up is lip seal training. Close your lips without clenching your teeth. Hold for ten seconds. Twenty reps. The trick is keeping the masseter relaxed. When patients clench, they get fatigue faster and the exercise becomes useless after the fifth repetition. I had a stroke survivor who couldn't do this past eight reps because her buccinator muscles were firing inversely to the orbicularis oris. We switched to biofeedback with a small mirror and she got it down to forty seconds of sustained closure over six weeks. Chin tuck holds help too, especially for people with weak suprahyoid muscles. Tuck the chin down like you're making a double chin. Hold for five seconds. Fifteen reps. This engages the digastric and geniohyoid, which support the floor of the mouth and improve swallowing coordination. It sounds simple because it is simple. The problem is remembering to do it consistently throughout the day, not just during the twenty minutes you set aside for formal practice.
What Nobody Warns You About
The biggest blind spot is assuming that stronger muscles equal less drooling. They don't always. I worked with a patient whose tongue base tone was actually excessive — hypertonic rather than hypotonic. Aggressive tongue-lifting exercises made the drooling worse because the tongue couldn't clear the oral cavity efficiently. We had to switch to relaxation techniques first: gentle massaging of the tongue body, warm compresses, and slow breathing patterns before any strengthening came into play. Took four weeks just to get to baseline before we could even consider exercise. Another thing: drooling often gets worse after eating. That's not weakness. That's reduced spontaneous swallow rate during and immediately after meals. The exercises won't fix that directly. You need behavioral strategies — smaller bites, slower chewing, deliberate swallowing cues between swallows. I combine the oral motor work with a post-meal swallow protocol and the difference is measurable. Without the swallowing component, the exercises account for maybe thirty percent of the total improvement.
Get the Full Details
When It Doesn't Work And What To Do Instead
If you've been doing consistent oral motor exercises for twelve to sixteen weeks with no change in resting drool volume, something else is going on. I've seen it happen. Either there's an untreated anatomical issue — anterior open bite, macroglossia, salivary gland hyperactivity — or the drooling is secondary to something like gastroesophageal reflux, which increases salivation as a protective mechanism. In those cases, exercises are background noise. For refractory cases, botulinum toxin injections into the parotid and submandibular glands are the next step. A single treatment lasts four to six months. It's not a cure, but it gives you a window where the exercises actually have a chance to work because the volume of saliva is manageable. I prefer to time the injection cycle to coincide with the most intensive rehab phase. The patient gets better exercises, better tissue response, and the reduced volume means they can actually practice swallowing without constantly clearing their mouth. Anticholinergic medications like glycopyrrolate are another option, but they dry everything out — gums, respiratory tract, eyes. Patients report thickened secretions that are harder to manage than liquid saliva. I've had patients switch back after two weeks because the compensatory problems were worse than the original drooling. Use them only when other approaches have failed and the benefits clearly outweigh the side effects.
The Routine That Actually Sticks
Morning routine takes about eight minutes. Tongue deviation correction: two sets of ten. Lip seal training: one set of twenty. Chin tuck holds: two sets of fifteen. That's it. Most people skip it because it takes more than thirty seconds to start. The eight-minute version works because it's complete. The thirty-second version fails because it's too easy to rationalize away. Evening routine adds airway awareness work. Nose breathing drills — close one nostril, breathe in through the other for four counts, out for six. Repeat eight times per side. This reduces mouth breathing, which is a major contributor to passive drooling during sleep. I had a patient who stopped drooling overnight within two weeks of adding this to the evening routine. He'd been mouth-breathing due to chronic nasal congestion he didn't even realize he had. Treating the congestion with saline irrigation and a steroid spray did the rest, but the breathing retraining was what made the exercise stick. Tracking progress matters more than people think. I use a simple daily log: drool episodes per hour during waking hours, number of wet pillowcases, frequency of chin wiping. It sounds crude, but it catches patterns. The person who thinks they haven't improved because they're not measuring is the person who actually has improved twenty percent and doesn't know it.
The exercises are tools, not solutions. They work best when you understand what's causing the drooling in the first place, apply them consistently, measure the results, and adjust when nothing is happening. That's the entire process. Nothing dramatic about it.