Working with Organs And Skeletal System Models in Practice
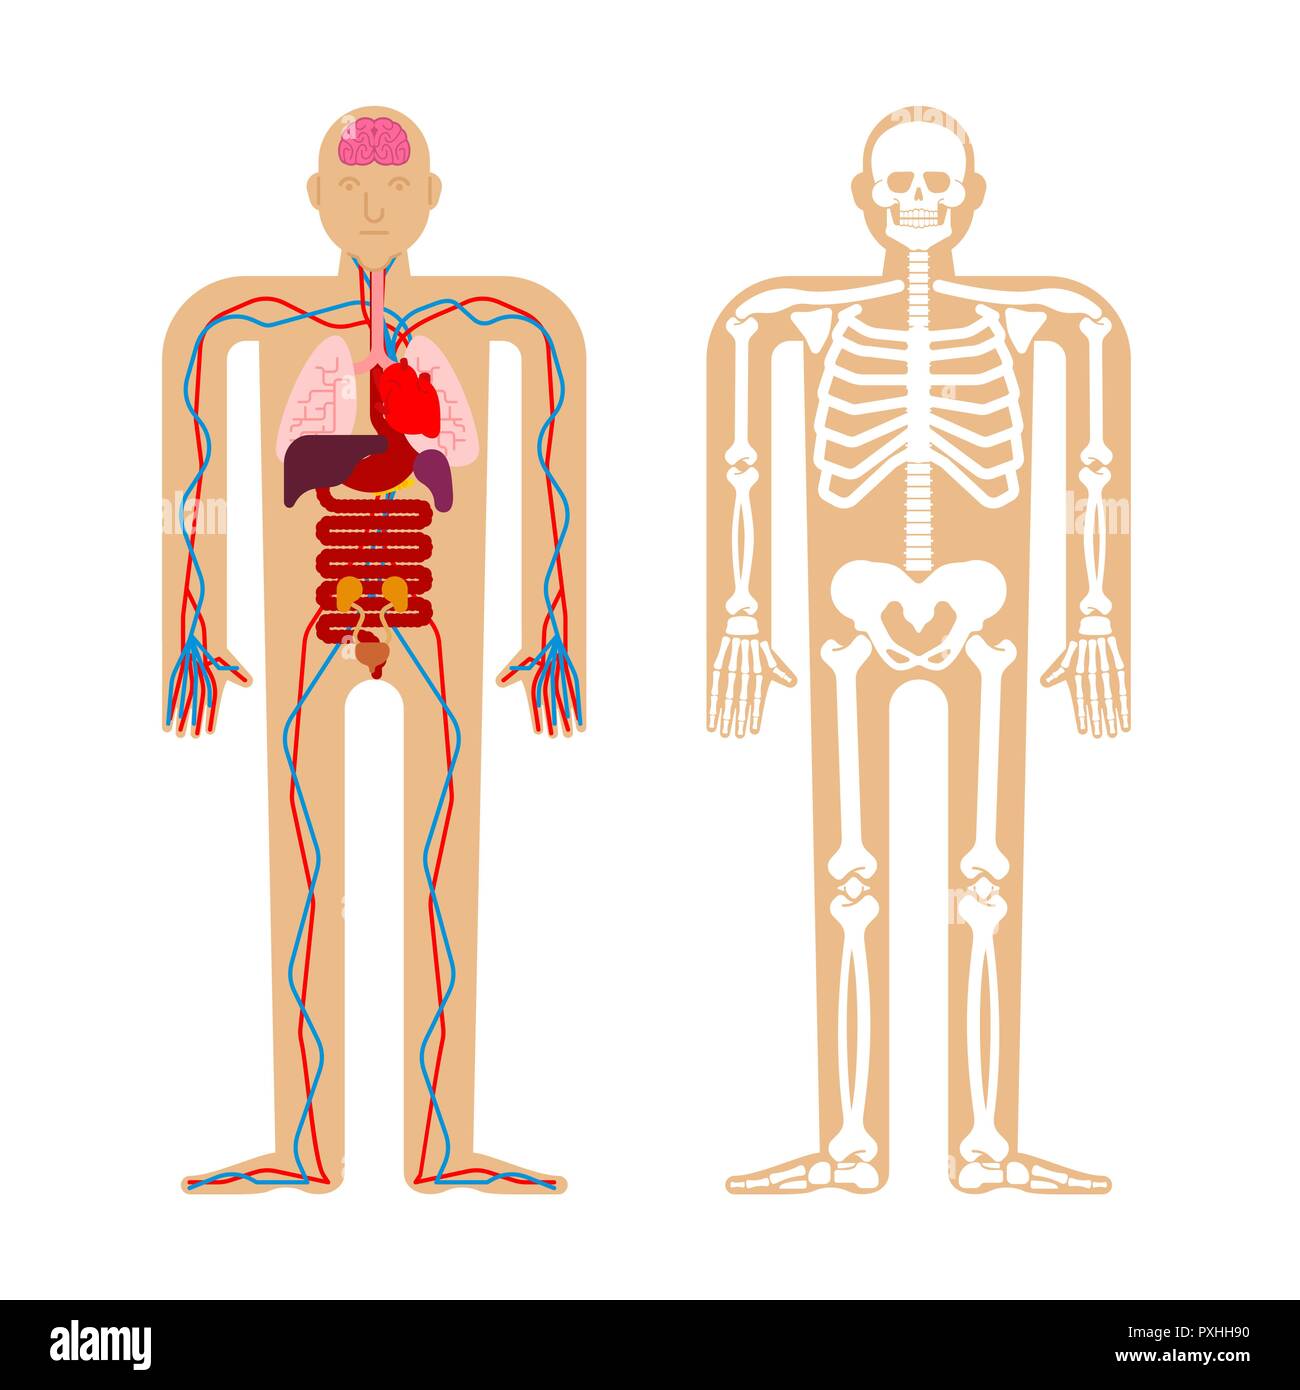
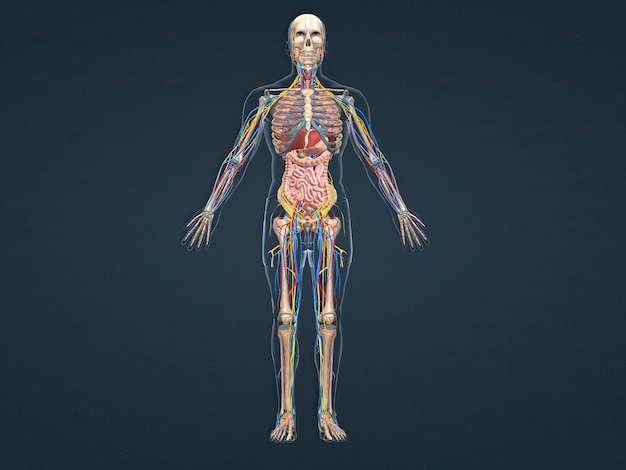
Most people treat the organ and skeletal systems as separate chapters in a textbook, but when you are actually working with them—whether in 3D modeling, animation rigging, or medical visualization—you quickly realize they operate as one continuous mesh of biomechanical constraints. The skeleton provides the structural framework, and the organs occupy the voids between bones, but neither moves independently without consequences. I spent about three years building anatomical rigs for game development before I started consulting on medical visualization projects. One of the first things you learn is that most tutorials get the hierarchy wrong. They place the rib cage as a child of the spine, which seems logical, but in reality the thoracic cavity should be parented to the pelvis in most IK setups. The spine moves too much on its own, and when you parent the ribs to it, the entire chest collapses in ways that look physically impossible during animation cycles.Why Organs And Skeletal System Integration Matters
If you are just learning anatomy, the standard approach is memorization: learn the bone names, learn the organ locations, repeat. That works for passing exams. It does not work for anything that requires understanding how these systems interact under load or movement. The skeletal system is not a static frame. Every bone is a living organ itself, and it responds to mechanical stress by remodeling its density. The organs are suspended in fascia, which is basically a continuous web of connective tissue that runs from the skull down to the feet. When you pull on one part of that web, it affects tension throughout the entire system. This is why back pain can originate from ankle issues, or why a tight psoas muscle can compress internal organs and cause digestive problems. I ran into this exact problem when working on a biomechanics simulation for a sports medicine clinic. We were modeling how sprinters distribute force through their bodies, and the initial version had completely unrealistic organ displacement. The liver and spleen, which should be relatively fixed by their ligamentous attachments, were floating around like loose objects in a backpack. The fix was adding elastic constraints between the major organs and the nearby skeletal structures, with different stiffness values for each organ based on its actual tissue composition. The liver is dense and heavy, so it needs stronger constraints than the stomach, which is more mobile.Countless beginners skip the fascial layer entirely, and that is usually why their models or simulations look wrong even when the bones and organs are individually correct. The body is not a bag of organs sitting on a skeleton. It is a tensegrity structure where every component influences every other component.
How to Approach This Properly
Start by understanding the myofascial chains rather than individual muscles. The superficial back line runs from the bottom of your feet, up through the calves, hamstrings, glutes, entire spine, and all the way to your forehead. When any part of that chain is restricted, it creates compensatory tension elsewhere. This is basic somatic practice, but it matters enormously if you are building anything that needs to move realistically. For skeletal modeling, work from the inside out. Build the pelvic girdle first because it is the foundation everything else hangs from. The sacrum sits between the ilium bones, and the hip joints articulate there. Get that right, and the spine has a proper base to build upon. Most people start with the spine and work downward, which is backwards. The lumbar vertebrae bear the most mechanical load, and if the pelvis is not correctly positioned, the entire spinal curvature will be wrong.Common Mistakes I See Repeatedly
The most frequent error is treating the diaphragm as just another muscle. It is not. It is the primary respiratory muscle and also a major dissociation point between the upper and lower body. In breathing mechanics, the diaphragm descends during inhalation, which increases intra-abdominal pressure and creates a corset effect around the spine. This pressure stabilization is why core strength and breathing are so deeply connected in athletic performance. Another mistake is ignoring the difference between visceral fat and subcutaneous fat in organ positioning. Visceral fat wraps around the organs and can shift their placement significantly. I worked on a project where we had to simulate obesity-related biomechanical changes, and the initial model placed the organs in anatomically correct positions regardless of body mass. That produced unrealistic results because in actuality, increased visceral fat pushes organs upward and changes their relationships to surrounding structures.Don't assume standard anatomical position applies to every body type. The organs shift. The skeletal alignment changes. A person with kyphosis has a completely different organ arrangement than someone with a neutral spine, and this matters for both animation and medical planning purposes.
The Fascial Web and Its Practical Implications
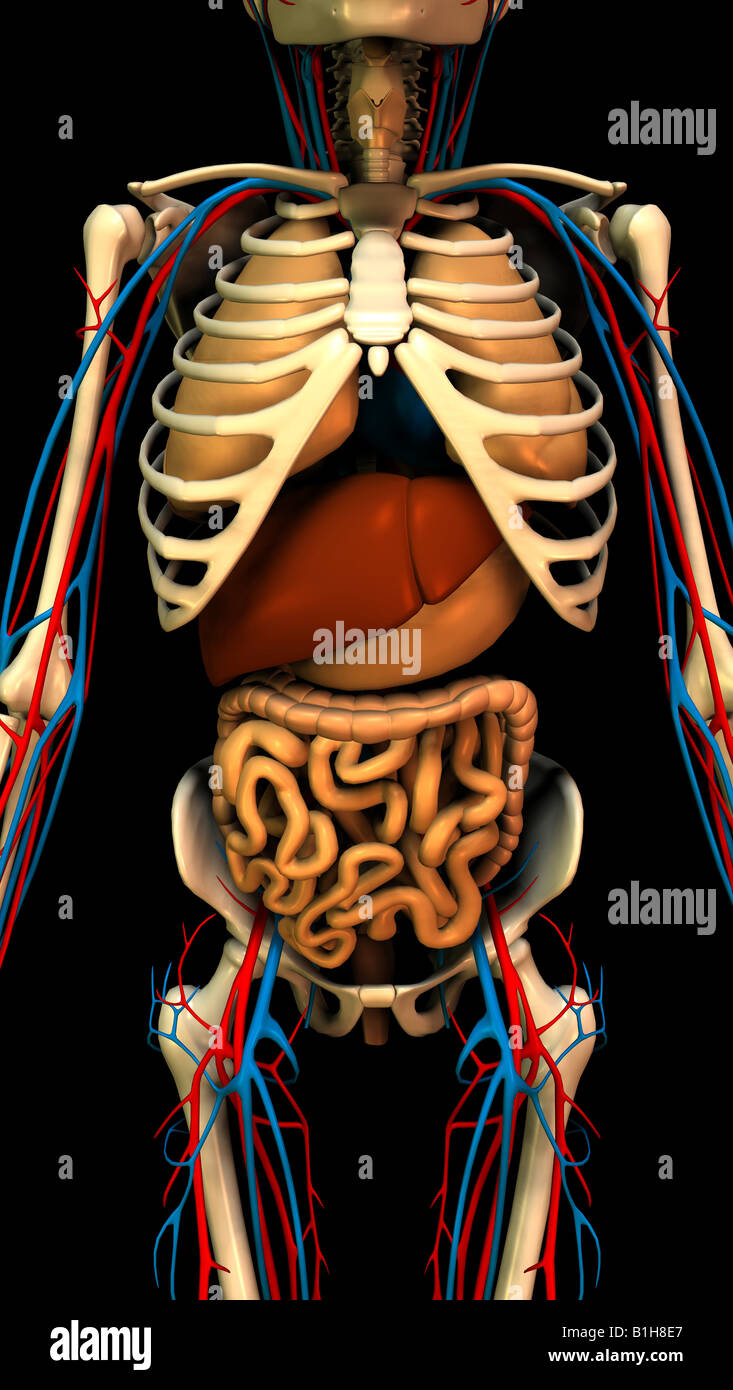
Here is something most introductory materials do not emphasize enough: the organs are not simply sitting in cavities. They are suspended and anchored by mesenteries, ligaments, and fascial continuities that connect them directly to the skeletal system. The liver is attached to the diaphragm by the falciform ligament. The kidneys are retroperitoneal, meaning they sit behind the peritoneal cavity but are still connected to the posterior abdominal wall through fascial layers. The uterus is supported by a complex network of ligaments that extend to the pelvic bones. When I was building the medical visualization for a surgical training platform, we initially treated organ movement as simple translation within their cavities. That produced sterile, unnatural results. The breakthrough came when we added fascial tension lines between organs and their skeletal attachments. Now when the spine flexes forward, the abdominal organs shift in response to the changing fascial tension, and the movement looks physically accurate. The skeletal system itself has fascial connections too. The periosteum, which covers every bone, is continuous with the deeper fascial layers. This means that when muscles pull on bones, they are also transmitting force through the fascial network to adjacent structures. This is why trigger points in one muscle can refer pain to distant areas, and why structural problems often present symptoms far from their origin.What Happens When You Get the Hierarchy Wrong
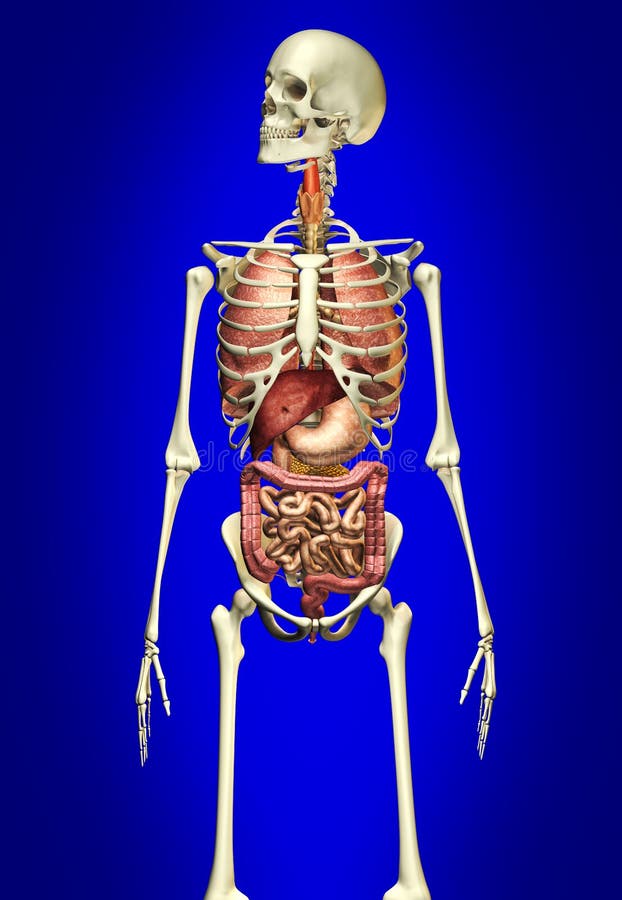
In 3D modeling terms, if you parent the rib cage to the spine and then animate spinal flexion, the ribs will follow the spine's rotation. But in the human body, the ribs have their own complex relationship with the thoracic vertebrae and the sternum, and they move somewhat independently during breathing and trunk rotation. The correct hierarchy in most rigging setups places the rib cage as a child of the root or pelvis, with IK handles that allow it to respond to spinal movement without being directly driven by it. This same principle applies to the organs. The stomach should not be parented to the liver. The intestines should not follow the spine as a single rigid unit. Each organ has its own range of motion constrained by its attachments, and simulating those constraints produces dramatically more realistic results than free-floating organs or rigid skeletal parenting. I lost about two weeks debugging a rig where the heart was displacing unnaturally during running cycles. The issue turned out to be the pericardial ligaments being too loose in the simulation parameters. The heart, which should move maybe a centimeter or two during normal locomotion, was translating nearly five centimeters vertically. Tightening those constraints to match real tissue stiffness values fixed it immediately.Practical Steps for Building Accurate Models
Get high-resolution CT or MRI scan data if you can. Atlas bodies are fine for reference, but they average out individual anatomical variation. Real patients have asymmetric rib cages, organs that sit slightly differently from the textbook illustrations, and soft tissue variations that change how everything fits together. I always keep a folder of scan data from different body types because the variations are significant and often overlooked. Work in layers. Start with the skeleton, then add the major organ masses with approximate positioning, then refine with fascial connections, then add the smaller organs and vascular structures. Each layer should be built on top of a stable foundation from the previous layer. Trying to add detailed organ textures before the skeletal framework is locked will cause cascading rework later.Test with extreme poses early. Most anatomical models look fine in neutral position. The real test is full flexion, extension, rotation, and combinations thereof. If something breaks or looks wrong in extreme poses, you have identified a hierarchy or constraint problem before it becomes a nightmare to fix downstream.
Get the Full Details