Glass Fiber Splinting in Orthodontic and Periodontic Cases
I keep seeing posts from residents and general dentists asking about bonding glass fiber splints for mobile teeth, so I figured I'd write down what actually works versus what the literature says should work. The two don't always line up. Glass fiber splinting uses a ribbon of E-glass fibers embedded in a composite matrix, usually 0.8mm to 1.2mm wide, bonded to the lingual surfaces of anterior teeth. The purpose is to distribute occlusal forces across multiple teeth rather than letting a single mobile tooth absorb all the trauma. In periodontics it stabilizes teeth with moderate to severe mobility. In orthodontics it's sometimes used to hold teeth in position after periodontal therapy or to maintain space when teeth are strategically extracted. The material itself doesn't move teeth. It just holds them where they are. I'll walk through the typical workflow for a maxillary anterior splint spanning canines, because that's the most common request.
Start with isolation. Glass fiber won't bond to anything wet, and saliva contamination is the number one reason these fail prematurely. A rubber dam is ideal. If you're doing lower anteriors where a dam is impractical, cotton rolls and a high-volume evacuator are mandatory, and you need to confirm complete dryness before proceeding. I once had a splint debond three weeks later because I didn't realize the patient had a deep floor-of-mouth fold that kept wicking saliva up against the lingual surfaces despite my best efforts with rolls. The fix was switching to a custom tray with gutta-percha packing around the area. Took ten extra minutes upfront and saved a recall appointment. Next, tooth preparation. You don't need to etch grooves into the enamel. That's an outdated step. Just clean the surface with pumice, rinse, and dry. If there's existing restorative material or calculus, remove it mechanically. The bond goes to enamel, not to old composite or biofilm. Etching comes next. Phosphoric acid gel at 37 percent for 30 seconds on enamel is the standard. For older patients with exposed root surfaces, cut that back to 15 seconds. Cementum and dentin don't respond well to long etching times, and you'll just create a sloppy hybrid layer that degrades faster.
Rinse thoroughly and dry until the enamel looks frosted. Not just dry, frosted. If it still looks glossy, you haven't removed the smear layer completely or there's residual moisture. Re-etch for another 10 seconds. Apply adhesive. A thin, even coat. Do not flood it. Blow it thin with air, then light-cure for the time recommended by the adhesive manufacturer. Most modern self-etch or total-etch systems cure in 10 to 20 seconds per surface. Now the fiber ribbon. Cut it to length so it spans from canine to canine on each arch, with the ends wrapping slightly around the distal of each canine for mechanical retention. This is important. A flat terminus on the distal of the canine is a stress concentrator. Wrap it 180 degrees around the contact area and you distribute the load much better. I learned this the hard way when the left lateral incisor segment of a splint fractured at the distal margin after six months of function. The patient had a heavy bite, and that unwrapped edge took every lateral force directly. After rewrapping both ends, I haven't had a recurrence in cases with similar bite patterns.
Get the Full Details
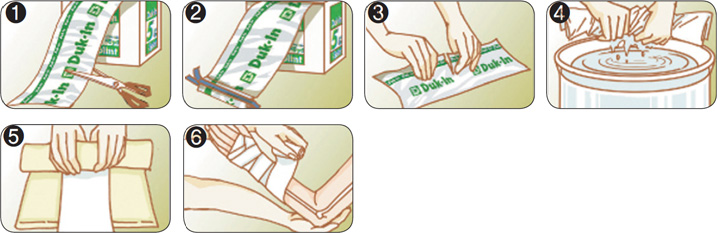
Impregnate the fiber with flowable composite or a low-viscosity splint material. Some people prefer a dedicated fiber reinforcement composite like Ribbond PerioBand or Transbond Plus, but any flowable works if you saturate it well. The fiber must be fully encased. You should not see bare glass strands through the cured material. That's a sign of incomplete wetting and it creates a pathway for microleakage. Position the splint. Press it firmly against the prepared teeth. Excess material should ooze out the margins, confirming good adaptation. Light-cure through the fiber from the facial side if your material is translucent enough. Most glass fiber ribbons are semi-translucent, so you can cure from both sides. Cure each segment for at least 20 seconds. The total cure time for a six-tooth splint is usually around 80 to 100 seconds of active curing, split between facial and lingual approaches. Remove excess material with a fine diamond or cutting disc, then polish. Rough surfaces accumulate plaque, and plaque accumulation on a splint is exactly how you get secondary caries and gingival inflammation around otherwise stable teeth.
Check the occlusion. This step gets skipped too often. Have the patient tap into maximum intercuspation, then slide laterally and protrusively. You should not feel the splint interfering with any contact. If it does, adjust it. A splint that catches on occlusion will either debond or cause trauma to the very teeth you're trying to protect.
Common Pitfalls That Aren't Obvious
The biggest mistake I see is under-preparing the case selection. Glass fiber splints are not a solution for teeth with hopeless periodontal prognosis. If a tooth has Grade 3 mobility, significant bone loss, and a vertical component to the mobility, splinting it to adjacent teeth just transfers the problem to healthy anchors. Those adjacent teeth will eventually degrade too. The right move is often extraction and replacement with an implant or bridge, not splinting. The fiber material is strong, but it can't compensate for a foundation that's already failing. Another pitfall is assuming the splint is permanent. It isn't. The average lifespan of a well-bonded glass fiber splint in the mandibular anterior region under normal function is three to seven years. In bruxers it might be two. You need to tell patients this clearly at the bonding visit. I schedule a six-month recall specifically to check the splint integrity, and I use a explorer to run along the margins and a mirror to check for any visible cracks in the composite mantle over the fiber. There's also the issue of cleaning. Patients need to be shown how to floss through and under the splint. A superfloss or threaded floss carrier is non-negotiable. Without it, the interproximal areas become plaque traps within weeks. I've seen gingival recession progress faster on splinted teeth in patients who couldn't commit to the flossing technique.

When Glass Fiber Isn't the Right Choice
For cases requiring longer-span splints, like premolar to premolar in the maxilla, stainless steel wire reinforced with composite or a cast metal framework is more predictable. Glass fiber has tensile strength, but it has limited flexural rigidity over longer distances. It will bend under heavy occlusal loads across six or more teeth, and that micro-movement at the bond interface accelerates failure. I switch to wire-reinforced splints for spans longer than four anterior teeth, or whenever the patient has a documented bruxism habit. There's also a cost consideration. Glass fiber materials are reasonably priced, but the bond failure rate means replacement appointments add up. If you're working in a high-volume clinic and the patient's oral hygiene is poor, a removable splint or night guard might be more pragmatic than committing to a fixed bond you know will need revision. One final thing that isn't covered in most guides: the effect on radiographic interpretation. Glass fiber is radiopaque to varying degrees depending on the manufacturer. Some ribbons show up clearly on bitewings, others are nearly invisible. Check your material's datasheet. If it's hard to see on X-rays, you'll miss recurrent caries under the splint margins. I keep a reference card in the operatory with the radiopacity values for every product we stock so I'm not guessing during follow-up visits.