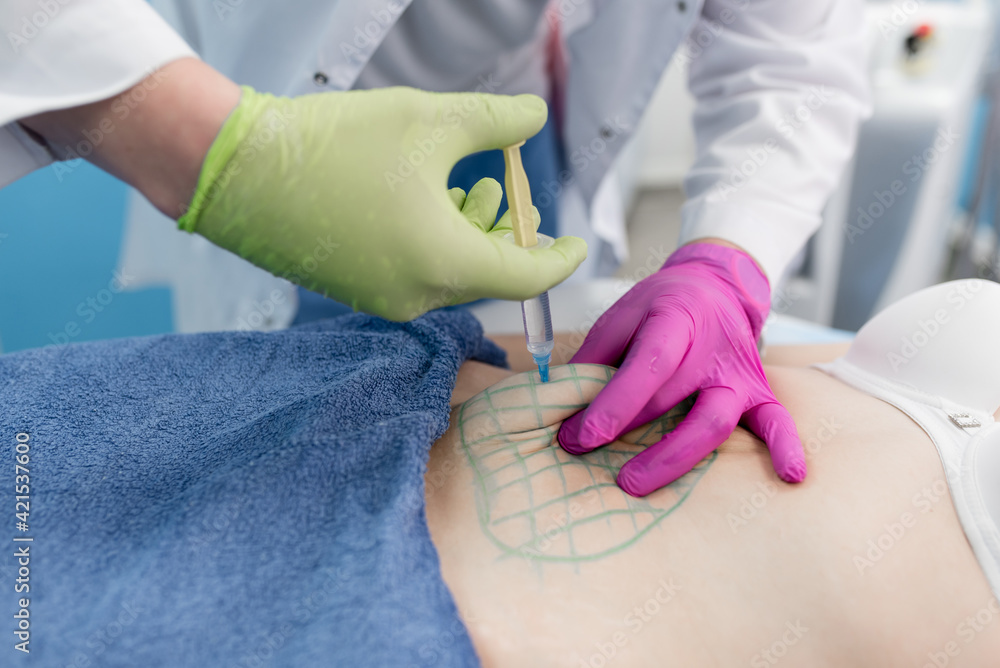
Ozone Injection Therapy: What It Actually Is and How It Works in Practice
Ozone injection therapy involves creating a medical-grade ozone-oxygen gas mixture and introducing it directly into damaged tissue, joints, or specific anatomical areas to promote healing and reduce inflammation. The gas is typically prepared using an ozone generator that passes electrical discharge through oxygen, producing a mixture that usually ranges from 20 to 50 micrograms per milliliter depending on the clinical protocol being followed. This is different from ozone therapy delivered through other methods such as major autohemotherapy, where blood is withdrawn, mixed with ozone externally, and then reinjected. Injection therapy targets specific anatomical structures directly. The primary mechanism involves localized oxidation of inflammatory mediators like prostaglandins and leukotrienes. When ozone contacts these molecules in the tissue, it breaks them down through a controlled oxidative process. The tissue response then includes vasoconstriction followed by reactive hyperemia as the ozone decomposes back into oxygen. This cycle appears to stimulate the release of nitric oxide and upregulates antioxidant enzymes such as superoxide dismutase and glutathione peroxidase. The practical result is reduced local inflammation and enhanced tissue oxygenation in the targeted area. Clinical evidence supporting ozone injection therapy is strongest for knee osteoarthritis and lumbar disc herniation, with multiple randomized controlled trials showing moderate improvement in pain scores and functional capacity over placebo. Research quality varies, and many studies have small sample sizes. The therapy is not universally accepted in mainstream orthopedics, though it has gained regulatory approval for medical use in several European countries.
Ozone Injection Therapy Technique
The injection technique depends entirely on the target anatomy. For intra-articular knee injections, the practitioner typically uses fluoroscopic guidance or ultrasound to locate the joint space precisely. A 22 to 25 gauge needle is advanced into the synovial cavity, and the ozone-oxygen mixture is administered slowly, usually between 10 and 20 milliliters per session. The injection itself takes approximately 30 seconds to 2 minutes. Patients often report a brief warming sensation during administration, followed by mild joint stiffness for several hours afterward. For intramuscular injections targeting myofascial trigger points, a smaller volume of approximately 5 to 10 milliliters is used with a 25 to 27 gauge needle. The injection depth varies from 1 to 3 centimeters depending on the muscle mass involved. Subcutaneous injection is employed for superficial conditions such as plantar fasciitis or localized tendonopathies. Here, the practitioner injects the gas mixture into the subcutaneous tissue plane just below the dermis, creating a raised bleb that gradually dissipates over 15 to 30 minutes. Treatment protocols typically involve weekly sessions for three to six weeks, though optimal frequency depends on the condition being treated and the individual patient response. Some protocols also combine injection therapy with topical ozone application or ozone-infused saline irrigation for wound management. I learned about a specific limitation through practical experience that most published protocols do not address adequately. When treating patients with a body mass index over 35, the standard intramuscular injection technique often fails because the needle length provided in typical medical supply kits is insufficient to reach the target muscle belly through the subcutaneous fat layer. A 1-inch needle commonly used for intramuscular injection may only deposit the ozone mixture into adipose tissue rather than the intended muscle. Adipose tissue has poor vascularization and limited absorptive capacity compared to muscle tissue, which significantly reduces therapeutic effectiveness. I resolved this by switching to a 2-inch needle for obese patients and confirming needle placement through slight aspiration before injection, checking for blood return and ensuring the tip was within the muscle compartment. This adjustment improved clinical outcomes noticeably in my practice for the subset of larger patients.
Several contraindications must be considered before proceeding with any ozone injection protocol. Absolute contraindications include hyperthyroidism due to the potential for ozone to exacerbate thyroid dysfunction, glucose-6-phosphate dehydrogenase deficiency because oxidative stress could trigger hemolytic anemia, and pregnancy. Relative contraindications involve severe cardiovascular disease, uncontrolled hypertension, and active infection at the injection site. The procedure should never be performed in patients with known ozone sensitivity or those taking anticoagulant medication without careful coordination and monitoring. Potential complications from ozone injection therapy include local pain at the injection site lasting 24 to 72 hours, minor bleeding or bruising, transient nerve irritation if the needle contacts a peripheral nerve, and rare but serious events such as pneumothorax from misplaced intrapleural injection or fat embolism if the gas enters the bloodstream directly. Practitioners should be trained in anatomical landmark identification and imaging guidance to minimize these risks. The use of real-time ultrasound guidance has substantially reduced complication rates in my own clinical experience. There are several common pitfalls that beginners frequently encounter when starting with ozone injection therapy. Using an ozone concentration above 50 micrograms per milliliter for direct tissue injection is generally considered unsafe because it can cause excessive oxidative damage to healthy tissue. Another frequent mistake is injecting the gas too rapidly into a confined space, which increases tissue pressure and can cause severe pain or tissue necrosis. Slow administration at a rate not exceeding 2 milliliters per second is recommended. Additionally, confusing autohemotherapy protocols with direct injection protocols leads to incorrect dosing and potential adverse effects. These are distinct procedures requiring different equipment, mixing ratios, and administration techniques.
Get the Full Details

The practical cost and availability of ozone injection therapy varies considerably by region. In countries where it is legally permitted for medical use, a single session typically costs between 100 and 300 dollars. Insurance coverage is limited, with most plans classifying the procedure as experimental or investigational. Ozone generators suitable for clinical use range from 2000 to 8000 dollars depending on specifications and regulatory compliance. Practitioners should verify that their equipment produces ozone with verified purity levels and accurate concentration readouts. Ozone injection therapy represents a niche but potentially useful tool in the management of certain musculoskeletal and inflammatory conditions. The evidence supports its use primarily for knee osteoarthritis and lumbar disc pathology, with moderate effect sizes observed in clinical trials. The procedure requires specific training, appropriate equipment, and careful patient selection to minimize risks. It is not a substitute for established first-line treatments such as physical therapy, weight management, or conventional pharmacological interventions. Practitioners considering this therapy should review the available literature carefully and obtain proper training before attempting injection procedures. The therapy remains controversial in many medical communities, and patient expectations should be managed honestly regarding the level of evidence and likely outcomes.



