
Why Most Pain Assessment Tools Fail in Advanced Dementia
I spent seven years working in geriatric neurology before moving into palliative care, and the thing that always trips people up is the assumption that a validated scale is enough on its own. It isn't. Pain in dementia doesn't follow the same patterns it does in intact patients. A person in moderate-to-severe stages may not be able to tell you where it hurts, what it feels like, or even that they're in pain at all. So you have to read them instead of asking them. The tools exist, but their utility depends entirely on who is using them and how often they actually get retrained. I'll walk through the ones that matter, the ones that don't, and the specific workflow I use when a resident scores zero on everything but still looks like they're in pain.
Pain Assessment Tools For Dementia: The Ones Worth Using
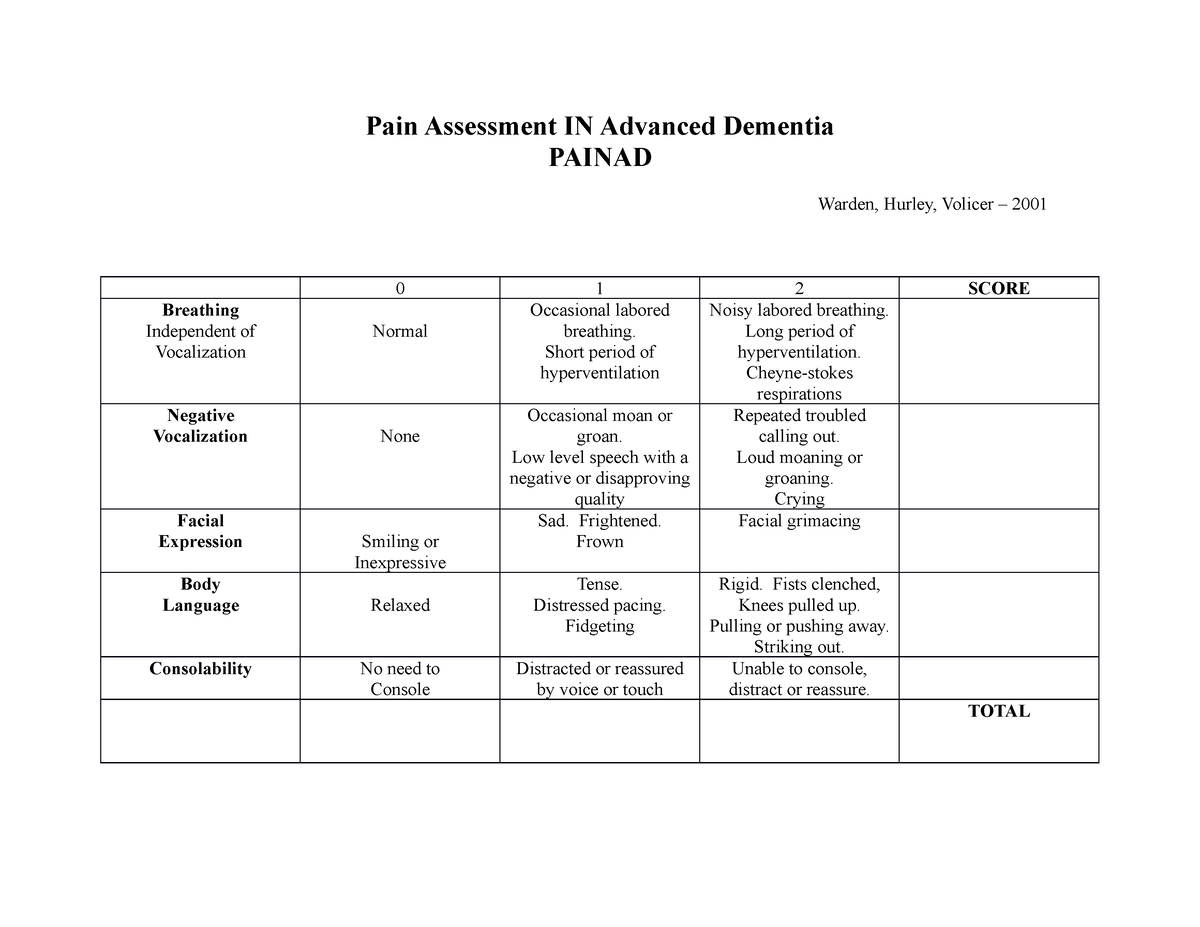
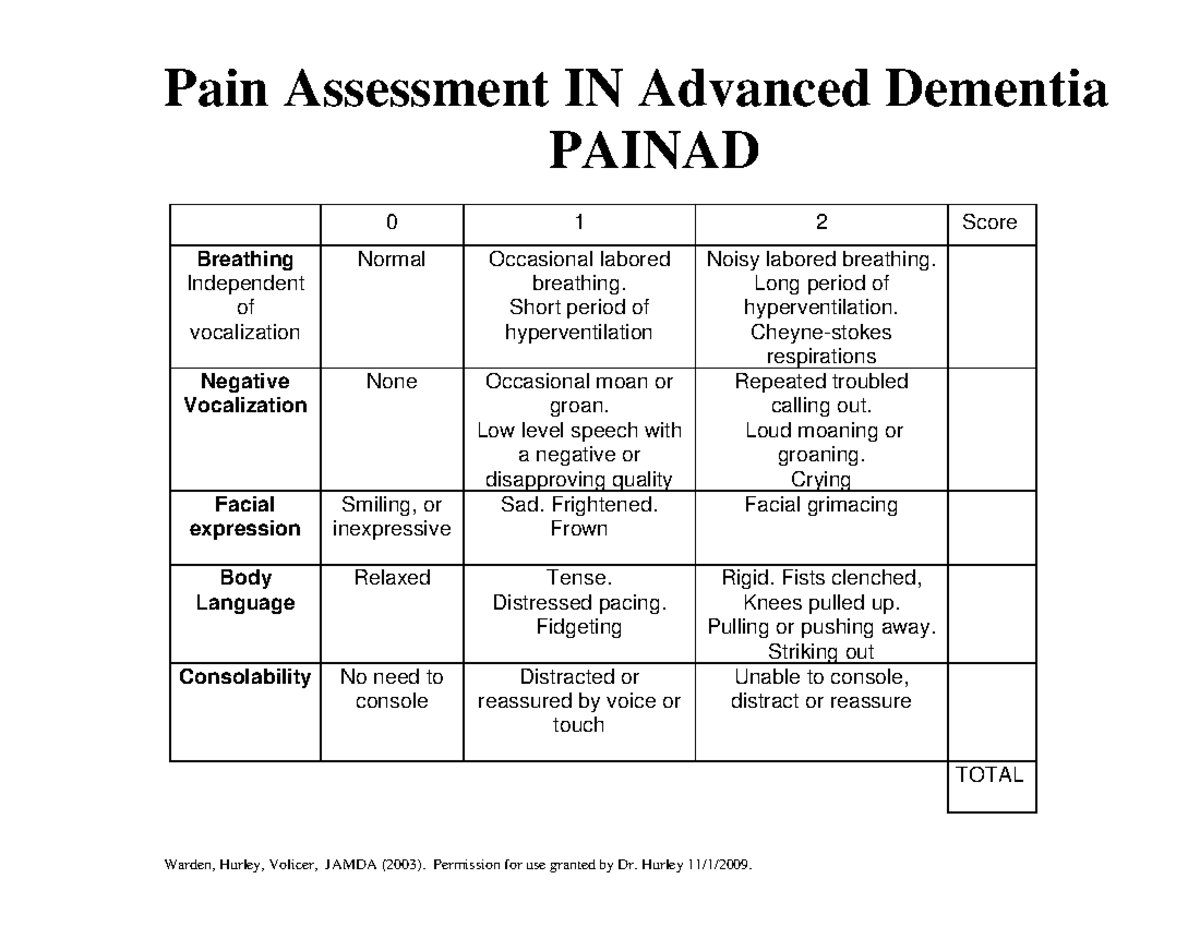
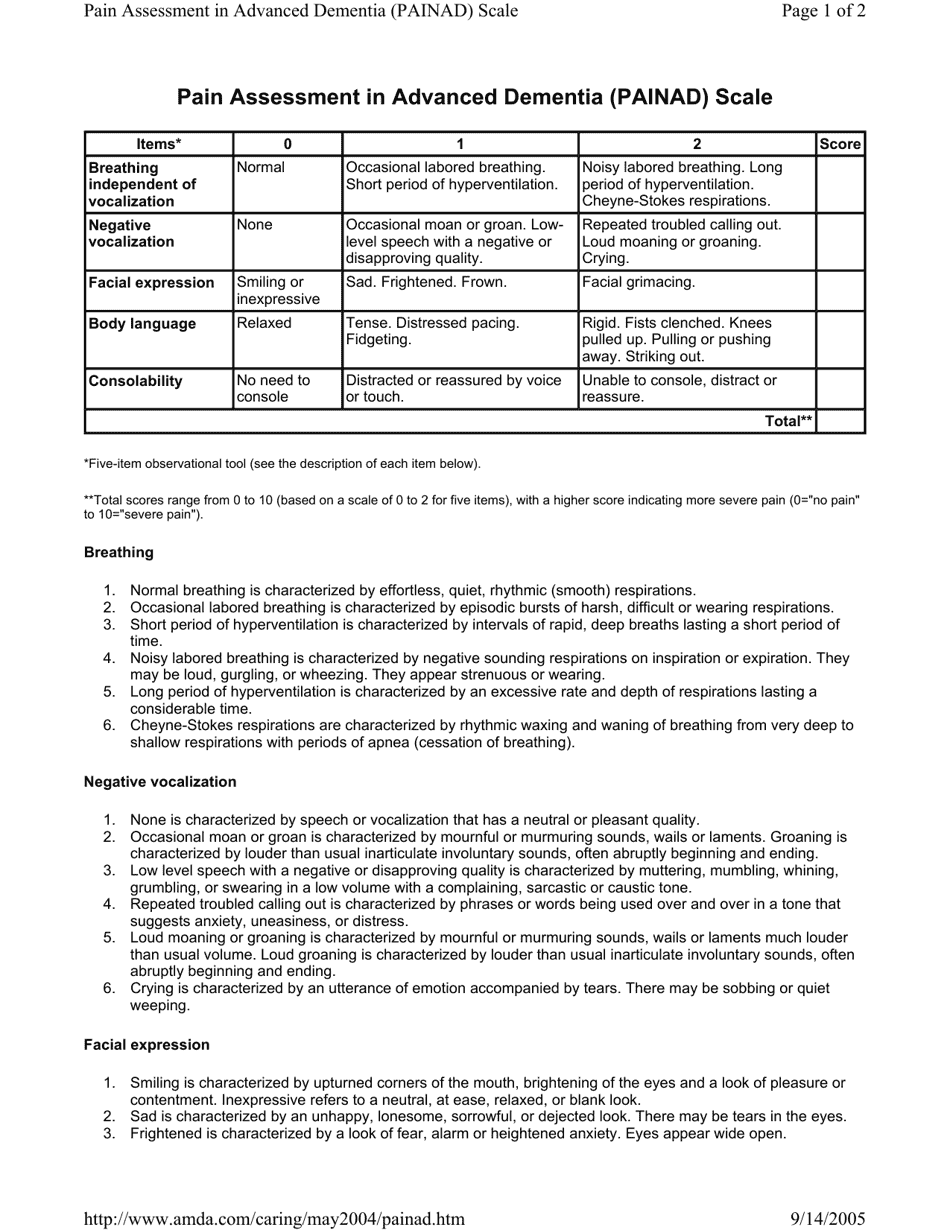
There are really three that hold up under scrutiny. The rest are either too vague for clinical use or require training levels that most facilities can't sustain. PAINAD (Pain Assessment in Advanced Dementia) is the workhorse here. Five items: breathing, negative vocalization, facial expression, body language, and consolability. Each scored 0 to 2, total range 0 to 10. A score of 0 to 1 means no apparent pain. 2 to 4 is mild. 5 to 7 is moderate. 8 to 10 is severe. The scoring takes about two minutes per observation window, and you're supposed to observe during and after a care activity like a bath or repositioning, not just walk by the door. That detail matters more than most people realize because a relaxed resident sitting quietly in a chair will score differently than the same resident being turned. Abbey Pain Scale is Australian in origin but widely adopted. Six items: breathing patterns, vocalization, facial expression, body language, behavioral changes, and physical changes. Also 0 to 12 range. It was designed specifically for end-stage dementia where nonverbal communication is the only reliable signal. The physical changes category captures things like rigidity, tremor, or restlessness that aren't captured in PAINAD. I use both together sometimes, cross-referencing the results. When they disagree, I trust the Abbey scale's behavioral and physical change categories more in my experience.
POS Pain Assessment Tool (Palliative Care Outcome Scale) is less commonly discussed in the US but very strong for residential settings. It focuses on pain, psychological distress, and communication. The pain subscale alone runs five items and captures quality and intensity of pain behaviors. It's better for tracking over time rather than snapshot decisions. If you're documenting a medication adjustment across weeks, POS gives you a clearer longitudinal picture than PAINAD ever will.
Get the Full Details
What Beginners Miss About These Scales
The biggest mistake I see is treating the score as a diagnosis. It's not. It's a signal. A PAINAD score of 3 after a wound dressing change could mean pain, it could mean agitation from the smell of antiseptic, it could mean the resident is confused by the disruption to routine, or it could mean nothing if that's their baseline behavior during care activities. Context is the variable nobody factors in. Another thing people get wrong is timing. Most scales are designed to be used proactively, not reactively. You assess during painful procedures, not two hours after the resident has been sedated with a PRN benzodiazepine because they wouldn't cooperate. I've seen this happen repeatedly. A staff member calls pain management because the resident is grimacing and pulling at lines, but the resident was given lorazepam six hours earlier for "agitation." The grimacing is now a residual drug effect, not uncontrolled pain. The score is garbage in that moment. Then there's the issue of baselines. Every resident has a behavioral baseline. Some are naturally restless. Some have chronic facial expressions that look like distress but aren't. I had a resident, male, late 80s, stage 3B Alzheimer's, who always frowned during morning care. Not because of pain. Just his face. His PAINAD scores were consistently 4 or 5 every single morning until I stopped scoring his facial expression category at all and relied on the other four. That dropped his scores to 1 or 2 and we stopped escalating analgesics for what looked like uncontrolled pain but was actually just his resting face. That decision changed his medication regimen completely and cut his opioid use roughly in half over three months.
When the Tools Break Down Completely
Let me be blunt about the limitations because nobody else does. PAINAD and Abbey have poor sensitivity in residents with Parkinson's disease, stroke-related facial paralysis, or advanced bulbar dysfunction. If someone can't change their facial expression due to neurological damage, the facial expression item becomes noise. You're scoring nothing or scoring artifacts of their condition as pain signals. In those cases, the body language and consolability items carry disproportionate weight, which biases the total score upward regardless of actual pain presence. Delirium is another scenario where these tools fail. Acute confusional state produces agitation, vocalization, restlessness, and resistance to care. It looks exactly like severe pain on a PAINAD or Abbey scale. I've seen residents scored at 9 or 10, pumped full of opioids, and then the delirium resolves and they're left confused from sedation with no actual pain problem. The correct move in delirium is to treat the underlying cause first. Pain assessment comes after the delirium is managed, not before. The third hard limit is advanced cachexia. In residents who are profoundly depleted, muscle rigidity and tremor from metabolic causes mimic the body language items on these scales. They're lying rigid because they're malnourished and electrolyte-imbalanced, not because they're in pain. Checking basic labs before scoring can save you from a cascade of unnecessary medication changes.
My Actual Workflow
Here's how I handle it in practice, step by step. First, I establish a behavioral baseline during a calm, non-procedural moment. Not during care. Not during meals. Just a quiet period where the resident is alert enough to show their normal state. I spend five minutes observing. What does their face look like at rest? How do they hold their hands? What vocalizations are normal for them? This takes longer than filling out a form but it makes everything that follows more accurate. Second, I use PAINAD during and immediately after care activities that are likely to provoke pain. Repositioning, wound care, transfers, bathing. I score all five items. I note the exact timing. I record what activity preceded the score.
Third, I layer in Abbey Pain Scale for residents with significant communication barriers or end-stage disease. The physical changes category catches things PAINAD misses. I document both scores side by side. Fourth, I compare the scores against the baseline. If the score is elevated but consistent with the baseline behavior during the same activity, I don't escalate treatment. I note it and monitor. If the score is elevated above baseline, I investigate. Is there a new wound? A change in bowel habits? A recent fall? A UTI? Pain in dementia residents is often a symptom of something else entirely. Fifth, I reassess after any intervention. Not after thirty minutes. After twenty. Opioids in this population can take longer to peak but the sedation hits faster. I need to know whether the pain responded or whether we're just sedating the behavior without treating the source.
The One Tool Nobody Talks About Much
Peggy Miller's Pain Assessment Checklist for Persons with Advanced Dementia is the most comprehensive tool I've encountered but also the most labor-intensive. Twenty-one items across four domains: verbalizations, facial expressions, body language, and interpersonal changes. It takes about eight minutes to complete and requires training that most facilities skip. But it caught pain in a resident that PAINAD and Abbey both missed. The person was making no vocalizations, had a relatively neutral face, and wasn't restless. But they were withdrawing from all social interaction and refusing to make eye contact. The interpersonal changes domain in Miller's tool captured that. We found a pressure injury that had been missed because the resident's lack of verbal complaint made everyone assume there was no pain. That case alone convinced me that having one additional tool in your kit is worth the extra time. Document the activity during which you assess. A score without context is nearly useless for decision-making. "PAINAD 6" tells you nothing. "PAINAD 6 during log-roll at 10:15 AM after overnight rest" tells you everything you need to know about whether this is procedure-related pain or constant pain. Train the entire team on the same tool. I've seen facilities where some nurses use PAINAD and others use Abbey, and then the care notes become incomparable. The tool doesn't matter as much as consistency. Pick one for routine use and add a second one only for complex cases.
Don't score during PRN medication peaks or troughs. If someone received midazolam four hours ago, wait. If they're due for their next dose in two hours, wait. Score at a point where the pharmacological noise is minimized. Check for constipation before escalating analgesics. It sounds basic but it's the most common reversible cause of elevated pain scores in this population that gets missed. A bowel program adjustment resolved elevated PAINAD scores in three residents I worked with last year before we changed a single pain medication. Use a pain diary alongside the tools. Scores are snapshots. A diary showing that scores rise every day at 4 PM during the shift change is telling you something about staffing or routine disruptions that a single number never will.
Download and Implementation Notes
Most of these tools are freely available and not proprietary. PAINAD was published in the Journal of Gerontological Nursing and is in the public domain. The Abbey Pain Scale is available through the Abbey Center at Charles Sturt University. The POS toolkit is published by the Palliative Care Research Unit in the UK. None of them require licensing fees. The real bottleneck isn't access to the forms. It's the training and the consistent application. I'd estimate that a facility starting from scratch typically needs about six weeks of weekly competency checks before staff scores are reliable and consistent with each other. After that, monthly calibration sessions keep drift to a minimum. Without that structure, the tools become exercises in documentation rather than clinical decision-making. I've also found that digital scoring through a simple EHR-integrated form cuts documentation time from about four minutes per assessment to under sixty seconds, which actually increases compliance. The best tool in the world is worthless if nobody uses it because it's too cumbersome to fill out properly.


